This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan PPP2CB chromogenic IHC in paraffin sections using the reported cytoplasmic and occasional nuclear staining pattern (HPA tissue IHC). Start antibody A07661 at 1:100–1:200 (datasheet: A07661 IHC), and interpret staining with the reported cross-gene caution in mind (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic; nuclear in some tissues (HPA tissue IHC) | |
| Staining pattern | Widespread cytoplasmic staining; nuclear in some tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep paraffin-section fixation consistent. (standard IHC practice; not target-specific) | |
| Caveat | Staining may include protein from another gene (HPA tissue IHC) | |
| Regulation | No specific expression regulator reported (UniProt) | |
| Isoform / epitope | No isoforms or cleavage; intracellular epitope access matters (UniProt) |
The catalog antibody’s IHC-P protocol is paired with one published PPP2CB protocol using paraffin-embedded colon cancer sections (PMC8377503 methods).
| Sample | Paraffin-embedded rat kidney tissue; fixative not specified (datasheet A07661) |
| Fixation | Image fixative and duration unreported (datasheet A07661); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-PPP2CB, 1:100-1:200 (datasheet A07661) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | PPP2CB-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression and nuclear expression in several tissues. No signal in the no-primary control. |
PPP2CB is a soluble protein found in the cytoplasm and nucleus, with centromere and spindle-pole localization during mitosis (UniProt P62714 topology and subcellular location). In paraffin-section IHC, expect broad cytoplasmic staining and nuclear staining in some tissues, including strong staining in several epithelial, hematopoietic, and neuronal cell populations (HPA tissue IHC). Interpret intensity cautiously: HPA rates the tissue pattern Approved, with medium agreement with RNA data and a warning that staining may reflect more than one gene (HPA tissue IHC).
| Clear cytoplasmic staining, with nuclei stained in some cells. | This fits the broad tissue pattern reported by HPA and the cytoplasmic and nuclear locations annotated by UniProt (HPA tissue IHC; UniProt P62714 subcellular location). Judge the signal against cell morphology and adjacent background; nuclear staining need not be equally prominent in every tissue (HPA tissue IHC). |
| Strong staining in adrenal gland or appendix glandular cells, bone marrow hematopoietic cells, or cortical neurons. | These are documented high-staining cell populations and useful positive tissue references (HPA tissue IHC: High in each listed population). A strong result supports assay performance, but staining alone cannot establish that the antibody distinguishes PPP2CB from other gene products (HPA tissue IHC: multi-gene caution). |
| A sharp cell-surface rim or predominantly extracellular deposit replaces the expected intracellular signal. | That distribution conflicts with the annotated cytoplasmic and nuclear locations and the absence of a transmembrane segment (UniProt P62714 subcellular location and topology). Treat it as suspect; check section morphology, precipitate, and control slides before assigning it to PPP2CB. |
| Strong signal appears chiefly in cardiomyocytes, skeletal myocytes, or soft-tissue fibroblasts. | HPA reports Low staining in those populations, not absence (HPA tissue IHC). Compare them with a documented high-staining population in the same run. Unexpected relative intensity warrants checks for nonspecific binding or endogenous detection activity; it does not by itself prove cross-reactivity. |
| Diffuse chromogen covers cells and extracellular space, or a documented high-staining tissue has no signal. | A uniform haze obscures compartment scoring; absence in a high-staining reference weakens confidence in a negative test section (HPA tissue IHC: High reference populations). Use control slides to distinguish background or detection failure from a plausible biological difference; neither appearance alone identifies the cause. |
| Cell population and reference tissue | HPA reports High staining in adrenal and appendix glandular cells, bone marrow hematopoietic cells, and several neuronal populations, but Low staining in cardiomyocytes, skeletal myocytes, and soft-tissue fibroblasts (HPA tissue IHC). Use these as relative intensity references; Low is not a negative control. |
| Compartment and cell-cycle state | Cytoplasm and nucleus are annotated locations; centromere localization is reported in prometaphase but not anaphase, and spindle-pole localization occurs during mitosis (UniProt P62714 subcellular location). Those transient structures should not be required in routine sections, where mitotic cells may be scarce. |
| Antibody-level interpretation | Two listed antibodies have Approved IHC status, while the tissue summary has medium agreement with RNA data and cautions that staining may reflect more than one gene (HPA antibodies; HPA tissue IHC). A plausible pattern supports interpretation but does not establish PPP2CB-specific recognition. |
| Target structure and processing | PPP2CB has no transmembrane segment, signal peptide, or propeptide; its annotated chain spans residues 1–309 (UniProt P62714 topology and processing). These facts support intracellular interpretation, but they do not establish an antibody epitope or predict antigen-retrieval conditions. |
| Fixation and antigen retrieval | Target-specific fixation sensitivity and retrieval requirements are unreported in the supplied UniProt and HPA records. For paraffin-section IHC, evaluate retrieval using the antibody’s IHC protocol and a documented high-staining tissue; do not infer a PPP2CB-specific fixation effect from tissue intensity. |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal appears in the test section or a documented high-staining reference. | The run may have failed at retrieval, primary-antibody binding, or chromogenic detection; the slide alone cannot distinguish these causes. | Check the positive control and reagent sequence, then review the catalog antibody’s IHC-P conditions before adjusting retrieval or primary dilution (HPA tissue IHC: High reference populations). |
| The whole section has a uniform haze or extracellular chromogen. | Background from incomplete blocking, washing, or detection chemistry can obscure intracellular staining (standard IHC practice). | Review the no-primary control, wash and blocking steps, and chromogen development; score only signal resolved within identifiable cells (standard IHC practice). |
| Strong staining is concentrated in a population HPA calls Low. | Relative intensity differs from the HPA reference; nonspecific binding or endogenous detection activity is possible, but Low does not mean absent (HPA tissue IHC). | Compare with a documented High population, inspect the no-primary control, and assess whether signal tracks the expected cytoplasmic or nuclear compartments (HPA tissue IHC; UniProt P62714 subcellular location). |
| Signal forms a membrane rim with little intracellular staining. | A dominant membrane pattern is difficult to reconcile with PPP2CB’s annotated locations and lack of a transmembrane segment (UniProt P62714 topology and subcellular location). | Inspect section edges and precipitate, compare control slides, and withhold a PPP2CB-positive call until an intracellular pattern is demonstrable. |
| Nuclear staining is absent, but cytoplasmic staining is clear. | HPA describes nuclear expression in several tissues rather than all tissues; UniProt also lists cytoplasmic localization (HPA tissue IHC; UniProt P62714 subcellular location). | Assess the cytoplasmic pattern and positive reference first. Record the nuclear result separately, without treating its absence alone as assay failure. |
| Does IF/ICC require the same visible balance of cytoplasmic and nuclear signal as IHC? | The HPA ICC-IF summary reports supported nucleoplasmic localization, while the tissue IHC summary reports broad cytoplasmic and some nuclear expression (HPA subcellular; HPA tissue IHC). | Interpret IF/ICC against its supported nucleoplasmic reference and IHC against the tissue pattern; use the separate IF/ICC guide for assay design (HPA subcellular; HPA tissue IHC). |
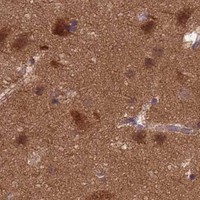
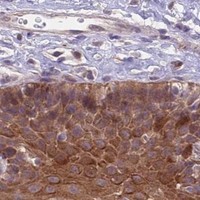
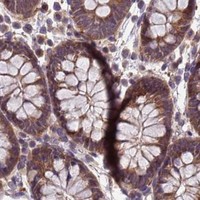
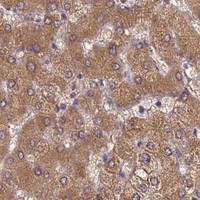


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: PPP2CB is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Use compartment, cell type, and matched controls to troubleshoot PPP2CB staining in paraffin sections; interpret tissue patterns cautiously because the reference antibody may recognize more than one gene (HPA).
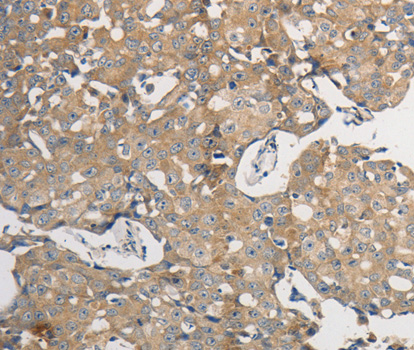
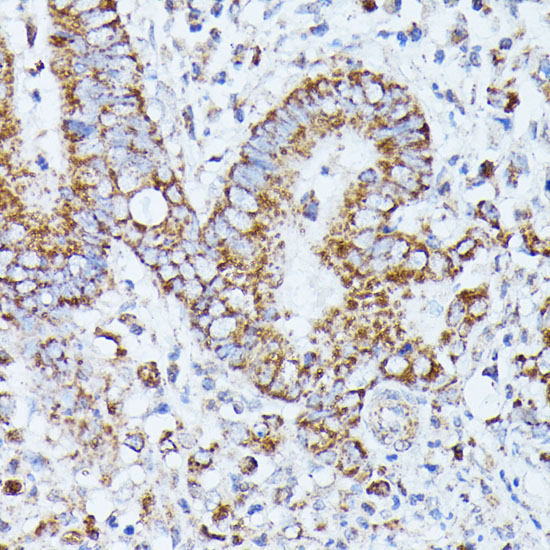
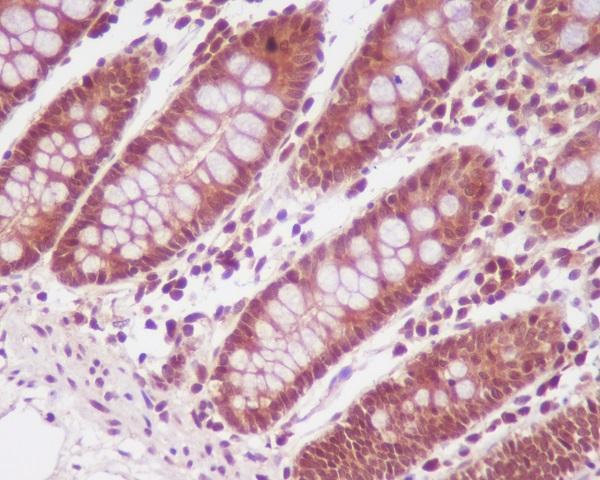
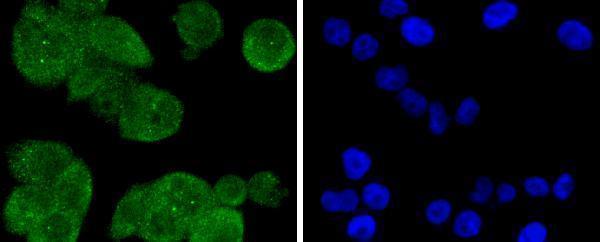
The catalog includes antibodies with IHC images from paraffin-embedded rat kidney, mouse kidney, human colon carcinoma, and human colon, plus an ICC image from PANC-1 cells (catalog image captions).
A07661 has IHC images from paraffin-embedded rat kidney, mouse kidney, and human colon carcinoma (A07661 image captions); M07661 has an IHC image from paraffin-embedded human colon (M07661 image caption). A07661-1 lists IHC and ICC applications and has an ICC image from PANC-1 cells fixed in paraformaldehyde (A07661-1 catalog; A07661-1 image caption).
Which to pick: For tissue IHC, choose A07661 when its rat kidney, mouse kidney, or human colon carcinoma examples match your sample (A07661 image captions), or M07661 for a rabbit monoclonal with a human colon example (M07661 catalog; M07661 image caption); both IHC captions report paraffin embedding but do not report the fixative (A07661 and M07661 image captions). For ICC, A07661-1 has an image from paraformaldehyde-fixed, permeabilised PANC-1 cells (A07661-1 image caption); for IF, A07661 and M07661 list that application, though their supplied figures show IHC (A07661 and M07661 catalogs; image captions). For broader listed species coverage, A07661-1 includes zebrafish alongside human, mouse, and rat, while its supplied figure documents ICC in PANC-1 cells (A07661-1 catalog; A07661-1 image caption).