PRDX1 / Peroxiredoxin-1 · IHC design guide

Design Immunohistochemistry for PRDX1

Plan PRDX1 staining in paraffin sections using cytoplasmic expression in most tissues as the expected pattern (HPA tissue IHC). This guide covers fixation consistency, antibody selection and chromogenic staining controls.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PRDX1 (IHC for PRDX1): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9348, validated IHC image, and IHC protocol steps
Printable PRDX1 IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody PB9348, controls and protocol steps. Open the full PRDX1 IHC guide →

PRDX1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9348)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ Adipose tissue+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet PB9348); verify before use.
Caveat Endogenous peroxidase may raise marrow background (HPA tissue IHC; standard IHC practice)
Regulation Expression regulation unreported (UniProt)
Isoform / epitope No annotated isoforms; mature chain spans residues 2–199 (UniProt)
Section 1

Recommended PRDX1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: PB9348) is accompanied by three published PRDX1 IHC methods (PMC9353087; PMC5777129; PMC4327392).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded Human Mammary Cancer tissue; fixative not specified (datasheet PB9348)
FixationImage fixative and duration unreported (datasheet PB9348); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9348); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9348)
Primary antibodyRabbit anti-PRDX1, 0.5-1μg/ml (datasheet PB9348)
Primary incubationOvernight at 4 °C (datasheet PB9348)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet PB9348)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPRDX1-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: PB9348); use each article’s stated conditions when reproducing its method.
Section 2

What Is the Expected PRDX1 Staining Pattern?

In paraffin-section IHC, expect predominantly cytoplasmic PRDX1 staining across many tissues, including high staining in bone-marrow hematopoietic cells, splenic red-pulp cells, and thyroid glandular cells (HPA: cytoplasmic in most tissues; High in these cells). PRDX1 has no transmembrane segment or signal peptide (UniProt Q06830 topology and processing). Treat this as an expected pattern, not a universal positive result: HPA rates its tissue-IHC evidence Approved, with medium consistency and pending external verification (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining in bone-marrow hematopoietic cells, splenic red-pulp cells, or thyroid glandular cells (HPA: High in these cells).This matches the reported compartment and high-staining examples (HPA: tissue IHC). Compare stained cells with their neighbors; HPA's High label describes those cell populations, not every cell in the section (HPA: tissue IHC).
Predominantly nuclear staining, or staining confined to cell borders, with little cytoplasmic signal.The compartment differs from the reported tissue-IHC pattern (HPA: cytoplasmic in most tissues). Check morphology, counterstain, and control staining before calling it PRDX1; compartment mismatch raises concern for artefact or nonspecific detection (general IHC practice).
Strong staining in adipocytes, cardiomyocytes, soft-tissue fibroblasts, or vaginal squamous cells (HPA: Not detected in these cells).These are reported negative cell populations, so strong staining there warrants a cross-reactivity or endogenous-detection check (HPA: tissue IHC; general IHC practice). A negative call applies to the named cells, not necessarily every other cell in those tissues (HPA: tissue IHC).
Color spreads evenly over cells and surrounding section, obscuring cytoplasmic boundaries.A diffuse, non-cell-specific deposit does not reproduce HPA's cytoplasmic pattern (HPA: tissue IHC). Compare a no-primary control and inspect blocking, washing, and detection chemistry as general IHC troubleshooting steps (general IHC practice).
No staining in the expected cells of an otherwise interpretable positive-control section.Absence in bone-marrow hematopoietic cells, splenic red-pulp cells, or thyroid glandular cells conflicts with HPA's High examples (HPA: tissue IHC). Check antibody, retrieval, detection, and control performance before treating the specimen as biologically negative (general IHC practice).
💡Expected PRDX1 appearanceCall the result concordant when staining is chiefly cytoplasmic and high in the specified bone-marrow, splenic red-pulp, or thyroid glandular cells; isolated dominant nuclear or border staining, or strong staining in HPA-negative cell populations, warrants investigation (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Which cells provide the clearest tissue-IHC comparison?HPA reports High staining in bone-marrow hematopoietic cells, splenic red-pulp cells, and thyroid glandular cells; Medium staining in appendix and breast glandular cells, bronchial respiratory epithelium, caudate glia, and cerebellar granular-layer cells (HPA: tissue IHC). Score the specified cells and compartment, because tissue-wide intensity can obscure cell-level disagreement (general IHC practice).
How firm is the reference pattern?The tissue-IHC profile is Approved, with medium agreement between antibody staining and RNA expression and external verification pending (HPA: reliability). HPA lists one rabbit polyclonal and one mouse monoclonal antibody as IHC Approved; that status alone does not establish an Enhanced validation designation (HPA: antibody validation).
Does PRDX1 topology support a surface pattern?UniProt places PRDX1 in the cytoplasm and reports no signal peptide or transmembrane segment (UniProt Q06830: subcellular location, topology, processing). Those annotations support an intracellular expectation; they do not identify the antibody epitope or establish any target-specific retrieval or fixation sensitivity (UniProt Q06830: topology and processing).
Does protein processing predict a separate staining compartment?UniProt reports no propeptide, a chain spanning residues 2–199, and no annotated isoforms (UniProt Q06830: processing and isoforms). Its melanosome annotation comes from mass spectrometry of melanosome fractions; that observation alone does not predict a distinct chromogenic tissue-IHC pattern (UniProt Q06830: subcellular location).
IF/ICC Q&A: Should mitochondrial fluorescence change the IHC call?HPA's ICC-IF summary calls the main location mitochondria, while its tissue-IHC profile says cytoplasmic expression in most tissues (HPA: subcellular ICC-IF; HPA: tissue IHC). Interpret the paraffin-section chromogenic result against the tissue-IHC profile; record the assay difference without assuming either observation is an error (HPA: assay-specific observations).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A high-expression reference section shows little or no cytoplasmic stain.A failed staining run is possible; HPA reports High staining in the named reference cells, but does not supply a PRDX1-specific fixation-sensitivity claim (HPA: tissue IHC).Confirm the correct cells are present, then check the IHC-validated antibody's stated IHC-P conditions, retrieval, dilution, and detection controls (general IHC practice).
The whole section is dark, including areas without plausible cellular signal.Diffuse deposit can reflect background from detection chemistry or incomplete blocking or washing (general IHC practice); it is unlike the reported cytoplasmic pattern (HPA: tissue IHC).Review a no-primary control, blocking and wash steps, and chromogen development; assess cell boundaries again after background is reduced (general IHC practice).
Only nuclei or sharply outlined cell borders are prominent.This compartment conflicts with HPA's cytoplasmic tissue-IHC profile (HPA: tissue IHC). It does not, by itself, identify the source of the mismatch.Verify cell morphology and the counterstain, compare a no-primary control, and repeat with an IHC-validated antibody if the pattern persists (general IHC practice).
A supposedly negative tissue still contains stained cells.HPA's Not detected calls name particular cell types, such as adipocytes and cardiomyocytes, rather than every cell in their tissues (HPA: tissue IHC).Identify the stained cell population before scoring a contradiction; investigate strong signal in the named negative cells with appropriate detection controls (HPA: tissue IHC; general IHC practice).
Weak staining in appendix, breast, or bronchus is scored as assay failure.HPA reports Medium staining in the specified glandular or respiratory epithelial cells, below its High examples (HPA: tissue IHC).Assess the stated cell population and cytoplasmic location, then compare a High-reference tissue processed in the same run before changing conditions (HPA: tissue IHC; general IHC practice).
Mitochondrial ICC-IF images appear inconsistent with diffuse cytoplasmic IHC.The location summaries come from different assays: mitochondria in ICC-IF and cytoplasm in most tissue IHC (HPA: subcellular ICC-IF; HPA: tissue IHC).For this chromogenic paraffin-section result, score the tissue-IHC cell and compartment pattern; keep the ICC-IF observation as assay-specific context (HPA: tissue IHC; HPA: subcellular ICC-IF).

Sample controls for PRDX1 IHC & IF

🧪Run thyroid gland first: glandular cells should stain (HPA: High in thyroid glandular cells). Use adipose tissue as the negative comparator; adipocytes should lack detectable staining (HPA: Not detected in adipocytes). On the thyroid slide, non-glandular cells without specific DAB signal should appear counterstained, but the supplied HPA data do not establish an internal PRDX1-negative cell type (HPA: thyroid glandular cells High).
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PRDX1 in A-431, U-251MG, U2OS, with annotated localisation: Mitochondria (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only), rabbit IgG isotype, and PRDX1-knockout biological controls where matched material is available (selected-SKU caption: rabbit primary antibody). Block endogenous peroxidase and check background in thyroid glandular cells before interpreting DAB signal (HPA: thyroid glandular cells High; selected-SKU caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected-SKU paraffin-section caption does not state a fixative (selected-SKU caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 is documented, but retrieval dependence and whether frozen sections or IF are easier are unreported (selected-SKU caption: heat retrieval in EDTA, pH 8.0). Endogenous thyroid peroxidase may complicate chromogenic interpretation in the chosen tissue; assess signal against the peroxidase-blocked controls (HPA: High in thyroid glandular cells; selected-SKU caption: HRP/DAB detection).

HPA tissue IHC evidence for PRDX1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Spleen Cells in red pulp High Protein (IHC) HPA →
Thyroid gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Vagina Squamous epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced PRDX1 IHC Tips

Troubleshoot PRDX1 staining in paraffin sections by checking retrieval, compartment, controls, and cell-specific scoring before interpreting chromogenic signal.

What retrieval conditions should I try when PRDX1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet PB9348). The selected paraffin-section example used this retrieval before incubation with 1 μg/ml primary antibody overnight at 4°C (caption PB9348). If staining remains weak, vary heating and cooling time on adjacent sections while keeping the buffer, antibody concentration, and detection steps constant (standard IHC practice). Include a positive-control section and a section processed without primary antibody in each run (standard IHC practice). Compare cellular signal with tissue background before increasing retrieval intensity, since excessive heating can damage morphology and make scoring unreliable (standard IHC practice).
Could fixation explain weak or uneven PRDX1 staining?
PRDX1-specific sensitivity to fixation is unknown from the supplied evidence (caption PB9348: fixative not stated). The selected image documents a paraffin-embedded section but gives no fixative, so its staining cannot establish how PRDX1 responds to fixation duration or fixative type (caption PB9348). Record those variables for each specimen and compare sections processed together before attributing differences to protein abundance (standard IHC practice). If staining is uneven, inspect morphology and compare deeper sections to assess whether processing or tissue damage tracks the weak areas (standard IHC practice). Keep retrieval at EDTA pH 8.0 during that comparison (datasheet PB9348).
Which compartments should contain convincing PRDX1 staining?
Expect predominantly cytoplasmic staining across many tissue cell types (HPA tissue IHC: cytoplasmic expression in most tissues; UniProt Q06830: cytoplasm). PRDX1 has no annotated transmembrane segment, so an exclusively sharp membrane outline warrants scrutiny (UniProt Q06830 topology). UniProt also reports PRDX1 in melanosome fractions, while HPA subcellular imaging lists mitochondria as its approved location; those observations do not establish a single exclusive compartment in paraffin sections (UniProt Q06830 subcellular; HPA subcellular). Compare suspicious puncta with cell morphology and a control section processed without primary antibody (standard IHC practice). Score the compartment you observe explicitly rather than treating all brown signal as equivalent (standard IHC practice).
How should I assess an unexpected staining pattern if the antibody epitope is unspecified?
The supplied record lists 0 PRDX1 isoforms, but it does not specify the PB9348 epitope (UniProt Q06830 isoforms; caption PB9348). PRDX1 has a thioredoxin domain spanning residues 6–165 and reported modified residues, including phosphoserine at 32 (UniProt Q06830 domains and modified residues). Without an epitope map, neither modification-dependent recognition nor a specific retrieval effect can be assigned to this antibody (supplied epitope evidence: unspecified). Check whether the pattern persists across adjacent sections and follows expected cellular morphology before interpreting it biologically (standard IHC practice). If available, compare with an independently validated PRDX1 antibody recognizing a documented different epitope (standard IHC validation practice).
How can I follow up an IHC pattern with multiplex IF?
Use IF as a separate validation experiment: the PB9348 example establishes paraffin-section chromogenic staining, while HPA reports ICC/IF images in A-431, U-251MG, and U2OS cells (caption PB9348; HPA subcellular). Pair PRDX1 with a marker for the cell population implicated by the IHC result, and confirm that each marker works in the chosen specimen (standard multiplex IF practice). Choose fluorophores after measuring specimen autofluorescence, placing the weaker signal in a cleaner spectral channel (standard IF practice). Because PRDX1 is intracellular and lacks a transmembrane segment, use permeabilisation appropriate for an intracellular epitope and verify it against antibody instructions (UniProt Q06830 topology and subcellular; standard IF practice). Include single-stain and no-primary controls to assess bleed-through and background (standard multiplex IF practice).
How do I reduce diffuse DAB or nonspecific PRDX1 staining?
First compare the stained section with a no-primary control and inspect whether brown deposit follows cells or spreads through damaged tissue (standard IHC practice). The selected PB9348 example used 10% goat serum blocking, 1 μg/ml primary antibody overnight at 4°C, and DAB development (caption PB9348). Optimise blocking, washes, and primary concentration one variable at a time while retaining the documented EDTA pH 8.0 retrieval as the starting condition (caption PB9348; standard IHC practice). Apply a peroxidase block before HRP detection to assess endogenous enzyme contribution (standard chromogenic IHC practice). Interpret persistent diffuse staining cautiously, since HPA reports cytoplasmic PRDX1 expression in most tissues (HPA tissue IHC).
What is a defensible way to quantify PRDX1 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic compartment before scoring, consistent with the reported broad cytoplasmic tissue pattern (HPA tissue IHC). For intensity-based analysis, record the percentage of cells at each prespecified intensity and calculate an H-score; report the scoring scale alongside results (standard IHC quantification practice). Alternatively, report percent positive cells or positive-cell density per mm² when intensity is unreliable (standard IHC quantification practice). Normalise cell counts to the number of eligible cells, or area measurements to viable tissue area, using the same exclusion rules for every section (standard IHC quantification practice). Keep imaging, DAB development, and thresholds consistent across batches and document control performance (standard IHC quantification practice).
When should I doubt a strong PRDX1-positive signal?
Question staining confined to a sharp membrane outline, given the reported cytoplasmic pattern and lack of a transmembrane segment (HPA tissue IHC; UniProt Q06830 topology). Check cell identity: HPA reports high staining in bone-marrow hematopoietic cells and spleen red-pulp cells, but no detection in adipocytes or cardiomyocytes (HPA tissue IHC). Edge-heavy deposits, staining limited to necrotic areas, or signal retained without primary antibody support an artefactual explanation (standard IHC interpretation practice). A peroxidase block and no-primary control help assess endogenous enzyme and detection background with HRP/DAB (standard chromogenic IHC practice). Treat an unexpected compartment or cell type as provisional until controls and an independent validation method support it (standard IHC validation practice).
Boster reagents

Best PRDX1 / Peroxiredoxin-1 IHC Antibodies

Anti-PRDX1 antibodies have IHC images from human, mouse and rat tissues, plus IF images from human cells (catalog image captions).

Real IHC data IHC analysis of Peroxiredoxin 1 using anti-Peroxiredoxin 1 antibody (PB9348). Peroxiredoxin 1 was detected in a paraffin-embedded section of Human Mammary Cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-Peroxiredoxin 1 Antibody (PB9348) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Peroxiredoxin 1/PRDX1 Antibody ®
Cat # PB9348
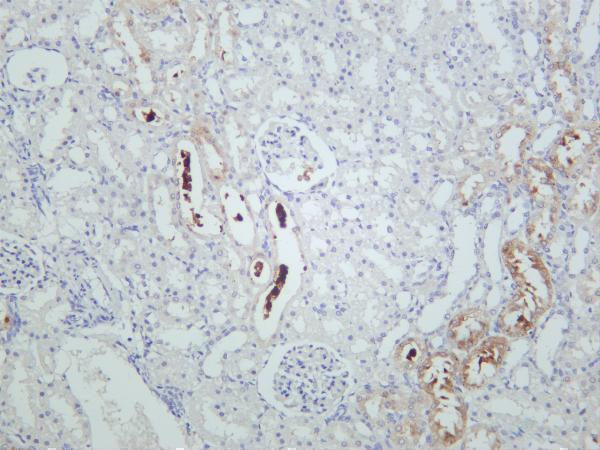
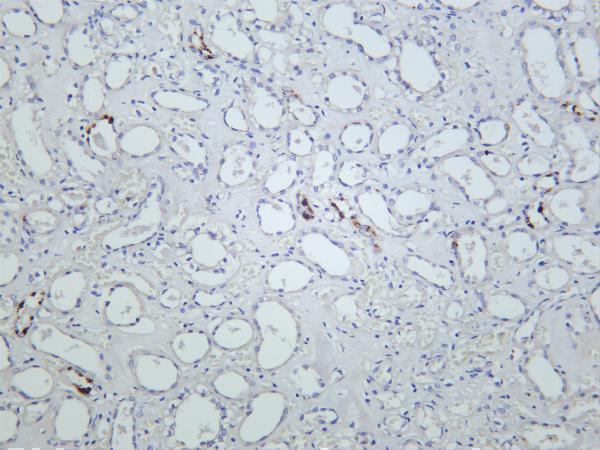
Real IHC data Rat kidney was stained with anti-Peroxiredoxin 1 rabbit antibody
Anti-Peroxiredoxin 1 Rabbit Monoclonal Antibody
Cat # M01845-3

PB9348 has IHC images from paraffin sections of human mammary cancer, mouse brain and rat brain, and IF images from HeLa and U20S cells (catalog image captions). M01845-3 has IHC images from rat kidney, human kidney and human thyroid; IF is listed as an application without a supplied IF image (catalog image captions; catalog applications).

Which to pick: For tissue IHC across human, mouse and rat, choose PB9348: its IHC captions document paraffin sections in all three species, with the fixative unreported (PB9348 IHC image captions). For IF/ICC, choose PB9348 because its application list includes both and its IF captions show human cell staining (PB9348 applications; PB9348 IF image captions). M01845-3 is a monoclonal alternative with listed human, mouse and rat reactivity and IHC/IF applications, but its IHC captions do not report tissue processing or fixative (M01845-3 catalog description; M01845-3 applications; M01845-3 reactivity; M01845-3 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q06830 (PRDX1_HUMAN, Peroxiredoxin-1).
  2. Human Protein Atlas. PRDX1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PRDX1 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. PRDX1 antibody validation summary (2 antibodies).
  5. The immunohistochemical detection of peroxiredoxin 1 and 2 in canine spontaneous vascular endothelial tumors. The Journal of veterinary medical science 2022 — PMC9353087.
  6. Peroxiredoxin 1 expression in active ulcerative colitis mucosa identified by proteome analysis and involvement of thioredoxin based on immunohistochemistry. Oncology letters 2018 — PMC5777129.
  7. Peroxiredoxin 1 promotes pancreatic cancer cell invasion by modulating p38 MAPK activity. Pancreas 2015 — PMC4327392.
  8. PRDX1 is a Tumor Suppressor for Nasopharyngeal Carcinoma by Inhibiting PI3K/AKT/TRAF1 Signaling. OncoTargets and therapy 2020 — PMC7501964.
  9. PubMed PMID:8496166 — UniProt-cited evidence.
  10. PubMed PMID:8026862 — UniProt-cited evidence.
  11. PubMed PMID:19054851 — UniProt-cited evidence.