PSMD4 / 26S proteasome non-ATPase regulatory subunit 4 · IHC design guide

Design Immunohistochemistry for PSMD4

Plan PSMD4 staining in paraffin sections with the catalog antibody at 2–5 μg/ml (datasheet A03544-1). Use nuclear and cytoplasmic staining in most tissues as the reference pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PSMD4 (IHC for PSMD4): expected localisation Nuclear and cytoplasmic in most tissues (HPA tissue IHC), antibody A03544-1, validated IHC image, and IHC protocol steps
Printable PSMD4 IHC protocol sheet — expected localisation Nuclear and cytoplasmic in most tissues (HPA tissue IHC), antibody A03544-1, controls and protocol steps. Open the full PSMD4 IHC guide →

PSMD4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic in most tissues (HPA tissue IHC)
Staining pattern Nuclear and cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03544-1)
Positive control ⓘ Caudate+4 more · see all
Negative control ⓘ Heart muscle+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03544-1)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation No specific regulator in the supplied record (UniProt)
Isoform / epitope 2 isoforms; epitope coverage unspecified (UniProt)
Section 1

Recommended PSMD4 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A03544-1) with three published PSMD4 paraffin-section methods (PMC8797679; PMC8463577; PMC5995171).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung adenocarcinoma tissue; fixative not specified (datasheet A03544-1)
FixationImage fixative and duration unreported (datasheet A03544-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03544-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03544-1)
Primary antibodyRabbit anti-PSMD4, 2-5 μg/ml (datasheet A03544-1)
Primary incubationOvernight at 4 °C (datasheet A03544-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03544-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPSMD4-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Nuclear and cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A03544-1); the published methods also document citrate-based retrieval (PMC8463577; PMC5995171).
Section 2

What Is the Expected PSMD4 Staining Pattern?

Expect nuclear and cytoplasmic PSMD4 staining in most tissues (HPA tissue IHC: Enhanced reliability; medium consistency with RNA). Neuronal cells in caudate, cerebral cortex and hippocampus, and testicular Leydig cells are useful high-staining references (HPA tissue IHC: High). PSMD4 has no transmembrane segment (UniProt P55036 topology), so a membrane-only pattern needs scrutiny.

What am I looking at on my slide?
Nuclear and cytoplasmic staining in the expected cells, with clear cell boundaries and limited background.This fits the tissue IHC profile (HPA: nuclear and cytoplasmic expression in most tissues). Compare intensity within the same run: neuronal cells in caudate, cortex and hippocampus and Leydig cells are High, whereas adipocytes are Medium (HPA tissue IHC). HPA reports Enhanced reliability, with medium consistency between staining and RNA; intensity is a reference pattern, not an absolute cutoff.
Strong staining confined to plasma membranes, with little nuclear or cytoplasmic signal.Treat this as a questionable compartment pattern: PSMD4 has no transmembrane segment (UniProt P55036 topology), and HPA describes nuclear and cytoplasmic tissue staining (HPA tissue IHC). Check morphology, controls and detection background before assigning it to PSMD4 (standard IHC practice). A membrane outline alone does not establish target localization.
Prominent signal in a cell population expected to be unstained, such as skeletal myocytes.HPA reports PSMD4 as Not detected in skeletal myocytes (HPA tissue IHC). Unexpected signal may reflect cross-reactivity or endogenous detection activity, but a negative HPA observation is not proof of universal absence. Inspect a reagent-only control and compare the suspect cells with expected positive cells on the same run (standard IHC practice).
Diffuse color covers tissue, empty spaces or many cell types without recognizable nuclear or cytoplasmic detail.This pattern limits interpretation because HPA's reported tissue pattern is cellular and nuclear/cytoplasmic (HPA tissue IHC). Nonspecific antibody binding, incomplete blocking or detection background are possible causes (standard IHC practice). Judge the slide against a negative reagent control and a known-positive section processed together (standard IHC practice).
No convincing signal in neuronal cells of caudate, cerebral cortex or hippocampus, or in Leydig cells.These are High-staining references in HPA tissue IHC (HPA: High in those cells). A blank result suggests a run-level problem before it supports a biological negative. Check section integrity, primary antibody application and detection controls (standard IHC practice); HPA's Enhanced rating does not guarantee every preparation will stain.
💡Expected PSMD4 appearanceCall a positive result when identifiable cells show nuclear and cytoplasmic chromogenic signal, especially High-staining neuronal or Leydig cells (HPA tissue IHC); isolated membrane rims or diffuse color without cellular detail warrant control review (UniProt P55036 topology; standard IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA records High neuronal staining in caudate, cortex and hippocampus and High Leydig-cell staining; cardiomyocytes and skeletal myocytes are Not detected (HPA tissue IHC). Use cell identity when interpreting a section: a low or negative reference cell does not substitute for a High positive control.
Evidence strengthThe tissue profile has Enhanced reliability but only medium consistency between antibody staining and RNA (HPA tissue IHC). HPA lists two rabbit antibodies with Enhanced IHC validation and one mouse antibody with Supported IHC validation (HPA antibodies). Interpret an unexpected pattern with the validation status of the antibody actually used.
Protein topology and processingUniProt lists no transmembrane segment, signal peptide or propeptide and describes a chain spanning residues 1–377 (UniProt P55036). These annotations support scrutiny of a membrane-only result; they do not predict antigen retrieval conditions or staining intensity.
Isoforms and epitope coverageUniProt lists Rpn10A and Rpn10E isoforms (UniProt P55036). No antibody epitope or isoform coverage is supplied here, so isoform-dependent staining cannot be inferred from a positive or negative section.
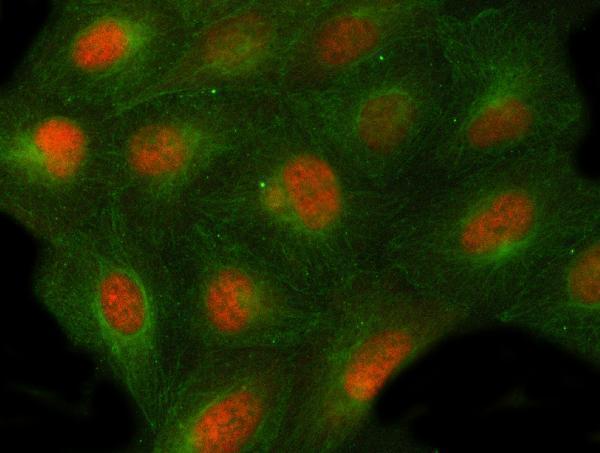
IF/ICC: what localization is expected?HPA reports mainly nucleoplasmic signal with additional cytosolic signal; both locations are approved (HPA subcellular ICC-IF). This answers the localization question for IF/ICC without treating an ICC image as an IHC-P protocol or requiring identical compartment intensity in tissue sections.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A High-reference cell is blank while the rest of the slide appears interpretable.The reference may have been misidentified, or staining may have failed locally; HPA reports High signal for the specified neuronal and Leydig cells (HPA tissue IHC).Confirm cell identity and tissue morphology, then compare another High-reference area stained in the same run (standard IHC practice). Record a genuine discordance rather than changing the HPA category.
The entire positive-control section is blank.A run-level failure of primary antibody application, retrieval or detection is possible (standard IHC practice); no PSMD4-specific retrieval requirement is supplied.Check reagent application, the catalog antibody's validated IHC-P instructions and detection controls; repeat with a High HPA reference tissue (HPA tissue IHC; standard IHC practice).
Broad brown signal appears on a negative reagent control.Detection chemistry or endogenous tissue activity may contribute signal independent of the primary antibody (standard IHC practice).Resolve the control signal using the detection system's blocking and control guidance before scoring PSMD4; reassess cellular localization after background is controlled (standard IHC practice).
The stain outlines membranes but spares nuclei and cytoplasm.This conflicts with HPA's nuclear/cytoplasmic tissue pattern and UniProt's lack of a transmembrane segment (HPA tissue IHC; UniProt P55036 topology).Compare a High-reference section and negative reagent control; inspect whether chromogen follows tissue edges or deposits outside cells (HPA tissue IHC; standard IHC practice).
Only weak signal is seen in liver hepatocytes or pancreatic exocrine cells.HPA calls both cell populations Low, so weak staining can be compatible with the reference profile (HPA tissue IHC).Check a High-reference cell population in the same run before calling the assay insensitive; score the named cell population rather than the whole tissue (HPA tissue IHC; standard IHC practice).
IF/ICC appears nucleoplasmic while tissue IHC appears nuclear and cytoplasmic.Both observations fit their respective HPA summaries: nucleoplasm is the main ICC-IF location, with additional cytosol, and tissue IHC reports both compartments (HPA subcellular ICC-IF; HPA tissue IHC).Assess each preparation against its own HPA pattern and its own negative control; investigate only if the observed compartment falls outside those patterns (HPA; standard IHC practice).

Sample controls for PSMD4 IHC & IF

🧪Run cerebral cortex first: neuronal cells should stain strongly (HPA: High in cerebral cortex neuronal cells). Use skeletal muscle myocytes as the negative tissue (HPA: Not detected in skeletal muscle myocytes); on the positive slide, cells lacking specific signal should show counterstain alone, although HPA does not identify a reliably negative cell type within cerebral cortex (HPA: cerebral cortex row).
Positive control tissue: Caudate (Neuronal cells, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PSMD4 in A-431, U-251MG, U2OS, MCF-7, PC-3, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only), concentration-matched rabbit IgG isotype, and a PSMD4-knockout biological control where available (selected SKU caption: rabbit primary antibody). Block endogenous peroxidase for chromogenic IHC; if examining cerebral cortex by IF, assess tissue autofluorescence, including lipofuscin (standard IHC/IF practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected SKU tissue-IHC caption does not state its fixative (selected SKU caption). Heat retrieval with EDTA at pH 8.0 was used for a paraffin section, but retrieval dependency is unreported (selected SKU caption). HPA documents ICC-IF localization mainly in the nucleoplasm with additional cytosolic signal, but the supplied evidence does not establish that IF or frozen sections are easier than paraffin IHC (HPA: subcellular).

HPA tissue IHC evidence for PSMD4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum GLUC cells - nucleus High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Hippocampus Neuronal cells High Protein (IHC) HPA →
Testis Leydig cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells Not detected Protein (IHC) HPA →
Ovary Ovarian stroma cells Not detected Protein (IHC) HPA →
Skeletal muscle Myocytes Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced PSMD4 IHC Tips

Troubleshoot PSMD4 staining in paraffin sections by checking retrieval, detection controls and cell-level localisation before interpreting chromogenic signal.

How should I adjust retrieval when PSMD4 staining is weak or patchy?
Start with heat-mediated EDTA retrieval at pH 8.0 for paraffin sections (datasheet A03544-1). The selected tissue-IHC image used that retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (A03544-1 tissue-IHC caption). If signal is weak, vary heating time in a small section series while holding antibody concentration and detection constant (standard IHC practice). Assess tissue damage and background alongside signal, since harsher retrieval can make an apparent gain difficult to interpret (standard IHC practice). If still needed, test another retrieval buffer as a documented fallback and compare it directly with EDTA pH 8.0 (standard IHC practice).
Could fixation explain weak PSMD4 staining in my paraffin sections?
PSMD4-specific sensitivity to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not state a fixative (A03544-1 tissue-IHC caption). Record the fixative and fixation duration for each specimen, then compare sections processed and stained together (standard IHC practice). Use the documented EDTA pH 8.0 retrieval and 2 μg/ml primary incubation as a starting reference, while checking whether morphology remains intact (A03544-1 tissue-IHC caption; standard IHC practice). If staining differs between processing batches, examine batch controls before attributing the difference to PSMD4 biology (standard IHC practice). Do not infer fixation tolerance from the protein's domains or tissue staining profile (UniProt P55036; HPA tissue IHC).
Is nuclear PSMD4 staining plausible when I also see cytoplasmic signal?
Yes: tissue IHC reports nuclear and cytoplasmic expression in most tissues, while subcellular imaging places PSMD4 mainly in the nucleoplasm and additionally in the cytosol (HPA tissue IHC; HPA subcellular). Score nuclear and cytoplasmic DAB signal separately against the counterstain rather than treating either compartment as automatically nonspecific (standard IHC practice). PSMD4 has no annotated transmembrane segment, so a crisp membrane-only outline needs independent validation (UniProt P55036 topology). Compare cells within intact tissue regions and include a no-primary control to identify deposits or endogenous detection signal (standard IHC practice). If one compartment changes across cases, confirm that tissue processing and scoring thresholds are matched (standard IHC practice).
Could the antibody miss a PSMD4 isoform or a modified epitope?
PSMD4 has 2 reported isoforms, Rpn10A and Rpn10E, but the supplied caption does not map this antibody's epitope (UniProt P55036; A03544-1 tissue-IHC caption). Its VWFA domain spans residues 5–188, and its ubiquitin-interacting motifs span 211–230 and 282–301 (UniProt P55036 domains). Reported phosphorylation includes residues 250, 253, 256, 266 and 358; none establishes an effect on this antibody's tissue staining (UniProt P55036 modified residues). If staining differs between specimens, request epitope information and compare an independently validated antibody where available (standard IHC practice). Keep retrieval and detection matched before interpreting a difference as isoform-specific (standard IHC practice).
How can I use IF to investigate an ambiguous PSMD4 IHC pattern?
Use IF as a separate validation experiment: PSMD4 is reported mainly in the nucleoplasm and additionally in the cytosol (HPA subcellular). Multiplex with a validated marker for the cell type under study, such as a neuronal marker when investigating neuronal staining, and inspect each channel separately (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and consider a far-red PSMD4 channel if the tissue has strong autofluorescence (standard IF practice). Permeabilise to allow antibody access to nuclear and cytosolic targets; PSMD4 has no transmembrane segment, and this antibody's epitope side is unspecified (UniProt P55036 topology; A03544-1 tissue-IHC caption). Optimise IF fixation and antibody concentration independently of the paraffin-section IHC conditions (standard IF practice).
What should I check when DAB staining obscures PSMD4-positive cells?
Compare a no-primary control with the PSMD4 slide to identify signal arising from secondary detection or endogenous peroxidase (standard IHC practice). The selected image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (A03544-1 tissue-IHC caption). If diffuse DAB remains, check the peroxidase block, washing, secondary-only control and chromogen development time (standard IHC practice). Titrate primary antibody against background while retaining the same retrieval and control sections (standard IHC practice). Do not score edge deposits, folds or necrotic areas as cellular PSMD4 staining (standard IHC practice).
How should I quantify PSMD4 across paraffin-section samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because PSMD4 may appear in nuclei and cytoplasm (HPA tissue IHC). For each compartment, record the percentage of positive cells and staining intensity, or use an H-score on a 0–300 scale with fixed intensity categories (standard IHC practice). Normalise positive-cell counts to the number of eligible cells; for spatial counts, report density per mm² of viable tissue (standard IHC practice). Exclude folds, section edges and necrosis using the same rules for every specimen (standard IHC practice). Keep retrieval, DAB development, imaging and threshold settings consistent, and report nuclear and cytoplasmic results separately (standard IHC practice).
How do I distinguish convincing PSMD4 staining from artefact?
Prioritise reproducible cellular nuclear or cytoplasmic staining, consistent with the reported tissue pattern, over isolated DAB deposits (HPA tissue IHC; standard IHC practice). Use cell identity as a check: neuronal cells and Leydig cells are reported high, whereas cardiomyocytes and skeletal-muscle myocytes are reported undetected in the listed HPA samples (HPA tissue IHC). These reference patterns guide comparison but do not establish a universal negative control, given the reported medium consistency between staining and RNA data (HPA tissue IHC). Treat membrane-only outlines, edge staining and necrotic deposits cautiously; PSMD4 has no transmembrane segment (UniProt P55036 topology; standard IHC practice). Check no-primary and peroxidase controls before calling diffuse chromogen a true positive (standard IHC practice).
Boster reagents

Best PSMD4 / 26S proteasome non-ATPase regulatory subunit 4 IHC Antibodies

A03544-1 has IHC data from human paraffin sections and IF data from human cells and tissue and rat tissue (catalog image captions); listed reactivity includes human, mouse and rat (catalog applications/reactivity).

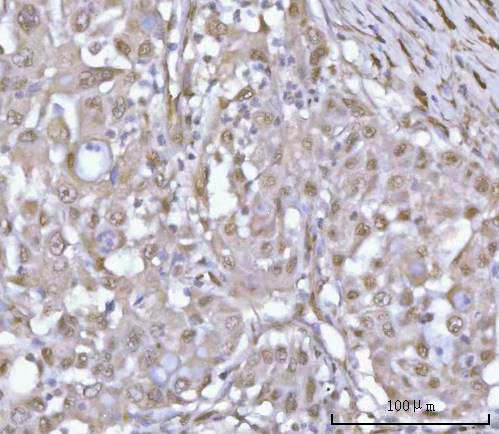
Real IHC data IHC analysis of PSMD4 using anti-PSMD4 antibody (A03544-1). PSMD4 was detected in a paraffin-embedded section of human lung adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PSMD4 Antibody (A03544-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PSMD4 Antibody ®
Cat # A03544-1

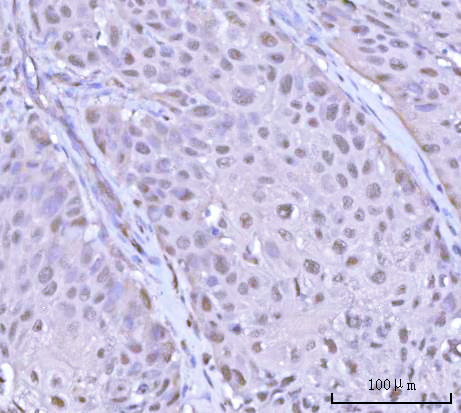
A03544-1 has IHC images from paraffin sections of human lung adenocarcinoma, urothelial carcinoma, lung cancer and liver cancer (catalog IHC image captions). The same SKU has IF images from U2OS cells, human intestinal cancer sections and rat brain sections (catalog IF image captions).

Which to pick: Choose A03544-1 for chromogenic IHC on paraffin sections: its lung adenocarcinoma image documents EDTA retrieval at pH 8.0, 2 μg/ml primary antibody and HRP/DAB detection (A03544-1 IHC image caption); the fixative is unreported (A03544-1 IHC image caption). For IF/ICC, A03544-1 is listed for both applications and has cell and tissue IF images at 5 μg/ml (catalog applications; A03544-1 IF image captions). For work across species, A03544-1 lists human, mouse and rat reactivity, while the supplied IF images show human and rat samples (catalog reactivity; A03544-1 IF image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P55036 (PSMD4_HUMAN, 26S proteasome non-ATPase regulatory subunit 4).
  2. Human Protein Atlas. PSMD4 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PSMD4 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the cytosol..
  4. Human Protein Atlas. PSMD4 antibody validation summary (3 antibodies).
  5. PSMD4 promotes malignant phenotypes and is associated with angiogenesis-related signaling and immune remodeling in hepatocellular carcinoma. Discover oncology 2026 — PMC13473052.
  6. Down-regulation of PSMD4 can attenuate autophagy, enhance the accumulation of intracellular ROS, and increase the sensitivity of epithelial ovarian cancer to carboplatin by inhibiting the NF-κB pathway. Translational cancer research 2021 — PMC8797679.
  7. Proteasome inhibition by bortezomib parallels a reduction in head and neck cancer cells growth, and an increase in tumor-infiltrating immune cells. Scientific reports 2021 — PMC8463577.
  8. PSMD4 is a novel therapeutic target in chemoresistant colorectal cancer activated by cytoplasmic localization of Nrf2. Oncotarget 2018 — PMC5995171.
  9. PubMed PMID:7657640 — UniProt-cited evidence.
  10. PubMed PMID:8641424 — UniProt-cited evidence.
  11. PubMed PMID:10921894 — UniProt-cited evidence.