PTK2B / Protein-tyrosine kinase 2-beta · IHC design guide

Design Immunohistochemistry for PTK2B

Plan PTK2B paraffin IHC with 2–5 μg/ml catalog antibody (datasheet A01066-1). Use high-staining fallopian tube ciliated cells and adipocytes with no detected staining as references, and score cytoplasmic and nuclear staining by cell type (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PTK2B (IHC for PTK2B): expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A01066-1, validated IHC image, and IHC protocol steps
Printable PTK2B IHC protocol sheet — expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC), antibody A01066-1, controls and protocol steps. Open the full PTK2B IHC guide →

PTK2B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear tissue staining (HPA tissue IHC)
Staining pattern Variable cytoplasmic and nuclear staining, mainly in brain and lymphoid tissue (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01066-1)
Positive control ⓘ Fallopian tube+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Expression varies by tissue and cell type (HPA tissue IHC)
Isoform / epitope 2 isoforms; no extracellular domain, so check epitope coverage (UniProt)
Section 1

Recommended PTK2B IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet: A01066-1) with published PTK2B staining methods from four articles (PMC2896956; PMC12575923; PMC12321221; PMC13226250).

Recommended immunohistochemistry (IHC-P) protocol parameters
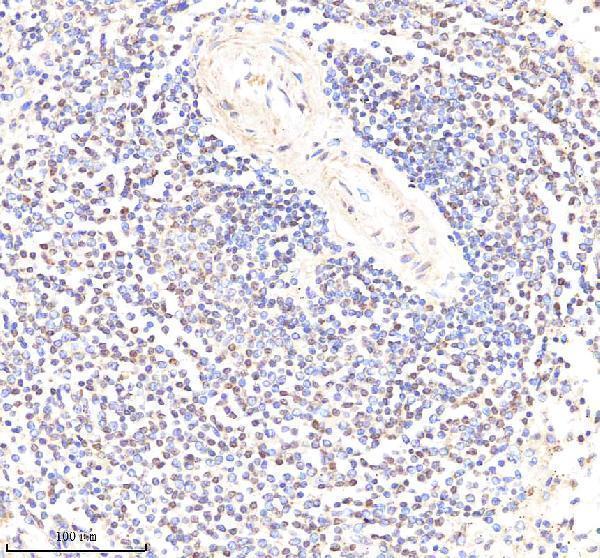
SampleParaffin-embedded human spleen tissue; fixative not specified (datasheet A01066-1)
FixationImage fixative and duration unreported (datasheet A01066-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01066-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01066-1)
Primary antibodyRabbit anti-PTK2B, 2-5 μg/ml (datasheet A01066-1)
Primary incubationOvernight at 4 °C (datasheet A01066-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01066-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPTK2B-positive staining in ciliated cells (cell body) of fallopian tube (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic and nuclear expression at variable levels in most cell types, mainly in the brain and lymphoid tissue. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A01066-1); optimize against tissue controls before adopting another antibody’s conditions (PMC13226250: citrate pH 6.0).
Section 2

What Is the Expected PTK2B Staining Pattern?

PTK2B staining may be cytoplasmic or nuclear in paraffin tissue sections, with variable intensity across cell types and prominent expression in brain and lymphoid tissue (HPA: tissue IHC profile; Approved, with medium consistency against RNA data). Membrane-associated staining is also plausible (UniProt Q14289: subcellular location). PTK2B has no transmembrane segment, so membrane signal does not imply an extracellular or membrane-spanning antigen (UniProt Q14289: topology).

What am I looking at on my slide?
Cytoplasmic staining in neurons or Purkinje cells, with some nuclear staining.This fits the variable cytoplasmic and nuclear tissue pattern (HPA: tissue IHC profile). Neuronal cells in caudate and cerebral cortex and Purkinje cells in cerebellum show Medium staining (HPA: tissue IHC). Score the named cell population rather than the whole section.
Signal appears confined to a noncellular space or forms a sharp luminal rim.That location alone does not fit PTK2B's reported cellular locations (UniProt Q14289: subcellular location). Inspect the counterstain and adjacent cells before assigning a compartment; deposits and edge staining can mislead in chromogenic IHC (general IHC practice).
Strong staining appears in adipocytes or skeletal myocytes.These cell types were Not detected in the supplied tissue IHC observations (HPA: adipocytes; skeletal myocytes). Recheck cell identification and detection controls for cross-reactivity or endogenous activity (general IHC practice). A different specimen or antibody result needs independent validation.
A uniform haze obscures cell boundaries across the section.Diffuse haze cannot establish the reported cell-specific pattern (HPA: tissue IHC profile). Assess no-primary and detection controls, then review blocking, washing and chromogen development (general IHC practice). Do not score haze as weak PTK2B staining.
Neurons are unstained in cerebral cortex or caudate.Both sites have Medium neuronal staining in the supplied observations (HPA: tissue IHC). Confirm that the section contains identifiable neurons, then check a positive control and the IHC-validated antibody's stated conditions (general IHC practice). A negative run alone does not establish biological absence.
💡Expected PTK2B appearanceCall a result positive when identifiable neuronal or Purkinje cells show cellular cytoplasmic, sometimes nuclear, staining of roughly Medium intensity in the cited brain sections (HPA: tissue IHC); uniform haze or noncellular deposits are suspect (general IHC practice).
How each factor affects the staining
Cell and tissue selectionExpression varies by cell type (HPA: tissue IHC profile). Ciliated cell bodies in fallopian tube and basal cells in nasopharynx are High; neurons in cited brain regions are Medium (HPA: tissue IHC). Compare like cells when judging intensity.
Subcellular interpretationTissue IHC reports cytoplasmic and nuclear expression (HPA: tissue IHC profile). UniProt also lists perinuclear cytoplasm, membrane, focal adhesions and lamellipodia (UniProt Q14289: subcellular location). A single section need not display every listed location.
Antibody validationThree listed antibodies have Approved IHC status (HPA: antibody records HPA026091, HPA026276, CAB003850). This supports use of their reported IHC patterns as a reference; it does not identify the catalog antibody's epitope or establish that every antibody reproduces them.
Isoforms and modificationTwo isoforms and multiple phosphorylation sites are recorded (UniProt Q14289: isoforms; modified residues). The supplied evidence does not map the catalog antibody's epitope, so total-PTK2B and site-specific staining cannot be equated without antibody documentation.
IF/ICC Q&AQ: Should IF/ICC show the same compartment pattern? A: HPA supports plasma membrane and cytosol in ICC-IF (HPA: subcellular summary). Tissue IHC also reports nuclear staining (HPA: tissue IHC profile); interpret each application using its own evidence.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a brain positive controlThe expected neuronal signal may be missed if the relevant cells are absent, or the run may have failed (HPA: Medium neuronal staining in cerebral cortex and caudate; general IHC practice).Verify neurons on the counterstain and inspect the positive control and detection reagents; use only retrieval and dilution conditions documented for the IHC-validated antibody (general IHC practice).
Only nuclei stain throughout the sectionNuclear PTK2B can occur, but a section-wide nuclear pattern without cell-type differences does not match the variable tissue profile (HPA: tissue IHC profile).Compare named cell populations with a no-primary control and check counterstain interpretation before scoring nuclear positivity (general IHC practice).
Unexpected signal in a stated negative cell populationAdipocytes and skeletal myocytes were Not detected in the supplied HPA observations; an unexpected positive may reflect cell misidentification, cross-reactivity or detection background (HPA: tissue IHC; general IHC practice).Confirm the cell type and repeat with appropriate detection controls; seek independent antibody evidence if the cellular signal persists (general IHC practice).
Weak signal in kidney tubulesLow staining is reported for kidney tubular cells, and UniProt describes low kidney protein levels (HPA: tissue IHC; UniProt Q14289: tissue specificity).Interpret against the named tubular cells and a brain positive control; do not treat weak kidney staining alone as a failed run (HPA: tissue IHC; general IHC practice).
Brown background across cells and tissue spacesNoncellular chromogen or endogenous detection activity can obscure the cellular pattern (general IHC practice).Inspect no-primary and detection controls, then review blocking, washing and development time before adjusting the staining run (general IHC practice).
An IF/ICC image disagrees with tissue IHCHPA supports plasma membrane and cytosol in ICC-IF, while tissue IHC reports cytoplasmic and nuclear expression (HPA: subcellular summary; tissue IHC profile).Use the evidence for the relevant application and specimen when assigning localisation; do not infer an IHC protocol or target-specific fixation effect from the ICC-IF pattern (general IHC practice).

Sample controls for PTK2B IHC & IF

🧪Run nasopharynx first and expect staining in basal cells (HPA: High in nasopharyngeal basal cells). Use adipose tissue adipocytes as the negative comparator (HPA: Not detected in adipocytes); on the positive slide, cells outside the basal layer that lack brown DAB signal are candidate internal negatives, but HPA does not establish them as PTK2B-negative (HPA: nasopharynx row identifies basal cells only).
Positive control tissue: Fallopian tube (Ciliated cells (cell body), HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PTK2B in A-431, U-251MG, U2OS, with annotated localisation: Plasma membrane (supported), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a host- and class-matched rabbit IgG isotype control (caption: rabbit primary and anti-rabbit secondary); use identically processed PTK2B-knockout material, if available, as a biological negative (standard IHC practice). Quench endogenous peroxidase and check for residual DAB signal, particularly if inflammatory cells are present in the nasopharyngeal section (standard chromogenic IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A01066-1 paraffin-section caption does not state the fixative (caption: fixative unreported). That caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required (caption: EDTA retrieval); the supplied evidence does not establish whether frozen sections or IF are easier. If inflammatory cells are present in nasopharyngeal tissue, endogenous peroxidase can produce misleading DAB signal; assess this with the no-primary control (standard chromogenic IHC practice).

HPA tissue IHC evidence for PTK2B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Fallopian tube Ciliated cells (cell body) High Protein (IHC) HPA →
Nasopharynx Basal cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Not detected Protein (IHC) HPA →
Ovary Follicle cells Not detected Protein (IHC) HPA →
Section 3

Advanced PTK2B IHC Tips

Troubleshoot PTK2B staining in paraffin sections by checking retrieval, cell type, compartment and controls before comparing signal across samples.

What retrieval conditions should I try when PTK2B staining is weak?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01066-1). The selected spleen example used that retrieval before overnight primary antibody incubation at 4°C, providing a direct starting point for this antibody (datasheet A01066-1). If staining remains weak, adjust heating duration in small increments while processing a positive control section alongside the specimen (standard IHC practice). Compare signal in expected cells with background and tissue integrity, since excessive retrieval can damage morphology and increase nonspecific staining (standard IHC practice). Record the heating method and duration for reproducible comparisons (standard IHC practice).
Could fixation explain weak or uneven PTK2B staining?
Target specific fixation sensitivity is unknown: the selected paraffin section caption does not state its fixative (datasheet A01066-1). Record the fixative, fixation duration and tissue thickness for each specimen, then compare sections processed under matched conditions (standard IHC practice). When staining varies, inspect morphology and compare a positive control processed in the same run before changing retrieval or antibody concentration (standard IHC practice). Avoid treating a weak result as proof of absent PTK2B, especially when fixation histories differ between samples (standard IHC practice). Keep fixation and retrieval records together so a repeat run can test the suspected processing difference (standard IHC practice).
Is nuclear PTK2B staining plausible, or should I expect only cytoplasm?
Nuclear staining is plausible because PTK2B is annotated in the nucleus as well as the cytoplasm, perinuclear region, membrane and focal adhesions (UniProt Q14289 localisation). Tissue IHC reports variable cytoplasmic and nuclear expression in many cell types, with an Approved reliability designation and medium consistency with RNA data (HPA tissue IHC). Evaluate nuclear and cytoplasmic signal separately within identified cell types, using the counterstain to define nuclei (standard IHC practice). Check whether membrane or peripheral staining fits the section's cell morphology; PTK2B can associate with the cell periphery and integrins (UniProt Q14289 localisation). A compartment pattern alone cannot establish antibody specificity (standard IHC practice).
How could isoforms or epitope choice change the staining pattern?
PTK2B has 2 annotated isoforms, while the supplied caption does not identify the antibody epitope or establish which isoforms it detects (UniProt Q14289 isoforms; datasheet A01066-1). Check the antibody's documented immunogen or epitope before interpreting discordant staining as an isoform difference (standard IHC practice). PTK2B contains a FERM domain at residues 39–359, a kinase domain at 425–683 and a focal adhesion targeting region at 870–1000 (UniProt Q14289 domains). It also has annotated phosphorylation sites, including Tyr 402, but this staining cannot be called phosphorylation specific without antibody evidence (UniProt Q14289 modified residues; standard IHC practice). Compare matched sections with an independently validated reagent if epitope coverage remains uncertain (standard IHC practice).
How should I adapt PTK2B localisation checks to multiplex IF?
For the separate IF/ICC workflow, pair PTK2B with a marker that identifies the expected cell population and score overlap within individual cells (standard IF practice). Choose fluorophores after checking tissue autofluorescence in an unstained section, and place the weaker signal in a cleaner detection channel (standard IF practice). PTK2B is found in cytosol and at the plasma membrane, with no transmembrane segment annotated; choose permeabilisation according to the documented antibody epitope and test access to intracellular epitopes (HPA subcellular; UniProt Q14289 topology; standard IF practice). Acquire single stain controls to assess channel bleed through before interpreting colocalisation (standard IF practice). Keep IF/ICC fixation and antibody conditions tied to direct IF/ICC validation rather than the paraffin IHC caption (standard IF practice).
How can I reduce diffuse or widespread brown background?
First compare a no primary control with the stained section to identify background from detection reagents or endogenous tissue activity (standard IHC practice). For HRP and DAB detection, include a peroxidase block and assess whether residual brown signal persists without primary antibody (standard IHC practice). The selected spleen example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase conjugated secondary for 30 minutes at 37°C (datasheet A01066-1). If background remains, optimise blocking, washes and primary concentration while retaining a positive control (standard IHC practice). Score cellular staining against the matched no primary control, particularly in lymphoid tissue where PTK2B expression is reported (HPA tissue IHC; standard IHC practice).
How should I quantify PTK2B staining across heterogeneous tissue? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because PTK2B staining can be cytoplasmic or nuclear and varies among cell types (HPA tissue IHC). For a defined population, report the percentage of positive cells and an intensity based H-score using the same thresholds across slides (standard IHC practice). If counting discrete positive cells, report density per mm² of viable tissue or of the annotated region, and give the denominator (standard IHC practice). Normalise measurements to the number of eligible cells or the analysed viable area, rather than comparing raw counts from unequal sections (standard IHC practice). Keep staining runs, imaging settings and thresholds consistent, and exclude folds or necrotic regions using predefined rules (standard IHC practice).
What distinguishes credible PTK2B staining from artefact?
Look for signal in intact cells with a plausible cytoplasmic, nuclear or peripheral pattern, rather than relying on brown colour alone (UniProt Q14289 localisation; HPA tissue IHC; standard IHC practice). PTK2B is reported in lymphoid tissue and neuronal populations, while HPA lists adipocytes as not detected; interpret each result within its identified cell population (HPA tissue IHC). Flag staining confined to section edges, folds or necrotic areas as suspect and compare those regions with adjacent intact tissue (standard IHC practice). A no primary control helps reveal residual endogenous peroxidase or detection background in a DAB workflow (standard IHC practice). Confirm a surprising compartment or cell type with appropriate controls before calling it a biological change (standard IHC practice).
Boster reagents

Best PTK2B / Protein-tyrosine kinase 2-beta IHC Antibodies

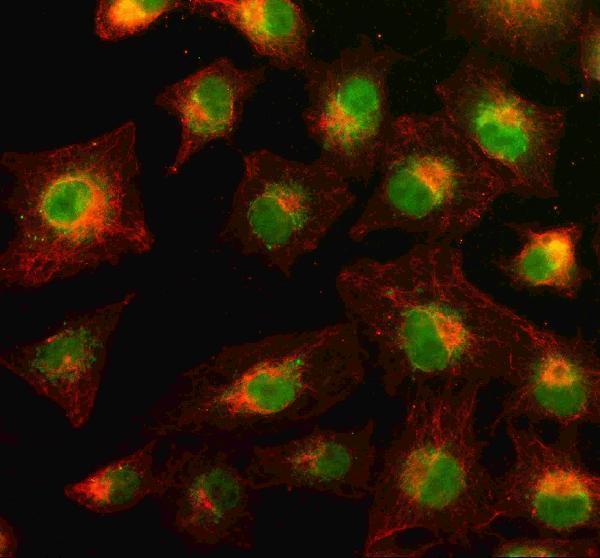
A01066-1 has IHC data from human spleen paraffin sections and IF/ICC data from A549 cells (catalog image captions). Its listed reactivity includes human, mouse and rat (catalog reactivity).

Real IHC data IHC analysis of PYK2/PTK2B using anti-PYK2/PTK2B antibody (A01066-1). PYK2/PTK2B was detected in a paraffin-embedded section of human spleen tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PYK2/PTK2B Antibody (A01066-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PYK2/PTK2B Antibody ®
Cat # A01066-1

A01066-1 is shown staining a human spleen paraffin section by chromogenic IHC (A01066-1 IHC image caption). The same SKU is shown staining A549 cells by IF/ICC (A01066-1 IF image caption).

Which to pick: Choose A01066-1 for paraffin-section IHC; its spleen example uses EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A01066-1 IHC image caption). Choose A01066-1 for IF/ICC in the separate guide because its A549 example uses 5 μg/ml primary antibody (A01066-1 IF image caption). For cross-species work, A01066-1 lists mouse and rat reactivity, while the supplied IHC image documents human tissue only; the IHC fixative is unreported (catalog reactivity; A01066-1 IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14289 (FAK2_HUMAN, Protein-tyrosine kinase 2-beta).
  2. Human Protein Atlas. PTK2B tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PTK2B subcellular location (ICC-IF): Localized to the plasma membrane and cytosol..
  4. Human Protein Atlas. PTK2B antibody validation summary (3 antibodies).
  5. Transcriptomic responses in mouse brain exposed to chronic excess of the neurotransmitter glutamate. BMC genomics 2010 — PMC2896956.
  6. Microwave dynamic therapy induces ferroptosis in colorectal cancer by targeting PTK2B to regulate STAT3-mediated GPX4 expression. Molecular biomedicine 2025 — PMC12575923.
  7. Human brain vascular multi-omics elucidates disease-risk associations. Neuron 2025 — PMC12321221.
  8. Unveiling novel macrophage-specific biomarkers in MASH through single-cell sequencing for diagnostic modeling. Journal of lipid research 2026 — PMC13226250.
  9. PubMed PMID:7544443 — UniProt-cited evidence.
  10. PubMed PMID:8838818 — UniProt-cited evidence.
  11. PubMed PMID:7673154 — UniProt-cited evidence.