PUF60 / Poly(U)-binding-splicing factor PUF60 · IHC design guide

Design Immunohistochemistry for PUF60

Plan PUF60 IHC in paraffin sections around its ubiquitous nuclear tissue staining (HPA tissue IHC). This guide identifies high-staining kidney proximal tubules and testis Leydig cells (HPA tissue IHC) and provides the catalog antibody’s IHC conditions (datasheet A05744-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PUF60 (IHC for PUF60): expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A05744-2, validated IHC image, and IHC protocol steps
Printable PUF60 IHC protocol sheet — expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A05744-2, controls and protocol steps. Open the full PUF60 IHC guide →

PUF60 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in tissue (HPA tissue IHC)
Staining pattern Ubiquitous nuclear staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A05744-2)
Positive control ⓘ Kidney+4 more · see all
Negative control ⓘ Nasopharynx
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Isoform 6 may alter colorectal cancer staining (UniProt)
Regulation Isoform 6 detected in colorectal cancer (UniProt)
Isoform / epitope 6 isoforms; antibody epitope coverage is unspecified (UniProt; datasheet A05744-2)
Section 1

Recommended PUF60 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is accompanied by published PUF60 methods for breast, ovarian and gastric tissue (PMC6340502; PMC10899302; PMC11704696).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A05744-2)
FixationImage fixative and duration unreported (datasheet A05744-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A05744-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A05744-2)
Primary antibodyRabbit anti-PUF60, 2-5 μg/ml (datasheet A05744-2)
Primary incubationOvernight at 4 °C (datasheet A05744-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A05744-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
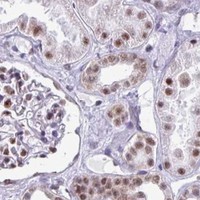
Expected resultPUF60-positive staining in proximal tubules (cell body) of kidney (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet: A05744-2); the breast and gastric protocols also report microwave retrieval in EDTA pH 8.0 (PMC6340502; PMC11704696).
Section 2

What Is the Expected PUF60 Staining Pattern?

PUF60 is a nuclear protein with no transmembrane segment (UniProt Q9UHX1 topology). In paraffin sections, expect predominantly nuclear staining across many cell types: HPA describes ubiquitous nuclear expression, with high staining in kidney proximal tubule cells and testis Leydig cells (HPA: tissue IHC). HPA rates the tissue profile Enhanced because antibody staining agrees well with RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Nuclear chromogen in proximal tubule cells or Leydig cells, with interpretable counterstained nuclei (HPA: High in both).This matches the expected compartment and offers useful positive tissue controls (UniProt Q9UHX1: nucleus; HPA: tissue IHC). Compare stained nuclei with surrounding cells; high is an HPA staining category, not a required score for every nucleus (HPA: tissue IHC).
Strong, predominantly membranous or cytoplasmic signal with little nuclear staining.The dominant compartment conflicts with PUF60's nuclear annotation and HPA's ubiquitous nuclear profile (UniProt Q9UHX1: nucleus; HPA: tissue IHC). Assess whether the distribution follows tissue edges, precipitate, or a detection reagent before interpreting it as PUF60 (standard IHC practice).
Prominent signal in nasopharyngeal basal cells, especially without convincing nuclear staining in positive controls.HPA reports PUF60 as not detected in those basal cells (HPA: nasopharynx). Consider cross-reactivity or endogenous detection activity; this cell-level observation does not establish that every cell in the tissue should be negative (HPA: tissue IHC; standard IHC practice).
Diffuse staining spans cells and stroma, obscuring nuclear boundaries.A broad haze cannot establish nuclear PUF60 localization (UniProt Q9UHX1: nucleus). Excess primary antibody, inadequate blocking or washing, and detection background are general IHC possibilities; check controls and staining conditions before scoring (standard IHC practice).
No nuclear signal in kidney proximal tubule cells or testis Leydig cells.This conflicts with HPA's high staining observations in those cells (HPA: kidney and testis). First check section integrity, antibody application, retrieval and detection using assay controls; absence alone cannot distinguish assay failure from sample differences (standard IHC practice).
💡Expected PUF60 appearanceCall a section positive when discrete nuclear chromogen is visible in expected cells, including HPA high proximal tubule or Leydig cells; diffuse stromal or dominant membrane staining is suspect (UniProt Q9UHX1: nucleus; HPA: tissue IHC).
How each factor affects the staining
Where should the signal be scored?Score nuclei within identifiable cells: UniProt places PUF60 in the nucleus, and HPA describes ubiquitous nuclear expression (UniProt Q9UHX1: subcellular location; HPA: tissue IHC). Its lack of a transmembrane segment gives no basis to expect a membrane pattern (UniProt Q9UHX1: topology).
Which tissues provide useful intensity contrasts?HPA reports high staining in kidney proximal tubule cells and testis Leydig cells, medium staining in adipocytes, and low staining in lung type I alveolar cells (HPA: tissue IHC). These are observed categories, not interchangeable tissue-wide intensity targets (HPA: tissue IHC).
How should a negative cell population be used?Nasopharyngeal basal cells are reported as not detected and can provide a cell-specific comparison (HPA: nasopharynx). HPA's overall profile is ubiquitous nuclear expression, so do not treat an entire tissue or every neighboring cell as a negative control (HPA: tissue IHC).
Does antibody validation guarantee every section?HPA lists IHC Enhanced for HPA052096 and HPA059714; HPA045733 has no IHC status in the supplied record (HPA: antibodies). The Enhanced tissue profile reflects agreement between staining and RNA data; verify the catalog antibody and local assay controls separately (HPA: tissue IHC; standard IHC practice).
Can isoforms change interpretation?UniProt lists six PUF60 isoforms and reports isoform 2 in colonic epithelium and colorectal epithelial cancer, while isoform 6 is detected in colorectal epithelial cancer but below detection in colonic epithelium (UniProt Q9UHX1: isoforms and tissue specificity). The supplied record gives no antibody epitope or isoform recognition data, so total IHC staining cannot assign an isoform (UniProt Q9UHX1; HPA: antibodies).
What does IF/ICC show?HPA's ICC-IF summary places PUF60 mainly in the nucleoplasm, with images listed for A-431, U-251MG, U2OS and MCF-7 (HPA: subcellular ICC-IF). This supports a nuclear localization comparison; IF/ICC procedure and scoring belong in its own guide (HPA: subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive control lacks nuclear staining.An assay step may have failed; HPA reports high staining in proximal tubule and Leydig cells (HPA: tissue IHC).Check antibody application, retrieval, detection reagents and counterstain against run controls; these are general IHC checks, not documented PUF60 fixation effects (standard IHC practice).
Nuclei are faint across a known-positive section.Weak contrast can reflect the staining workflow; HPA's high category applies to specified cells, not every cell in the section (HPA: tissue IHC; standard IHC practice).Compare the same cell type with the positive control, then review retrieval and antibody dilution using the assay instructions (standard IHC practice).
Cytoplasmic or membranous color dominates.That distribution disagrees with the expected nuclear pattern (UniProt Q9UHX1: nucleus; HPA: tissue IHC).Inspect a no-primary control and tissue morphology; review detection background before calling the signal specific (standard IHC practice).
Color appears in nasopharyngeal basal cells.HPA reports that specific population as not detected; cross-reactivity or endogenous detection activity is possible (HPA: nasopharynx; standard IHC practice).Compare nuclear localization and positive controls, then use a no-primary control to check detection-derived color (standard IHC practice).
The entire section has a diffuse brown haze.General causes include excess primary antibody, insufficient washing or blocking, and chromogen background (standard IHC practice).Review dilution, blocking, wash steps and chromogen development with the assay's control slides (standard IHC practice).
Adjacent cells differ in staining intensity.HPA reports different levels among named cell populations; tissue identity alone does not prescribe one intensity for all cells (HPA: tissue IHC).Identify each cell population and score nuclear signal separately; avoid inferring isoform identity from intensity alone (HPA: tissue IHC; UniProt Q9UHX1: six isoforms).

Sample controls for PUF60 IHC & IF

🧪Run kidney first: proximal tubule cell bodies should stain (HPA: High in proximal tubules). Run nasopharynx as the negative tissue, focusing on basal cells (HPA: Not detected in basal cells); cells without nuclear staining on the kidney slide can indicate background, but no kidney cell type is established as an internal biological negative (UniProt: nucleus; HPA: kidney row).
Positive control tissue: Kidney (Proximal tubules (cell body), HPA High)
Negative control tissue: Nasopharynx (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PUF60 in A-431, U-251MG, U2OS, MCF-7, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section, a host- and class-matched rabbit IgG isotype control, and a matched PUF60-knockout section where available (standard IHC control practice; caption: rabbit primary antibody). For kidney DAB staining, quench endogenous peroxidase and check for endogenous biotin if using avidin–biotin detection (standard IHC practice; HPA: kidney positive).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A05744-2 tissue-IHC caption does not state a fixative (selected-SKU caption). The caption uses heat retrieval in EDTA at pH 8.0 before paraffin-section IHC, but does not establish that retrieval is required; no supplied evidence establishes that frozen sections or IF are easier (selected-SKU caption). Kidney proximal tubules can show endogenous biotin signal with avidin–biotin detection, so assess that artefact if using that detection system (standard IHC practice; HPA: High in proximal tubules).

HPA tissue IHC evidence for PUF60

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Kidney Proximal tubules (cell body) High Protein (IHC) HPA →
Testis Leydig cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Nasopharynx Basal cells Not detected Protein (IHC) HPA →
Section 3

Advanced PUF60 IHC Tips

Troubleshoot PUF60 staining in paraffin sections by checking nuclear localisation, retrieval, controls and scoring against the selected antibody’s IHC evidence (HPA tissue IHC; datasheet A05744-2).

Which retrieval conditions should I try first for weak PUF60 staining?
Start with heat-mediated retrieval in EDTA, pH 8.0, for this paraffin-section assay (datasheet A05744-2). The selected antibody detected PUF60 after that retrieval, followed by 2 μg/ml primary antibody overnight at 4°C (datasheet A05744-2). If nuclear staining is weak, compare a longer heating interval with a matched control section, keeping detection and primary concentration fixed (standard IHC practice). A citrate buffer at pH 6.0 is a fallback to test only if the stated retrieval remains inadequate (standard IHC practice). Judge each condition by nuclear signal and tissue morphology together, because PUF60 is mainly nucleoplasmic (HPA subcellular; standard IHC practice).
How should I assess whether fixation is causing weak PUF60 IHC signal?
The selected image documents a paraffin-embedded section, but its fixative is unreported; PUF60-specific sensitivity to fixation is therefore unknown here (datasheet A05744-2). Compare sections with documented fixation histories using the same EDTA, pH 8.0 retrieval and 2 μg/ml primary concentration (datasheet A05744-2; standard IHC practice). Examine intact areas for nuclear signal alongside morphology, since tissue damage can make an apparent staining difference hard to interpret (HPA subcellular; standard IHC practice). If a section is weak, adjust retrieval on matched sections before attributing the result to fixation (standard IHC practice). Record fixation duration and processing conditions for any comparison (standard IHC practice).
Is cytoplasmic PUF60 staining credible when nuclear signal is weak?
Expect predominantly nuclear staining: UniProt places PUF60 in the nucleus, and the HPA reports mainly nucleoplasmic localisation (UniProt Q9UHX1; HPA subcellular). PUF60 has no transmembrane segment, so a membrane outline is not its expected pattern (UniProt Q9UHX1 topology). Compare nuclear and cytoplasmic signal in the same intact cells and check whether cytoplasmic colour persists when the primary antibody is omitted (standard IHC practice). A weak nuclear signal with broad cytoplasmic deposit warrants review of retrieval, antibody concentration and detection background before biological interpretation (standard IHC practice). Retain nuclear counterstain and examine multiple fields to distinguish nuclei from overlapping cell profiles (standard IHC practice).
Can this IHC assay distinguish PUF60 isoforms or modified epitopes?
Do not assign an isoform from this staining unless the antibody epitope and cross-reactivity are established; the supplied caption establishes tissue detection, not isoform selectivity (datasheet A05744-2). PUF60 has 6 listed isoforms and several modified residues, including phosphorylation and acetylation sites (UniProt Q9UHX1). Isoform 2 is reported in colonic epithelium and colorectal epithelial cancer, whereas isoform 6 is reported in colorectal epithelial cancer below detection in colonic epithelium (UniProt Q9UHX1). Compare epitope mapping with isoform sequences before interpreting differential staining (standard IHC practice). If selectivity remains unknown, report the result as PUF60 immunoreactivity and keep retrieval identical across specimens (standard IHC practice).
How can IF help check the compartment and cell type behind PUF60 IHC staining?
For a separate IF assay, expect mainly nucleoplasmic PUF60 signal rather than a membrane pattern (HPA subcellular; UniProt Q9UHX1 topology). In kidney, multiplex with a validated proximal-tubule marker and a nuclear counterstain to identify the cells reported as strongly stained by tissue IHC (HPA tissue IHC; standard IF practice). Choose a spectrally separated, preferably far-red fluorophore after inspecting unstained tissue for autofluorescence (standard IF practice). Because PUF60 is nuclear and has no transmembrane segment, use controlled permeabilisation after fixation to give antibody access to intracellular epitopes (UniProt Q9UHX1; standard IF practice). Optimise IF fixation and permeabilisation independently; the selected paraffin-section caption does not report a fixative (datasheet A05744-2; standard IF practice).
What should I check when DAB obscures PUF60 nuclear staining?
The selected paraffin-section assay used a peroxidase-linked secondary antibody and DAB chromogen, so evaluate both antibody-dependent and enzyme-related background (datasheet A05744-2; standard IHC practice). Include a no-primary control and an endogenous-peroxidase block, then compare deposit outside nuclei with the expected nucleoplasmic pattern (HPA subcellular; standard IHC practice). The reported workflow blocked sections with 10% goat serum and used 2 μg/ml primary antibody overnight at 4°C (datasheet A05744-2). If background persists, titrate primary antibody and shorten chromogen development on matched sections (standard IHC practice). Review tissue edges and damaged areas separately from intact tissue when judging specificity (standard IHC practice).
How should I score heterogeneous PUF60 nuclear staining across sections? ⚠ ANSWER MARKED FOR VERIFICATION
Score staining in defined cell populations and count only nuclei with credible signal, consistent with PUF60’s mainly nucleoplasmic location (HPA subcellular; standard IHC practice). Record the percentage of positive cells and nuclear intensity, or calculate an H-score from intensity categories 0–3 for a possible range of 0–300 (standard IHC practice). Normalise each result to the number of evaluable nuclei in the same compartment and apply one positivity threshold across the compared sections (standard IHC practice). Exclude necrotic areas and section edges using a prespecified rule (standard IHC practice). Report cell type separately because HPA tissue staining varies across cell populations (HPA tissue IHC).
How can I separate genuine PUF60 signal from staining artefact?
A credible result is predominantly nuclear in intact cells, consistent with UniProt and HPA localisation and the HPA’s ubiquitous nuclear tissue profile (UniProt Q9UHX1; HPA subcellular; HPA tissue IHC). Strong staining in proximal-tubule cells or Leydig cells is compatible with reported IHC patterns, while absent staining in nasopharyngeal basal cells is also reported (HPA tissue IHC). Treat a membrane rim, isolated edge staining or colour concentrated in necrotic tissue as a reason to review specificity and morphology (UniProt Q9UHX1 topology; standard IHC practice). Check a no-primary control for residual DAB deposit and verify that endogenous peroxidase was blocked (standard IHC practice). Interpret the remaining nuclear signal with cell identity and section quality in view (standard IHC practice).
Boster reagents

Best PUF60 / Poly(U)-binding-splicing factor PUF60 IHC Antibodies

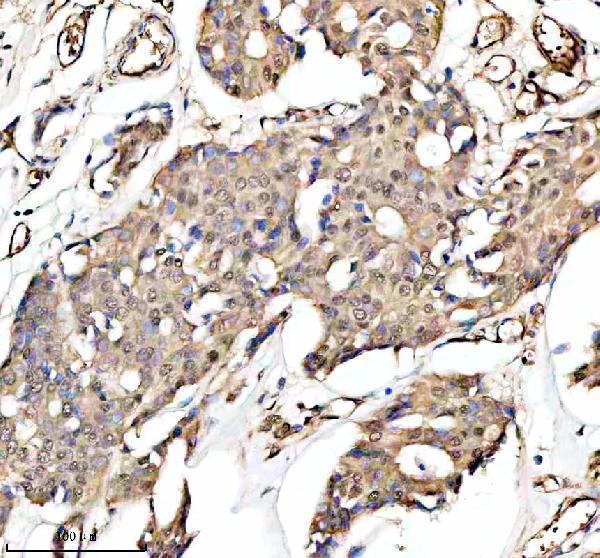
A05744-2 has real IHC data from a paraffin-embedded human breast cancer section (catalog IHC caption); the catalog lists human and mouse reactivity (catalog applications/reactivity). No IF image is provided (catalog images).

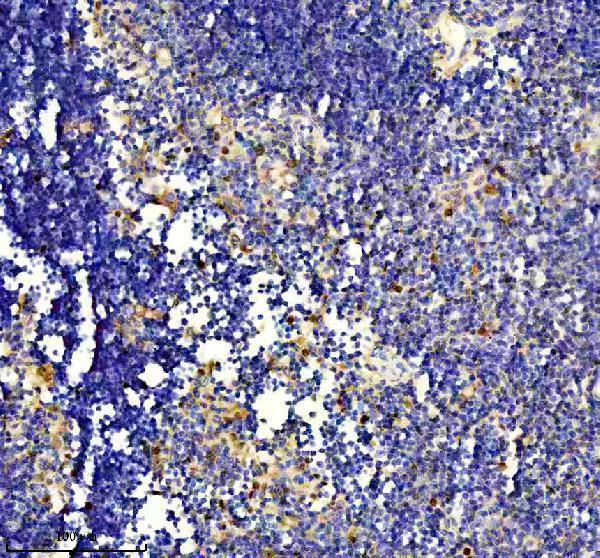
Real IHC data IHC analysis of PUF60 using anti-PUF60 antibody (A05744-2). PUF60 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PUF60 Antibody (A05744-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PUF60 Antibody ®
Cat # A05744-2

A05744-2 will render with an IHC figure from a paraffin-embedded human breast cancer section (catalog IHC caption). Its listed applications include IHC, and its listed reactivity is human and mouse (catalog applications/reactivity).

Which to pick: Choose A05744-2 for paraffin-section IHC: its own caption documents EDTA retrieval and staining at 2 μg/ml in human breast cancer tissue; the fixative is unreported (catalog IHC caption). No listed SKU has IF/ICC validation or an IF figure, so an IF/ICC choice cannot be supported here (catalog applications/images). A05744-2 lists mouse reactivity, but its supplied IHC figure shows only human tissue (catalog reactivity/IHC caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UHX1 (PUF60_HUMAN, Poly(U)-binding-splicing factor PUF60).
  2. Human Protein Atlas. PUF60 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PUF60 subcellular location (ICC-IF): Mainly localized to the nucleoplasm..
  4. Human Protein Atlas. PUF60 antibody validation summary (3 antibodies).
  5. PUF60: a prominent new target of the autoimmune response in dermatomyositis and Sjögren's syndrome. Annals of the rheumatic diseases 2016 — PMC4828328.
  6. PUF60 accelerates the progression of breast cancer through downregulation of PTEN expression. Cancer management and research 2019 — PMC6340502.
  7. Targeting PUF60 prevents tumor progression by retarding mRNA decay of oxidative phosphorylation in ovarian cancer. Cellular oncology (Dordrecht, Netherlands) 2024 — PMC10899302.
  8. PUF60 Promotes Chemoresistance Through Drug Efflux and Reducing Apoptosis in Gastric Cancer. International journal of medical sciences 2025 — PMC11704696.
  9. PubMed PMID:10882074 — UniProt-cited evidence.
  10. PubMed PMID:10668799 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.