PUS7 / Pseudouridylate synthase 7 homolog · IHC design guide

Design Immunohistochemistry for PUS7

Plan PUS7 IHC around mainly nuclear tissue staining (HPA tissue IHC). Use the catalog antibody at 2–5 μg/ml (datasheet A13434-1) and score nuclear staining by cell type.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PUS7 (IHC for PUS7): expected localisation Mainly nuclear tissue staining (HPA tissue IHC), antibody A13434-1, validated IHC image, and IHC protocol steps
Printable PUS7 IHC protocol sheet — expected localisation Mainly nuclear tissue staining (HPA tissue IHC), antibody A13434-1, controls and protocol steps. Open the full PUS7 IHC guide →

PUS7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Mainly nuclear tissue staining (HPA tissue IHC)
Staining pattern Mainly nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A13434-1)
Positive control ⓘ Cervix+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A13434-1)
Caveat Antibody staining has medium RNA concordance (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended PUS7 IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 retrieval (datasheet A13434-1). Published IHC protocols below cover gastric cancer, osteosarcoma, and lung cancer samples (PMC11341916; PMC11164482; PMC10329395).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A13434-1)
FixationImage fixative and duration unreported (datasheet A13434-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A13434-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A13434-1)
Primary antibodyRabbit anti-PUS7, 2-5 μg/ml (datasheet A13434-1)
Primary incubationOvernight at 4 °C (datasheet A13434-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A13434-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultPUS7-positive staining in squamous epithelial cells of cervix (HPA tissue IHC: High). HPA tissue profile: Mainly nuclear expression in all tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A13434-1). The lung cancer study reports a 97 °C, 20 min pretreatment (PMC10329395).
Section 2

What Is the Expected PUS7 Staining Pattern?

PUS7 should appear mainly in nuclei across tissues (UniProt Q96PZ0: nucleus; HPA tissue IHC: mainly nuclear). High staining is reported in cervical squamous epithelium, endometrial and parathyroid glandular cells, placental trophoblasts, and testicular Leydig cells (HPA tissue IHC: High). PUS7 has no transmembrane segment (UniProt Q96PZ0 topology). HPA rates the tissue profile Approved, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear chromogen in the expected cell populations.This fits PUS7 localisation (UniProt Q96PZ0: nucleus; HPA tissue IHC: mainly nuclear). High staining in cervical squamous, endometrial glandular, placental trophoblastic, or testicular Leydig cells provides a useful comparison (HPA tissue IHC: High in each). Judge nuclei against the section's counterstain (general IHC practice).
Predominantly cytoplasmic or membrane-like staining with little nuclear signal.This conflicts with the reported nuclear pattern (UniProt Q96PZ0: nucleus; HPA tissue IHC: mainly nuclear). PUS7 has no transmembrane segment (UniProt Q96PZ0 topology). Consider nonspecific staining or detection artefact; confirm with a reagent control and an expected high-staining tissue before assigning localisation (general IHC practice).
Strong signal in a cell population reported as low, or staining outside the expected cells.For example, HPA reports low staining in hepatocytes and lung alveolar cells (HPA tissue IHC: Low in each). Strong staining there warrants a cross-reactivity or endogenous detection-activity check (general IHC practice). Low is not absent (HPA tissue IHC: Low), so intensity alone does not establish a false positive.
Diffuse brown haze over nuclei, cytoplasm, and surrounding tissue.A haze that obscures cell boundaries cannot establish a nuclear PUS7 pattern (HPA tissue IHC: mainly nuclear). Assess the no-primary control, blocking, washing, and chromogen development for nonspecific or endogenous signal (general IHC practice); do not score the haze as PUS7-positive nuclei.
No nuclear signal in a tissue and cell type reported as high.Absence in endometrial glandular cells or placental trophoblasts conflicts with the reported high staining (HPA tissue IHC: High in each). Check section quality, antibody dilution, retrieval, and detection with appropriate controls (general IHC practice). One negative slide does not establish absent PUS7 expression.
💡Expected PUS7 appearanceCall a section positive when the expected cells show discernible nuclear chromogen, with stronger staining plausible in HPA High populations (UniProt Q96PZ0: nucleus; HPA tissue IHC: mainly nuclear and High in listed cells); diffuse tissue haze or cytoplasmic-only color is suspect (general IHC practice).
How each factor affects the staining
Tissue and cell selectionUse HPA High populations as expected-positive references, including cervical squamous and parathyroid glandular cells (HPA tissue IHC: High). Interpret weak signal in hepatocytes, cardiomyocytes, or lung alveolar cells against their reported Low levels; none is designated negative (HPA tissue IHC: Low; negative list empty).
Strength of the tissue evidenceThe tissue profile is Approved but has medium staining-to-RNA consistency and awaits external verification (HPA tissue IHC reliability). Antibody HPA024116 is Approved for IHC, with no Enhanced IHC status supplied (HPA antibody record). Treat departures from the reference pattern as findings to verify.
Isoforms and epitope coverageTwo PUS7 isoforms are listed (UniProt Q96PZ0: isoforms 1 and 2). The supplied record gives no antibody epitope or isoform-specific staining result, so an unusual IHC pattern cannot be assigned to one isoform from these data.
IF/ICC Q&A: where should PUS7 appear?In the separate IF/ICC application, the answer is nucleoplasm (HPA subcellular: approved nucleoplasm; HPA024116: ICC Approved). HPA lists images from A-431, U-251MG, and U2OS (HPA subcellular). Those observations support a localisation check; they do not supply an IHC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
An expected-positive IHC section has no nuclear signal.The assay may have insufficient detectable signal; the reference cell type should stain highly (HPA tissue IHC: High in listed populations).Verify that the expected cells are present, then review catalog-antibody dilution, retrieval, and detection controls (general IHC practice). Avoid calling the tissue PUS7-negative from this slide alone.
Color is mainly cytoplasmic or outlines membranes.That distribution disagrees with nuclear PUS7 localisation (UniProt Q96PZ0: nucleus; HPA tissue IHC: mainly nuclear).Compare with a nuclear counterstain and an expected-positive section; inspect reagent controls for nonspecific signal (general IHC practice).
Brown haze makes individual nuclei hard to score.Diffuse background can obscure compartment assignment (general IHC practice); the reference pattern is mainly nuclear (HPA tissue IHC).Review the no-primary control, blocking and washes, then adjust chromogen development if needed (general IHC practice). Score only clearly resolved nuclei.
The no-primary control also develops color.Signal without primary antibody implicates endogenous detection activity or another assay background source (general IHC practice).Address the control signal through the detection system's recommended blocking and reagent checks before interpreting PUS7 staining (general IHC practice).
Hepatocytes or lung alveolar cells stain as strongly as expected-high cells.Both are reported Low, while selected comparison populations are High (HPA tissue IHC). Cross-reactivity or background is possible; Low does not mean absent.Compare compartment and intensity on matched sections, review reagent controls, and seek independent confirmation before changing the expected pattern (general IHC practice).
The expected cells show patchy nuclear staining across a section.Uneven section preparation or staining may complicate scoring (general IHC practice); HPA's tissue profile also has medium consistency with RNA data (HPA tissue IHC reliability).Check section integrity and whether controls stain consistently, then score only interpretable regions and repeat the run if necessary (general IHC practice).

Sample controls for PUS7 IHC & IF

🧪Run cervix first and assess nuclear staining in squamous epithelial cells (HPA: High in cervical squamous epithelial cells; UniProt Q96PZ0: nucleus). HPA lists no negative tissue because PUS7 is detected in all 45 scored tissues, so use no-primary and isotype controls for background; on the positive slide, treat any cells lacking nuclear signal as an internal background reference, without assigning a cell type as PUS7-negative (HPA: no negative tissue listed; detected in all 45 scored tissues).
Positive control tissue: Cervix (Squamous epithelial cells, HPA High)
Negative control tissue: None in HPA: PUS7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PUS7 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a matched rabbit IgG isotype control, and PUS7 knockout material or a validated peptide-block control where available (catalog caption: rabbit anti-PUS7 antibody; standard IHC specificity controls). For chromogenic detection, quench endogenous peroxidase and check background in the cervical section before interpreting DAB staining (catalog caption: peroxidase detection with DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A13434-1 paraffin-section caption does not state the fixative (catalog caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required for every specimen (catalog caption: EDTA heat retrieval). Frozen-section performance is unreported; ICC-IF images exist for A-431, U-251MG and U2OS, but the supplied evidence does not establish that IF is easier than paraffin IHC (HPA subcellular: ICC-IF image cell lines; catalog caption: paraffin-section IHC).

HPA tissue IHC evidence for PUS7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cervix Squamous epithelial cells High Protein (IHC) HPA →
Endometrium Glandular cells High Protein (IHC) HPA →
Parathyroid gland Glandular cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Skin Fibroblasts Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: PUS7 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced PUS7 IHC Tips

Troubleshoot PUS7 staining in paraffin sections by checking retrieval, nuclear localisation, antibody specificity and cell based controls.

Which retrieval conditions should I use when PUS7 staining is weak?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections stained with A13434-1 (datasheet A13434-1). Keep section thickness, heating equipment, cooling and antibody incubation consistent while comparing retrieval runs, so a change in nuclear signal can be attributed to retrieval (standard IHC practice). The documented colon cancer section was incubated with 2 μg/ml antibody overnight at 4°C after retrieval, providing a useful reference for that antibody (datasheet A13434-1). If staining remains weak, adjust heating duration in a small pilot and inspect tissue preservation alongside nuclear signal before considering another retrieval buffer (standard IHC practice).
Could fixation explain inconsistent PUS7 staining between sections?
PUS7 specific sensitivity to fixation is unknown: the selected paraffin section caption does not state its fixative, and its staining cannot establish a preferred fixation condition (datasheet A13434-1). Record fixative, fixation duration and processing history for each specimen before comparing chromogenic nuclear staining (standard IHC practice). For prospectively collected material, compare matched neutral buffered formalin fixation periods, such as 12 and 24 hours, while holding retrieval and detection constant (standard IHC practice). Judge each condition by tissue preservation, background and interpretable nuclear staining, using a positive control section in the same run (standard IHC practice).
How should I assess cytoplasmic staining when scoring PUS7?
Score nuclear staining first: PUS7 is annotated in the nucleus, and tissue IHC shows mainly nuclear expression across tissues (UniProt Q96PZ0 localisation; HPA tissue IHC). Its approved subcellular location is the nucleoplasm, which helps define the expected compartment when examining cells at higher resolution (HPA subcellular). Compare suspicious cytoplasmic colour with nuclear staining in an established positive tissue, such as endometrial glandular cells, reported at high expression (HPA tissue IHC). If cytoplasmic staining persists, review the no primary control and optimise antibody concentration and chromogen development before calling it PUS7 specific (standard IHC practice).
Could the antibody miss a PUS7 isoform or modified epitope?
PUS7 has 2 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish equal recognition of both (UniProt Q96PZ0 isoforms; datasheet A13434-1). Obtain the immunogen or epitope sequence and align it with both isoforms before interpreting absent staining as absent PUS7 (standard antibody validation practice). The annotated TRUD domain spans residues 370–580, with reported phosphorylation at 10, 127 and 610; these annotations alone do not show that staining depends on modification state (UniProt Q96PZ0 domains and modified residues). Where isoform recognition matters, use independently validated antibody or genetic control evidence alongside matched IHC sections (standard IHC practice).
How can IF help resolve ambiguous nuclear PUS7 staining?
Use IF as a separate follow up to chromogenic IHC and look for nucleoplasmic signal, the approved subcellular location reported for PUS7 (HPA subcellular). Multiplex PUS7 with a marker for the expected cell population, such as an epithelial marker when examining squamous epithelial cells in cervix, where PUS7 staining is reported high (HPA tissue IHC). Choose a far red PUS7 fluorophore when tissue autofluorescence affects shorter wavelengths, and include single channel controls to check bleed through (standard IF practice). Permeabilise sufficiently for antibody access to the nuclear epitope; PUS7 has no annotated transmembrane segment, but the antibody epitope is unspecified here (UniProt Q96PZ0 topology; datasheet A13434-1).
What should I change when DAB obscures nuclear PUS7 staining?
First examine a no primary control to distinguish detection system background from staining associated with the primary antibody (standard IHC practice). The documented paraffin section used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and DAB development; these are reference conditions for A13434-1 (datasheet A13434-1). Include an endogenous peroxidase block before HRP and DAB detection, and shorten chromogen development if nuclei become obscured (standard chromogenic IHC practice). If diffuse colour remains, compare antibody titrations and washing conditions on adjacent sections while checking that the expected nuclear pattern remains visible (UniProt Q96PZ0 localisation; standard IHC practice).
How should I quantify PUS7 across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region of interest before scoring, then count PUS7 positive nuclei within that population (standard IHC quantification practice; UniProt Q96PZ0 localisation). Report the percentage of positive nuclei with staining intensity, or calculate an H score from 0–300 using intensity categories and their cell percentages (standard IHC quantification practice). Normalise counts to the number of eligible cells, or report positive cell density per mm² when tissue area is the appropriate denominator (standard IHC quantification practice). Keep retrieval, imaging, threshold and observer rules consistent, and report background controls because tissue IHC reliability is approved with medium RNA staining consistency pending external verification (standard IHC practice; HPA tissue IHC).
How do I distinguish convincing PUS7 staining from artefact?
A convincing pattern places signal predominantly in nuclei, consistent with the nuclear UniProt annotation and mainly nuclear tissue staining (UniProt Q96PZ0 localisation; HPA tissue IHC). Check whether staining occurs in an expected cell population, such as endometrial glandular cells or placental trophoblastic cells, both reported at high levels (HPA tissue IHC). Treat staining concentrated at section edges, within necrotic areas or in a no primary control as a prompt to investigate processing or detection artefacts (standard IHC practice). Endogenous peroxidase can also produce DAB colour, so confirm that a peroxidase blocked control supports the interpretation before assigning unusual cytoplasmic or tissue restricted staining to PUS7 (standard chromogenic IHC practice).
Boster reagents

Best PUS7 / Pseudouridylate synthase 7 homolog IHC Antibodies

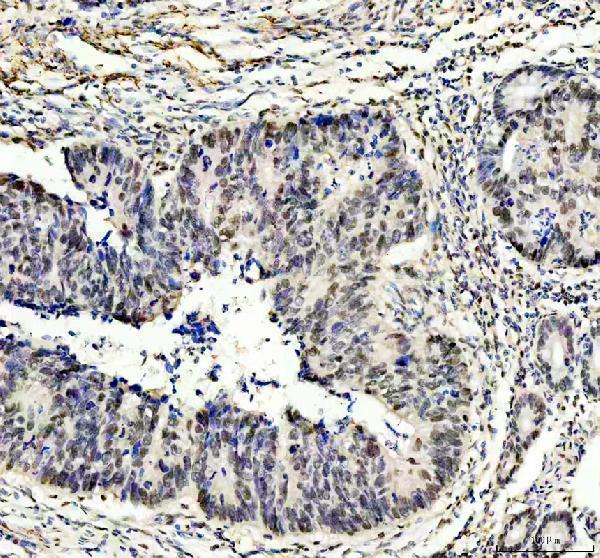
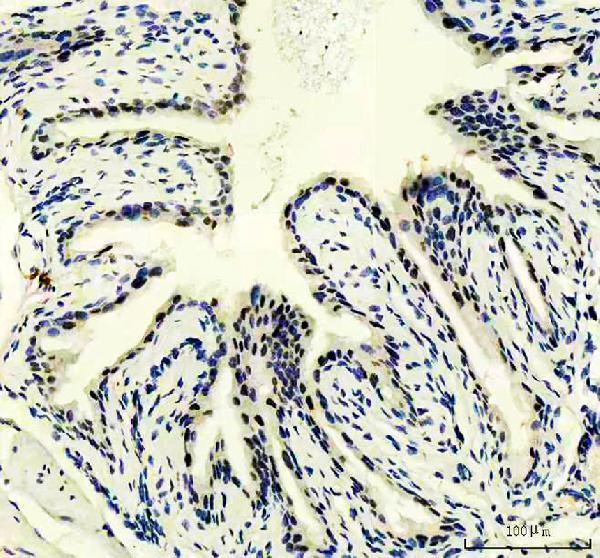
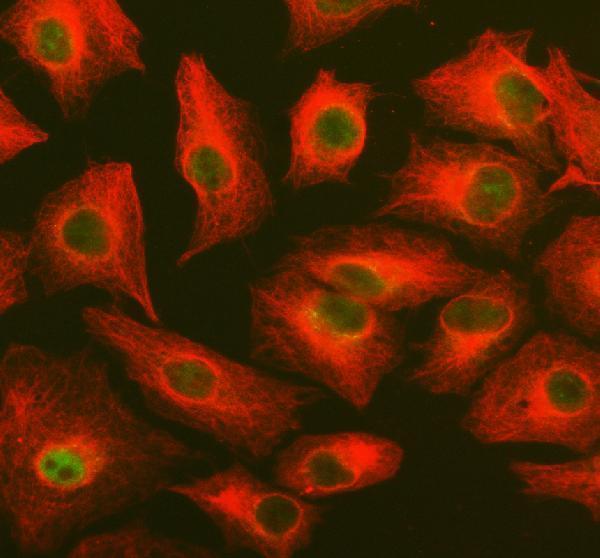
A13434-1 has IHC images from paraffin sections of human colon cancer and mouse and rat bladder, plus IF images from A549 cells and mouse bladder sections (catalog image captions).

Real IHC data IHC analysis of PUS7 using anti-PUS7 antibody (A13434-1). PUS7 was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-PUS7 Antibody (A13434-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-PUS7 Antibody ®
Cat # A13434-1

A13434-1 has IHC images from human colon cancer and mouse and rat bladder paraffin sections (catalog IHC captions). Its IF images show A549 cells and mouse bladder paraffin sections (catalog IF captions).

Which to pick: Choose A13434-1 for paraffin-section IHC: its tissue captions document EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml; the fixative is unreported (catalog IHC captions). The same SKU supports IF/ICC through its listed applications and IF images, with 5 μg/ml listed for IF (catalog applications, IF captions and dilution). It is the listed cross-species choice for human, mouse and rat; the catalog identifies a rabbit host but does not report clonality (catalog reactivity, host and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q96PZ0 (PUS7_HUMAN, Pseudouridylate synthase 7 homolog).
  2. Human Protein Atlas. PUS7 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. PUS7 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. PUS7 antibody validation summary (1 antibodies).
  5. PUS7-dependent pseudouridylation of ALKBH3 mRNA inhibits gastric cancer progression. Clinical and translational medicine 2024 — PMC11341916.
  6. Comprehensive analysis to identify PUS7 as a prognostic biomarker from pan-cancer analysis to osteosarcoma validation. Aging 2024 — PMC11164482.
  7. Higher expression of pseudouridine synthase 7 promotes non-small cell lung cancer progression and suggests a poor prognosis. Journal of cardiothoracic surgery 2023 — PMC10329395.
  8. The pseudouridine synthase PUS7 is associated with stemness and represents a potential therapeutic target in triple-negative breast cancer cells. Scientific reports 2026 — PMC12819403.
  9. PubMed PMID:12853948 — UniProt-cited evidence.
  10. PubMed PMID:15489334 — UniProt-cited evidence.
  11. PubMed PMID:11572484 — UniProt-cited evidence.