PVALB / Parvalbumin alpha · IHC design guide

Design Immunohistochemistry for PVALB

Plan chromogenic PVALB IHC in paraffin sections using cerebellum or kidney as positive controls and adipose tissue as a negative control (HPA tissue IHC). Interpret staining against the reported selective cytoplasmic and nuclear tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for PVALB (IHC for PVALB): expected localisation Cytoplasmic and nuclear staining in selected tissues (HPA tissue IHC), antibody M04041, validated IHC image, and IHC protocol steps
Printable PVALB IHC protocol sheet — expected localisation Cytoplasmic and nuclear staining in selected tissues (HPA tissue IHC), antibody M04041, controls and protocol steps. Open the full PVALB IHC guide →

PVALB Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic and nuclear staining in selected tissues (HPA tissue IHC)
Staining pattern Renal tubules, tonsil, cerebellum and parathyroid: cytoplasmic/nuclear staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M04041)
Positive control ⓘ Cerebellum+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Caudate glia are unstained despite cerebellar positivity (HPA tissue IHC)
Regulation Expression regulation is not annotated (UniProt)
Isoform / epitope No isoforms annotated; no membrane-spanning epitope distinction (UniProt)
Section 1

Recommended PVALB IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M04041) with the published human precentral gyrus IHC method (PMC7951111).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse cerebellum tissue; fixative not specified (datasheet M04041)
FixationImage fixative and duration unreported (datasheet M04041); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M04041); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M04041)
Primary antibodyRabbit monoclonal (clone AOFB-16) anti-PVALB, 1:50 (datasheet M04041)
Primary incubationOvernight at 4 °C (datasheet M04041)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M04041)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
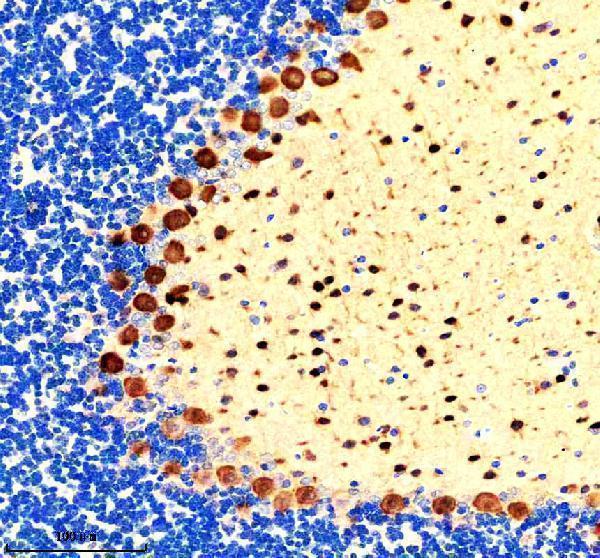
Expected resultPVALB-positive staining in molecular layer cells - cytoplasm/membrane of cerebellum (HPA tissue IHC: High). HPA tissue profile: Selective cytoplasmic and nuclear expression in renal tubules, tonsil, cerebellum and parathyroid gland. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet M04041); the published method does not specify retrieval (PMC7951111).
Section 2

What Is the Expected PVALB Staining Pattern?

PVALB staining should be selective: HPA reports cytoplasmic and nuclear expression in renal tubules, tonsil, cerebellum and parathyroid gland, with an Enhanced tissue IHC reliability rating (HPA: tissue IHC). High staining is reported in cerebellar molecular layer cells, kidney tubule cells and parathyroid glandular cells (HPA: tissue IHC). PVALB has no transmembrane segment or signal peptide (UniProt P20472: topology and processing).

What am I looking at on my slide?
Strong staining in cerebellar molecular layer cells, kidney tubule cells or parathyroid glandular cells.These are reported High IHC sites (HPA: tissue IHC). Judge the pattern by both cell identity and compartment: HPA describes selective cytoplasmic and nuclear tissue staining, while its cerebellar entry specifies cytoplasm/membrane (HPA: tissue IHC).
A compartment pattern seems inconsistent, such as staining restricted to a membrane outline across many cells.Recheck tissue context before calling artefact. HPA reports cytoplasmic and nuclear tissue expression and cytoplasm/membrane staining in cerebellar molecular layer cells (HPA: tissue IHC). PVALB has no transmembrane segment (UniProt P20472: topology); a widespread membrane-only pattern warrants review of controls and detection background (general IHC practice).
Strong staining appears in cells reported as negative, such as adipocytes or adrenal glandular cells.HPA lists those cells as Not detected (HPA: tissue IHC). Consider antibody cross-reactivity or endogenous detection activity, particularly if staining persists in a no-primary control; neither mechanism can be assigned from appearance alone (general IHC practice).
Color covers most of the section with little distinction between cells.A broadly diffuse pattern does not match HPA's selective tissue profile (HPA: tissue IHC). Compare no-primary and known-positive sections, then review blocking, primary concentration, washes and detection conditions as general sources of chromogenic background (general IHC practice).
No staining is visible in a known-positive cerebellum, kidney or parathyroid section.HPA reports High staining in the specified cells of these tissues (HPA: tissue IHC). Confirm that those cells are present, then check antibody dilution, retrieval and detection controls; the supplied sources do not establish a PVALB-specific retrieval or fixation effect (general IHC practice; source scope).
💡Expected PVALB appearanceCall a result positive when staining is selective in the reported cells and fits their reported compartments: High in cerebellar molecular layer cells, kidney tubule cells or parathyroid glandular cells (HPA: tissue IHC); widespread staining of HPA-negative cell types is suspect (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Tissue and cell selection (HPA: tissue IHC)Use a reported high-staining population to assess whether the assay can show PVALB: cerebellar molecular layer cells, kidney tubule cells or parathyroid glandular cells (HPA: tissue IHC). Cerebral cortical neuronal cells are reported at Medium, and tonsil germinal center cells are listed as low (HPA: tissue IHC); they set different expectations.
Compartment and topology (HPA: tissue IHC; UniProt P20472: topology)HPA describes selective cytoplasmic and nuclear tissue expression and cytoplasm/membrane staining in cerebellar molecular layer cells (HPA: tissue IHC). UniProt lists no transmembrane segment or signal peptide (UniProt P20472: topology and processing). Interpret a membrane outline in its cell and tissue context.
Antibody evidence (HPA: antibody validation)HPA048536 and CAB002515 each have Enhanced IHC validation (HPA: antibodies). HPA describes its tissue IHC profile as highly consistent with RNA expression data (HPA: tissue IHC reliability). These summaries support pattern assessment but do not specify how this catalog antibody behaves under a particular retrieval condition.
Target-specific fixation sensitivity (source scope)Neither the supplied HPA staining profile nor UniProt topology and modification records report a PVALB-specific fixation effect (HPA: tissue IHC; UniProt P20472: topology and modified residues). Treat retrieval optimization as an assay check, without predicting a tissue-specific gain or loss from those records.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The expected high-staining cells are blank.The section may lack the reported cell population, or an assay step may have failed; appearance alone cannot distinguish these causes (HPA: tissue IHC; general IHC practice).Locate the relevant cerebellar, kidney or parathyroid cells first (HPA: tissue IHC). Then check the catalog antibody's IHC-P instructions, dilution, retrieval and detection controls (general IHC practice); no PVALB-specific fixation response is supplied.
Every cell has a similar brown signal.That distribution conflicts with HPA's selective staining profile and may reflect excess primary or detection background (HPA: tissue IHC; general IHC practice).Run a no-primary control and inspect blocking, washes and primary dilution (general IHC practice). Compare with an HPA-reported negative population, such as adipocytes, before interpreting faint color as PVALB (HPA: Not detected in adipocytes).
Signal is strongest in an unexpected cell type.Cross-reactivity or endogenous detection activity is possible; HPA's negative calls identify populations where the observed result needs scrutiny (HPA: tissue IHC; general IHC practice).Compare a matched no-primary control and a reported positive tissue in the same run (general IHC practice). Check whether the suspect cells match HPA's listed cell types before assigning target-specific staining (HPA: tissue IHC).
Only membrane outlines stain across the section.A broad membrane-only result is difficult to reconcile with HPA's selective cytoplasmic and nuclear profile, although cerebellar molecular layer cells have a cytoplasm/membrane annotation (HPA: tissue IHC).Review cell identity and the no-primary control (general IHC practice). Avoid rejecting a cerebellar result solely for its membrane component; PVALB has no transmembrane segment (HPA: tissue IHC; UniProt P20472: topology).
Cerebral cortex stains less strongly than cerebellum.HPA reports Medium staining in cerebral cortical neuronal cells and High staining in cerebellar molecular layer cells (HPA: tissue IHC).Compare the annotated cell populations, rather than requiring equal intensity across tissues (HPA: tissue IHC). If the high-staining cerebellar population is also blank, check assay controls and the catalog antibody's IHC-P instructions (general IHC practice).
Does nuclear signal in IF/ICC invalidate the IHC result?HPA's ICC-IF summary calls the nucleoplasm its main approved location, with nucleoli and cell junctions also approved; HPA tissue IHC includes nuclear expression (HPA: subcellular ICC-IF; HPA: tissue IHC).Assess the IHC slide against its tissue and cell pattern (HPA: tissue IHC). Use the separate IF/ICC guide for that application; the ICC-IF compartment summary does not establish an IHC-P staining protocol (HPA: subcellular ICC-IF; source scope).

Sample controls for PVALB IHC & IF

🧪Run cerebellum first and look for staining in molecular layer cells (HPA: High in cerebellar molecular layer cells). Use adipose tissue as the negative tissue and expect adipocytes to lack specific staining (HPA: Not detected in adipocytes). On the cerebellar slide, cells judged negative should retain counterstain without a specific DAB deposit; do not assume every cell outside the molecular layer is negative (standard IHC practice).
Positive control tissue: Cerebellum (Molecular layer cells - cytoplasm/membrane, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show PVALB in AF22, RT-4, U2OS, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, an isotype control matched to the rabbit primary’s host species and antibody format, and PVALB-knockout tissue as a biological negative when available (hero caption: rabbit primary; standard IHC practice). Block endogenous peroxidase and check the cerebellar molecular layer for background DAB signal (hero caption: peroxidase/DAB detection; HPA: High in cerebellar molecular layer cells; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected M04041 paraffin-section caption does not state a fixative (hero caption: fixative unreported). That caption uses heat retrieval in EDTA at pH 8.0, but it does not establish that retrieval is required or that frozen sections or IF/ICC are easier (hero caption: EDTA retrieval). In cerebellum, assess background carefully before assigning diffuse DAB signal to molecular layer cells (HPA: molecular layer cells; standard IHC practice).

HPA tissue IHC evidence for PVALB

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Molecular layer cells - cytoplasm/membrane High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Parathyroid gland Glandular cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced PVALB IHC Tips

Troubleshoot PVALB staining in paraffin sections by checking the documented retrieval conditions, cell pattern and controls before comparing results across specimens.

Which antigen retrieval conditions should I try first for PVALB in paraffin sections?
Start with heat-mediated antigen retrieval in EDTA buffer at pH 8.0 for the catalog antibody (datasheet M04041). The documented mouse cerebellum image used this retrieval before 1:50 primary antibody incubation overnight at 4°C, so use that combination as the initial benchmark (caption M04041). If staining is weak, compare a shorter and a longer heating period on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Examine tissue preservation alongside signal, since excessive heating can damage section morphology and complicate cell-level scoring (standard IHC practice). Include a cerebellum control section in each comparison to distinguish retrieval failure from a low-expressing specimen (caption M04041; standard IHC practice).
How should I troubleshoot weak PVALB staining when fixation history is uncertain?
The selected image establishes staining in a paraffin-embedded mouse cerebellum section, but does not state its fixative (caption M04041). Target-specific sensitivity to fixative type or fixation duration is therefore unknown; record those details for each specimen before comparing staining intensity (caption M04041; standard IHC practice). Process an expected-positive control alongside test sections, using the documented EDTA pH 8.0 retrieval and overnight 4°C primary incubation as starting conditions (caption M04041). If the control stains and a test section does not, compare tissue preservation and processing records before interpreting the result biologically (standard IHC practice). Do not infer a PVALB fixation effect from its EF-hand domains or modified residues (UniProt P20472).
Where should convincing PVALB staining appear in chromogenic tissue sections?
Assess staining within identifiable cells: tissue IHC reports selective cytoplasmic and nuclear expression, including high signal in cerebellar molecular layer cells and renal tubules (HPA tissue IHC). Cerebral cortex neuronal cells show medium signal, while tonsil germinal center cells are reported at low level (HPA tissue IHC). For the catalog antibody, compare the cellular pattern with its paraffin-section mouse cerebellum example rather than requiring every structure to stain uniformly (caption M04041). PVALB has no annotated transmembrane segment, so isolated outlines without convincing cellular staining need closer review for artefact (UniProt P20472; standard IHC practice). Score nuclear and cytoplasmic signal separately when their proportions differ across specimens (HPA tissue IHC; standard IHC practice).
Could isoforms or epitope placement explain inconsistent PVALB staining?
The supplied protein record lists 0 isoforms and a processed chain spanning residues 2–110; it does not identify the catalog antibody's epitope (UniProt P20472; caption M04041). Two EF-hand regions span residues 39–74 and 78–110, while reported modified residues include positions 2 and 24 (UniProt P20472). Those features cannot establish whether fixation or retrieval masks this antibody's binding site without an epitope map and direct testing (UniProt P20472; standard IHC practice). If sections disagree, first repeat the documented EDTA pH 8.0 retrieval with the same antibody dilution and detection conditions (caption M04041). Compare an expected-positive section in the same run before assigning the difference to an epitope effect (standard IHC practice).
How can I compare an IF experiment with this PVALB chromogenic IHC result?
Treat the catalog antibody's paraffin-section DAB image as IHC evidence; its caption does not establish an IF fixation or permeabilisation protocol (caption M04041). For IF comparison, multiplex PVALB with a neuronal marker in cerebral cortex, where neuronal cells show medium PVALB tissue signal (HPA tissue IHC; standard IF practice). Choose a longer-wavelength fluorophore and image an unstained section to assess tissue autofluorescence before interpreting faint signal (standard IF practice). Because PVALB has no transmembrane segment and tissue IHC includes cytoplasmic and nuclear staining, test mild permeabilisation for access to intracellular epitopes (UniProt P20472; HPA tissue IHC; standard IF practice). Compare cell identity and compartment patterns across methods without assuming equal signal intensity (standard IHC/IF practice).
What controls help identify nonspecific PVALB DAB background?
Inspect a no-primary section to reveal signal from the detection system, and compare it with an expected-positive cerebellum section processed in parallel (standard IHC practice; caption M04041). The documented image used 10% goat serum blocking, a peroxidase-linked secondary and DAB development; these are its reported conditions, not evidence that every background source was eliminated (caption M04041). Apply a peroxidase block before HRP detection and check for residual endogenous enzyme signal in the no-primary control (standard IHC practice). If diffuse staining persists, optimise blocking, antibody concentration and wash conditions one variable at a time (standard IHC practice). Compare cellular staining with reported PVALB-positive and undetected tissue patterns before calling faint deposits specific (HPA tissue IHC).
How should I quantify PVALB staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the region and cell population before scoring: examples with reported signal include cerebellar molecular layer cells, renal tubular cells and cerebral cortex neuronal cells (HPA tissue IHC). For cell-based analysis, record the percentage of positive cells and staining intensity as an H-score, keeping nuclear and cytoplasmic scores distinct (HPA tissue IHC; standard IHC practice). Where individual cells cannot be resolved reliably, measure positive-cell density per mm² of evaluable tissue instead (standard IHC practice). Normalise counts to the corresponding eligible cell population or sampled tissue area, and exclude folds, damaged edges and necrosis consistently (standard IHC practice). Keep retrieval, DAB development and image thresholds consistent across comparison groups (standard IHC practice).
When is an apparent PVALB-positive cell likely to be artefactual?
Give greatest weight to staining in anatomically identifiable cells with patterns supported by tissue evidence, such as cerebellar molecular layer cells or renal tubules (HPA tissue IHC). Reconsider isolated signal in cell populations reported as undetected, including adipocytes in adipose tissue, especially when an expected-positive control also fails (HPA tissue IHC; standard IHC practice). Review unexpected membrane-only outlines against PVALB's lack of a transmembrane segment and the reported cytoplasmic and nuclear tissue pattern (UniProt P20472; HPA tissue IHC). Edge accentuation, necrotic deposits and staining that persists without primary antibody warrant investigation as technical signal (standard IHC practice). A peroxidase-blocked, no-primary control helps distinguish endogenous enzyme activity from antigen-dependent DAB staining (standard IHC practice).
Boster reagents

Best PVALB / Parvalbumin alpha IHC Antibodies

Two rabbit monoclonal anti-PVALB antibodies have IHC images from brain tissue; both list human, mouse and rat reactivity (catalog applications/reactivity; IHC image captions). IF is listed for M04041-3 (catalog applications).

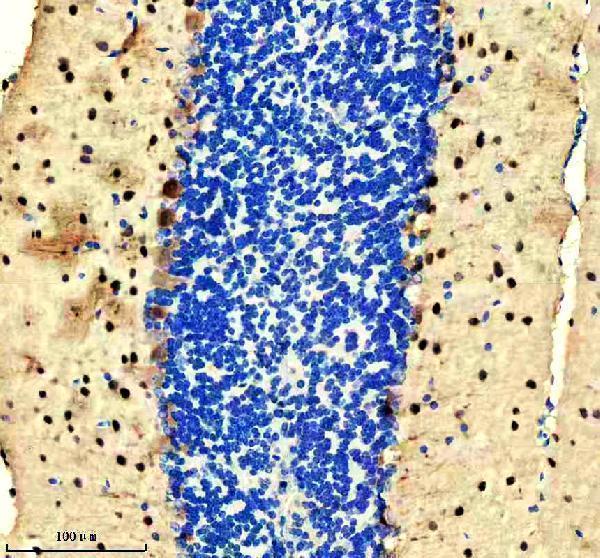
Real IHC data IHC analysis of PVALB using anti-PVALB antibody (M04041). PVALB was detected in a paraffin-embedded section of mouse cerebellum tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-PVALB Antibody (M04041) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Parvalbumin PVALB Rabbit Monoclonal Antibody
Cat # M04041
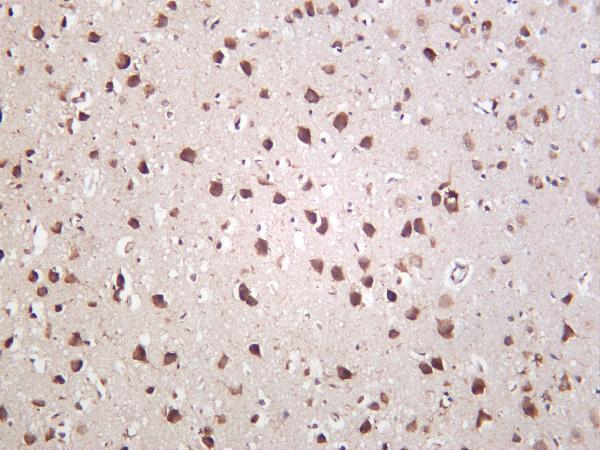
Real IHC data Rat brain was stained with anti-Parvalbumin rabbit antibody
Anti-Parvalbumin Rabbit Monoclonal Antibody
Cat # M04041-3

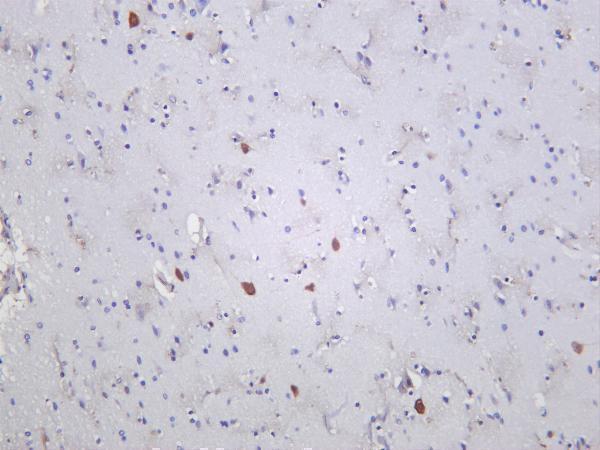
M04041 has IHC images from paraffin-embedded mouse and rat cerebellum (M04041 IHC image captions). M04041-3 has IHC images from rat, human and mouse brain and lists IF as an application (M04041-3 IHC image captions; catalog applications).

Which to pick: For paraffin-section IHC, choose M04041: its own captions document paraffin-embedded cerebellum sections, EDTA retrieval at pH 8.0 and a 1:50 dilution; the fixative is unreported (M04041 IHC image captions). For IF, choose M04041-3 because IF is listed at 1:200–1:1000; ICC validation and IF images are unreported (M04041-3 catalog applications/dilutions; image payload). Both are rabbit monoclonals reactive with human, mouse and rat, while M04041-3 has IHC images from all three species; its captions do not report section processing or fixative (catalog titles/reactivity; M04041-3 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P20472 (PRVA_HUMAN, Parvalbumin alpha).
  2. Human Protein Atlas. PVALB tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. PVALB subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the nucleoli and cell junctions..
  4. Human Protein Atlas. PVALB antibody validation summary (2 antibodies).
  5. Parvalbumin expression changes with retinal ganglion cell degeneration. Frontiers in neuroscience 2023 — PMC10600448.
  6. CSF parvalbumin levels reflect interneuron loss linked with cortical pathology in multiple sclerosis. Annals of clinical and translational neurology 2021 — PMC7951111.
  7. Diversity of Interneurons in the Dorsal Striatum Revealed by Single-Cell RNA Sequencing and PatchSeq. Cell reports 2018 — PMC6117871.
  8. Age-dependent sexual dimorphism in hippocampal cornu ammonis-1 perineuronal net expression in rats. Brain and behavior 2019 — PMC6520292.
  9. PubMed PMID:2614829 — UniProt-cited evidence.
  10. PubMed PMID:8354278 — UniProt-cited evidence.
  11. PubMed PMID:15461802 — UniProt-cited evidence.