RAB14 / Ras-related protein Rab-14 · IHC design guide

Design Immunohistochemistry for RAB14

Plan RAB14 chromogenic IHC in paraffin sections using the catalog antibody at 2–5 μg/mL (datasheet PB9815). Compare staining with the general cytoplasmic tissue profile and high signal in colon glandular cells (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RAB14 (IHC for RAB14): expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody PB9815, validated IHC image, and IHC protocol steps
Printable RAB14 IHC protocol sheet — expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC), antibody PB9815, controls and protocol steps. Open the full RAB14 IHC guide →

RAB14 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in tissue sections (HPA tissue IHC)
Staining pattern General cytoplasmic staining; glandular cells can be high (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9815)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Spleen
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet PB9815); verify before use.
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Low tissue specificity (HPA RNA specificity)
Isoform / epitope No isoforms annotated; chain spans residues 2–215 (UniProt)
Section 1

Recommended RAB14 IHC & IF Protocols

The catalog antibody has an EDTA pH 8.0 IHC protocol (datasheet: PB9815); four published RAB14 IHC protocols provide additional tissue and staining conditions (PMC7105221; PMC10412633; PMC7509480; PMC5166543).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet PB9815)
FixationImage fixative and duration unreported (datasheet PB9815); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9815); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9815)
Primary antibodyRabbit anti-RAB14, 2-5μg/ml (datasheet PB9815)
Primary incubationOvernight at 4 °C (datasheet PB9815)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet PB9815)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRAB14-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 for the catalog antibody (datasheet: PB9815). Published protocols also report citrate retrieval for other antibodies (PMC7509480; PMC5166543).
Section 2

What Is the Expected RAB14 Staining Pattern?

RAB14 is associated with endosomes, Golgi membranes and cytoplasmic vesicles, and has no transmembrane segment (UniProt P61106 subcellular location; topology). In paraffin-section IHC, expect cytoplasmic staining, especially in glandular cells from several HPA high-staining tissues and esophageal squamous epithelial cells (HPA: high; general cytoplasmic expression). HPA rates its tissue IHC profile Approved, with medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining in colon or duodenal glandular cells; some cells show granular emphasis.This fits the reported high staining in those glandular cells and general cytoplasmic IHC profile (HPA: high; tissue profile). Granularity is compatible with endosomal and vesicular localization, but chromogenic IHC alone does not identify an individual organelle (UniProt P61106 subcellular location; general IHC practice).
Predominantly nuclear staining, with little convincing cytoplasmic signal.A nuclear dominant pattern is discordant with the reported cytoplasmic IHC profile and supported vesicular ICC-IF location (HPA: tissue profile; subcellular). Review antibody specificity and the detection controls before scoring it as RAB14; an unusual compartment alone cannot establish the cause (general IHC practice).
Strong staining in spleen red-pulp cells, especially when expected epithelial staining is weak.HPA reports RAB14 as not detected in spleen red-pulp cells (HPA: tissue IHC). Check for cross-reactivity or endogenous detection activity with appropriate controls (general IHC practice). This comparison does not make every red-pulp cell an absolute biological negative across all samples (HPA: tissue IHC).
Uniform color over cells, extracellular areas and blank regions, without a readable cellular pattern.Treat field-wide haze as background pending controls (general IHC practice). Do not reject all broad cytoplasmic staining: HPA describes general cytoplasmic expression, while its ICC-IF data support vesicles (HPA: tissue profile; subcellular). Tissue structure and a no-primary control help separate signal from background (general IHC practice).
No cytoplasmic signal in glandular cells of a known high-staining HPA tissue.Absence conflicts with the reported high staining for the specified cell type, such as colon glandular cells (HPA: high in colon glandular cells). First verify that the expected cells are present and the run's controls worked; a blank section by itself cannot establish absent RAB14 (general IHC practice).
💡Expected RAB14 appearanceCall a section positive when interpretable cytoplasmic signal occurs in the specified HPA high-staining cells, such as colon glandular cells, with intensity judged against the run's controls; predominantly nuclear signal or color extending across cell-free areas warrants investigation (HPA: high in colon glandular cells; general cytoplasmic expression; general IHC practice).
How each factor affects the staining
Compartment and optical resolutionUniProt places RAB14 at endosomes, Golgi membranes and cytoplasmic vesicles, while HPA calls its paraffin-section profile generally cytoplasmic (UniProt P61106 subcellular location; HPA: tissue profile). Score the visible cytoplasmic pattern; do not assign specific organelles from chromogenic staining alone (general IHC practice).
Choice of comparison tissueHPA reports high staining in glandular cells of colon, duodenum, appendix and several other listed tissues, and not-detected staining in spleen red-pulp cells (HPA: tissue IHC). Compare the stated cell populations, not whole-organ averages (general IHC practice); HPA also reports low tissue RNA specificity (HPA: RNA specificity).
Strength of antibody evidenceHPA lists two antibodies with Approved IHC status; it describes the tissue profile as having medium consistency with RNA expression (HPA: antibody validation; reliability). These labels support pattern comparison but do not certify that every stained cell or preparation is specific (general IHC practice).
IF/ICC Q&A: what pattern should a separate IF experiment assess?Look for vesicular localization: HPA reports a supported vesicle location and images in A-431, U-251MG, U2OS and RPTEC/TERT1; HPA026419 has Supported ICC status (HPA: subcellular; antibody validation). Use the separate IF/ICC guide for experimental setup.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A high-staining comparison tissue is blank.The selected field may lack the specified glandular or squamous cells, or the IHC run may have failed (HPA: tissue IHC; general IHC practice).Confirm cell identity and section quality, then inspect the run's positive control and detection steps before interpreting the blank field (general IHC practice).
Nuclear staining dominates.This conflicts with HPA's general cytoplasmic tissue profile and supported vesicle location; the staining source is unresolved (HPA: tissue profile; subcellular).Compare with a known high-staining cell population and review antibody and no-primary controls; report the compartment discrepancy if it persists (HPA: tissue IHC; general IHC practice).
Strong color appears in spleen red-pulp cells.That cell population is reported as not detected by HPA; cross-reactivity or endogenous detection activity is possible, but the pattern alone cannot distinguish them (HPA: tissue IHC; general IHC practice).Inspect no-primary and detection-system controls, then compare staining in an HPA high-staining tissue from the same run (HPA: tissue IHC; general IHC practice).
Diffuse color obscures cell boundaries.Field-wide background may reflect a detection or blocking problem (general IHC practice); HPA's general cytoplasmic profile does not establish that every diffuse signal is specific (HPA: tissue profile).Check a no-primary control, blocking and washes; adjust routine detection conditions only after identifying where background enters the run (general IHC practice).
Cytoplasmic signal is weak but the section is otherwise readable.HPA reports low staining in some cell populations, including liver cholangiocytes and skeletal-muscle myocytes, so weak signal may be consistent with the chosen cells (HPA: low in cholangiocytes; low in myocytes).Identify the cells being scored and compare them with an HPA high-staining population processed in the same run; avoid upgrading weak color solely because RAB14 is broadly expressed (HPA: tissue IHC; general IHC practice).
Two sampled tissues give different staining intensities.HPA assigns different levels to specified cell populations and reports medium consistency between tissue staining and RNA expression (HPA: tissue IHC; reliability). A tissue-wide intensity comparison can hide differences in cell composition (general IHC practice).Record intensity by identified cell type, use the same scoring and detection conditions, and retain HPA's reliability caveat when interpreting a mismatch (HPA: tissue IHC; reliability; general IHC practice).

Sample controls for RAB14 IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use spleen red-pulp cells as a negative tissue (HPA: Not detected in spleen red pulp); on the colon slide, assess unstained areas for background, without assuming that non-glandular cells lack RAB14.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Spleen (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RAB14 in A-431, U-251MG, U2OS, RPTEC/TERT1, with annotated localisation: Vesicles (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, an isotype control matched to the rabbit primary’s clonality, and RAB14-knockout tissue as a biological negative (selected tissue-IHC caption: rabbit primary). Block endogenous peroxidase and check inflammatory cells for residual DAB background in colon sections (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU paraffin-section caption does not state a fixative (selected tissue-IHC caption: fixative unreported). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish whether retrieval is required (selected tissue-IHC caption: EDTA retrieval). IF offers a vesicular localisation readout in imaged cell lines (HPA: vesicles supported); the supplied evidence does not show that IF or frozen sections are easier, and endogenous peroxidase in colon inflammatory cells may complicate chromogenic scoring (standard chromogenic IHC practice).

HPA tissue IHC evidence for RAB14

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Endometrium Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced RAB14 IHC Tips

Troubleshoot RAB14 staining in paraffin sections by checking retrieval, specimen handling, cytoplasmic localisation and chromogenic controls before scoring.

How should I retrieve RAB14 in paraffin sections when staining is weak?
Use heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet PB9815). That condition produced RAB14 staining in a human breast cancer paraffin section, although the caption does not report its fixative (datasheet PB9815). Keep retrieval conditions constant while first testing the documented 2 μg/ml primary antibody concentration and overnight incubation at 4°C (datasheet PB9815). If staining remains weak, compare a modest change in heating time or an alternative retrieval buffer on adjacent sections, with an established positive section in each run (standard IHC practice). Judge improvement by cytoplasmic signal alongside preserved tissue morphology and low no-primary background (HPA tissue IHC; standard IHC practice).
Could fixation explain inconsistent RAB14 staining between paraffin specimens?
Target-specific fixation sensitivity is unknown: the PB9815 tissue caption describes a paraffin section but does not state its fixative (datasheet PB9815). Record each specimen’s fixative and fixation duration, and compare sections processed together before attributing intensity differences to RAB14 abundance (standard IHC practice). For a controlled pilot, use consistently prepared 10% neutral buffered formalin specimens and hold section thickness and EDTA retrieval at pH 8.0 constant (standard IHC practice; datasheet PB9815). Examine morphology and staining in an established positive section from every processing batch (standard IHC practice). Do not infer fixation sensitivity from tissue expression patterns or membrane association alone (HPA tissue IHC; UniProt P61106 topology).
What RAB14 staining pattern should I expect in tissue sections?
Expect predominantly cytoplasmic staining in paraffin sections, with possible granular or punctate accentuation rather than a nuclear-only pattern (HPA tissue IHC; UniProt P61106 subcellular location). RAB14 is associated with recycling and early endosomes, Golgi membranes, and cytoplasmic vesicles, supporting that compartmental expectation (UniProt P61106 subcellular location). Individual vesicles may be difficult to resolve with chromogenic brightfield microscopy, so score reproducible cytoplasmic distribution across intact cells (standard IHC practice). Glandular cells in colon and gallbladder are reported as high-staining tissue references (HPA: High in colon and gallbladder glandular cells). Compare those references in the same staining run before interpreting diffuse nuclear colour or staining confined to damaged edges as target signal (standard IHC practice).
How can epitope location affect my RAB14 IHC result?
No alternative isoforms are annotated for RAB14, but the supplied evidence does not identify the catalog antibody’s epitope (UniProt P61106 isoforms; datasheet PB9815). The annotated protein chain spans residues 2–215, with N-terminal acetylation and a C-terminal cysteine methyl ester recorded (UniProt P61106 processing and modified residues). RAB14 has no transmembrane segment, yet it associates with endosomal and Golgi membranes (UniProt P61106 topology and subcellular location). Without an epitope map, do not assign weak staining to either terminal modification or to masking of a particular membrane-facing surface (UniProt P61106 modified residues; standard IHC interpretation). Titrate around the documented 2 μg/ml condition and compare an independent antibody or genetic specificity control when available (datasheet PB9815; standard IHC practice).
How should IF complement chromogenic RAB14 IHC?
Use IF as a separate localisation check: the tissue IHC profile describes general cytoplasmic expression, while subcellular IF supports vesicular localisation (HPA tissue IHC; HPA subcellular). Multiplex RAB14 with a marker of the cell population being scored, such as an epithelial marker when assessing glandular cells, and include single-stain controls (HPA: High in glandular cells in several tissues; standard IF practice). Choose spectrally separated fluorophores, favouring red or far-red detection where tissue autofluorescence obscures shorter wavelengths (standard IF practice). Because RAB14 lacks a transmembrane segment and associates with intracellular membranes, test mild permeabilisation, such as 0.1% detergent, for access to cytoplasmic epitopes (UniProt P61106 topology and subcellular location; standard IF practice). Confirm that permeabilisation preserves puncta and does not create diffuse background before comparing IF with IHC (HPA subcellular; standard IF practice).
What should I check when RAB14 DAB staining looks nonspecific?
Start with a no-primary control and inspect where DAB appears; colour persisting without primary antibody implicates detection chemistry or endogenous tissue activity (standard IHC practice). Block endogenous peroxidase before HRP detection and assess endogenous pigment in an unstained section when brown deposits complicate interpretation (standard IHC practice). The documented tissue workflow used 10% goat serum, 2 μg/ml primary antibody overnight at 4°C, and HRP with DAB (datasheet PB9815). If background rises with primary antibody, titrate below that starting concentration, review blocking and washes, and compare intact regions with section edges (standard IHC practice). Retain a positive tissue section so a cleaner result is not mistaken for lost RAB14 detection (HPA tissue IHC; standard IHC practice).
How should I quantify RAB14 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue region before scoring, because the reported tissue profile assigns expression to specific cell types (HPA tissue IHC; standard IHC practice). For cellular staining, record both the percentage of positive cells and an intensity category, then calculate an H-score from 0–300 using the same thresholds across slides (standard IHC practice). For spatial analysis, report positive-cell density per mm² of viable tissue, with epithelial and stromal compartments scored separately where relevant (standard IHC practice). Normalize each measure to the eligible cells or area actually examined, and document exclusions for necrosis, folds and edges (standard IHC practice). Include a consistently processed positive tissue reference in every batch to monitor run variation (HPA tissue IHC; standard IHC practice).
How can I distinguish genuine RAB14 signal from tissue artefact?
Favour cytoplasmic staining in intact cells, potentially with granular accentuation, because the tissue profile is cytoplasmic and the protein localises to intracellular membranes and vesicles (HPA tissue IHC; UniProt P61106 subcellular location). Check the cell type: glandular cells in colon or gallbladder are reported as high-staining references, whereas cells in splenic red pulp were not detected in the cited profile (HPA tissue IHC). Treat colour restricted to section edges, folds or necrotic regions as suspect until it recurs in well-preserved cells (standard IHC practice). A no-primary control helps identify endogenous enzyme activity or detection background that could mimic DAB signal (standard IHC practice). Confirm unexpected nuclear-only or compartmentally inconsistent staining with an independent specificity control before assigning biological meaning (UniProt P61106 subcellular location; standard IHC practice).
Boster reagents

Best RAB14 / Ras-related protein Rab-14 IHC Antibodies

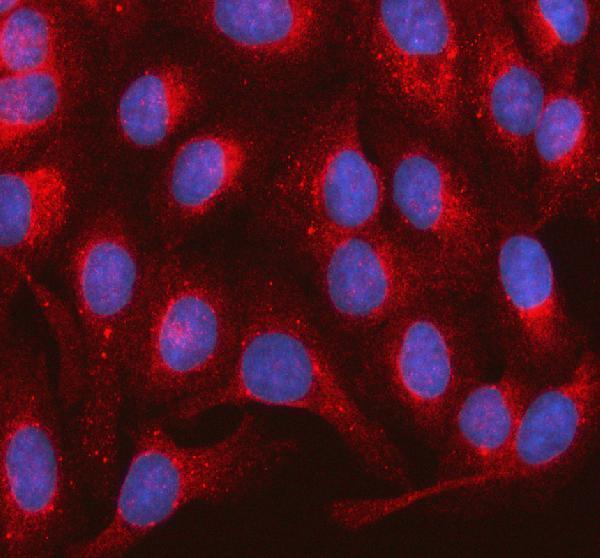
PB9815 has documented IHC staining in human paraffin sections and IF staining in human colon cancer sections and U2OS cells (catalog image captions). The catalog lists human, mouse, and rat reactivity (catalog: PB9815).

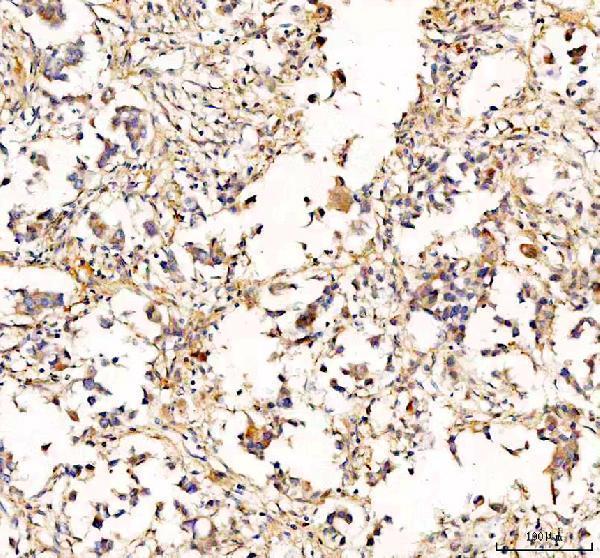
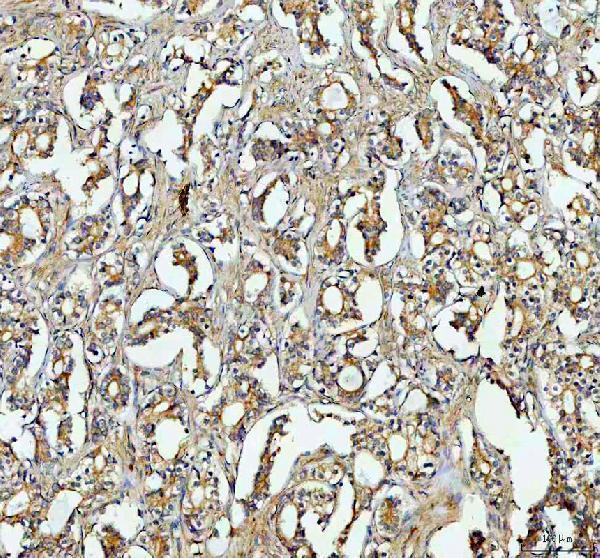
Real IHC data IHC analysis of RAB14 using anti-RAB14 antibody (PB9815). RAB14 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-RAB14 Antibody (PB9815) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RAB14 Antibody ®
Cat # PB9815

PB9815 has IHC images from human breast cancer, ovarian cancer, placenta, and cervical carcinoma paraffin sections (catalog IHC image captions). Its IF images show human colon cancer paraffin sections and U2OS cells (catalog IF image captions).

Which to pick: Choose PB9815 for paraffin-section IHC: its breast cancer image documents EDTA pH 8 retrieval and 2 μg/ml primary antibody (PB9815 IHC image caption). Choose PB9815 for IF/ICC because those applications and 5 μg/ml are listed, with images from colon cancer sections and U2OS cells (catalog: PB9815; PB9815 IF image captions). For mouse or rat work, PB9815 lists reactivity with both species, but the supplied IHC images are human; clonality and the paraffin sections’ fixative are unreported (catalog: PB9815; PB9815 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P61106 (RAB14_HUMAN, Ras-related protein Rab-14).
  2. Human Protein Atlas. RAB14 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. RAB14 subcellular location (ICC-IF): Localized to vesicles..
  4. Human Protein Atlas. RAB14 antibody validation summary (2 antibodies).
  5. Proteomic analysis of cathepsin B- and L-deficient mouse brain lysosomes. Biochimica et biophysica acta 2007 — PMC7105221.
  6. RAB14 promotes epithelial-mesenchymal transition in bladder cancer through autophagy‑dependent AKT signaling pathway. Cell death discovery 2023 — PMC10412633.
  7. Rab14 Overexpression Promotes Proliferation and Invasion Through YAP Signaling in Non-Small Cell Lung Cancers. OncoTargets and therapy 2020 — PMC7509480.
  8. Rab14 Suppression Mediated by MiR-320a Inhibits Cell Proliferation, Migration and Invasion in Breast Cancer. Journal of Cancer 2016 — PMC5166543.
  9. PubMed PMID:10931946 — UniProt-cited evidence.
  10. PubMed PMID:17974005 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.