RBBP4 / Histone-binding protein RBBP4 · IHC design guide

Design Immunohistochemistry for RBBP4

Plan RBBP4 chromogenic IHC on paraffin sections with the catalog antibody (datasheet M02702). This guide covers expected nuclear staining (HPA tissue IHC), fixation consistency and controls (standard IHC practice), and the HPA multi-gene targeting caveat (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
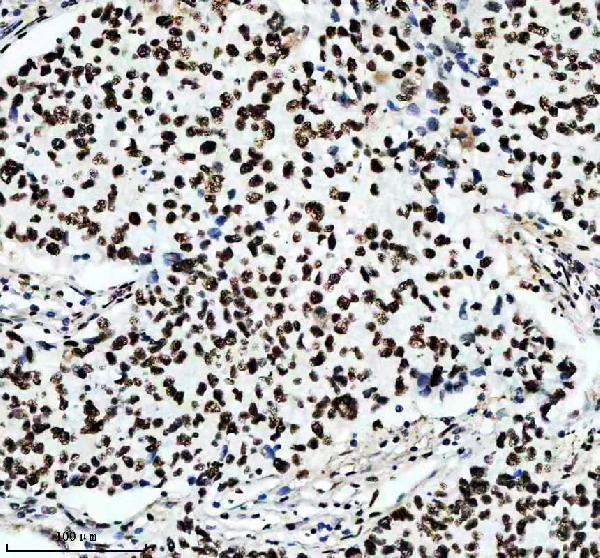
Immunohistochemistry protocol sheet for RBBP4 (IHC for RBBP4): expected localisation Nucleus (HPA tissue IHC), antibody M02702, validated IHC image, and IHC protocol steps
Printable RBBP4 IHC protocol sheet — expected localisation Nucleus (HPA tissue IHC), antibody M02702, controls and protocol steps. Open the full RBBP4 IHC guide →

RBBP4 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nucleus (HPA tissue IHC)
Staining pattern Widespread nuclear staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M02702)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image M02702)
Caveat HPA staining may target proteins from multiple genes (HPA tissue IHC)
Regulation No staining-linked regulator reported (UniProt)
Isoform / epitope 4 isoforms; epitope coverage unreported (UniProt)
Section 1

Recommended RBBP4 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet M02702) with published mouse liver and glioma IHC protocols (PMC9134917; PMC10469049).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet M02702)
FixationImage fixative and duration unreported (datasheet M02702); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M02702); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M02702)
Primary antibodyRabbit monoclonal (clone AEII-18) anti-RBBP4, 1:50 (datasheet M02702)
Primary incubationOvernight at 4 °C (datasheet M02702)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M02702)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRBBP4-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA at pH 8.0 (datasheet M02702); the mouse liver study used 0.01 M sodium citrate–hydrochloric acid buffer (PMC9134917).
Section 2

What Is the Expected RBBP4 Staining Pattern?

RBBP4 is nuclear and associates with chromatin; it has no transmembrane segment (UniProt Q09028). In paraffin-section IHC, expect nuclear staining across many cell types, including glandular, hematopoietic, respiratory epithelial and glial cells (HPA tissue IHC: ubiquitous nuclear expression; listed cells High). HPA rates the tissue staining Supported, with a caution that the assay may detect proteins from more than one gene (HPA tissue IHC).

What am I looking at on my slide?
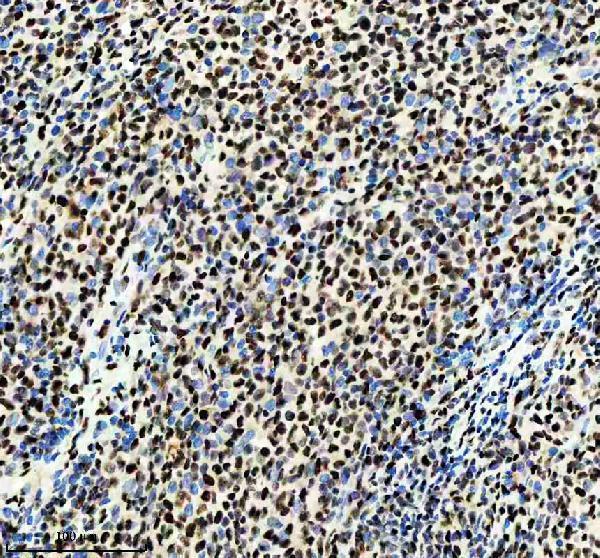
Nuclei stain in multiple cell types, while surrounding cytoplasm remains comparatively clear.This fits the reported ubiquitous nuclear IHC profile and RBBP4 localization (HPA tissue IHC; UniProt Q09028). HPA lists High staining in glandular, hematopoietic, respiratory epithelial and glial cells; use nuclear location alongside intensity when judging a section.
Predominant cytoplasmic or cell-surface staining, with little nuclear signal.This conflicts with the nuclear IHC profile, nucleoplasmic IF localization and lack of a transmembrane segment (HPA tissue IHC; HPA subcellular; UniProt Q09028). Treat it as a possible staining artefact and check controls before assigning it to RBBP4.
Signal appears in a cell population outside the examples listed by HPA.Cell identity alone cannot establish a false positive: HPA describes ubiquitous nuclear expression, and its supplied tissue list contains no negative cell populations (HPA tissue IHC). If the signal is unexpected in location or persists in controls, investigate cross-reactivity or endogenous detection activity (general IHC practice).
Chromogen is diffuse across the section or obscures nuclear boundaries.Diffuse signal prevents a reliable nuclear localization call (HPA tissue IHC: nuclear profile). Check whether the primary-omission control also develops signal; background there points toward detection-system or endogenous activity rather than a specific primary-antibody pattern (general IHC practice).
A listed positive tissue has no convincing nuclear staining.For example, HPA reports High staining in breast glandular cells and bone marrow hematopoietic cells (HPA tissue IHC). An absent result calls for technical review, but one section alone does not establish that its cells lack RBBP4; assess tissue quality, controls and the antibody's IHC instructions (general IHC practice).
💡Expected RBBP4 appearanceCall a result positive when nuclei show clear staining in the relevant cell population, potentially High in HPA-listed cells; predominant cytoplasmic or diffuse signal is suspect (HPA tissue IHC; UniProt Q09028).
How each factor affects the staining
Compartment and topologyRBBP4 is nuclear, localizes to chromatin as part of PRC2, and has no transmembrane segment (UniProt Q09028). Score the nuclear pattern; membrane-dominant signal does not fit that annotation.
Tissue range and strengthHPA calls expression ubiquitous and RNA tissue specificity low; its supplied examples show High nuclear staining in several cell classes (HPA tissue IHC). The list is illustrative, not a set of exclusive positive tissues.
Antibody-specific confidenceHPA lists IHC as Supported for HPA060724 and CAB006264; HPA060710 has no supplied IHC status (HPA antibodies). The tissue summary also cautions that staining may represent proteins from more than one gene (HPA tissue IHC).
Isoforms and epitope coverageUniProt lists 4 RBBP4 isoforms (UniProt Q09028). The supplied record does not map the IHC antibodies' epitopes, so it cannot establish which isoforms a particular stain detects.
IF/ICC Q&A: Where should fluorescence appear?Mainly in the nucleoplasm (HPA subcellular: Nucleoplasm, enhanced). That observation supports a nuclear localization check; IF/ICC validation does not supply an IHC-P protocol (HPA subcellular; HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No nuclear stain in an HPA-listed positive tissue.The result conflicts with its reported High IHC staining (HPA tissue IHC); a technical failure or unsuitable antibody conditions are possible (general IHC practice).Confirm the tissue and nuclear counterstain, inspect control sections, and follow the catalog antibody's IHC-P instructions for retrieval, dilution and detection (general IHC practice).
Cytoplasm or membranes stain more strongly than nuclei.The pattern conflicts with nuclear localization and absent transmembrane topology (HPA tissue IHC; UniProt Q09028); nonspecific staining is possible (general IHC practice).Compare a primary-omission control, review blocking and detection, and score only a reproducible nuclear signal (general IHC practice).
The entire section has diffuse chromogen.Background can obscure the nuclear pattern expected for RBBP4 (HPA tissue IHC); detection-system or endogenous activity may contribute (general IHC practice).Check a primary-omission control, review endogenous-activity blocking appropriate to the detection system, and reassess primary-antibody dilution (general IHC practice).
A surprising cell population stains.HPA reports ubiquitous nuclear expression and provides no negative population in this payload, so cell identity alone is inconclusive (HPA tissue IHC).First check whether its signal is nuclear; then compare controls and, where available, an independently validated IHC antibody (HPA tissue IHC; HPA antibodies; general IHC practice).
Two antibodies give different tissue patterns.The supplied IHC statuses differ, and HPA cautions that the tissue signal may include proteins from more than one gene (HPA antibodies; HPA tissue IHC).Check each antibody's IHC validation and controls, then compare nuclear patterns in the same tissue before interpreting the discrepancy (HPA antibodies; general IHC practice).
IF/ICC looks nuclear, but IHC-P is negative.HPA reports enhanced nucleoplasmic IF localization, while IHC requires its own validated staining conditions (HPA subcellular; HPA antibodies; general IHC practice).Review the IHC-validated antibody's paraffin-section instructions and IHC controls; do not infer IHC performance from the IF image alone (HPA antibodies; general IHC practice).

Sample controls for RBBP4 IHC & IF

🧪Run bone marrow first: hematopoietic cells should show nuclear staining (HPA: High in bone marrow hematopoietic cells; UniProt Q09028: nucleus). HPA lists no negative tissue and detects RBBP4 in all 45 scored tissues, so no-primary and isotype controls carry the negative comparison; within the positive slide, enucleated erythrocytes should lack nuclear staining, but they are not a validated RBBP4-negative nucleated cell population (HPA: no negative tissue; standard IHC practice).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: RBBP4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RBBP4 in HEK293, HeLa, U2OS, A-431, U-251MG, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Run a no-primary, secondary-only section and a concentration-matched nonimmune rabbit IgG isotype control alongside the test section (selected M02702 caption: rabbit primary and anti-rabbit secondary). Use an RBBP4 knockout specimen, if available, as a biological specificity control; block endogenous peroxidase in bone marrow before HRP–DAB detection (standard IHC practice; selected M02702 caption: HRP–DAB detection).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected M02702 paraffin-section caption does not state the fixative (selected M02702 caption: fixative unreported). The caption uses heat-mediated retrieval in EDTA at pH 8.0 and a 1:50 primary dilution, but does not establish that retrieval is required across specimens (selected M02702 caption). Frozen-section IHC and IF ease cannot be compared from these data; marrow's endogenous peroxidase can create background with HRP–DAB detection (standard IHC practice; selected M02702 caption: HRP–DAB detection).

HPA tissue IHC evidence for RBBP4

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: RBBP4 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced RBBP4 IHC Tips

Use nuclear staining and matched controls to troubleshoot RBBP4 chromogenic IHC; the catalog image documents paraffin sections but does not report the fixative (datasheet M02702).

How should I troubleshoot weak RBBP4 staining after antigen retrieval?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet M02702). The catalog image used this retrieval on a paraffin-embedded human lung cancer section, followed by antibody at 1:50 overnight at 4°C (datasheet M02702). If nuclear staining is weak, check that sections were fully deparaffinised and that heating was consistent across slides before changing retrieval conditions (standard IHC practice). Compare a retrieval time series on adjacent sections, keeping antibody concentration and detection constant; excessive heating can damage morphology or increase background (standard IHC practice). Judge improvement by nuclear signal and preserved tissue architecture, with a no-primary control alongside each condition (UniProt Q09028 subcellular location; standard IHC practice).
Can I infer the best fixative for RBBP4 from the catalog image?
No target-specific fixation sensitivity is established by the supplied evidence: the catalog image identifies a paraffin-embedded section but does not state its fixative (datasheet M02702). Record the fixative, fixation duration, tissue thickness and processing conditions for each specimen, because these variables affect antigen preservation and morphology in routine IHC (standard IHC practice). When signal differs between samples, compare similarly processed sections and repeat the documented EDTA pH 8.0 retrieval before attributing the difference to biology (datasheet M02702; standard IHC practice). A small fixation comparison may help optimise a local workflow, but its result requires experimental validation for this antibody (standard IHC practice). Score nuclear staining only in intact, interpretable cells (UniProt Q09028 subcellular location; standard IHC practice).
What staining pattern should count as RBBP4 positive?
Score convincing staining within intact nuclei: RBBP4 is assigned to the nucleus and chromatin, and the tissue profile describes ubiquitous nuclear expression (UniProt Q09028 subcellular location; HPA tissue IHC). Nuclear counterstain and morphology help distinguish labelled nuclei from overlying pigment, precipitate or damaged cells in chromogenic sections (standard IHC practice). Review cytoplasmic or diffuse extracellular colour against the no-primary control before calling it specific, especially where tissue edges stain strongly (standard IHC practice). HPA reports high staining in bronchial respiratory epithelial cells and bone-marrow hematopoietic cells, but these are contextual examples rather than required positives for every section (HPA tissue IHC). Record the cell population and nuclear pattern together (standard IHC practice).
Could RBBP4 isoforms or epitope masking explain inconsistent nuclear staining?
RBBP4 has 4 annotated isoforms, while the supplied catalog caption does not define the antibody epitope or establish isoform coverage (UniProt Q09028 isoforms; datasheet M02702). Avoid interpreting a weak section as loss of one isoform without an epitope map and an independent isoform-specific assay (standard IHC practice). RBBP4 associates with histones and several chromatin complexes, so accessibility may differ with preparation; that possibility needs testing rather than assuming a specific masking mechanism (UniProt Q09028 function and subunits; standard IHC practice). It also has annotated acetylated and phosphorylated residues, including phosphoserine at 110 and 355, but their effect on this antibody is unknown (UniProt Q09028 modified residues; datasheet M02702). Keep retrieval and detection matched when comparing specimens (standard IHC practice).
How can IF help assess the nuclear IHC pattern?
Use IF as an orthogonal localisation check and pair RBBP4 with a marker identifying the expected cell population in the specimen; HPA reports mainly nucleoplasmic localisation (HPA subcellular; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with low measured tissue autofluorescence, using single-stain and unstained controls (standard IF practice). Because RBBP4 is nuclear and has no transmembrane segment, optimise permeabilisation for access to the nuclear epitope after fixation (UniProt Q09028 topology and subcellular location; standard IF practice). Compare nuclear overlap with the cell marker and counterstain, while checking for bleed-through and autofluorescence before relating IF observations to chromogenic IHC (standard IF practice).
What should I check when DAB obscures RBBP4 nuclei?
Run a no-primary control to separate antibody-associated staining from tissue or detection background, and inspect pigment and precipitate at the same magnification (standard IHC practice). The catalog image used 10% goat serum blocking, peroxidase-linked secondary detection and DAB; these are documented conditions for that image, not proof that every tissue needs them (datasheet M02702). Include an appropriate endogenous peroxidase block before HRP detection and check its effectiveness in blood-rich areas (standard IHC practice). If background persists, optimise primary concentration and washes while keeping EDTA pH 8.0 retrieval fixed initially (datasheet M02702; standard IHC practice). Retain nuclear morphology as the criterion for interpretable signal (UniProt Q09028 subcellular location; standard IHC practice).
How should I quantify heterogeneous RBBP4 nuclear IHC? ⚠ ANSWER MARKED FOR VERIFICATION
Define the analysed cell population and regions before scoring, then exclude folds, necrosis and poorly preserved areas using the counterstain (standard IHC practice). For intact nuclei, report the percentage positive and staining intensity, or calculate an H-score as the sum of each intensity category multiplied by its percentage of cells (standard IHC practice). Normalise counts to the number of eligible nuclei, or express positive-cell density per mm² of viable tissue when cell abundance is itself relevant (standard IHC practice). Keep exposure, DAB development, thresholds and scoring rules consistent across a comparison, with a no-primary control to set background (standard IHC practice). Stratify by cell type because the reported tissue pattern is broadly nuclear (HPA tissue IHC).
When should an apparent RBBP4 positive be considered artefactual?
Treat staining as persuasive when it tracks intact nuclei in an anatomically identifiable cell population and exceeds the matched no-primary control (UniProt Q09028 subcellular location; standard IHC practice). Question dominant cytoplasmic or extracellular deposits, intense section-edge colour, and signal confined to necrotic regions; these patterns require artefact checks before biological interpretation (standard IHC practice). Check endogenous peroxidase activity when DAB appears in blood-rich areas, and inspect a nuclear counterstain to verify cell boundaries (standard IHC practice). HPA describes ubiquitous nuclear expression but cautions that its antibody staining may detect protein from more than one gene; its pattern alone cannot establish antibody specificity (HPA tissue IHC). Resolve unexpected patterns with an independent specificity control (standard IHC practice).
Boster reagents

Best RBBP4 / Histone-binding protein RBBP4 IHC Antibodies

RBBP4 IHC images cover human paraffin sections and mouse and rat frozen sections (catalog IHC captions). IF/ICC images cover human cells (PB9797 IF captions). All three antibodies list human, mouse, and rat reactivity (catalog reactivity).

Real IHC data IHC analysis of RbAp48 using anti-RbAp48 antibody (M02702). RbAp48 was detected in a paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-RbAp48 Antibody (M02702) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RbAp48 Rabbit Monoclonal Antibody
Cat # M02702
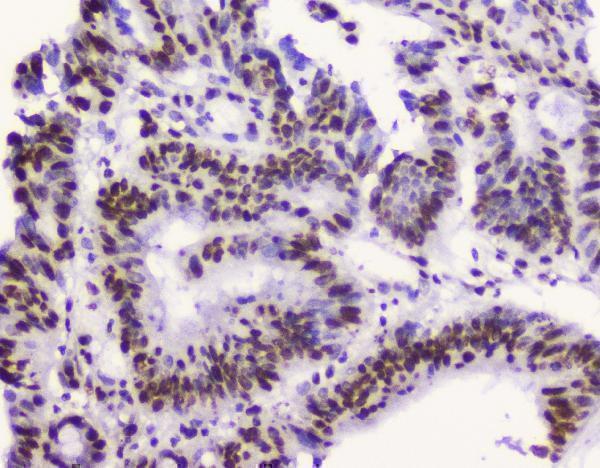
Real IHC data IHC analysis of RbAp48 using anti-RbAp48 antibody (M02702-1). RbAp48 was detected in paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2μg/ml mouse anti-RbAp48 Antibody (M02702-1) overnight at 4°C. Biotinylated goat anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1021) with DAB as the chromogen.
Anti-RbAp48 RBBP4 Antibody ® (monoclonal, 9F3)
Cat # M02702-1
Real IHC data IHC analysis of RbAp48 using anti-RbAp48 antibody (PB9797). RbAp48 was detected in paraffin-embedded section of Human Intestinal Cancer Tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-RbAp48 Antibody (PB9797) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-RbAp48/RBBP4 Antibody ®
Cat # PB9797

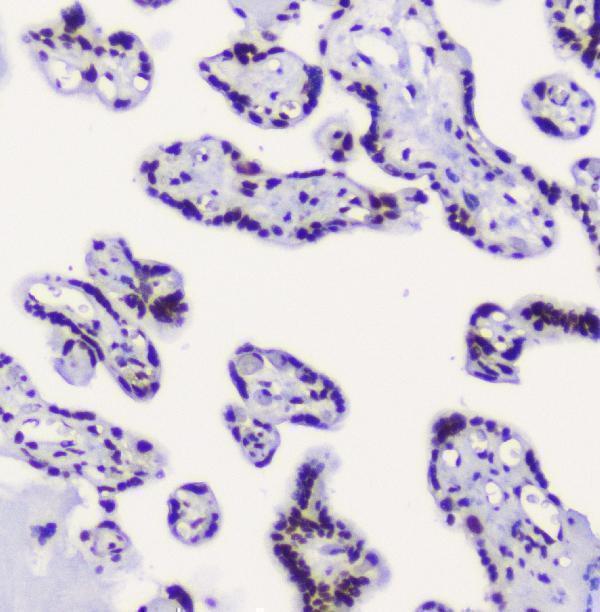
M02702 shows IHC in human lung cancer paraffin sections, while M02702-1 shows IHC in human intestinal cancer paraffin sections (respective IHC captions). PB9797 shows IHC in human intestinal cancer paraffin sections and mouse and rat frozen sections, plus IF/ICC in U2OS and A431 cells (PB9797 IHC and IF captions).

Which to pick: For paraffin tissue IHC, choose M02702 for rabbit monoclonal data with EDTA retrieval at pH 8.0, or M02702-1 for mouse monoclonal data with citrate retrieval at pH 6; PB9797 also has a paraffin citrate image (catalog host/clone fields; respective IHC captions). For IF/ICC, PB9797 has cell images, while M02702 lists IF/ICC without an IF image; for mouse or rat tissue IHC, PB9797 has frozen-section images, and all three list mouse and rat reactivity (catalog applications/reactivity; PB9797 IF and IHC captions). Fixative is unreported in the paraffin captions, so confirm fixation compatibility before use (respective IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q09028 (RBBP4_HUMAN, Histone-binding protein RBBP4).
  2. Human Protein Atlas. RBBP4 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. RBBP4 subcellular location (ICC-IF): Mainly localized to the nucleoplasm..
  4. Human Protein Atlas. RBBP4 antibody validation summary (3 antibodies).
  5. Loss of Immunohistochemical Reactivity in Association With Handling-Induced Dark Neurons in Mouse Brains. Toxicologic pathology 2020 — PMC7113115.
  6. Quantitative proteomics of HFD-induced fatty liver uncovers novel transcription factors of lipid metabolism. International journal of biological sciences 2022 — PMC9134917.
  7. Expression and clinical significance of RBBP4 gene in lower-grade glioma: An integrative analysis. Biochemistry and biophysics reports 2023 — PMC10469049.
  8. Armadillo repeat containing 12 promotes neuroblastoma progression through interaction with retinoblastoma binding protein 4. Nature communications 2018 — PMC6053364.
  9. PubMed PMID:8350924 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.