This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan RBBP9 staining in paraffin sections using the reported cytoplasmic tissue pattern (HPA tissue IHC). This guide covers fixation, interpretation, and the 2 reported isoforms (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in most tissues (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in glandular cells and other tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, heat-mediated (datasheet A09378) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09378) | |
| Caveat | Antibody staining has low consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Higher expression in carcinoma tissues (UniProt) | |
| Isoform / epitope | 2 isoforms; epitope coverage is unspecified (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet A09378) with a published RBBP9 paraffin-section IHC workflow (PMC11786897).
| Sample | Paraffin-embedded rat ovary tissue; fixative not specified (datasheet A09378) |
| Fixation | Image fixative and duration unreported (datasheet A09378); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Citrate pH 6.0 (datasheet A09378); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-RBBP9, 1:50-1:200 (datasheet A09378) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | RBBP9-positive staining in glandular cells of adrenal gland (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control. |
For paraffin-section IHC, expect predominantly cytoplasmic RBBP9 staining in cells such as glandular cells of the colon, duodenum, breast, appendix, and adrenal gland (HPA: tissue IHC). These sites are reported at medium intensity (HPA: tissue IHC). RBBP9 has no annotated transmembrane segment (UniProt O75884: topology). Treat the pattern as provisional: HPA rates tissue IHC “Approved” but reports low consistency between antibody staining and RNA expression (HPA: reliability).
| Cytoplasmic signal in colon or duodenal glandular cells, with a clear cell outline. | This matches the reported compartment and cell types; both are listed at medium staining (HPA: tissue IHC). Compare positive cells with neighboring cells on the same section, then score the proportion and intensity consistently (general IHC practice). |
| Predominantly nuclear staining in a paraffin-section IHC slide. | This differs from the reported cytoplasmic tissue IHC pattern (HPA: tissue IHC). Review the counterstain and detection controls before accepting it as RBBP9; nucleoplasmic localisation belongs to the separate ICC-IF observation (HPA: subcellular ICC-IF). |
| Strong staining in adipocytes, skin fibroblasts, or bone-marrow hematopoietic cells. | Those cell types are listed as not detected (HPA: tissue IHC). Check whether the signal tracks tissue structure or occurs in a no-primary control; cross-reactivity or endogenous detection activity is possible (general IHC practice). |
| Uniform colour across cells, stroma, and section edges. | A field-wide deposit is difficult to reconcile with cell-resolved cytoplasmic staining (HPA: tissue IHC). Review no-primary controls, blocking, washes, and detection exposure for background (general IHC practice). |
| No convincing staining in colon or duodenal glandular cells. | Both are reported at medium staining (HPA: tissue IHC), so first check tissue preservation, retrieval and detection controls (general IHC practice). A failed positive control limits interpretation of other negative areas; HPA’s low RNA–staining consistency also cautions against treating every discrepancy as technical failure (HPA: reliability). |
| Assay-specific localisation | Tissue IHC is described as cytoplasmic, while ICC-IF has a supported nucleoplasmic main location (HPA: tissue IHC; HPA: subcellular ICC-IF). Interpret each against its own assay evidence; the two observations do not establish the cause of the difference. |
| Antibody evidence | HPA015830 has “Approved” IHC status; HPA049005 has “Supported” ICC status, with no IHC status supplied for that antibody (HPA: antibodies). These labels do not make the two assays interchangeable. |
| Positive and negative comparison cells | Colon and duodenal glandular cells are reported at medium staining; adipocytes and skin fibroblasts are listed as not detected (HPA: tissue IHC). Use the named cell populations, rather than a whole-tissue label, when comparing slides. |
| Topology and isoforms | UniProt lists no transmembrane segment, no signal peptide or propeptide, one chain spanning residues 1–186, and two isoforms (UniProt O75884). Epitope position and isoform coverage are not supplied, so these entries cannot predict antibody staining differences. |
| IF/ICC Q&A | Q: Should IF/ICC show the same compartment as paraffin IHC? A: HPA reports supported nucleoplasmic ICC-IF localisation and cytoplasmic tissue IHC expression (HPA: subcellular ICC-IF; HPA: tissue IHC). Evaluate IF/ICC on its separate guide page. |
| Situation | Likely cause | Next action |
|---|---|---|
| The intended positive glandular cells have little or no signal. | The run may lack usable target detection; the cells are reported at medium staining (HPA: tissue IHC). | Check section quality, retrieval conditions, primary-antibody use and detection reagents against run controls (general IHC practice). Do not infer an RBBP9-specific fixation effect from this result. |
| The slide shows nuclear-only signal. | Its compartment differs from the reported cytoplasmic tissue IHC pattern (HPA: tissue IHC); HPA’s nucleoplasmic observation comes from ICC-IF (HPA: subcellular ICC-IF). | Verify the cellular counterstain, review antibody and detection controls, and report the compartment as a discrepancy if it persists (general IHC practice). |
| Cells listed as not detected stain strongly. | Adipocytes, skin fibroblasts and bone-marrow hematopoietic cells are listed as not detected (HPA: tissue IHC); cross-reactivity or endogenous detection activity may contribute (general IHC practice). | Compare a no-primary control and inspect whether the deposit follows a particular cell type or occurs broadly (general IHC practice). |
| Colour covers the section without clear cellular boundaries. | Diffuse deposition can obscure the reported cytoplasmic pattern (HPA: tissue IHC; general IHC practice). | Inspect no-primary controls, blocking and wash steps, and detection exposure; rescore only after cell boundaries are interpretable (general IHC practice). |
| Only low or variable signal appears across otherwise usable sections. | HPA reports low tissue RNA specificity and low consistency between antibody staining and RNA expression (HPA: tissue IHC; HPA: reliability). The supplied sources do not identify an RBBP9-specific fixation sensitivity. | Compare the same named cell populations across sections and record intensity and proportion separately; use run controls to check assay performance (general IHC practice). |
| An IF/ICC result appears nucleoplasmic while IHC is cytoplasmic. | Those are the respective reported assay observations (HPA: subcellular ICC-IF; HPA: tissue IHC). | Record assay and compartment with each result; assess IF/ICC using its separate guide, without treating either pattern alone as proof of the other (HPA: subcellular ICC-IF; HPA: tissue IHC). |
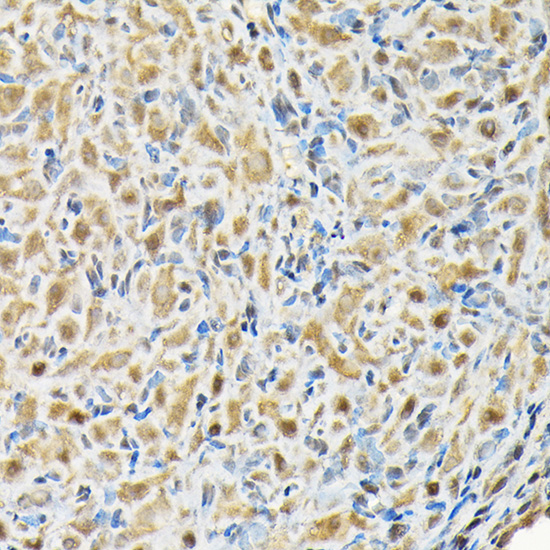
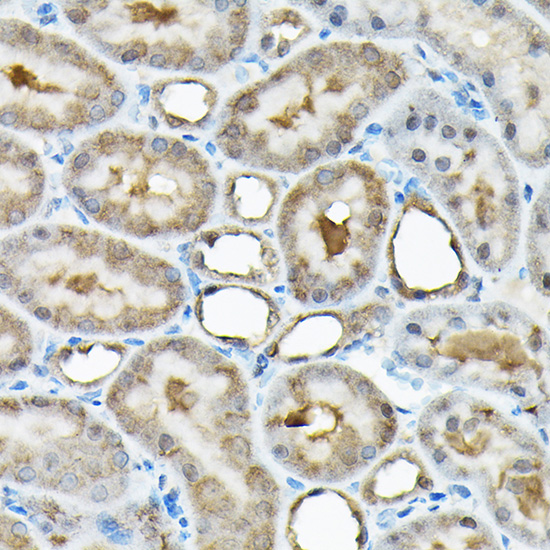



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Glandular cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Bronchus | Basal cells | Not detected | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Oral mucosa | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Use the catalog antibody’s paraffin-section image as a starting point, then judge staining against tissue morphology and the differing localisation reported by HPA.
A09378 has real IHC images of paraffin-embedded rat ovary, rat kidney and human lung cancer (catalog image captions); listed reactivity covers human, mouse and rat (catalog: reactivity).
A09378 is listed for IHC and has images from paraffin-embedded rat ovary, rat kidney and human lung cancer (catalog: applications; image captions). It is listed as reactive with human, mouse and rat, with no IF application or IF image reported (catalog: reactivity; applications; IF images).
Which to pick: Choose A09378 for paraffin-section IHC: its captions specify 1:200 and high-pressure retrieval in 10 mM citrate buffer at pH 6.0; the fixative is unreported (catalog image captions). A09378 is a rabbit polyclonal with listed human, mouse and rat reactivity, though its IHC images show only human and rat samples (catalog: host; dilution_raw; reactivity; image captions). No SKU here is listed for IF/ICC, so this payload does not support an IF/ICC pick (catalog: applications; IF images).