RCC1 / Regulator of chromosome condensation · IHC design guide

Design Immunohistochemistry for RCC1

Plan RCC1 IHC in paraffin sections around the general nuclear tissue staining pattern (HPA tissue IHC). The catalog antibody A02719-1 has an IHC dilution of 0.5–1 μg/ml (datasheet: A02719-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RCC1 (IHC for RCC1): expected localisation Predominantly nuclear tissue staining (HPA tissue IHC), antibody A02719-1, validated IHC image, and IHC protocol steps
Printable RCC1 IHC protocol sheet — expected localisation Predominantly nuclear tissue staining (HPA tissue IHC), antibody A02719-1, controls and protocol steps. Open the full RCC1 IHC guide →

RCC1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly nuclear tissue staining (HPA tissue IHC)
Staining pattern General nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02719-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02719-1)
Caveat Mitotic chromosome binding may change the pattern (UniProt)
Regulation Staining intensity varies by cell type (HPA tissue IHC)
Isoform / epitope Two isoforms; epitope coverage is unreported (UniProt)
Section 1

Recommended RCC1 IHC & IF Protocols

The catalog antibody protocol uses EDTA retrieval (datasheet: A02719-1). The published RCC1 IHC protocols below provide four tissue-specific examples (PMC5964113; PMC8051708; PMC8674189; PMC12804135).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human rectal cancer tissue; fixative not specified (datasheet A02719-1)
FixationImage fixative and duration unreported (datasheet A02719-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02719-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02719-1)
Primary antibodyRabbit anti-RCC1, 0.5-1μg/ml (datasheet A02719-1)
Primary incubationOvernight at 4 °C (datasheet A02719-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02719-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRCC1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA at pH 8.0 for the catalog antibody (datasheet: A02719-1). Citrate retrieval is a published alternative for other antibodies (PMC8051708; PMC8674189).
Section 2

What Is the Expected RCC1 Staining Pattern?

RCC1 is predominantly nuclear in interphase and binds mitotic chromosomes (UniProt P18754). In paraffin tissue sections, expect nuclear staining across multiple cell types, including strong staining in several epithelial and glandular populations (HPA: general nuclear expression; High in listed cells). The tissue profile has Enhanced reliability, reflecting agreement between staining and RNA expression (HPA: Enhanced). RCC1 has no transmembrane segment (UniProt P18754 topology).

What am I looking at on my slide?
Clear nuclear chromogenic staining in glandular or epithelial cells.This fits RCC1 localisation (UniProt P18754: predominantly nuclear) and reported High staining in breast glandular and esophageal squamous epithelial cells (HPA: tissue IHC). Compare nuclei within the same section; intensity alone does not prove antibody specificity.
Signal follows condensed chromosomes in a mitotic cell.Chromosome-associated signal is plausible during mitosis (UniProt P18754: binds mitotic chromosomes). Interpret the cell-cycle context before calling this a misplaced pattern; surrounding interphase cells should still provide a nuclear reference (UniProt P18754).
Strong, widespread cytoplasmic staining with little nuclear signal.This conflicts with the predominant interphase nuclear pattern (UniProt P18754) and general nuclear tissue profile (HPA: tissue IHC). RCC1 has a cytoplasmic annotation (UniProt P18754), so isolated cytoplasmic signal is not decisive; a dominant cytoplasmic pattern warrants an artefact check.
Strong staining is restricted to cells expected to stain weakly.Prominent cardiomyocyte or glial staining merits scrutiny because these populations are Low in the supplied tissue observations (HPA: heart muscle, hippocampus, caudate). Consider cross-reactivity or endogenous detection activity; Low is not a validated negative result.
No nuclear signal appears in a tissue selected for High staining.A blank breast glandular or esophageal squamous epithelial region conflicts with the supplied observations (HPA: High in these cells). Check tissue preservation and assay performance before interpreting absence as biology; the HPA profile does not establish fixation sensitivity.
💡Expected RCC1 appearanceA convincing positive is predominantly nuclear chromogenic signal, potentially strong in the listed glandular or epithelial cells (UniProt P18754; HPA: High), whereas dominant diffuse cytoplasmic or nonspecific background staining requires investigation (general IHC practice).
How each factor affects the staining
Cell-cycle stateInterphase nuclei and mitotic chromosomes provide different legitimate RCC1 patterns (UniProt P18754: predominant interphase nuclear localisation; mitotic chromosome binding). Record which cells are mitotic when comparing compartments.
Tissue and cell populationHigh staining is reported in several glandular and epithelial populations; cardiomyocytes and selected glia are Low (HPA: tissue IHC). Use High populations as practical reference regions, but do not treat Low populations as proven negative controls.
Antibody validationIHC is Enhanced for HPA027573 and CAB015413, and Supported for HPA027574 (HPA: antibody validation). Those grades support interpretation of their reported patterns; they do not establish equivalent performance for an unrelated catalog antibody.
Molecular formTwo isoforms are listed, with no signal peptide or transmembrane segment (UniProt P18754: isoforms, processing, topology). The payload gives no antibody epitope, so it cannot establish whether either isoform stains differently in IHC.
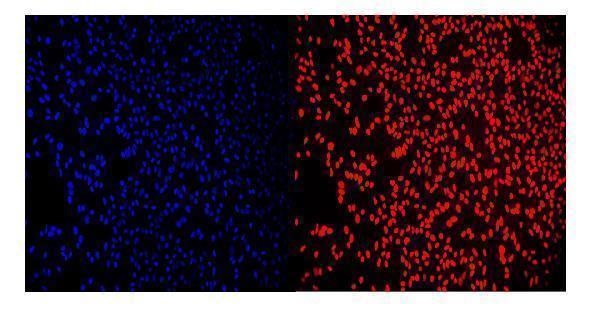
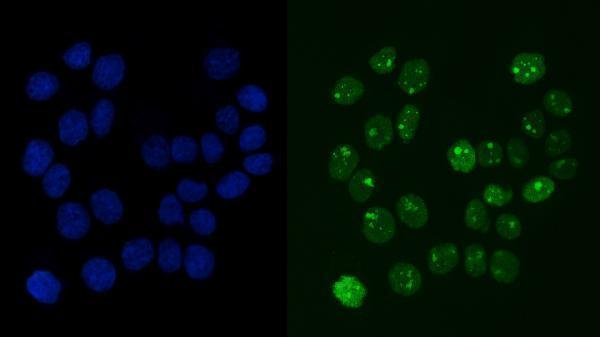
IF/ICC Q: What localisation should an IF image show?A: Expect nucleoplasmic RCC1 (HPA: ICC-IF, enhanced), consistent with predominant interphase nuclear localisation (UniProt P18754). This is a localisation cross-check only; IF/ICC assay conditions belong to its separate guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A High reference region is blank.Primary staining, retrieval, or detection may have failed (general IHC practice); breast glandular and esophageal squamous cells are High reference populations (HPA: tissue IHC).Inspect tissue morphology and assay controls, then review the validated IHC-P retrieval, primary incubation, and detection settings (general IHC practice). Do not infer RCC1-specific fixation sensitivity from HPA staining levels.
Nuclei are weak across the section.Signal may be underdeveloped or primary staining insufficient (general IHC practice); the listed High populations should offer a comparison (HPA: tissue IHC).Compare a listed High population on the same run, verify detection reagents and counterstain balance, and adjust only within the antibody's validated IHC-P instructions (general IHC practice).
Most cells show diffuse cytoplasmic colour.Background or off-target binding may dominate (general IHC practice); RCC1 is predominantly nuclear in interphase (UniProt P18754).Review blocking, primary concentration, washes, and detection controls (general IHC practice). Reassess compartment localisation in intact interphase cells before scoring the section.
Unexpected cell populations stain intensely.Cross-reactivity or endogenous enzyme activity is possible (general IHC practice), especially if the result reverses a Low observation (HPA: cardiomyocytes or selected glia Low).Check the detection-only control and endogenous activity block, then compare with a listed High population (general IHC practice; HPA: tissue IHC). Treat a Low HPA observation as a comparison, not proof of absence.
Colour obscures nuclear boundaries.Excess chromogen development or heavy counterstain can hinder localisation calls (general IHC practice).Review development time and counterstain intensity, then score only nuclei whose boundaries remain readable (general IHC practice). Avoid assigning diffuse colour to RCC1 without a distinct cellular pattern.
A mitotic cell differs from nearby interphase nuclei.RCC1 binds mitotic chromosomes while predominating in interphase nuclei (UniProt P18754).Inspect nuclear morphology and compare neighbouring interphase cells (general IHC practice). Score chromosome-associated mitotic signal separately from widespread cytoplasmic background.

Sample controls for RCC1 IHC & IF

🧪Run adrenal gland first; its glandular cells should show RCC1 staining (HPA: High in adrenal gland glandular cells). HPA detects RCC1 in all 45 scored tissues, so no negative tissue is available; use no-primary and isotype controls, and expect any enucleated erythrocytes present on the positive slide to lack nuclear staining (HPA: no negative tissues; standard IHC practice).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: None in HPA: RCC1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RCC1 in A-431, U-251MG, U2OS, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a matched rabbit IgG isotype control, and RCC1 knockout material as a biological negative (selected IHC caption: rabbit primary; standard IHC practice). Block endogenous peroxidase and, for the caption’s biotin-based detection, endogenous biotin before interpreting adrenal gland staining (selected IHC caption: biotinylated secondary and DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A02719-1 paraffin-section caption does not state a fixative (selected IHC caption: fixative unreported). That caption uses heat retrieval in EDTA at pH 8.0; it does not establish whether retrieval is required for every specimen (selected IHC caption: EDTA pH 8.0). HPA has RCC1 ICC-IF images, but the supplied evidence does not establish whether IF or frozen sections are easier; inspect adrenal sections for endogenous brown pigment before scoring DAB (HPA: ICC-IF images in A-431, U-251MG and U2OS; standard IHC practice).

HPA tissue IHC evidence for RCC1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →
Endometrium Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: RCC1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced RCC1 IHC Tips

Troubleshoot RCC1 staining in paraffin sections by checking nuclear localisation, retrieval, detection background, and how positive cells are scored.

Which retrieval should I try first when RCC1 nuclear staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02719-1). The selected image used this retrieval before overnight incubation at 4°C with 1 μg/ml catalog antibody (datasheet A02719-1). If nuclear staining remains weak, vary heating time on matched sections while keeping buffer and detection conditions constant (standard IHC practice). Compare intact cell nuclei in the same staining run and record any tissue damage or rising background as retrieval changes (standard IHC practice). HPA describes general nuclear RCC1 expression, so absent nuclear signal across intact cells warrants a check of retrieval and detection (HPA: general nuclear expression; standard IHC practice).
Could fixation explain weak RCC1 staining in my paraffin sections?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (datasheet A02719-1). Record the fixative, fixation duration, and processing history for each specimen before comparing staining intensity across sections (standard IHC practice). If material permits, stain matched sections from differently processed specimens together using EDTA at pH 8.0 and the same detection conditions (datasheet A02719-1; standard IHC practice). Assess nuclear signal alongside tissue morphology, because poor preservation can make a staining difference difficult to interpret (standard IHC practice). Neither HPA tissue patterns nor RCC1 topology establishes a fixation effect for this antibody (HPA: tissue IHC profile; UniProt P18754 topology).
Where should convincing RCC1 staining appear in chromogenic IHC?
Expect staining predominantly in interphase nuclei, with RCC1 also binding mitotic chromosomes (UniProt P18754: subcellular location). HPA reports general nuclear tissue staining and an enhanced nucleoplasmic location in cell imaging (HPA: tissue IHC profile; HPA: subcellular location). Assess intact nuclei and mitotic figures separately, using a nuclear counterstain to locate cells before judging the brown chromogen (standard IHC practice). RCC1 has no annotated transmembrane segment, so a membrane-only pattern needs additional verification rather than assignment to its established location (UniProt P18754 topology; UniProt P18754: subcellular location). Note any cytoplasmic signal without treating it alone as proof of specificity, since cytoplasm is also listed for RCC1 (UniProt P18754: subcellular location).
How should I investigate discordant RCC1 staining across antibodies or specimens?
RCC1 has 2 listed isoforms, but the supplied antibody caption does not identify its epitope or isoform coverage (UniProt P18754: isoforms; datasheet A02719-1). Before comparing antibodies, obtain each immunogen or epitope description and check whether the recognized sequence is shared (standard IHC practice). The record lists modifications at residues 2 and 11, making epitope location relevant when evaluating possible differences, without establishing an effect on this antibody (UniProt P18754: modified residues; standard IHC practice). Run candidate antibodies on adjacent sections under their documented conditions and compare nuclear patterns in the same cell populations (standard IHC practice). Treat a discordant result as unresolved until epitope information and staining controls support an explanation (standard IHC practice).
How can IF help check RCC1 localisation alongside a cell-type marker?
For a separate IF experiment, pair RCC1 with a marker for the cell population being assessed, then check whether RCC1 occupies its nuclei (UniProt P18754: predominantly nuclear; standard IF practice). Choose spectrally separated fluorophores and inspect an unstained tissue section so tissue autofluorescence does not masquerade as RCC1 signal (standard IF practice). RCC1 has no transmembrane segment and is predominantly nuclear, so use permeabilisation compatible with access to intracellular nuclear epitopes, titrated for preserved morphology (UniProt P18754 topology and subcellular location; standard IF practice). Include single-label controls when assessing channel bleed-through, and compare interphase nuclei separately from mitotic chromosomes (standard IF practice; UniProt P18754: mitotic chromosome binding). The paraffin-section caption supplies IHC conditions, not an IF fixation or permeabilisation protocol (datasheet A02719-1).
What should I check when RCC1 DAB staining is diffuse or widespread?
Separate brown nuclear signal from diffuse cytoplasmic deposits, edge staining, and pigment by examining morphology and a control lacking primary antibody (standard IHC practice). The selected paraffin-section image used 10% goat serum, a biotinylated secondary, a streptavidin–biotin complex, and DAB (datasheet A02719-1). Check the peroxidase block and secondary-only control when troubleshooting DAB background; these are general chromogenic IHC controls (standard IHC practice). With this biotin-based detection scheme, investigate tissue-associated biotin as one possible source of nonspecific signal (datasheet A02719-1; standard IHC practice). Compare background in intact nuclei with low-staining cell populations, without treating those populations as proven RCC1-negative controls (HPA: low staining in cerebellar granular-layer cells and cardiomyocytes; standard IHC practice).
How should I score RCC1 IHC when cell composition varies between sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and scoring region before measuring RCC1, then exclude damaged areas consistently (standard IHC practice). Score nuclear signal as the percentage of positive nuclei or an H-score combining nuclear intensity and positive-cell fraction (UniProt P18754: predominantly nuclear; standard IHC practice). Report the number of evaluable cells and normalise positive counts to that denominator; for spatial comparisons, report positive nuclei per mm² of viable tissue (standard IHC practice). Record mitotic figures separately if their chromosome-associated signal could shift intensity distributions (UniProt P18754: mitotic chromosome binding; standard IHC practice). HPA reports low tissue RNA specificity, so differences in cell mixture deserve explicit documentation when comparing regions (HPA: low tissue specificity; standard IHC practice).
How can I distinguish true RCC1 staining from an IHC artefact?
A credible pattern includes nuclear staining in intact interphase cells and may include mitotic chromosomes (UniProt P18754: subcellular location). HPA reports general nuclear expression and enhanced tissue IHC reliability, offering a comparison for compartment and distribution rather than proof that an individual slide is specific (HPA: tissue IHC profile and reliability; standard IHC practice). Question isolated membrane staining, strong section-edge signal, and deposits over necrotic material by comparing morphology and controls (UniProt P18754 topology; standard IHC practice). Because the selected method uses DAB with a streptavidin–biotin detection complex, inspect controls for endogenous peroxidase or biotin-related signal (datasheet A02719-1; standard IHC practice). Confirm any unexpected cell-specific pattern on a repeat section before assigning biological meaning (standard IHC practice).
Boster reagents

Best RCC1 / Regulator of chromosome condensation IHC Antibodies

Anti-RCC1 IHC images cover human and mouse paraffin sections; IF images cover human tissue sections and cultured cells (catalog image captions: A02719-1, M02719-2).

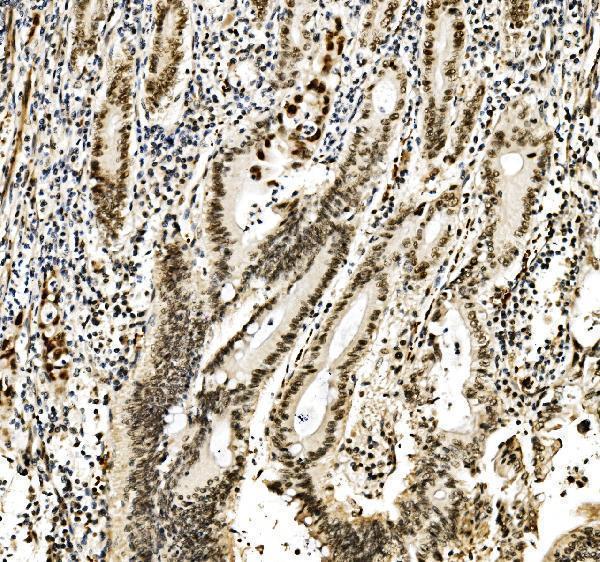
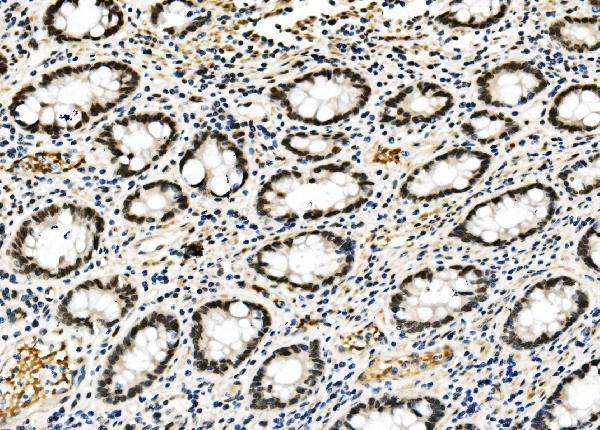
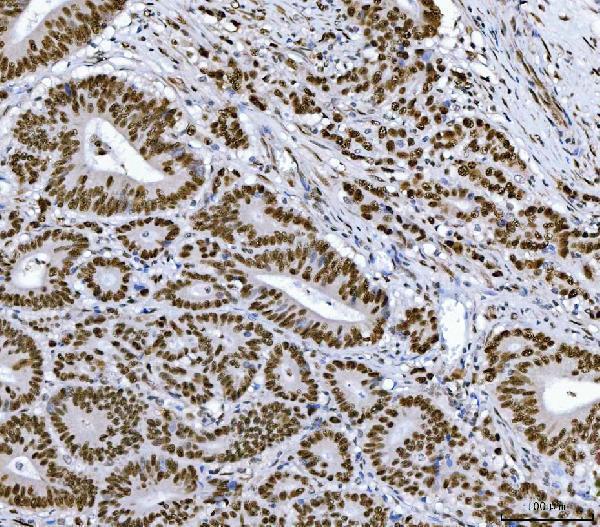
Real IHC data IHC analysis of RCC1 using anti-RCC1 antibody (A02719-1). RCC1 was detected in paraffin-embedded section of human rectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-RCC1 Antibody (A02719-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-RCC1 Antibody ®
Cat # A02719-1
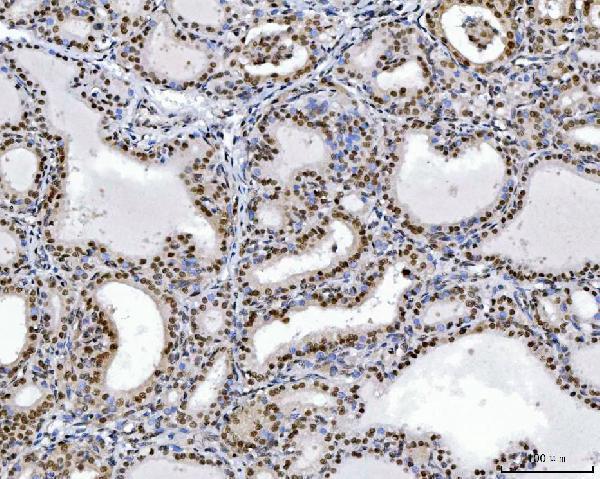
Real IHC data IHC analysis of RCC1 using anti-RCC1 antibody (M02719-2). RCC1 was detected in a paraffin-embedded section of human thyroiditis tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml mouse anti-RCC1 Antibody (M02719-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-mouse IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Mouse IgG Super Vision Assay Kit (Catalog # SV0001) with DAB as the chromogen.
Anti-RCC1 Antibody ® (monoclonal, 6B11E7)
Cat # M02719-2

A02719-1 has IHC images from paraffin sections of human rectal and lung cancers and mouse lung, plus IF images from HeLa cells and human intestine cancer sections (catalog image captions: A02719-1). M02719-2 has IHC images from paraffin sections of human thyroiditis, colorectal adenocarcinoma, breast cancer and spleen, plus an IF image from A431 cells (catalog image captions: M02719-2).

Which to pick: For paraffin tissue IHC, choose A02719-1 for human or mouse samples, or M02719-2 when a human-reactive mouse monoclonal is preferred (catalog image captions and reactivity: A02719-1, M02719-2). For IF/ICC, A02719-1 has both tissue IF and cell ICC images, while M02719-2 has a cell ICC image (catalog IF image captions: A02719-1, M02719-2). For cross-species work, A02719-1 lists human, mouse and rat reactivity, though its IHC images document human and mouse samples; both SKUs’ IHC captions report EDTA retrieval at pH 8.0 and leave the fixative unreported (catalog reactivity and IHC image captions: A02719-1, M02719-2).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P18754 (RCC1_HUMAN, Regulator of chromosome condensation).
  2. Human Protein Atlas. RCC1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. RCC1 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. RCC1 antibody validation summary (3 antibodies).
  5. Regulator of chromatin condensation 1 abrogates the G1 cell cycle checkpoint via Cdk1 in human papillomavirus E7-expressing epithelium and cervical cancer cells. Cell death & disease 2018 — PMC5964113.
  6. Down-regulation of RCC1 sensitizes immunotherapy by up-regulating PD-L1 via p27(kip1) /CDK4 axis in non-small cell lung cancer. Journal of cellular and molecular medicine 2021 — PMC8051708.
  7. RCC1 Expression as a Prognostic Marker in Colorectal Liver Oligometastases. Pathology oncology research : POR 2021 — PMC8674189.
  8. KRAS(G12D) mutation promotes pancreatic tumorigenesis by suppressing sirtuin three via the guanine nucleotide exchange factor RCC1. The Journal of biological chemistry 2026 — PMC12804135.
  9. PubMed PMID:3678831 — UniProt-cited evidence.
  10. PubMed PMID:1769659 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.