RERG / Ras-related and estrogen-regulated growth inhibitor · IHC design guide

Design Immunohistochemistry for RERG

Plan chromogenic RERG IHC in paraffin sections using cytoplasmic smooth muscle staining as a reference (HPA tissue IHC). Select controls with the reported staining–RNA inconsistency in mind (HPA tissue IHC), and start with the catalog antibody’s 1:100–1:300 IHC dilution range (datasheet A09613).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RERG (IHC for RERG): expected localisation Cytoplasmic in smooth muscle cells (HPA tissue IHC), antibody A09613, validated IHC image, and IHC protocol steps
Printable RERG IHC protocol sheet — expected localisation Cytoplasmic in smooth muscle cells (HPA tissue IHC), antibody A09613, controls and protocol steps. Open the full RERG IHC guide →

RERG Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in smooth muscle cells (HPA tissue IHC)
Staining pattern Smooth muscle cells show cytoplasmic staining (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A09613)
Positive control ⓘ Epididymis+2 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining and RNA levels show low consistency (HPA tissue IHC)
Regulation Reduced in poor-prognosis breast tumors (UniProt)
Isoform / epitope 2 isoforms; epitope impact undetermined (UniProt)
Section 1

Recommended RERG IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A09613) is followed by two published RERG IHC workflows (PMC5410235; PMC10346852).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human tonsil tissue; fixative not specified (datasheet A09613)
FixationImage fixative and duration unreported (datasheet A09613); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Tris-EDTA pH 9.0 (datasheet A09613); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-RERG, 1:100-1:300 (datasheet A09613)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRERG-positive staining in glandular cells of epididymis (HPA tissue IHC: Medium). HPA tissue profile: Cytoplasmic expression in smooth muscle. No signal in the no-primary control.
💡Decision noteStart with heat-mediated Tris-EDTA retrieval at pH 9.0 (datasheet A09613); boiled citrate buffer is a published alternative (PMC10346852).
Section 2

What Is the Expected RERG Staining Pattern?

In paraffin-section IHC, expect RERG mainly in the cytoplasm of smooth muscle cells, with medium staining reported in smooth muscle and selected glandular or ciliated cells (HPA tissue IHC). RERG is cytoplasmic and has no transmembrane segment (UniProt Q96A58). HPA rates the tissue staining Approved but reports low consistency with RNA expression, so interpret cell-specific staining with controls (HPA tissue IHC).

What am I looking at on my slide?
Smooth muscle cells show cytoplasmic chromogen at moderate intensity, while adjacent cells differ.This matches the reported medium smooth muscle signal and cytoplasmic profile (HPA tissue IHC). Compare cells within the same section before assigning positivity; HPA reports low staining–RNA consistency (HPA tissue IHC).
Strong nuclear-only or membrane-rim staining dominates a paraffin section.That differs from the cytoplasmic tissue IHC profile (HPA tissue IHC; UniProt Q96A58). Check whether the pattern persists with appropriate controls before calling it RERG; nuclear signal has separate, partly uncertain ICC-IF evidence (HPA subcellular).
Adipocytes or glial cells stain strongly while expected smooth muscle cells remain faint.HPA reports no detection in breast or adipose adipocytes and caudate glial cells, but medium smooth muscle staining (HPA tissue IHC). Consider cross-reactivity or endogenous detection activity and inspect control sections (general IHC practice).
Chromogen coats many structures diffusely without clear cell boundaries or cytoplasmic enrichment.A widespread haze cannot establish the cell-specific cytoplasmic pattern reported for RERG (HPA tissue IHC). Review background and reagent controls, blocking, washes, and detection conditions (general IHC practice).
A smooth muscle control section has no discernible cytoplasmic staining.That conflicts with the reported medium smooth muscle signal (HPA tissue IHC). Treat the run as inconclusive until section integrity, retrieval, antibody application, and detection controls are checked (general IHC practice).
💡Expected RERG appearanceCall a positive paraffin-section result when smooth muscle cells show distinct, approximately medium cytoplasmic staining (HPA tissue IHC); strong nuclear-only, membrane-rim, or widespread background signal needs control-based review before attribution to RERG (HPA tissue IHC; UniProt Q96A58; general IHC practice).
How each factor affects the staining
Tissue and cell contextMedium signal is reported in smooth muscle cells, epididymal glandular cells, and fallopian-tube ciliary rootlets (HPA tissue IHC). Evaluate the named cells, since a whole-tissue label alone cannot predict every cell's result (HPA tissue IHC).
Antibody evidenceThe listed antibody HPA041387 is Approved for IHC, while HPA reports low consistency between tissue staining and RNA expression (HPA antibodies; HPA tissue IHC). Use that limitation when interpreting weak or unexpected staining.
Compartment and topologyUniProt assigns RERG to cytoplasm and reports no transmembrane segment (UniProt Q96A58). A membrane-rim pattern alone lacks support from that annotation; examine whether cytoplasmic signal accompanies it.
Isoforms and processingUniProt lists two isoforms, no signal peptide or propeptide, and one annotated chain spanning residues 1–199 (UniProt Q96A58). These annotations do not identify the antibody epitope or predict which isoform this IHC assay detects.
ICC-IF comparisonHPA reports supported cytosol and uncertain nucleoplasm and nucleolar fibrillar-center locations in ICC-IF (HPA subcellular). Those cell-image observations do not establish an expected nuclear pattern in paraffin tissue IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The smooth muscle control is blank or much weaker than expected.A failed staining run or unsuitable assay conditions are possible; HPA reports medium smooth muscle staining (HPA tissue IHC).Verify tissue morphology and control performance, then review retrieval, antibody application, and chromogenic detection against the validated IHC procedure (general IHC practice).
Adipocytes stain as strongly as smooth muscle cells.That distribution conflicts with reported non-detection in adipocytes and medium staining in smooth muscle cells (HPA tissue IHC); nonspecific binding or endogenous activity is possible.Compare a no-primary control and the expected cell populations; check blocking and detection reagents before assigning adipocyte signal to RERG (general IHC practice).
A section has diffuse brown haze across cells and stroma.The haze obscures the expected cell-specific cytoplasmic pattern (HPA tissue IHC); background from the detection workflow is possible (general IHC practice).Inspect no-primary and reagent controls, then review blocking, washes, incubation conditions, and chromogen development (general IHC practice).
Only nuclei stain in paraffin tissue.Nuclear-only tissue staining differs from the cytoplasmic IHC profile (HPA tissue IHC); HPA calls nucleoplasm localization uncertain in ICC-IF (HPA subcellular).Check controls and whether cytoplasmic smooth muscle staining is present before interpreting the nuclear signal as RERG (HPA tissue IHC; general IHC practice).
A negative-reference cell population shows isolated positive cells.HPA reports non-detection for specified populations, including adipocytes and caudate glial cells, but its tissue IHC has low RNA consistency (HPA tissue IHC).Confirm the cell identity and compare matched controls; report the observed pattern with its HPA limitation instead of treating one discrepant cell as definitive (HPA tissue IHC; general IHC practice).
Q: Can nuclear ICC-IF staining set the acceptance rule for tissue IHC?A: HPA supports cytosol but marks nucleoplasm and nucleolar fibrillar-center ICC-IF localization uncertain (HPA subcellular).Judge paraffin tissue against the reported cytoplasmic smooth muscle pattern (HPA tissue IHC); interpret ICC-IF on its own guide page (HPA subcellular).

Sample controls for RERG IHC & IF

🧪Run epididymis first; its glandular cells should stain at the reported Medium level (HPA: epididymis, glandular cells, Medium). Use adipose tissue adipocytes as the negative comparison (HPA: adipocytes, Not detected); on the epididymis slide, cells outside the glandular compartment should show only background, though HPA does not establish that each is RERG-negative (HPA: epididymis glandular-cell annotation).
Positive control tissue: Epididymis (Glandular cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RERG in EFO-21, HeLa, U2OS, with annotated localisation: Nucleoplasm (uncertain), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a primary-host-matched isotype control, using matched IgG for a monoclonal antibody or normal IgG for a polyclonal antibody; use validated RERG-knockout material or a peptide-blocked primary when the immunizing peptide is available (standard IHC/IF controls). For chromogenic epididymis IHC, block endogenous peroxidase and check background staining; for IF, check tissue autofluorescence with the no-primary control (standard IHC/IF practice).
⚠️Feasibility: The selected A09613 paraffin-section caption uses Tris-EDTA at pH 9.0 for retrieval and a 1:200 primary dilution, but reports no fixative (A09613 tissue-IHC caption). A RERG-specific fixation window or fixation effect is unreported; the caption supports testing its retrieval conditions, while the supplied evidence does not establish that frozen sections or tissue IF would be easier (A09613 tissue-IHC caption; HPA: ICC-IF images in EFO-21, HeLa and U2OS). No epididymis-specific artefact is reported in the supplied evidence; assess peroxidase background for IHC or autofluorescence for IF (standard IHC/IF practice).

HPA tissue IHC evidence for RERG

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Epididymis Glandular cells Medium Protein (IHC) HPA →
Fallopian tube Ciliated cells (ciliary rootlets) Medium Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced RERG IHC Tips

Troubleshoot RERG staining in paraffin sections using the catalog antibody’s tissue image, reported localisation, and appropriate controls.

Which retrieval conditions should I try first for weak RERG staining?
Start with heat-mediated retrieval in Tris-EDTA at pH 9.0 for paraffin sections (datasheet A09613). The selected human tonsil image used this buffer, followed by primary antibody at 1:200 overnight at 4°C (caption A09613). If staining remains weak, compare a shorter and longer heating interval on adjacent sections while keeping antibody concentration and detection constant (standard IHC practice). Use sections processed together, and record the heating duration and cooling conditions so that any improvement can be reproduced (standard IHC practice). Check whether stronger signal retains a plausible cytoplasmic pattern before accepting the retrieval change (UniProt Q96A58 localisation; HPA tissue IHC).
Could fixation explain variable RERG staining across paraffin blocks?
RERG-specific sensitivity to fixation is unknown from the supplied evidence, and the selected paraffin-section caption does not state a fixative (caption A09613). Compare blocks only after recording their documented fixative, time in fixative, processing history, section age, and storage conditions (standard IHC practice). On matched sections, hold Tris-EDTA retrieval at pH 9.0 and primary dilution at 1:200 constant while evaluating signal (datasheet A09613; caption A09613). Include an on-slide reference section where possible, and assess staining in intact cells away from damaged edges (standard IHC practice). Differences between blocks alone do not establish a RERG-specific fixation effect (caption A09613).
How should I assess nuclear staining when I expect cytoplasmic RERG?
Prioritise a cytoplasmic pattern when assessing paraffin-section staining because UniProt places RERG in the cytoplasm and HPA reports cytoplasmic expression in smooth muscle (UniProt Q96A58 localisation; HPA tissue IHC). HPA cell imaging also reports supported cytosol staining and uncertain nucleoplasm and nucleolar fibrillar-centre staining (HPA subcellular). Therefore, score nuclear staining separately from cytoplasmic staining, and compare its distribution with the counterstain and adjacent control sections (standard IHC practice). If nuclear-only signal persists, check secondary-only and antibody-specificity controls before assigning it to RERG (standard IHC practice). Record the cell type and compartment explicitly, since tissue-level staining is not uniform across cell populations (HPA tissue IHC).
Can this antibody distinguish RERG isoforms in paraffin sections?
RERG has 2 annotated isoforms, but the supplied evidence does not map this antibody’s epitope to either one (UniProt Q96A58 isoforms; caption A09613). Treat chromogenic staining as RERG-associated until epitope information or an isoform-selective control supports a narrower claim (standard IHC interpretation). UniProt describes a 199-residue chain without an annotated signal peptide, transmembrane segment, glycosylation site, or modified residue (UniProt Q96A58 processing, topology and PTMs). Those annotations cannot establish which epitope survives paraffin processing or retrieval (UniProt Q96A58; caption A09613). If isoform identity matters, pair staining with an independently validated isoform-resolved assay and report what each measurement identifies (standard IHC practice).
How can I investigate RERG localisation by IF alongside paraffin-section IHC?
For the separate IF/ICC workflow, multiplex RERG with a validated smooth-muscle marker to assess the cell type highlighted by tissue IHC (HPA tissue IHC). Choose a fluorophore channel after inspecting unstained tissue autofluorescence, and include single-colour controls to evaluate bleed-through (standard IF practice). For an intracellular epitope, optimise mild permeabilisation after fixation, because RERG has no annotated transmembrane segment and cytosolic localisation is supported (UniProt Q96A58 topology; HPA subcellular). The supplied evidence does not establish IF fixation or permeabilisation conditions for this antibody, so document both during optimisation (HPA subcellular; caption A09613). Compare compartments cautiously across methods, especially for nuclear signal classed as uncertain by HPA (HPA subcellular).
What should I check when RERG chromogenic staining appears diffuse or widespread?
Inspect a section without primary antibody to assess secondary-reagent signal, and block endogenous peroxidase before DAB development as standard chromogenic IHC controls (standard IHC practice). Compare staining at the caption’s 1:200 primary dilution with a more dilute condition while keeping retrieval and development time fixed (caption A09613; standard IHC practice). If diffuse colour tracks section edges, folds, or damaged areas, evaluate intact interior tissue separately (standard IHC practice). Apply a consistent blocking and wash schedule across comparison sections, and record whether background changes with primary dilution (standard IHC practice). Give greater weight to cell-associated cytoplasmic staining than to diffuse extracellular colour when evaluating RERG (UniProt Q96A58 localisation; HPA tissue IHC).
How should I quantify RERG staining across heterogeneous paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic scoring compartment before reviewing outcomes, using the reported smooth-muscle pattern where that population is present (HPA tissue IHC). An H-score can combine the percentage of positive cells with intensity categories of 0–3; alternatively, report percentage positive cells within the defined population (standard IHC scoring practice). If counting discrete positive cells, report density per mm² of viable analysed tissue and state the segmentation rules (standard IHC quantification practice). Normalise counts to eligible cells or viable tissue area, and keep section thickness, staining batch, illumination, and threshold rules consistent (standard IHC practice). Report nuclear and cytoplasmic measurements separately if both occur (HPA subcellular; standard IHC practice).
What makes an apparent RERG-positive cell convincing rather than artefactual?
Look for reproducible, cell-associated cytoplasmic staining in intact cells; HPA reports cytoplasmic expression in smooth muscle, while UniProt places RERG in the cytoplasm (HPA tissue IHC; UniProt Q96A58 localisation). Check the stained cell type against morphology and a serial-section marker before assigning signal to smooth muscle or another population (standard IHC practice). Treat isolated nuclear-only colour, edge accentuation, necrotic areas, and pigment-like deposits cautiously, using a secondary-only control and an endogenous-peroxidase check (HPA subcellular; standard IHC practice). HPA labels its tissue evidence Approved but reports low consistency between antibody staining and RNA expression (HPA tissue IHC). Interpret a strong signal alongside controls and independent evidence, especially when its compartment or cell distribution is unexpected (standard IHC practice).
Boster reagents

Best RERG / Ras-related and estrogen-regulated growth inhibitor IHC Antibodies

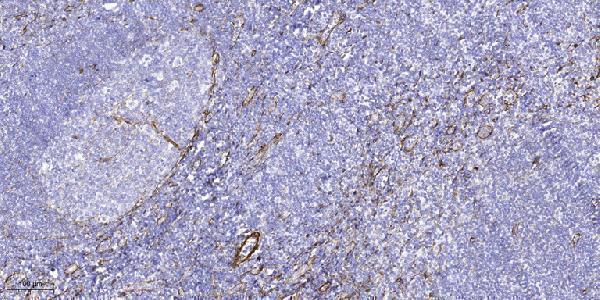
A09613 is listed for human and mouse IHC and IF (catalog: applications/reactivity); its IHC image shows paraffin-embedded human tonsil (A09613 image caption).

Real IHC data Immunohistochemical analysis of paraffin-embedded human tonsil. 1, Tris-EDTA, pH9.0 was used for antigen retrieval. 2 Antibody was diluted at 1:200 (4° overnight.3, Secondary antibody was diluted at 1:200 (room temperature, 45min).
Anti-RERG Antibody
Cat # A09613

A09613 lists IHC and IF applications with human and mouse reactivity (catalog: applications/reactivity). Its IHC image documents paraffin-embedded human tonsil, Tris-EDTA retrieval at pH 9.0, and a 1:200 primary dilution (A09613 image caption).

Which to pick: For tissue IHC, choose A09613, a rabbit polyclonal listed at 1:100–1:300 (catalog: host/clonality/IHC dilution); its image supports paraffin sections, and the fixative is unreported (A09613 image caption). For IF, A09613 is listed at 1:50, but no IF image or ICC application is supplied (catalog: IF dilution/IF image alts/applications). For human and mouse studies, A09613 lists reactivity with both species, while its shown IHC result is human tonsil (catalog: reactivity; A09613 image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q96A58 (RERG_HUMAN, Ras-related and estrogen-regulated growth inhibitor).
  2. Human Protein Atlas. RERG tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. RERG subcellular location (ICC-IF): Mainly localized to the nucleoplasm and cytosol. In addition localized to the nucleoli fibrillar center..
  4. Human Protein Atlas. RERG antibody validation summary (1 antibodies).
  5. MicroRNA-382-5p aggravates breast cancer progression by regulating the RERG/Ras/ERK signaling axis. Oncotarget 2017 — PMC5410235.
  6. Missing link between tissue specific expressing pattern of ERβ and the clinical manifestations in LGBLEL. Frontiers in medicine 2023 — PMC10346852.
  7. RERG suppresses cell proliferation, migration and angiogenesis through ERK/NF-κB signaling pathway in nasopharyngeal carcinoma. Journal of experimental & clinical cancer research : CR 2017 — PMC5490152.
  8. PubMed PMID:11533059 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.
  10. PubMed PMID:16541075 — UniProt-cited evidence.