This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section RILPL2 IHC using bone marrow hematopoietic cells, which show medium staining, as a positive reference (HPA tissue IHC). The catalog antibody starts at 2.5 μg/mL (datasheet); expect mainly cytoplasmic staining and interpret it cautiously because antibody staining has low consistency with RNA data (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Mainly cytoplasmic in most tissues (HPA tissue IHC) | |
| Staining pattern | Mainly cytoplasmic staining across tissues (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | Esophagus+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining has low consistency with RNA data (HPA tissue IHC) | |
| Regulation | No expression regulator reported (UniProt) | |
| Isoform / epitope | 0 isoforms; one 1–211 chain, with no transmembrane segment (UniProt) |
The catalog antibody IHC-P protocol is accompanied by a published RILPL2 tissue microarray IHC method (PMC11564405).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A14157); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-RILPL2, 2.5 μg/mL (datasheet A14157) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | RILPL2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: Mainly cytoplasmic expression in most tissues. No signal in the no-primary control. |
RILPL2 is a cytosolic protein without a transmembrane segment (UniProt Q969X0). In paraffin-section IHC, expect mainly cytoplasmic staining across many tissues, including medium staining in bone-marrow hematopoietic cells and bronchial respiratory epithelial cells (HPA tissue IHC). Treat this as a provisional pattern: HPA rates the IHC staining Approved, but reports low consistency with RNA expression and says external verification is pending (HPA tissue IHC).
| Cytoplasmic chromogen in bone-marrow hematopoietic cells or bronchial respiratory epithelial cells. | This matches the cell compartments and Medium staining reported for those cells (HPA tissue IHC). Compare signal with neighboring cells and background on the same slide; a matching pattern alone does not resolve HPA's stated RNA–staining inconsistency (HPA tissue IHC). |
| Predominantly nuclear staining, or an apparent cell-surface rim with little cytoplasmic signal. | These compartments diverge from the mainly cytoplasmic tissue pattern (HPA tissue IHC) and cytosolic location (UniProt Q969X0; HPA subcellular). Review morphology and detection controls before interpreting the signal as RILPL2 (general IHC practice). |
| Strong staining in esophageal or vaginal squamous epithelial cells, or skeletal-muscle myocytes. | HPA reports RILPL2 as Not detected in those specific cell populations (HPA tissue IHC). Assess cross-reactivity and endogenous detection activity; the HPA result does not mean every cell in those tissues must be unstained (general IHC practice; HPA tissue IHC). |
| Uniform chromogen across tissue, extracellular spaces, and cells expected to differ. | A diffuse pattern obscures the cell-restricted cytoplasmic interpretation (HPA tissue IHC). Check whether background persists when primary antibody is omitted and inspect blocking, washing, and chromogen development (general IHC practice). |
| No cytoplasmic signal in a selected HPA-positive cell population. | A negative result warrants a technical check, but HPA calls its listed positive populations Medium, not uniformly strong (HPA tissue IHC). Confirm that the relevant cells are present, then review section quality, retrieval, detection, and antibody conditions (general IHC practice). |
| Expected compartment | RILPL2 has no transmembrane segment and is annotated in cytosol, centrosome, and cilium (UniProt Q969X0). Tissue IHC is mainly cytoplasmic (HPA tissue IHC); a possible small ciliary or centrosomal focus should not replace the broader cytoplasmic assessment. |
| Cell-specific tissue evidence | HPA reports Medium staining in adipocytes, adrenal glandular cells, Purkinje cells, and several other listed populations, but Not detected in specified squamous epithelial and muscle cells (HPA tissue IHC). Score the named cell type, not the entire tissue. |
| Validation strength | The listed rabbit polyclonal antibody HPA028958 is IHC Approved, while the tissue profile has low consistency with RNA and awaits external verification (HPA antibodies; HPA tissue IHC). Interpret an unexpected pattern cautiously and use appropriate controls (general IHC practice). |
| Does IF/ICC show the same location? | HPA ICC-IF supports a mainly cytosolic location, with additional vesicle and primary-cilium locations marked Approved (HPA subcellular). Those finer structures can help interpret localization, but this section supplies no IF/ICC protocol (HPA subcellular). |
| Situation | Likely cause | Next action |
|---|---|---|
| The expected positive cells show no chromogen. | The selected section may lack the relevant cells, or the IHC workflow may have failed; HPA's reported signal in those cells is Medium (HPA tissue IHC; general IHC practice). | Locate the named cell population on the counterstained section. Check a concurrently processed positive control, then review retrieval, primary-antibody conditions, and detection according to the antibody's IHC-P instructions (general IHC practice). |
| Signal is mainly nuclear. | This conflicts with cytosolic localization and mainly cytoplasmic tissue staining (UniProt Q969X0; HPA tissue IHC). Nonspecific staining or misread tissue morphology is possible (general IHC practice). | Compare nuclei and cytoplasm against the counterstain, inspect a primary-antibody-omission control, and reassess the result in an HPA-listed positive cell type (general IHC practice; HPA tissue IHC). |
| Strong chromogen appears in an HPA-undetected cell population. | For example, HPA reports esophageal squamous epithelial cells as Not detected (HPA tissue IHC). Cross-reactivity or endogenous detection activity can mimic a positive result (general IHC practice). | Verify cell identity and compare with a primary-antibody-omission control. If the detection system uses peroxidase, assess endogenous peroxidase blocking (general IHC practice). |
| Diffuse background makes cell boundaries hard to score. | Nonselective detection, insufficient blocking or washing, or excessive chromogen development can obscure a cytoplasmic pattern (general IHC practice; HPA tissue IHC). | Compare an omission control and a positive section processed together; adjust blocking, washing, and development within the detection system's instructions (general IHC practice). |
| A small punctum is the only apparent positive signal. | Centrosomal or ciliary localization is annotated, but HPA describes tissue IHC as mainly cytoplasmic (UniProt Q969X0; HPA tissue IHC). A punctum alone is hard to assign in chromogenic sections (general IHC practice). | Confirm the structure and cell identity at suitable magnification, then look for reproducible cytoplasmic staining in an HPA-listed positive population (general IHC practice; HPA tissue IHC). |
| Positive and negative populations stain alike. | HPA reports different staining levels for specified cell types, although its tissue pattern has low consistency with RNA expression (HPA tissue IHC). Uniform staining may also reflect background (general IHC practice). | Score each named cell population separately, compare the omission control, and report the discrepancy without treating HPA's Approved rating as independent confirmation of specificity (general IHC practice; HPA tissue IHC). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Lymphoid tissue | Medium | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Medium | Protein (IHC) | HPA → |
| Breast | Adipocytes | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Parathyroid gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
| Smooth muscle | Smooth muscle cells | Not detected | Protein (IHC) | HPA → |
| Vagina | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot RILPL2 staining in paraffin sections by checking retrieval, cellular distribution and controls before comparing signal across samples.
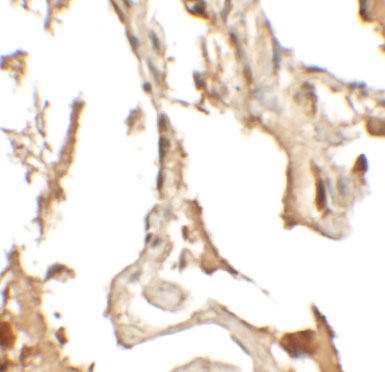
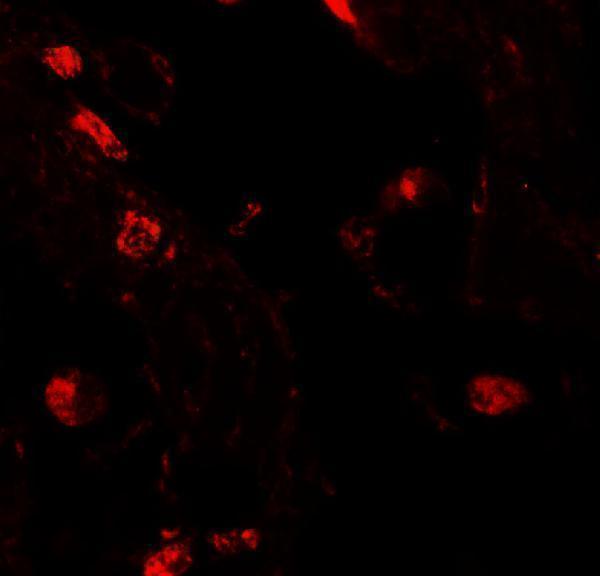
A14157 is listed for human IHC-P and IF, with IHC and IF images from human lung tissue (catalog: applications and reactivity; image captions).
A14157 has an IHC image of human lung tissue at 2.5 μg/mL (IHC image caption). A14157 also has an IF image of human lung tissue at 20 μg/mL (IF image caption).
Which to pick: For paraffin-section tissue IHC, choose A14157: it is a rabbit antibody listed for human IHC-P, and its own IHC image shows human lung tissue (catalog: host, reactivity and applications; IHC image caption). For IF, choose A14157 based on its human lung image; ICC validation is unreported (catalog: applications; IF image caption). No cross-species option is supported because A14157 lists only human reactivity; its IHC caption does not report a fixative (catalog: reactivity; IHC image caption).