RPL23 / Large ribosomal subunit protein uL14 · IHC design guide

Design Immunohistochemistry for RPL23

Plan RPL23 paraffin IHC around granular cytoplasmic staining (HPA tissue IHC). Start with 2–5 μg/ml of the IHC-validated antibody (datasheet A06155-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RPL23 (IHC for RPL23): expected localisation Granular cytoplasm in tissue sections (HPA tissue IHC), antibody A06155-2, validated IHC image, and IHC protocol steps
Printable RPL23 IHC protocol sheet — expected localisation Granular cytoplasm in tissue sections (HPA tissue IHC), antibody A06155-2, controls and protocol steps. Open the full RPL23 IHC guide →

RPL23 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm in tissue sections (HPA tissue IHC)
Staining pattern Granular cytoplasmic staining across tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06155-2)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Smooth muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat Smooth muscle cells may lack staining (HPA tissue IHC)
Regulation No specific regulator annotated (UniProt)
Isoform / epitope No annotated isoforms or processing variants (UniProt)
Section 1

Recommended RPL23 IHC & IF Protocols

The catalog antibody protocol is followed by published RPL23 IHC methods for hepatocellular carcinoma tissue (PMC8677661) and bone marrow trephine biopsies (PMC5443795).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendiceal adenocarcinoma tissue; fixative not specified (datasheet A06155-2)
FixationImage fixative and duration unreported (datasheet A06155-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06155-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06155-2)
Primary antibodyRabbit anti-RPL23, 2-5 μg/ml (datasheet A06155-2)
Primary incubationOvernight at 4 °C (datasheet A06155-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A06155-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRPL23-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression with a granular pattern in all tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A06155-2); consider citrate retrieval at 105 °C for 20 min for the hepatocellular carcinoma method (PMC8677661).
Section 2

What Is the Expected RPL23 Staining Pattern?

RPL23 is a cytoplasmic component of the large ribosomal subunit and has no transmembrane segment (UniProt P62829). In paraffin sections, expect granular cytoplasmic staining across many tissues, with strong staining in several epithelial and neuronal cell populations (HPA tissue IHC). HPA rates its tissue IHC profile Approved, with medium consistency between antibody staining and RNA expression data (HPA tissue IHC).

What am I looking at on my slide?
Granular cytoplasmic staining in colon glandular cells or bronchial respiratory epithelial cells.This matches the reported compartment and examples of high staining (HPA tissue IHC). Judge the pattern within identified cells; an HPA high call does not require every cell in the section to look equally dark.
Predominantly nuclear or membrane outlined staining, with little granular cytoplasmic signal.This conflicts with the cytoplasmic tissue pattern (HPA tissue IHC) and cytoplasmic assignment (UniProt P62829). Treat the compartment mismatch as a possible artefact; review morphology and staining controls before scoring it as RPL23.
Strong staining in smooth muscle cells while expected positive cells stain weakly or remain clear.HPA reports RPL23 as not detected in smooth muscle cells (HPA tissue IHC). This reversal raises concern for cross reactivity or endogenous detection activity; it does not establish either cause by itself.
Color spreads through stroma, lumens, or much of the section without clear cell boundaries.The diffuse deposit cannot be read confidently as the reported granular cytoplasmic pattern (HPA tissue IHC). Background from a general IHC detection step is a possibility (standard IHC practice); compare with controls before assigning cellular signal.
No staining in colon glandular cells in an otherwise interpretable section.Colon glandular cells are a high staining example (HPA tissue IHC), so this is an unexpected negative. First check whether the positive control and section detection worked (standard IHC practice); absence here alone cannot establish absent RPL23.
💡Expected RPL23 appearanceCall a result positive when identified epithelial or neuronal cells show granular cytoplasmic staining, potentially strong in HPA high examples; dominant nuclear staining or diffuse noncellular color is suspicious (HPA tissue IHC; UniProt P62829).
How each factor affects the staining
Tissue and cell selectionHPA reports high staining in colon glandular cells and cerebellar Purkinje cells, but low staining in ovarian stroma cells and no detection in smooth muscle cells (HPA tissue IHC). Choose controls at the named cell level, not from tissue name alone.
Compartment and textureThe expected tissue pattern is granular and cytoplasmic (HPA tissue IHC). RPL23 is a large ribosomal subunit component assigned to the cytoplasm (UniProt P62829); assess signal within cells rather than treating any brown deposit as positive.
Antibody evidenceHPA lists HPA003373 as Approved for IHC, while its tissue profile has medium consistency with RNA expression (HPA antibodies; HPA tissue IHC). An unexpected pattern therefore needs control based review rather than automatic acceptance.
Protein annotationUniProt lists one chain spanning residues 1–140, no signal peptide or propeptide, and no transmembrane segment (UniProt P62829). These annotations support a cellular cytoplasmic reading; they do not establish an antigen retrieval condition or fixation sensitivity.
IF/ICC Q&A: where should fluorescence appear?Expect cytosolic signal: HPA calls the cytosol its supported main location in ICC-IF (HPA subcellular). This is an interpretation cue for the separate IF/ICC guide, not an IF protocol or a claim that fluorescence intensity matches paraffin IHC.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No signal in a high staining reference section.A technical failure is possible when expected colon glandular cells or bronchial respiratory epithelial cells are blank (HPA tissue IHC).Confirm the section contains the named cells, then inspect the positive control, primary antibody step, detection reagents, and counterstain (standard IHC practice). Do not infer target absence until the run is interpretable.
Widespread brown haze obscures cell boundaries.Diffuse color is hard to reconcile with granular cytoplasmic staining (HPA tissue IHC); nonspecific detection background is possible (standard IHC practice).Compare a no primary control, inspect washing and blocking steps, and score only deposits that can be assigned to cells (standard IHC practice). Reassess the tissue pattern after background is controlled.
Nuclei dominate the staining.A nuclear dominant result disagrees with the cytoplasmic tissue profile (HPA tissue IHC) and UniProt cytoplasmic location (UniProt P62829).Check the hematoxylin counterstain against the chromogen and review a positive control (standard IHC practice). Record the nuclear pattern as discordant if it persists.
Smooth muscle cells stain strongly.HPA calls smooth muscle cells not detected (HPA tissue IHC); cross reactivity or endogenous detection activity is possible, but the image alone cannot distinguish them.Compare a no primary control and an HPA high cell population on the same run where available (standard IHC practice; HPA tissue IHC). Do not use smooth muscle staining alone as confirmation.
Cells show uniform cytoplasmic color without visible granularity.A uniform appearance differs from HPA's reported granular cytoplasmic profile (HPA tissue IHC), although section detail may limit pattern assessment (standard IHC practice).Examine well preserved cells at suitable magnification and compare the positive control (standard IHC practice). Score localisation separately from pattern quality when granularity cannot be resolved.
A low staining population appears weaker than a high staining population.This can fit the reference: ovarian stroma cells are low, while colon glandular cells are high (HPA tissue IHC).Identify each cell population before comparing intensity. Use the HPA cell level calls as context and check run controls before treating a low signal as assay failure (HPA tissue IHC; standard IHC practice).

Sample controls for RPL23 IHC & IF

🧪Run appendix first: glandular cells should stain (HPA: High in appendix glandular cells). Use smooth muscle as the negative tissue; smooth muscle cells within the appendix section, if present, should lack specific staining (HPA: Not detected in smooth muscle cells).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Smooth muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RPL23 in A-431, U-251MG, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and rabbit IgG isotype controls matched to the primary antibody’s clonality where known, plus a verified RPL23 knockout sample as a biological negative (caption: rabbit anti-RPL23 antibody). Quench endogenous peroxidase and check for endogenous biotin background when using the caption’s SABC–DAB detection (caption: SABC–DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A06155-2 paraffin-section caption does not state a fixative. Heat-mediated retrieval in EDTA at pH 8.0 was used, but retrieval dependence is unreported (caption: EDTA pH 8.0). Frozen sections are not established as easier; ICC-IF shows supported cytosolic localisation, while glandular background should be checked against controls on the appendix slide (HPA: Cytosol supported; HPA: High in appendix glandular cells).

HPA tissue IHC evidence for RPL23

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced RPL23 IHC Tips

Troubleshoot RPL23 staining in paraffin sections by checking retrieval, cytoplasmic localisation, controls and cell-specific scoring (datasheet A06155-2; HPA tissue IHC).

Which retrieval condition should I start with for RPL23 IHC?
Use heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A06155-2). The selected tissue image used this condition before incubation with 2 μg/ml antibody overnight at 4°C, so keep those settings together for the first comparison (datasheet A06155-2). If staining is weak, adjust heating duration in a small test series while keeping section thickness, detection and exposure to DAB consistent (standard IHC practice). Compare cytoplasmic granular staining in viable glandular cells with background in adjacent tissue, because the expected pattern is granular and cytoplasmic (HPA tissue IHC).
How should I investigate fixation-related loss of RPL23 staining?
The selected caption identifies a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity is unknown (datasheet A06155-2). Record the fixative, fixation duration and processing history for each specimen, then compare sections processed alike before attributing a difference to RPL23 biology (standard IHC practice). If a controlled fixation series is available, apply the same EDTA pH 8.0 retrieval and 2 μg/ml primary antibody conditions throughout (datasheet A06155-2). Evaluate tissue preservation and cytoplasmic granular signal together; uneven loss near poorly preserved regions cannot establish a target-specific fixation effect (HPA tissue IHC; standard IHC practice).
Where should convincing RPL23 staining appear in a paraffin section?
Expect a granular cytoplasmic pattern across tissues, with supported cytosolic localisation in cell imaging (HPA tissue IHC; HPA subcellular). RPL23 is a component of the large ribosomal subunit and has no annotated transmembrane segment, so a crisp cell-surface outline alone is discordant with the supplied localisation evidence (UniProt P62829). Inspect viable appendix glandular cells as a high-expression reference, while recognising that smooth muscle cells were reported as not detected in the tissue survey (HPA tissue IHC). Score the cytoplasmic compartment separately from nuclear pigment, extracellular deposits and section-edge staining, using the same detection settings across comparisons (standard IHC practice).
Could isoforms or modified residues explain inconsistent RPL23 staining?
The supplied record lists 0 isoforms and a single chain spanning residues 1–140, so it does not support assigning different staining patterns to documented RPL23 isoforms (UniProt P62829). It lists phosphoserine at residue 17 and phosphotyrosine at residue 38, but supplies no antibody epitope or evidence that either modification changes IHC binding (UniProt P62829; datasheet A06155-2). When staining varies, compare retrieval and processing on matched sections before proposing an epitope-specific mechanism (standard IHC practice). If specificity remains uncertain, use an independently validated antibody or a suitable loss-of-target control and compare the expected cytoplasmic pattern (HPA tissue IHC; standard IHC practice).
How can I assess RPL23 localisation by multiplex IF?
For secondary IF/ICC work, pair RPL23 with a marker identifying the expected cell population, such as a glandular-cell marker when examining appendix epithelium (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and place the weaker signal in a channel with less tissue autofluorescence, checking single-stain and unstained controls before interpreting overlap (standard IF practice). Because RPL23 is cytosolic and has no transmembrane segment, use permeabilisation that permits antibody access to the cytosol, then verify morphology and background (HPA subcellular; UniProt P62829; standard IF practice). Judge co-localisation within cells rather than treating shared tissue regions as evidence of molecular association (standard IF practice).
How do I reduce diffuse brown background without losing RPL23 signal?
Start by comparing a no-primary control with the stained section, then check whether brown deposit follows the expected granular cytoplasmic pattern (HPA tissue IHC; standard IHC practice). The selected procedure used 10% goat serum block, biotinylated goat anti-rabbit secondary for 30 minutes at 37°C, and an avidin-biotin detection complex with DAB (datasheet A06155-2). Control endogenous peroxidase before DAB development and assess endogenous biotin when using avidin-biotin detection; these are general chromogenic IHC controls (standard IHC practice). If background persists, optimise blocking, washing and DAB development on matched sections while retaining a tissue reference with expected cytoplasmic staining (HPA tissue IHC; standard IHC practice).
What should I measure when comparing RPL23 across IHC specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable tissue region before scoring, because RPL23 staining is broadly cytoplasmic and cell types can differ in intensity (HPA tissue IHC; standard IHC practice). For glandular cells, record the percentage positive and an intensity-based H-score on the conventional 0–300 scale, with one consistent threshold and observer rules (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or positive area to viable tissue area in mm², and report the denominator (standard IHC practice). Exclude necrosis, folds and section edges consistently, then compare staining against matched controls acquired with the same retrieval and DAB settings (standard IHC practice).
How can I distinguish genuine RPL23 staining from IHC artefact?
A credible result shows granular cytoplasmic signal in viable cells, consistent with the tissue profile and supported cytosolic localisation (HPA tissue IHC; HPA subcellular). Strong appendix glandular-cell staining fits the reported high level, whereas a smooth-muscle-only signal conflicts with the reported not-detected finding and warrants control review (HPA tissue IHC). Treat isolated nuclear staining, extracellular precipitate, accentuation at section edges and signal restricted to necrotic regions as suspect until reproduced on well-preserved tissue (standard IHC practice). Use a no-primary control and an endogenous-peroxidase control to distinguish detection-system colour from antibody-dependent staining before assigning biological meaning (standard IHC practice).
Boster reagents

Best RPL23 / Large ribosomal subunit protein uL14 IHC Antibodies

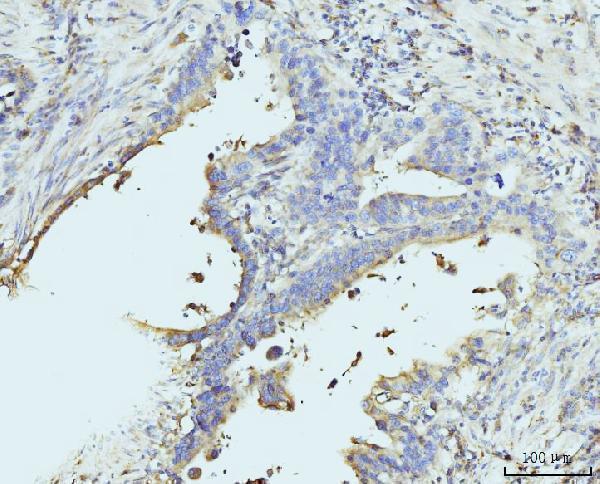
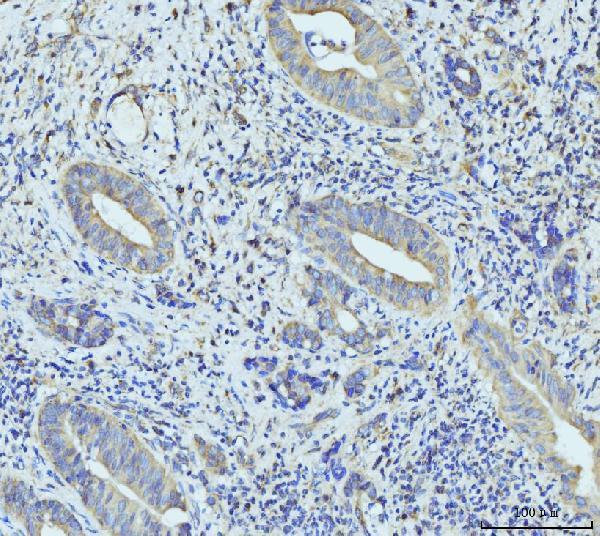
A06155-2 has real IHC images from paraffin sections of human tumors and mouse brain (catalog IHC captions). No IF/ICC image or application is provided (catalog applications and image list).

Real IHC data IHC analysis of RPL23 using anti-RPL23 antibody (A06155-2). RPL23 was detected in a paraffin-embedded section of human appendiceal adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-RPL23 Antibody (A06155-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-RPL23 Antibody ®
Cat # A06155-2

A06155-2 is shown on paraffin sections of human appendiceal adenocarcinoma, gall bladder adenosquamous carcinoma, and lung cancer (catalog IHC captions). It is also shown on mouse brain; Human, Mouse, and Rat are listed as reactive, but no rat tissue image is provided (catalog IHC captions; catalog reactivity).

Which to pick: Choose A06155-2 for paraffin-section IHC: its captions document staining at 2 μg/ml, within the listed 2–5 μg/ml IHC range (catalog IHC captions; catalog dilution). No listed SKU has IF/ICC validation, so there is no supported IF/ICC pick; A06155-2 is rabbit-hosted, with clonality unreported (catalog applications, image list, host, and clone field). For cross-species IHC, A06155-2 lists Human, Mouse, and Rat reactivity, with images for Human and Mouse only; the caption does not report the fixative (catalog reactivity; catalog IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P62829 (RL23_HUMAN, Large ribosomal subunit protein uL14).
  2. Human Protein Atlas. RPL23 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. RPL23 subcellular location (ICC-IF): Localized to the cytosol..
  4. Human Protein Atlas. RPL23 antibody validation summary (1 antibodies).
  5. A super-SILAC based proteomics analysis of diffuse large B-cell lymphoma-NOS patient samples to identify new proteins that discriminate GCB and non-GCB lymphomas. PloS one 2019 — PMC6788715.
  6. Ribosomal Protein L23 Drives the Metastasis of Hepatocellular Carcinoma via Upregulating MMP9. Frontiers in oncology 2021 — PMC8677661.
  7. Ribosomal protein L23 negatively regulates cellular apoptosis via the RPL23/Miz-1/c-Myc circuit in higher-risk myelodysplastic syndrome. Scientific reports 2017 — PMC5443795.
  8. Integrated single-cell and bulk RNA-seq analysis reveals an NK-cell-related immune landscape and a prognostic signature for hepatocellular carcinoma. Discover oncology 2026 — PMC13376102.
  9. PubMed PMID:1861993 — UniProt-cited evidence.
  10. PubMed PMID:1874450 — UniProt-cited evidence.
  11. PubMed PMID:11875025 — UniProt-cited evidence.