RPS15A / Small ribosomal subunit protein uS8 · IHC design guide

Design Immunohistochemistry for RPS15A

Plan chromogenic IHC for RPS15A in paraffin sections using the catalog antibody at 2–5 μg/ml (datasheet A09164-1). Assess the granular cytoplasmic pattern and compare high staining in kidney tubule cells with undetected staining in lymph node germinal center cells (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for RPS15A (IHC for RPS15A): expected localisation Granular cytoplasm (HPA tissue IHC); nucleolus (UniProt), antibody A09164-1, validated IHC image, and IHC protocol steps
Printable RPS15A IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); nucleolus (UniProt), antibody A09164-1, controls and protocol steps. Open the full RPS15A IHC guide →

RPS15A Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); nucleolus (UniProt)
Staining pattern Broad granular cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A09164-1)
Positive control ⓘ Duodenum+4 more · see all
Negative control ⓘ Lymph node+1 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09164-1)
Caveat Staining and RNA show only medium consistency (HPA tissue IHC)
Regulation No expression regulator annotated (UniProt)
Isoform / epitope No isoforms annotated; mature chain spans residues 2–130 (UniProt)
Section 1

Recommended RPS15A IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A09164-1) is accompanied by published RPS15A IHC methods for mouse tissue, lung adenocarcinoma, and osteosarcoma (PMC10309527; PMC4793315; PMC8626936).

Recommended immunohistochemistry (IHC-P) protocol parameters
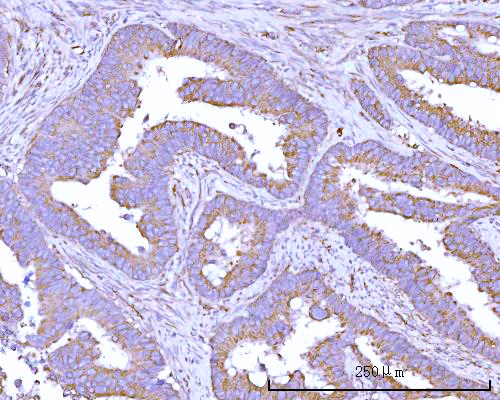
SampleParaffin-embedded human colon adenocarcinoma tissue; fixative not specified (datasheet A09164-1)
FixationImage fixative and duration unreported (datasheet A09164-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A09164-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A09164-1)
Primary antibodyRabbit anti-RPS15A, 2-5 μg/ml (datasheet A09164-1)
Primary incubationOvernight at 4 °C (datasheet A09164-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A09164-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRPS15A-positive staining in endocrine cells of duodenum (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet: A09164-1); compare citrate retrieval if staining needs optimization (PMC10309527; PMC8626936).
Section 2

What Is the Expected RPS15A Staining Pattern?

RPS15A is a 40S ribosomal protein found in the cytoplasm and nucleolus (UniProt P62244). In paraffin section IHC, expect predominantly granular cytoplasmic staining (HPA tissue IHC: Supported). High staining is reported in kidney tubular cells, liver hepatocytes and several glandular or endocrine cell populations (HPA tissue IHC). RPS15A has no transmembrane segment, so a membrane-only IHC pattern needs scrutiny (UniProt P62244 topology).

What am I looking at on my slide?
Granular cytoplasmic staining in kidney tubular cells or hepatocytes.This matches HPA's general cytoplasmic pattern and its High calls for both cell populations (HPA tissue IHC). Assess intensity within the identified cells; staining across an entire section should not be read as proof that every cell type has the same expression.
Staining appears chiefly at cell borders, with little granular cytoplasmic signal.A membrane-only IHC result conflicts with the tissue IHC profile and lacks support from RPS15A topology (HPA tissue IHC; UniProt P62244 topology). Review the section and controls before assigning the border signal to RPS15A; HPA's separate ICC-IF membrane summary does not establish this paraffin section pattern.
Strong signal occurs in an unexpected cell population while the expected cells are weak.Check cell identity and compare with a documented positive population before treating the signal as specific (HPA tissue IHC: cell-level calls). Cross-reactivity or endogenous chromogen-producing activity can produce misleading staining (general IHC practice); an unexpected cell type alone does not establish either cause.
Diffuse color covers tissue and empty areas without a discernible cellular pattern.This cannot be scored as the granular cytoplasmic pattern reported by HPA (HPA tissue IHC). Background may arise from detection reagents, inadequate blocking or excess antibody (general IHC practice). Compare a no-primary control and inspect whether color follows cells, tissue edges or areas outside the section.
A kidney tubule or hepatocyte positive-control population has no detectable signal.Both populations have High HPA staining calls, making them useful checks of this IHC run (HPA tissue IHC). A blank result may reflect a workflow or reagent problem (general IHC practice); it does not by itself overturn the reported pattern. Check section quality, retrieval, detection and the antibody's IHC validation.
💡Expected RPS15A appearanceA convincing positive result shows High, granular cytoplasmic staining in an identified kidney tubular cell or hepatocyte population (HPA tissue IHC), while isolated membrane-only color or diffuse, cell-independent color calls for control review (UniProt P62244 topology; general IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA reports High staining in duodenal endocrine cells, gallbladder and stomach glandular cells, kidney tubular cells, hepatocytes, pancreatic exocrine cells, placental decidual cells and testicular Leydig cells (HPA tissue IHC). Identify the sampled cell population before judging a slide against these calls.
Low or undetected comparison populationsHPA calls oral and vaginal squamous cells, ovarian stromal cells, smooth muscle cells, fibroblasts and adipocytes Low; germinal center cells and splenic red pulp cells are Not detected (HPA tissue IHC). These are cell-specific comparisons, not claims that their whole tissues must be blank.
Compartment and topologyUniProt places RPS15A in cytoplasm and nucleolus and reports no transmembrane segment (UniProt P62244). HPA tissue IHC instead describes the observable section pattern as generally granular cytoplasmic (HPA tissue IHC); a nucleolar expectation should not replace that IHC readout.
IHC evidence strengthThe tissue profile is Supported, with medium consistency between antibody staining and RNA expression (HPA tissue IHC). Antibody HPA047103 is also IHC Supported (HPA antibodies); neither label is an Enhanced validation claim, so use morphology and controls when interpreting an unusual result.
Protein contextRPS15A is a component of the 40S subunit and the small subunit processome (UniProt P62244). UniProt lists a chain spanning residues 2–130, no annotated isoforms and no transmembrane segment (UniProt P62244). These facts support a cellular localization check; they do not specify an IHC dilution or retrieval condition.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Known-positive cells are blank.The run may have failed at retrieval, primary-antibody incubation or detection (general IHC practice); HPA reports High staining in kidney tubular cells and hepatocytes (HPA tissue IHC).Confirm the expected cells are present, then check the catalog antibody's IHC-P instructions, reagent performance and positive-control slide (general IHC practice). Avoid assigning a target-specific fixation sensitivity: none is supplied here.
Everything looks uniformly brown.Excess background or endogenous detection activity can obscure cell boundaries (general IHC practice). A uniform wash of color does not resemble HPA's granular cytoplasmic profile (HPA tissue IHC).Compare a no-primary control, inspect tissue-free areas, and review blocking, washes, antibody concentration and detection steps (general IHC practice). Score RPS15A only where a cellular pattern remains interpretable.
Cell borders dominate the IHC result.A membrane-only pattern is at odds with the granular cytoplasmic tissue profile and with the absence of a transmembrane segment (HPA tissue IHC; UniProt P62244 topology).Check morphology and control slides, then repeat with the validated IHC conditions if needed (general IHC practice). Do not call border color a confirmed RPS15A pattern solely because the separate HPA ICC-IF summary says Membrane.
Unexpected cells stain more strongly than the intended comparison cells.The sampled cells may differ from the HPA-listed population; cross-reactivity or endogenous chromogenic activity are other possibilities (HPA tissue IHC; general IHC practice).Identify cells on the counterstained section and compare a no-primary control with a documented High population (HPA tissue IHC; general IHC practice). Treat the unexpected signal as unresolved until its pattern and controls agree.
A Low or Not detected HPA population shows color.HPA levels describe specified cell populations, and its tissue IHC reliability is Supported with medium RNA agreement (HPA tissue IHC). Color may also reflect background (general IHC practice).Verify the cell type and staining location, review the no-primary control, and compare a High population in the same run (HPA tissue IHC; general IHC practice). Do not apply one cell-level HPA call to an entire organ.
Q: Should an ICC-IF membrane signal set the IHC scoring rule?A: HPA lists Membrane in its ICC-IF summary, but supplies no main location or cell-line images there; tissue IHC reports granular cytoplasmic staining (HPA subcellular; HPA tissue IHC).Use the tissue IHC pattern for paraffin section scoring (HPA tissue IHC). Evaluate ICC-IF on its own guide page; the supplied ICC-IF summary does not provide a protocol or resolve the compartment difference.

Sample controls for RPS15A IHC & IF

🧪Run kidney first; tubular cells should stain (HPA: High in kidney cells in tubules). Use lymph node germinal center cells as the negative tissue (HPA: Not detected); on the kidney slide, internal negative cells should retain counterstain without specific DAB signal, but the supplied HPA row does not identify a kidney cell type expected to be negative (HPA: kidney row).
Positive control tissue: Duodenum (Endocrine cells, HPA High)
Negative control tissue: Lymph node (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for RPS15A; derive a cell-line control from the positive tissue's cell type (Endocrine cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control; rabbit IgG matched to the primary antibody’s isotype and clonality where known; and RPS15A knockout material as a biological negative (caption: rabbit primary and goat anti-rabbit secondary; standard IHC practice). Block endogenous peroxidase for HRP/DAB detection and endogenous biotin if using avidin-biotin detection, particularly in kidney tubules (caption: HRP/DAB; standard IHC practice).
⚠️Feasibility: No matched source reports a target-specific fixation window or fixation effect, and the selected A09164-1 tissue-IHC caption does not report a fixative (supplied evidence; caption: A09164-1). The caption uses heat retrieval in EDTA at pH 8.0, but does not establish that retrieval is required (caption: A09164-1). The evidence does not establish whether frozen sections or IF/ICC are easier; HPA supplies no ICC-IF images, and kidney tubules can contribute endogenous biotin artefact with avidin-biotin detection (HPA subcellular; standard IHC practice).

HPA tissue IHC evidence for RPS15A

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Duodenum Endocrine cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Kidney Cells in tubules High Protein (IHC) HPA →
Liver Hepatocytes High Protein (IHC) HPA →
Pancreas Exocrine glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced RPS15A IHC Tips

Troubleshooting RPS15A staining in paraffin sections with chromogenic IHC, with one question on translating the readout to IF.

What retrieval should I start with when RPS15A staining is weak?
Start with heat mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A09164-1). The selected tissue IHC example used this retrieval before staining with 2 μg/ml antibody overnight at 4°C, so keep those conditions together for the initial comparison (datasheet A09164-1). If staining remains weak, vary heating duration on matched sections while keeping buffer and detection conditions fixed, and monitor tissue integrity (standard IHC practice). Compare each run with a secondary only control and a documented positive tissue area to distinguish retrieval failure from detection background (standard IHC practice). Do not assign a target specific optimal heating time from the caption, which does not report one (datasheet A09164-1).
How should I troubleshoot fixation related loss of RPS15A signal?
The selected image documents a paraffin embedded section but does not state its fixative, so RPS15A sensitivity to fixation is unknown here (datasheet A09164-1). Record the fixative, exposure time, section age and retrieval conditions for each specimen before comparing staining intensity (standard IHC practice). When archival sections differ, test matched sections with the page retrieval condition, EDTA at pH 8.0, and hold antibody concentration at 2 μg/ml initially (datasheet A09164-1; standard IHC practice). Evaluate tissue morphology and a positive reference alongside signal, because poor preservation can complicate interpretation (standard IHC practice). Do not infer fixation tolerance from the reported tissue staining pattern or the protein's topology (HPA tissue IHC; UniProt P62244 topology).
Which compartment should count as credible RPS15A staining?
Assess granular cytoplasmic staining first: that is the reported tissue IHC profile, while UniProt also places RPS15A in the nucleolus (HPA tissue IHC; UniProt P62244 subcellular). A sharply restricted cell surface rim warrants caution because the supplied subcellular summary says membrane while its main location and ICC/IF image list provide no supporting detail (HPA subcellular). Score cytoplasmic and nucleolar signal separately on the same section rather than merging them into one intensity value (standard IHC practice; UniProt P62244 subcellular). Compare staining with a secondary only control and adjacent tissue morphology before calling either compartment positive (standard IHC practice). Keep the interpretation compartment specific when reporting discordance between tissue staining and the subcellular summary (HPA tissue IHC; HPA subcellular).
Could epitope masking or an isoform explain patchy staining?
The supplied record lists 0 isoforms, no transmembrane segment and a processed chain spanning residues 2–130; an isoform switch is therefore unsupported by these data (UniProt P62244 isoforms, topology and processing). Lysine 88 is listed as an example modified residue, but the antibody epitope and any effect of that modification on binding are unspecified (UniProt P62244 modified residues; datasheet A09164-1). For patchiness, compare matched areas after the documented EDTA pH 8.0 retrieval, checking section preservation and staining controls before proposing epitope masking (datasheet A09164-1; standard IHC practice). Keep incubation and detection constant across those sections so a retrieval comparison remains interpretable (standard IHC practice). Report modification dependent recognition only if separately demonstrated for the antibody (standard IHC practice).
How can I check an IHC pattern with multiplex IF?
Use the chromogenic paraffin result as the comparison point: the selected antibody example documents tissue IHC, while the supplied HPA subcellular record lists no ICC/IF images (datasheet A09164-1; HPA subcellular). In multiplex IF, pair RPS15A with an independently validated marker for the expected cell population, such as kidney tubular cells, and assess whether signals occupy the same cells (HPA: high in kidney tubular cells; standard IF practice). Choose a far red fluorophore when tissue autofluorescence interferes with shorter wavelengths, and include single stain controls (standard IF practice). Because RPS15A has no transmembrane segment and is reported in cytoplasm and nucleolus, assess permeabilisation for intracellular access (UniProt P62244 topology and subcellular; standard IF practice). Optimise IF fixation and permeabilisation independently of the paraffin IHC caption (datasheet A09164-1; standard IF practice).
What should I change when DAB staining is diffuse or granular everywhere?
Separate expected granular cytoplasmic signal from diffuse deposits by reviewing cell boundaries and a secondary only control (HPA tissue IHC; standard IHC practice). The selected example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, a peroxidase linked secondary for 30 minutes at 37°C, and DAB development (datasheet A09164-1). Include an endogenous peroxidase block and control DAB development time to investigate widespread chromogen signal (standard chromogenic IHC practice). If background persists, titrate primary antibody from the documented starting concentration while keeping retrieval and imaging comparable (datasheet A09164-1; standard IHC practice). Check damaged edges and necrotic regions separately before attributing diffuse colour to RPS15A (standard IHC practice).
How should I score RPS15A across heterogeneous tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because reported tissue IHC is generally granular and cytoplasmic, with substantial differences among listed cell populations (HPA tissue IHC). For intensity based analysis, report an H-score from the percentage of cells at each staining intensity; also report the percentage of positive cells if the threshold is prespecified (standard IHC practice). For spatial comparisons, count positive cells per mm² of viable tissue and normalise each count to the assessed cell population or viable area (standard IHC practice). Apply the same counterstain, detection settings and scoring threshold across sections, and exclude folds and necrosis by a stated rule (standard IHC practice). Report cytoplasmic and nucleolar scores separately if both are assessed (UniProt P62244 subcellular; standard IHC practice).
How do I distinguish true RPS15A signal from staining artefact?
A credible call combines the reported granular cytoplasmic tissue pattern with appropriate cell identity and clean controls; UniProt also allows nucleolar localisation (HPA tissue IHC; UniProt P62244 subcellular; standard IHC practice). Compare a high staining reference population, such as hepatocytes, with a reported low staining population, such as adipocytes, while recognising that these are observations rather than assay controls (HPA: high in hepatocytes; HPA: low in adipocytes). Treat staining concentrated at section edges, folds or necrotic areas as suspect and inspect matched morphology (standard IHC practice). Investigate signal in the secondary only control or after omitted primary antibody for endogenous enzyme activity and detection background (standard chromogenic IHC practice). Do not interpret an isolated membrane rim as established RPS15A localisation from these data (HPA subcellular; HPA tissue IHC).
Boster reagents

Best RPS15A / Small ribosomal subunit protein uS8 IHC Antibodies

A09164-1 has IHC images from human paraffin tissue and IF images from human cells and tissue (catalog image captions); the application list also includes IHC, ICC and IF (catalog applications).

Real IHC data IHC analysis of RPS15A using anti-RPS15A antibody (A09164-1). RPS15A was detected in a paraffin-embedded section of human colon adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-RPS15A Antibody (A09164-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-RPS15A Antibody ®
Cat # A09164-1

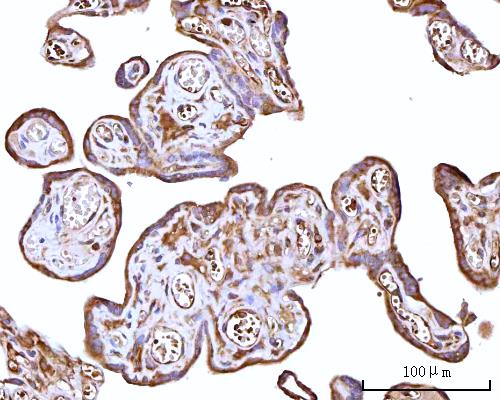
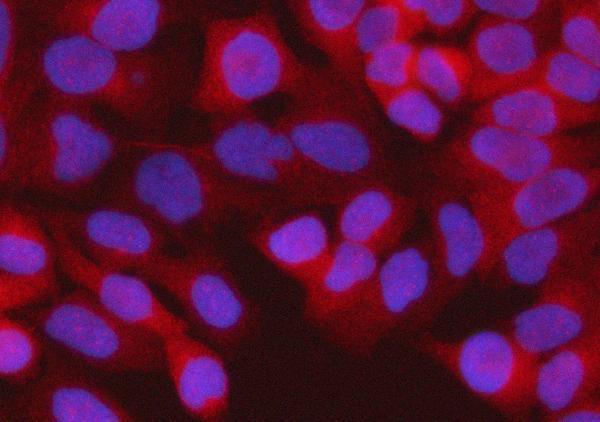
A09164-1 has IHC images from human colon adenocarcinoma, placenta and testicular seminoma paraffin sections (catalog IHC captions). Its IF images show HeLa cells and human testis cancer paraffin tissue; the catalog lists Human, Mouse and Rat reactivity (catalog IF captions; catalog reactivity).

Which to pick: Choose A09164-1 for human paraffin-section IHC: its own caption documents heat retrieval in pH 8.0 EDTA and primary antibody at 2 μg/ml (A09164-1 IHC caption). For IF/ICC, the same SKU has human cell and tissue IF images and a listed dilution of 5 μg/ml (A09164-1 IF captions; datasheet: 5 μg/ml). For Mouse or Rat, reactivity is listed, but the supplied IHC and IF images document Human samples only; the paraffin captions do not report a fixative (catalog reactivity; A09164-1 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P62244 (RS15A_HUMAN, Small ribosomal subunit protein uS8).
  2. Human Protein Atlas. RPS15A tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. RPS15A subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. RPS15A antibody validation summary (1 antibodies).
  5. Elevated FBXL18 promotes RPS15A ubiquitination and SMAD3 activation to drive HCC. Hepatology communications 2023 — PMC10309527.
  6. The effect of ribosomal protein S15a in lung adenocarcinoma. PeerJ 2016 — PMC4793315.
  7. RPS15A promotes gastric cancer progression via activation of the Akt/IKK-β/NF-κB signalling pathway. Journal of cellular and molecular medicine 2019 — PMC6378197.
  8. TMED3/RPS15A Axis promotes the development and progression of osteosarcoma. Cancer cell international 2021 — PMC8626936.
  9. PubMed PMID:15489334 — UniProt-cited evidence.
  10. PubMed PMID:8706699 — UniProt-cited evidence.
  11. PubMed PMID:9582194 — UniProt-cited evidence.