RUNX3 / Runt-related transcription factor 3 · IHC design guide

Design Immunohistochemistry for RUNX3

Plan paraffin-section RUNX3 IHC around nuclear staining in a subset of immune cells (HPA tissue IHC). This guide covers controls, fixation, chromogenic detection and scoring using the catalog antibody at 0.5–1 μg/ml (datasheet: PB9432).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
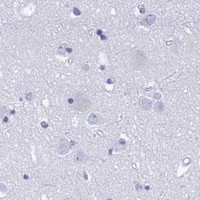
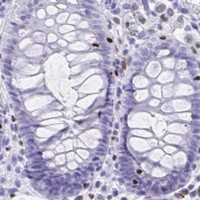
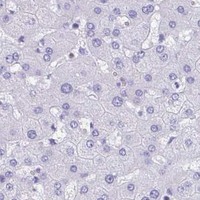
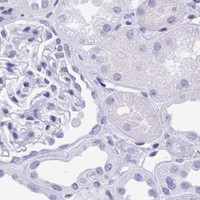
Immunohistochemistry protocol sheet for RUNX3 (IHC for RUNX3): expected localisation Nuclear tissue staining; cytoplasmic location is possible (HPA tissue IHC; UniProt), antibody PB9432, validated IHC image, and IHC protocol steps
Printable RUNX3 IHC protocol sheet — expected localisation Nuclear tissue staining; cytoplasmic location is possible (HPA tissue IHC; UniProt), antibody PB9432, controls and protocol steps. Open the full RUNX3 IHC guide →

RUNX3 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear tissue staining; cytoplasmic location is possible (HPA tissue IHC; UniProt)
Staining pattern Nuclear staining in a subset of immune cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet PB9432)
Positive control ⓘ Skin+2 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation TGF-beta promotes nuclear translocation (UniProt)
Isoform / epitope 2 isoforms; check antibody epitope coverage (UniProt)
Section 1

Recommended RUNX3 IHC & IF Protocols

The catalog antibody specifies heat-mediated EDTA pH 8.0 retrieval (datasheet PB9432). The published RUNX3 IHC protocol below describes tissue microarray staining (PMC3572981).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse spleen tissue; fixative not specified (datasheet PB9432)
FixationImage fixative and duration unreported (datasheet PB9432); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet PB9432); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9432)
Primary antibodyRabbit anti-RUNX3, 0.5-1μg/ml (datasheet PB9432)
Primary incubationOvernight at 4 °C (datasheet PB9432)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9432)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultRUNX3-positive staining in langerhans cells of skin (HPA tissue IHC: Medium). HPA tissue profile: Nuclear expression in a subset of immune cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet PB9432); the published tissue microarray method does not specify retrieval (PMC3572981).
Section 2

What Is the Expected RUNX3 Staining Pattern?

RUNX3 is a mainly nuclear transcription factor with regulated cytoplasmic localization and no transmembrane segment (UniProt Q13761). In paraffin section IHC, expect nuclear staining in a subset of immune cells, including tonsillar non-germinal center cells and skin Langerhans cells (HPA tissue IHC). HPA rates the tissue pattern Enhanced, with medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear staining in some tonsillar non-germinal center cells or skin Langerhans cells.This fits the reported immune-cell pattern; both cell populations have Medium staining in HPA tissue IHC. Judge the stained cells and their nuclear compartment rather than expecting every cell in the section to be positive (HPA tissue IHC).
Predominantly cytoplasmic or vesicular signal, with little nuclear staining.Review before calling it artefact: UniProt reports cytoplasmic RUNX3 after tyrosine phosphorylation, and HPA ICC-IF reports vesicles and cytosol. Those observations do not validate a cytoplasm-only pattern in paraffin tissue IHC (UniProt Q13761; HPA subcellular ICC-IF).
Broad staining of adipocytes or adrenal glandular cells.These cells are reported as Not detected in the sampled HPA tissues. Widespread signal there raises concern for nonspecific binding or endogenous detection activity; compare a control processed with the primary antibody omitted (HPA tissue IHC; general IHC practice).
Diffuse brown deposit across cells and surrounding section.A diffuse deposit obscures the expected subset of stained nuclei and cannot establish cellular localization (HPA tissue IHC). Check primary-omission and detection controls, blocking, and wash quality as general chromogenic IHC troubleshooting steps (general IHC practice).
No discernible staining in a tonsil section selected as a positive control.HPA reports Medium staining in tonsillar non-germinal center cells, so absence warrants checking cell identification and assay performance. A negative result alone does not establish RUNX3 absence; review retrieval, primary-antibody use, and detection controls (HPA tissue IHC; general IHC practice).
💡Expected RUNX3 appearanceCall a result positive when a subset of tonsillar non-germinal center cells or skin Langerhans cells shows discernible nuclear staining at the reported Medium level; widespread adipocyte staining or diffuse brown background is suspect (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Cell population chosen for the controlTonsillar non-germinal center cells and skin Langerhans cells are reported at Medium staining; bone marrow hematopoietic cells and lymph-node non-germinal center cells are Low. Select and interpret controls at their reported levels (HPA tissue IHC).
Compartment and signaling stateUniProt places RUNX3 in nucleus and cytoplasm, reports cytoplasmic localization of the tyrosine-phosphorylated form, and describes movement to the nucleus after TGF-beta stimulation. Tissue IHC alone cannot assign the cause of cytoplasmic staining (UniProt Q13761).
Antibody and tissue evidenceHPA lists Enhanced IHC validation for HPA059006 and CAB025416, while its tissue profile notes only medium consistency with RNA. Interpret an unexpected pattern against cellular morphology and controls, even when using an IHC-validated antibody (HPA antibodies; HPA tissue IHC).
Target form and epitopeUniProt records 2 isoforms, a Runt domain at residues 54–182, and a single chain spanning residues 1–415. The supplied record does not identify the catalog antibody's epitope, so isoform-specific detection cannot be inferred (UniProt Q13761).
IF/ICC Q&A: what localization is reported?HPA ICC-IF reports mainly nucleoplasm and vesicles, with additional cytosol. This is cell-imaging evidence; use the separate IF/ICC guide for that application and assess paraffin IHC against the tissue pattern above (HPA subcellular ICC-IF; HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Tonsil control has no nuclear signal.Assay signal may be inadequate, or the assessed cells may miss the reported positive subset (HPA tissue IHC; general IHC practice).Identify non-germinal center cells, then review the IHC-validated antibody's documented procedure, antigen retrieval, and detection-control performance (HPA tissue IHC; general IHC practice).
All nuclei look similarly brown.A section-wide pattern exceeds HPA's reported subset of immune-cell nuclei; excessive assay signal is a possible technical cause (HPA tissue IHC; general IHC practice).Compare the primary-omission control and review primary concentration, incubation, and chromogen development using the validated IHC procedure (general IHC practice).
Cytoplasmic staining dominates.Regulated cytoplasmic RUNX3 is biologically plausible, but its cause cannot be assigned from this stain alone (UniProt Q13761).Check whether the same pattern appears without primary antibody, assess nuclear signal, and report the compartment observed without claiming phosphorylation status (UniProt Q13761; general IHC practice).
Adipocytes or adrenal glandular cells stain strongly.Those cell types are Not detected in HPA tissue IHC; nonspecific antibody binding or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Review primary-omission and detection controls, endogenous-activity blocking, and whether the signal follows the expected cellular pattern (HPA tissue IHC; general IHC practice).
Brown haze prevents confident cell scoring.Background can hide the reported nuclear signal in a subset of immune cells (HPA tissue IHC).Check blocking, wash steps, and detection controls; score only cells whose boundaries and nuclei remain interpretable (general IHC practice).
A low-level lymph-node or bone-marrow signal appears inconsistent with tonsil.HPA reports Low staining in those populations and Medium staining in tonsillar non-germinal center cells; different signal strengths can therefore be expected (HPA tissue IHC).Compare the same cell populations and compartments, retain an appropriate positive control, and record intensity by tissue rather than treating every weak cell as assay failure (HPA tissue IHC; general IHC practice).

Sample controls for RUNX3 IHC & IF

🧪Run tonsil first and score staining in non-germinal center cells (HPA: Medium); run adipose tissue as the negative and score adipocytes (HPA: Not detected). On the tonsil slide, neighboring cells without detectable signal provide an internal negative comparison, but their identity should not be assumed from the HPA row (HPA: non-germinal center cells, Medium).
Positive control tissue: Skin (Langerhans cells, HPA Medium)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show RUNX3 in A-549, SiHa, U2OS, NIH 3T3, with annotated localisation: Nucleoplasm (supported), Vesicles (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit IgG isotype control for the rabbit primary; and RUNX3-knockout tissue as a biological negative if available (caption: rabbit anti-RUNX3; standard IHC practice). For tonsil stained with the caption’s biotin/SABC-DAB system, quench endogenous peroxidase and check for endogenous biotin background (caption: biotinylated secondary and SABC-DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected PB9432 paraffin-section caption does not state a fixative (caption: fixative unreported). Heat retrieval in EDTA at pH 8.0 is documented, but its necessity has not been established by the supplied evidence (caption: EDTA retrieval). HPA has RUNX3 ICC-IF images, but the supplied evidence does not establish that IF or frozen sections are easier than paraffin IHC; in tonsil, assess peroxidase and biotin background when using the caption’s detection system (HPA: ICC-IF images; caption: biotin/SABC-DAB; standard IHC practice).

HPA tissue IHC evidence for RUNX3

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Skin Langerhans cells Medium Protein (IHC) HPA →
Small intestine Enterocytes - Microvilli Medium Protein (IHC) HPA →
Tonsil Non-germinal center cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Section 3

Advanced RUNX3 IHC Tips

Troubleshoot RUNX3 staining in paraffin sections by checking retrieval, compartment, cell identity and controls before comparing signal intensity.

How should I optimize retrieval when RUNX3 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA, pH 8.0, for paraffin sections (PB9432 tissue-IHC caption). In the documented mouse spleen example, the section was blocked with 10% goat serum and incubated with 1 μg/ml catalog antibody overnight at 4°C; use that combination as a documented starting point, not a universal optimum (PB9432 tissue-IHC caption). If staining remains weak, compare retrieval heating and cooling conditions on matched sections while holding detection and exposure to DAB constant (standard IHC practice). Inspect tissue integrity and nuclear staining together: stronger color accompanied by damaged morphology does not establish improved RUNX3 detection (standard IHC practice; HPA tissue IHC: nuclear expression in a subset of immune cells).
Could fixation explain weak RUNX3 staining in my paraffin sections?
The selected paraffin-section example does not report a fixative, so RUNX3-specific sensitivity to fixation is unknown (PB9432 tissue-IHC caption). Record the actual fixative, fixation duration and processing history for each specimen before changing retrieval or antibody conditions (standard IHC practice). Compare similarly processed sections side by side, using the documented EDTA, pH 8.0 retrieval and 1 μg/ml overnight primary incubation as starting conditions (PB9432 tissue-IHC caption). If staining varies with processing, check morphology and a known-positive section from the same processing batch before attributing the change to RUNX3 biology (standard IHC practice; HPA tissue IHC: nuclear expression in a subset of immune cells).
How should I assess RUNX3 staining outside the nucleus?
Score nuclear and cytoplasmic staining separately because RUNX3 is reported in both compartments, with tyrosine-phosphorylated RUNX3 localized to cytoplasm and nuclear translocation reported after TGF-beta stimulation (UniProt Q13761: subcellular location). Nuclear signal in a subset of immune cells has tissue-IHC support, while cytosolic signal also has subcellular imaging support (HPA tissue IHC: profile; HPA subcellular: cytosol supported). Use the counterstain to define intact nuclei and inspect staining within individual cells rather than assigning diffuse DAB to nearby cells (standard IHC practice). Treat a new cytoplasmic pattern as a hypothesis until cell identity, morphology and staining controls support it; compartment alone does not identify phosphorylation state (UniProt Q13761: subcellular note; standard IHC practice).
Can one IHC stain distinguish RUNX3 isoforms or modification states?
RUNX3 has 2 listed isoforms and a Runt domain spanning residues 54–182 (UniProt Q13761: isoforms and domains). The supplied PB9432 tissue-IHC caption does not identify the antibody epitope, so its DAB signal cannot by itself be assigned to either isoform (PB9432 tissue-IHC caption; UniProt Q13761: isoforms). Confirm epitope mapping and isoform coverage from antibody documentation before comparing staining across specimens; use an independently characterized reagent if isoform discrimination is essential (standard IHC practice). RUNX3 also has a recorded phosphoserine at residue 243, but an uncharacterized total-RUNX3 stain cannot establish that modification or the tyrosine phosphorylation linked to cytoplasmic localization (UniProt Q13761: modified residue and subcellular note; standard IHC practice).
How can IF help verify RUNX3 cell identity and compartment?
For IF/ICC, pair RUNX3 with a marker identifying the cell population under study and a nuclear counterstain, then inspect whether signals occupy the same intact cells (standard IF practice). This is useful when comparing with the reported nuclear expression in a subset of immune cells (HPA tissue IHC: profile). RUNX3 has no transmembrane segment and is reported in nucleus and cytoplasm, so assess intracellular access with a mild, empirically optimized permeabilisation step after the chosen fixation (UniProt Q13761: topology and subcellular location; standard IF practice). Measure unstained tissue autofluorescence first, choose well-separated fluorophores with an appropriate low-background channel, and include single-color controls to check bleed-through (standard IF practice).
What should I check when DAB background obscures RUNX3-positive cells?
Run a no-primary section through the same secondary and chromogen steps to assess detection background, and compare it with a fully stained adjacent section (standard IHC practice). The documented example used a biotinylated goat anti-rabbit secondary, streptavidin-biotin detection and DAB, making endogenous biotin and peroxidase relevant controls for that workflow (PB9432 tissue-IHC caption; standard IHC practice). Apply a peroxidase block and evaluate a biotin-blocking control if background follows those pathways; titrate the primary and DAB development while preserving morphology (standard IHC practice). Judge improvement by clearer staining in intact nuclei of the expected cell population, rather than by lower whole-section color alone (HPA tissue IHC: profile; standard IHC practice).
How should I quantify RUNX3 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: HPA describes nuclear RUNX3 in a subset of immune cells, so a whole-section average can dilute that signal (HPA tissue IHC: profile; standard IHC practice). Report the percentage of positive nuclei and a prespecified intensity-weighted H-score, or positive-cell density per mm² when cell abundance is the question (standard IHC practice). Normalize positive nuclei to the number of evaluable nuclei in the defined population, and normalize density to the measured viable tissue area (standard IHC practice). Keep retrieval, counterstain, DAB development, imaging and positivity thresholds consistent across batches; record cytoplasmic staining separately if it is under study (standard IHC practice; UniProt Q13761: subcellular location).
How do I distinguish credible RUNX3 staining from section artefacts?
Prioritize staining in intact nuclei of an identifiable cell population, consistent with the reported nuclear signal in a subset of immune cells (HPA tissue IHC: profile). Check whether apparent positives cluster at section edges, folds or necrotic areas, and compare them with adjacent intact tissue before scoring (standard IHC practice). Cytoplasmic RUNX3 is biologically possible, but diffuse color outside recognizable cells or signal reproduced on a no-primary control needs investigation before interpretation (UniProt Q13761: subcellular location; standard IHC practice). For the documented biotin-based DAB workflow, test endogenous peroxidase and biotin contributions if they could explain the pattern, and use the same cell and compartment criteria across specimens (PB9432 tissue-IHC caption; standard IHC practice).
Boster reagents

Best RUNX3 / Runt-related transcription factor 3 IHC Antibodies

PB9432 has IHC images from paraffin sections of mouse and rat spleen and human intestinal and lung cancer tissue (PB9432 IHC captions), plus an IF image of U20S cells (PB9432 IF caption).

Real IHC data IHC analysis of RUNX3 using anti-RUNX3 antibody (PB9432). RUNX3 was detected in a paraffin-embedded section of mouse spleen tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-RUNX3 Antibody (PB9432) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-RUNX3 Antibody ®
Cat # PB9432

PB9432 is listed for IHC in human, mouse and rat, with paraffin-section images from the tissues named above (PB9432 applications; PB9432 reactivity; PB9432 IHC captions). PB9432 is also listed for IF/ICC, with an IF image of U20S cells (PB9432 applications; PB9432 IF caption).

Which to pick: Choose PB9432 for tissue IHC based on its paraffin-section images; the fixative is unreported (PB9432 IHC captions). Choose PB9432 for IF/ICC based on its application list and U20S cell IF image (PB9432 applications; PB9432 IF caption). For work across human, mouse and rat samples, PB9432 lists reactivity in all three species; its clonality is unspecified (PB9432 reactivity; PB9432 clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q13761 (RUNX3_HUMAN, Runt-related transcription factor 3).
  2. Human Protein Atlas. RUNX3 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. RUNX3 subcellular location (ICC-IF): Mainly localized to the nucleoplasm and vesicles. In addition localized to the cytosol..
  4. Human Protein Atlas. RUNX3 antibody validation summary (3 antibodies).
  5. H. pylori-Eradication Therapy Increases RUNX3 Expression in the Glandular Epithelial Cells in Enlarged-Fold Gastritis. Journal of clinical biochemistry and nutrition 2010 — PMC2872232.
  6. Combination immunohistochemistry for SMAD4 and Runt-related transcription factor 3 may identify a favorable prognostic subgroup of pancreatic ductal adenocarcinomas. Oncotarget 2017 — PMC5652736.
  7. Enhancer of zeste homologue 2 (EZH2) down-regulates RUNX3 by increasing histone H3 methylation. The Journal of biological chemistry 2008 — PMC2427338.
  8. RUNX3 suppresses migration, invasion and angiogenesis of human renal cell carcinoma. PloS one 2013 — PMC3572981.
  9. PubMed PMID:7622058 — UniProt-cited evidence.
  10. PubMed PMID:7835892 — UniProt-cited evidence.
  11. PubMed PMID:16710414 — UniProt-cited evidence.