S100A7 / Protein S100-A7 · IHC design guide

Design Immunohistochemistry for S100A7

Plan paraffin-section S100A7 IHC with consistent fixation, antigen retrieval, and chromogenic detection. Use the squamous epithelial staining profile to select comparison tissue and interpret the result (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for S100A7 (IHC for S100A7): expected localisation Cytoplasmic or secreted (UniProt), antibody A02369-1, validated IHC image, and IHC protocol steps
Printable S100A7 IHC protocol sheet — expected localisation Cytoplasmic or secreted (UniProt), antibody A02369-1, controls and protocol steps. Open the full S100A7 IHC guide →

S100A7 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic or secreted (UniProt)
Staining pattern Squamous epithelia stain; subcellular pattern unreported (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet A02369-1)
Positive control ⓘ Skin+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Secretion can separate protein staining from RNA patterns (HPA tissue IHC)
Regulation Up-regulated in psoriatic epidermis (UniProt)
Isoform / epitope No isoforms or transmembrane segment; no sided epitope map (UniProt)
Section 1

Recommended S100A7 IHC & IF Protocols

The catalog antibody uses citrate pH 6 retrieval (datasheet A02369-1). The published S100A7 IHC protocols below cover tissue staining in three articles (PMC11732109; PMC12031700; PMC2914786).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissue; fixative not specified (datasheet A02369-1)
FixationImage fixative and duration unreported (datasheet A02369-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet A02369-1)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02369-1)
Primary antibodyRabbit anti-S100A7, 0.5-1μg/ml (datasheet A02369-1)
Primary incubationOvernight at 4 °C (datasheet A02369-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02369-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultS100A7-positive staining in cells in corneal layer of skin (HPA tissue IHC: High). HPA tissue profile: Expression in squamous epithelia. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6 heat retrieval for the catalog antibody (datasheet A02369-1); the oral tissue protocol also reports citrate pH 6 microwave retrieval (PMC2914786).
Section 2

What Is the Expected S100A7 Staining Pattern?

In paraffin-section IHC, expect S100A7 mainly in squamous epithelia, with high staining in skin corneal-layer cells and medium staining in several other squamous epithelia (HPA tissue IHC). Cytoplasmic staining fits its annotation; a secreted pool may complicate tissue localisation (UniProt P31151). S100A7 has no transmembrane segment (UniProt P31151 topology). HPA rates tissue staining “Enhanced” but notes medium consistency with RNA and antibodies that can target proteins from multiple genes (HPA tissue IHC).

What am I looking at on my slide?
Strong signal marks skin corneal-layer cells; squamous epithelial cells stain in cervix, esophagus, oral mucosa, tonsil or vagina (HPA tissue IHC).This matches the reported distribution: skin is high, while those squamous sites are medium (HPA tissue IHC). Judge staining within the named cell population; a whole-section intensity score can obscure where the signal arose (general IHC practice).
Signal appears predominantly nuclear, membranous or confined to cell borders instead of cytoplasmic (UniProt P31151; HPA subcellular ICC-IF).That compartment is discordant with cytoplasm in UniProt and supported cytosol in HPA ICC-IF (UniProt P31151; HPA subcellular ICC-IF). Review morphology and controls before assigning it to S100A7; the secreted annotation permits cautious interpretation of extracellular signal, but does not establish a membrane pattern (UniProt P31151).
The strongest stain is in an unexpected cell population, while the expected squamous cells are weak or unstained (HPA tissue IHC).Consider cross-reactivity, endogenous detection activity or misidentified cells (general IHC practice). HPA warns that its tissue assessment involves antibodies targeting proteins from more than one gene, so location alone cannot establish molecular specificity (HPA tissue IHC).
A uniform haze covers tissue and empty spaces, obscuring cell boundaries (general IHC practice).Treat diffuse background as an assay interpretation problem, not a tissue-expression result (general IHC practice). Check the detection-only control and staining distribution before comparing intensity with HPA's cell-specific observations (general IHC practice; HPA tissue IHC).
Skin corneal-layer cells show no convincing signal in an otherwise interpretable section (HPA tissue IHC).This conflicts with HPA's high observation, but a single negative slide cannot distinguish assay failure from specimen variation (HPA tissue IHC; general IHC practice). Check tissue preservation and controls, then assess the catalog antibody's stated IHC-P conditions (general IHC practice).
💡Expected S100A7 appearanceCall the result concordant when skin corneal-layer cells show high staining or the listed squamous epithelial cells show medium staining, with cytoplasmic localisation; isolated nuclear or indiscriminate background signal is suspect (HPA tissue IHC; UniProt P31151; general IHC practice).
How each factor affects the staining
Tissue and cell populationHPA reports high staining in skin corneal-layer cells and medium staining in several squamous epithelia; adipocytes in adipose tissue are “not detected” (HPA tissue IHC). Use the specified cells when interpreting controls, rather than treating every cell in a named tissue alike (general IHC practice).
Intracellular and secreted poolsUniProt annotates cytoplasm and non-classical secretion; HPA ICC-IF supports cytosol (UniProt P31151; HPA subcellular ICC-IF). Extracellular signal therefore needs context, and its presence alone does not identify the stained cell of origin (UniProt P31151; general IHC practice).
Antibody specificity and validationHPA lists IHC as Supported for HPA006997 and Enhanced for CAB001453 and CAB033766; its tissue summary cautions that antibodies can target proteins from multiple genes (HPA antibodies; HPA tissue IHC). Match the chosen antibody's own validation to the observed pattern (general IHC practice).
Protein processing and epitope informationUniProt lists a 2–101 chain, no signal peptide or propeptide, and no glycosylation sites (UniProt P31151). The supplied record gives no antibody epitope position, so it cannot predict which pool an antibody detects (UniProt P31151; supplied evidence).
Antigen retrievalTarget-specific fixation effects are not established by the supplied assay evidence. Verify with a matched IHC source before attributing a result to fixation.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in skin corneal-layer cells, the reported high population (HPA tissue IHC).The assay or specimen may be uninformative; the absence alone does not identify a cause (general IHC practice).Verify morphology, positive and detection controls, then check the catalog antibody's IHC-P instructions and any recorded retrieval or dilution deviation (general IHC practice).
Only nuclei or cell borders stain (general IHC practice).That pattern disagrees with UniProt cytoplasm and HPA's supported ICC-IF cytosol localisation (UniProt P31151; HPA subcellular ICC-IF).Inspect a positive control and compare the pattern with a separately validated antibody if available; avoid scoring the discordant compartment as confirmed S100A7 (general IHC practice; HPA antibodies).
Unexpected cells stain more strongly than the listed squamous epithelial populations (HPA tissue IHC).Cross-reactivity or endogenous detection activity is possible (general IHC practice); HPA flags multi-gene antibody targeting (HPA tissue IHC).Identify the cells by morphology, review the detection-only control, and compare antibody validation and the HPA cell-specific pattern (general IHC practice; HPA antibodies; HPA tissue IHC).
Diffuse stain prevents cell-level scoring (general IHC practice).Background from detection or inadequate assay blocking is possible (general IHC practice).Inspect the detection-only control, then review blocking, washing and detection settings before interpreting tissue intensity (general IHC practice).
Two antibodies give different staining maps (general IHC practice).Their validation status differs, and HPA cautions that some antibodies target proteins from multiple genes (HPA antibodies; HPA tissue IHC).Record each antibody's identity and validation, compare cell populations against HPA tissue IHC, and report unresolved discordance rather than combining scores (HPA antibodies; HPA tissue IHC; general IHC practice).
IF/ICC question: is predominantly cytosolic fluorescence expected?Yes; HPA reports supported cytosol localisation in ICC-IF, while UniProt annotates cytoplasm and secretion (HPA subcellular ICC-IF; UniProt P31151).Interpret fluorescence against cell boundaries and controls; HPA cautions that its subcellular result uses antibodies targeting proteins from multiple genes (general IF practice; HPA subcellular ICC-IF).

Sample controls for S100A7 IHC & IF

🧪Run skin first and expect staining in cells of the corneal layer (HPA: High in skin corneal-layer cells). Use adipose tissue as a negative comparator, focusing on adipocytes (HPA: Not detected in adipose adipocytes); on the skin slide, use cells outside the corneal layer as internal background comparators, without assuming they are validated negatives (HPA: High in corneal-layer cells).
Positive control tissue: Skin (Cells in corneal layer, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show S100A7 in A-431, U2OS, with annotated localisation: Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a host- and class-matched rabbit IgG isotype control, and a biological negative such as S100A7 knockout material or a validated peptide-block control (caption: rabbit primary antibody; standard IHC controls). For skin sections, quench endogenous peroxidase and check for endogenous biotin background when using the caption’s biotin-based SABC/DAB detection (caption: biotinylated secondary and SABC/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A02369-1 paraffin-section caption does not state the fixative (caption: fixative unreported). The caption uses citrate retrieval at pH 6 for 20 minutes, but does not establish that retrieval is required; the supplied evidence also does not establish whether frozen sections or IF are easier (caption: heat-mediated citrate retrieval). In skin, distinguish brown DAB signal from pigment and assess background in the keratin-rich corneal layer (HPA: High in skin corneal-layer cells; standard IHC practice).

HPA tissue IHC evidence for S100A7

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Caution, targets protein from more than one gene. At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Skin Cells in corneal layer High Protein (IHC) HPA →
Cervix Squamous epithelial cells Medium Protein (IHC) HPA →
Epididymis Glandular cells Medium Protein (IHC) HPA →
Esophagus Squamous epithelial cells Medium Protein (IHC) HPA →
Nasopharynx Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Breast Adipocytes Not detected Protein (IHC) HPA →
Section 3

Advanced S100A7 IHC Tips

Use the catalog antibody’s paraffin-section workflow as a starting point, then assess S100A7 staining against its reported tissue and cellular distribution.

What retrieval should I use if S100A7 staining is weak?
Start with heat-mediated citrate pH 6 antigen retrieval for 20 minutes on paraffin sections (datasheet A02369-1). The selected image then used 10% goat serum block and 1 µg/ml primary antibody overnight at 4°C (datasheet A02369-1). If staining remains weak, first check tissue integrity, primary incubation, and development against a positive control, such as skin corneal-layer cells (HPA: High in skin corneal-layer cells; standard IHC practice). Only then compare a different retrieval condition on adjacent sections, holding antibody concentration and detection constant (standard IHC practice). Excess heating can damage morphology and make apparent gains in staining difficult to interpret (standard IHC practice).
How should I troubleshoot fixation-related loss of S100A7 staining?
The selected paraffin-section caption does not state a fixative, so S100A7-specific fixation sensitivity is unknown (datasheet A02369-1). Record the fixative and processing history for each specimen, and compare suspect and reference sections under identical staining conditions (standard IHC practice). Keep citrate retrieval at pH 6 for 20 minutes while evaluating that comparison, because those are the documented conditions for this antibody (datasheet A02369-1). Include a skin section with corneal-layer cells as a positive reference and inspect morphology before attributing a negative result to fixation (HPA: High in skin corneal-layer cells; standard IHC practice). A difference between specimens alone cannot establish target-specific fixation sensitivity (standard IHC practice).
Where should convincing S100A7 staining appear in tissue?
Prioritise cytoplasmic staining in the appropriate epithelial cells: S100A7 is cytoplasmic and secreted, with no transmembrane segment (UniProt P31151), while cytosolic localisation is supported in cell imaging (HPA subcellular). Skin corneal-layer cells show High staining, and several squamous epithelia show Medium staining in tissue IHC (HPA tissue IHC). Because secretion occurs through a non-classical pathway, extracellular signal may occur, but it needs morphological and control-based assessment before assignment to a producing cell (UniProt P31151; standard IHC practice). Compare compartment and cell identity across adjacent sections stained under the documented citrate pH 6 retrieval condition (datasheet A02369-1). Diffuse signal without cellular structure warrants background checks (standard IHC practice).
Could epitope biology explain inconsistent S100A7 IHC?
The record lists 0 isoforms, a protein chain spanning residues 2–101, and no glycosylation sites; it does not map this antibody’s epitope (UniProt P31151; datasheet A02369-1). S100A7 contains two EF-hand regions and an N-terminal acetylated residue, but their effects on this antibody’s staining have not been established here (UniProt P31151; datasheet A02369-1). Avoid assigning differential tissue staining to a particular isoform or masked epitope without antibody-specific evidence (standard IHC practice). The tissue IHC resource cautions that its antibodies target proteins from more than one gene, so use its distribution as context rather than proof of antibody specificity (HPA tissue IHC). Compare positive and negative tissue controls under the same retrieval and detection conditions (standard IHC practice).
How can I assess S100A7 by multiplex IF?
Treat IF/ICC as a separate application requiring its own antibody validation; the selected antibody evidence describes chromogenic staining of paraffin sections (datasheet A02369-1; standard IF practice). Pair S100A7 with an epithelial marker such as pan-cytokeratin to assess whether signal belongs to the expected squamous epithelial cells (HPA tissue IHC; standard IF practice). Select a fluorophore away from the specimen’s strongest autofluorescence and include single-stain, secondary-only, and unstained controls before interpreting overlap (standard IF practice). For a cytosolic epitope, test permeabilisation and compare it with an unpermeabilised condition; the antibody’s precise epitope is unreported (HPA subcellular; datasheet A02369-1; standard IF practice). Image the same compartments at matched exposure settings, accounting for possible secreted protein (UniProt P31151; standard IF practice).
What causes diffuse brown signal in S100A7 sections?
First distinguish cellular staining from diffuse DAB deposition by inspecting the section with a no-primary control and matched development time (standard IHC practice). The documented workflow used 10% goat serum block, biotinylated secondary antibody, streptavidin-biotin detection, and DAB (datasheet A02369-1). Check endogenous peroxidase and endogenous biotin contributions with appropriate controls before changing the primary antibody concentration (standard IHC practice). If background persists, compare wash conditions and primary incubation while retaining the documented citrate pH 6 retrieval as the reference (datasheet A02369-1; standard IHC practice). Interpret extracellular staining cautiously because S100A7 can be secreted (UniProt P31151).
How should I score S100A7 across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored compartment and cell population before counting, using the same rules for every section (standard IHC practice). For nucleated epithelial cells, report the percentage positive and an H-score calculated from intensity grades 0–3, yielding 0–300; retain the raw cell counts (standard IHC practice). Quantify corneal-layer staining separately, since skin corneal-layer cells are a reported High-staining population and a nucleated-cell denominator may be inappropriate there (HPA tissue IHC; standard IHC practice). Normalise each result to eligible epithelial cells or epithelial area, and exclude folds, necrosis, and section edges using prespecified criteria (standard IHC practice). Keep retrieval, imaging, and DAB development consistent across the comparison (standard IHC practice).
How do I separate true S100A7 signal from artefact?
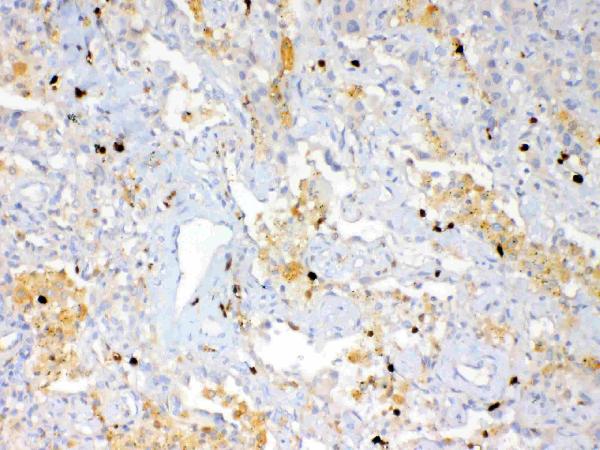
Look for reproducible cellular staining in expected populations, especially skin corneal-layer cells and squamous epithelial cells, with compatible cytoplasmic localisation (HPA tissue IHC; UniProt P31151). Secreted S100A7 can complicate assignment of extracellular signal to its producing cell, so compare cellular and adjacent extracellular patterns separately (UniProt P31151; standard IHC practice). Treat isolated edge staining, necrotic deposits, and signal persisting in a no-primary control as possible artefacts; check endogenous peroxidase in a DAB workflow (standard IHC practice). The selected paraffin image demonstrates staining in human lung cancer tissue under citrate pH 6 retrieval, but does not establish that every lung tumour should stain (datasheet A02369-1). Resolve unexpected compartments with morphology and independent specificity controls (standard IHC practice).
Boster reagents

Best S100A7 / Protein S100-A7 IHC Antibodies

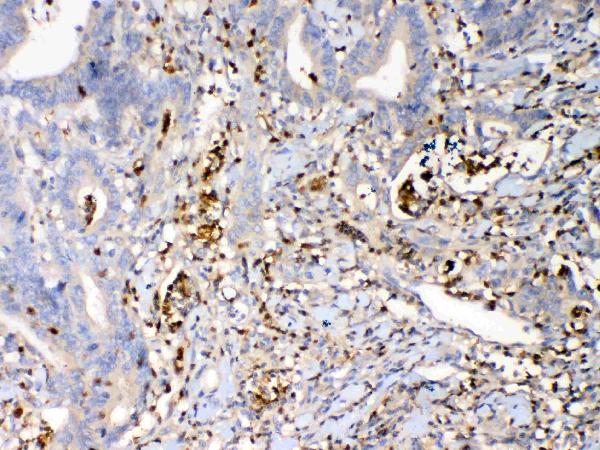
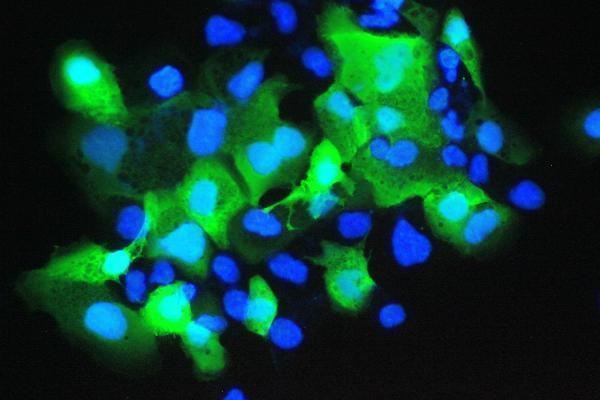
A02369-1 has IHC images from paraffin sections of human lung and rectal cancer tissue and IF data from A431 cells (catalog image captions). Listed reactivity covers human, mouse and rat (catalog reactivity).

Real IHC data IHC analysis of Psoriasin using anti-Psoriasin antibody (A02369-1). Psoriasin was detected in paraffin-embedded section of human lung cancer tissue. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-Psoriasin Antibody (A02369-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-Psoriasin/S100A7 Antibody ®
Cat # A02369-1

A02369-1 is listed for IHC and shown on paraffin sections of human lung and rectal cancer tissue (catalog applications; catalog IHC captions). A02369-1 is also listed for IF/ICC and shown in A431 cells by IF (catalog applications; catalog IF caption).

Which to pick: Choose A02369-1 for chromogenic IHC on paraffin sections: its IHC captions describe citrate pH 6 retrieval and DAB detection; the fixative is unreported (catalog IHC captions). For IF/ICC, the same SKU lists both applications and has an A431 IF image (catalog applications; catalog IF caption). For mouse or rat samples, A02369-1 lists reactivity with both species, but the supplied IHC images show human tissue; clonality is unreported (catalog reactivity; catalog IHC captions; catalog clone field).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P31151 (S10A7_HUMAN, Protein S100-A7).
  2. Human Protein Atlas. S100A7 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. S100A7 subcellular location (ICC-IF): Localized to the cytosol. Caution: Based on antibodies targeting proteins from multiple genes..
  4. Human Protein Atlas. S100A7 antibody validation summary (3 antibodies).
  5. Compensatory effect-based oxidative stress management microneedle for psoriasis treatment. Bioactive materials 2025 — PMC11732109.
  6. S100A7 as a predictive biomarker in malignant transformation of oral epithelial dysplastic lesions. Discover oncology 2025 — PMC12031700.
  7. The Characteristics and Function of S100A7 Induction in Squamous Cell Carcinoma: Heterogeneity, Promotion of Cell Proliferation and Suppression of Differentiation. PloS one 2015 — PMC4460013.
  8. Nuclear S100A7 is associated with poor prognosis in head and neck cancer. PloS one 2010 — PMC2914786.
  9. PubMed PMID:1940442 — UniProt-cited evidence.
  10. PubMed PMID:16710414 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.