This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan SDCBP2 chromogenic IHC in paraffin sections using gastrointestinal and gallbladder tissue staining as a reference (HPA tissue IHC). This guide covers fixation, the catalog antibody’s staining conditions, and interpretation where presumed off-target binding may complicate scoring (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic staining in GI tract and gallbladder (HPA tissue IHC) | |
| Staining pattern | GI enterocytes/endocrine cells and gallbladder glands: cytoplasmic (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A13491-2) | |
| Positive control | Colon+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target binding can complicate scoring (HPA tissue IHC) | |
| Regulation | Expressed in differentiated keratinocytes (UniProt) | |
| Isoform / epitope | 2 isoforms (1, 3); epitope impact undetermined (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet A13491-2) with the published SDCBP2 staining protocol for LUAD tissue microarrays (PMC12705533).
| Sample | Paraffin-embedded human breast cancer tissue; fixative not specified (datasheet A13491-2) |
| Fixation | Image fixative and duration unreported (datasheet A13491-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A13491-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A13491-2) |
| Primary antibody | Rabbit anti-SDCBP2, 2-5 μg/ml (datasheet A13491-2) |
| Primary incubation | Overnight at 4 °C (datasheet A13491-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A13491-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SDCBP2-positive staining in enterocytes - Microvilli of colon (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression mainly in gastrointestinal tract and gallbladder. No signal in the no-primary control. |
In paraffin-section IHC, expect SDCBP2 staining chiefly in the cytoplasm of gastrointestinal and gallbladder cells, with strong staining in the specific cell populations listed below (HPA: tissue IHC, Enhanced). Apical microvillar staining is also plausible in colon enterocytes (HPA: High in colon enterocyte microvilli; UniProt Q9H190: apical enrichment). SDCBP2 has no transmembrane segment; nuclear localization is documented in a separate cellular context (UniProt Q9H190: topology and localization).
| Strong cytoplasmic staining in small-intestinal enterocytes or stomach and gallbladder glandular cells. | This matches the reported high-staining populations (HPA: High in each population). Assess the identified cells and their compartments; a uniformly brown section does not reproduce this selective pattern (general IHC practice). |
| Prominent staining at colon enterocyte microvilli, with nearby cells less conspicuous. | An apical pattern is credible here (HPA: High in colon enterocyte microvilli; UniProt Q9H190: apical enrichment). Record it separately from broader cytoplasmic staining; a sharp surface signal alone does not establish that every colon cell is positive (HPA: cell-specific IHC finding). |
| Staining is confined to extracellular material or unrelated structures, with no expected cellular pattern. | Treat this as a localization mismatch requiring review (HPA: chiefly cytoplasmic tissue profile; UniProt Q9H190: cytoplasm and intracellular locations). Nuclear staining alone needs context: nucleoplasm is supported by ICC-IF and is not automatically an artefact (HPA: subcellular ICC-IF). |
| Strong staining appears in adipocytes or lung alveolar cells instead of the expected positive populations. | Investigate cross-reactivity or endogenous detection activity before assigning SDCBP2 positivity (HPA: not detected in adipocytes and alveolar cells; HPA: presumed off-target binding disregarded). These HPA findings are cell-specific comparisons, not a claim that every cell in those tissues is negative. |
| The section is diffusely brown, or a known-positive gastrointestinal population has no detectable staining. | Diffuse color limits cell-specific interpretation; absent signal in a reported high-staining population leaves assay performance unresolved (HPA: high gastrointestinal populations; general IHC practice). Check controls and staining conditions before calling the tissue negative. |
| Cell population and tissue context | HPA reports High staining in small-intestinal enterocytes, stomach and gallbladder glandular cells, and duodenal and rectal endocrine cells; it reports other populations as Medium, Low, or Not detected (HPA: tissue IHC). Score the named cells rather than averaging the whole section (general IHC practice). |
| Antibody evidence | The tissue profile has Enhanced reliability, with medium staining-to-RNA consistency and presumed off-target binding observed and disregarded (HPA: tissue IHC). HPA064490 has Enhanced IHC validation; HPA005804 has no stated IHC status in this payload (HPA: antibody validation). Interpret unexpected staining cautiously. |
| Intracellular distribution and topology | SDCBP2 has cytoplasmic, nuclear, and membrane-associated localizations but no transmembrane segment (UniProt Q9H190: localization and topology). Tissue IHC is chiefly cytoplasmic, while ICC-IF supports nucleoplasm and cytosol and lists Golgi localization as uncertain (HPA: tissue IHC and subcellular ICC-IF). Match the compartment claim to the assay. |
| Processing and isoforms | The record lists a single 1–292 chain, no signal peptide or propeptide, and two isoforms (UniProt Q9H190: processing and isoforms). These facts do not identify the antibody epitope or establish isoform coverage; avoid explaining an absent IHC signal by cleavage or shedding without further evidence. |
| IF/ICC Q: Is nuclear SDCBP2 staining expected? | A: Mainly nucleoplasmic localization is supported in ICC-IF; cytosol is also supported, while Golgi localization is uncertain (HPA: subcellular ICC-IF). Use the separate IF/ICC guide for its workflow; these cellular findings do not prescribe a paraffin-section IHC protocol. |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive stomach glandular cells or small-intestinal enterocytes show no signal. | A reported High population is absent, so the result cannot yet distinguish a weak assay from a sample-specific finding (HPA: tissue IHC). | Confirm that the expected cells are present and review section quality, retrieval, antibody dilution, detection, and a positive control (general IHC practice). Do not infer SDCBP2-specific retrieval or fixation sensitivity from HPA staining levels. |
| Color develops across the section and cell boundaries are hard to score. | Diffuse background can arise from detection or blocking conditions (general IHC practice); HPA also flags presumed off-target binding in its tissue assessment (HPA: reliability note). | Examine a no-primary control, review blocking and detection steps, and adjust assay conditions using an expected positive population as a reference (general IHC practice; HPA: High gastrointestinal populations). |
| Adipocytes or lung alveolar cells stain strongly. | That conflicts with the reported Not detected status for those named cells; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice). | Compare the named cells with a positive-control section and inspect a no-primary control (general IHC practice). Report the discrepancy without extending the HPA negative call to every cell in the tissue. |
| Only extracellular deposits or a uniform surface rim stain. | The pattern does not match the chiefly cytoplasmic tissue profile or the reported intracellular and apical localizations (HPA: tissue IHC; UniProt Q9H190: localization). | Check morphology and counterstain, then compare with the expected cell-specific pattern (general IHC practice; HPA: tissue IHC). Keep colon microvillar staining distinct from a nonspecific rim (HPA: High in colon enterocyte microvilli). |
| A nuclear signal appears and is being marked as automatically false. | SDCBP2 can occupy nuclear compartments, and nucleoplasmic ICC-IF localization is supported (UniProt Q9H190: localization; HPA: subcellular ICC-IF). The tissue IHC summary, however, is chiefly cytoplasmic (HPA: tissue IHC). | Record the assay and cell type, compare tissue staining with its cytoplasmic reference pattern, and assess controls before interpreting nuclear IHC staining (HPA: tissue IHC; general IHC practice). |
| Different antibodies give different tissue patterns. | HPA reports presumed off-target binding in the tissue assessment, and the supplied IHC validation status differs between HPA064490 and HPA005804 (HPA: reliability note and antibody validation). | Prioritize the antibody with stated Enhanced IHC validation, compare staining in the same named positive and not-detected populations, and document any discordance (HPA: antibody validation and tissue IHC; general IHC practice). |




Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Colon | Enterocytes - Microvilli | High | Protein (IHC) | HPA → |
| Duodenum | Endocrine cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Rectum | Endocrine cells | High | Protein (IHC) | HPA → |
| Small intestine | Enterocytes | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Epididymis | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Lung | Alveolar cells | Not detected | Protein (IHC) | HPA → |
Troubleshoot SDCBP2 staining in paraffin sections by checking retrieval, cell type, compartment, and controls before comparing signal intensity.
A13491-2 is listed for human IHC and IF (catalog: applications and reactivity), with images of paraffin-embedded human cancer tissue and U20S cells (catalog: IHC and IF image captions).
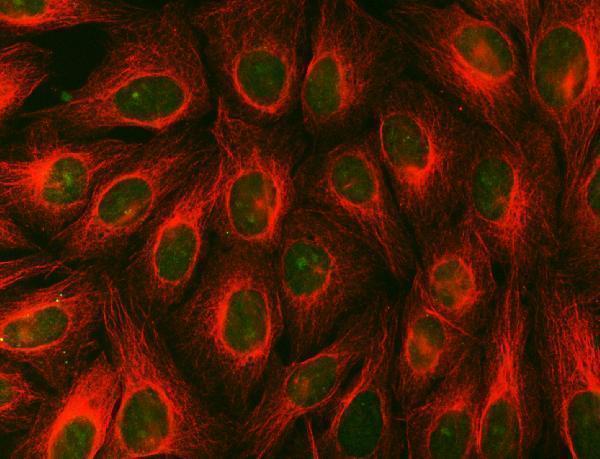
A13491-2 will render with an IHC figure from a paraffin-embedded human breast cancer section (catalog: IHC image caption). The same SKU is listed for IF/ICC and has an IF image from U20S cells (catalog: applications and IF image caption).
Which to pick: Choose A13491-2 for human paraffin-section IHC: its caption reports EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (catalog: IHC image caption). For IF/ICC, A13491-2 is also listed and has a U20S-cell IF image at 5 μg/ml (catalog: applications and IF image caption). No cross-species choice is supported because A13491-2 lists human reactivity only (catalog: reactivity).