SHARPIN / Sharpin · IHC design guide

Design Immunohistochemistry for SHARPIN

Plan SHARPIN IHC in paraffin sections using the documented cytoplasmic tissue pattern and a catalog antibody with an IHC-P protocol (HPA tissue IHC; datasheet A06687-2). Compare staining by cell type, with colon glandular cells as a high-staining reference (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SHARPIN (IHC for SHARPIN): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A06687-2, validated IHC image, and IHC protocol steps
Printable SHARPIN IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody A06687-2, controls and protocol steps. Open the full SHARPIN IHC guide →

SHARPIN Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Colon glandular cells show high cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A06687-2)
Positive control ⓘ Colon+4 more · see all
Negative control ⓘ Bone marrow+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A06687-2)
Caveat Staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Upregulated in some tumor tissues (UniProt)
Isoform / epitope 2 isoforms; epitope differences unspecified (UniProt)
Section 1

Recommended SHARPIN IHC & IF Protocols

The catalog antibody uses EDTA retrieval (datasheet A06687-2). These published SHARPIN IHC protocols describe skin and tumor sections (PMC6434243; PMC7371178; PMC6256368).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human liver tissue; fixative not specified (datasheet A06687-2)
FixationImage fixative and duration unreported (datasheet A06687-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A06687-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A06687-2)
Primary antibodyRabbit anti-SHARPIN, 2-5 μg/ml (datasheet A06687-2)
Primary incubationOvernight at 4 °C (datasheet A06687-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A06687-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSHARPIN-positive staining in glandular cells of colon (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 for the catalog antibody (datasheet A06687-2); the published citrate protocols used other SHARPIN antibodies (PMC6434243; PMC6256368).
Section 2

What Is the Expected SHARPIN Staining Pattern?

SHARPIN should give predominantly cytoplasmic staining in paraffin tissue sections, with prominent signal in colon and fallopian tube glandular cells and lymph node non-germinal center cells (HPA: general cytoplasmic expression; High in these cells). It is a cytosolic protein with no transmembrane segment (UniProt Q9H0F6: location and topology). HPA rates its tissue IHC evidence Approved, with medium consistency between staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Clear cytoplasmic staining in colon or fallopian tube glandular cells.This fits the expected compartment and a reported High-staining cell population (HPA: general cytoplasmic expression; High in both glandular cell populations). Compare intensity within the same run because chromogenic signal also depends on the staining workflow (general IHC practice).
Predominantly nuclear staining, with little cytoplasmic signal.A nuclear-only pattern conflicts with the reported tissue pattern and cytosolic location (HPA: general cytoplasmic expression; UniProt Q9H0F6: cytosol). Treat it as suspect and check controls and detection conditions before assigning it to SHARPIN (general IHC practice).
Strong staining in smooth muscle cells while nearby expected cells are weak.HPA reports SHARPIN as Not detected in smooth muscle cells (HPA: smooth muscle cells). Unexpected cell staining may reflect antibody cross-reactivity or endogenous chromogenic activity; a negative reagent control helps distinguish detection artefact from primary-antibody-dependent staining (general IHC practice).
Uniform color across cells, stroma and blank tissue spaces.A diffuse, poorly cell-associated deposit does not match the reported cytoplasmic pattern (HPA: general cytoplasmic expression). Review background controls, blocking, washing and detection development before scoring it as positive (general IHC practice).
No signal in colon glandular cells on an otherwise interpretable slide.Colon glandular cells are reported High, so an absent result needs a technical check (HPA: colon glandular cells, High). Confirm tissue identity, section integrity and control staining; an HPA population-level observation does not guarantee every specimen or section will stain (HPA: tissue IHC profile; general IHC practice).
💡Expected SHARPIN appearanceCall a positive result when cytoplasmic chromogen is readily visible in expected cells, such as colon glandular cells with High reported staining; isolated nuclear color or diffuse tissue-wide deposit is suspect (HPA: general cytoplasmic expression; colon glandular cells, High; general IHC practice).
How each factor affects the staining
Cell and tissue contextHPA reports High staining in fallopian tube glandular cells, lymph node non-germinal center cells and late spermatids, but Not detected in bone marrow hematopoietic cells (HPA: tissue IHC). Interpret each cell population separately; UniProt's high skeletal-muscle tissue expression does not override HPA's Low staining in myocytes (UniProt Q9H0F6: tissue specificity; HPA: skeletal muscle myocytes, Low).
Topology and compartmentSHARPIN has no transmembrane segment and is annotated in the cytosol, with synaptic enrichment in mature neurons (UniProt Q9H0F6: topology and location). Tissue IHC is summarized as generally cytoplasmic; do not require a membrane rim to call a paraffin-section result positive (HPA: tissue IHC profile).
Isoforms and modificationsUniProt lists two isoforms and phosphoserines at residues 165 and 312 (UniProt Q9H0F6: isoforms and modified residues). The supplied evidence does not map the IHC antibody epitope, so these entries cannot establish isoform-specific staining or a phosphorylation-dependent pattern (supplied UniProt/HPA record).
Antibody evidence and retrievalOne listed antibody, HPA044453, has Approved IHC status; the tissue profile has medium staining–RNA consistency (HPA: antibodies; tissue IHC reliability). Antigen retrieval can be optimized as a general paraffin IHC step, but target-specific fixation sensitivity is unreported in the supplied record (general IHC practice; supplied UniProt/HPA record).
IF/ICC Q: Is membrane staining expected?A: HPA's ICC-IF summary places SHARPIN mainly at the plasma membrane, with additional Golgi and cytosolic signal (HPA: subcellular ICC-IF). This assay-specific observation can coexist with the general cytoplasmic tissue IHC profile; assess IF/ICC using its separate guide (HPA: tissue IHC profile; subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in colon glandular cells.The positive population may be missing from the section, or the IHC run may have failed (HPA: colon glandular cells, High; general IHC practice).Verify the glandular cells on the counterstain, then check run controls, primary-antibody incubation and chromogen development (general IHC practice).
Signal is weak across expected positive cells.Low detection sensitivity or an unsuitable retrieval condition may reduce visible chromogen (general IHC practice); no SHARPIN-specific fixation effect is established (supplied UniProt/HPA record).Compare a known-positive section in the same run; optimize retrieval and detection within the antibody's IHC instructions (general IHC practice).
Diffuse color obscures cell boundaries.Background from inadequate blocking, washing or excess detection reagent can obscure localization (general IHC practice).Check a negative reagent control, improve blocking and washing, and adjust chromogen development before scoring (general IHC practice).
Strong nuclear-only staining.The localization conflicts with cytosolic SHARPIN and general cytoplasmic tissue staining (UniProt Q9H0F6: location; HPA: tissue IHC profile).Review the counterstain and negative control; repeat with adjusted primary-antibody and detection conditions if the pattern persists (general IHC practice).
Unexpected staining in cells reported as Not detected.Cross-reactivity or endogenous detection activity is possible, while HPA observations are cell-population references rather than guarantees for every specimen (HPA: tissue IHC; general IHC practice).Compare a matched negative reagent control and an expected positive cell population; score the unexpected cells separately (general IHC practice; HPA: tissue IHC).

Sample controls for SHARPIN IHC & IF

🧪Run colon first and expect staining in glandular cells (HPA: High in colon glandular cells). Use parathyroid glandular cells as the negative tissue (HPA: Not detected); on the colon slide, treat cells without specific signal as a background reference without assuming a named cell population is SHARPIN-negative (standard IHC practice).
Positive control tissue: Colon (Glandular cells, HPA High)
Negative control tissue: Bone marrow (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SHARPIN in PC-3, SiHa, U2OS, with annotated localisation: Plasma membrane (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and rabbit IgG controls matched to the primary antibody’s format and concentration, plus a verified SHARPIN-knockout biological negative where available (caption: rabbit primary; standard IHC practice). Quench endogenous peroxidase and check for background in colon sections before interpreting DAB staining (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window is unreported, and the fixative used for the selected A06687-2 paraffin section is unreported (caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used in that example, but the evidence does not establish that retrieval is required (caption: heat-mediated EDTA retrieval). The supplied evidence does not establish whether frozen sections or IF are easier; colon tissue autofluorescence may complicate IF interpretation (standard IF practice).

HPA tissue IHC evidence for SHARPIN

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Colon Glandular cells High Protein (IHC) HPA →
Fallopian tube Glandular cells High Protein (IHC) HPA →
Lymph node Non-germinal center cells High Protein (IHC) HPA →
Testis Elongated or late spermatids High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Section 3

Advanced SHARPIN IHC Tips

Troubleshoot SHARPIN staining in paraffin sections by checking retrieval, controls, cellular location, and scoring within defined cell populations.

How should I adjust retrieval when SHARPIN staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A06687-2). The selected liver image used this retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C (datasheet A06687-2). If staining is weak, compare retrieval durations such as 10 and 20 minutes while keeping detection and section thickness constant (standard IHC practice). Include a known positive cell population, such as colon glandular cells, in each comparison (HPA: High in colon glandular cells). Check tissue morphology alongside signal, because excessive heat can damage sections and make staining harder to interpret (standard IHC practice).
Could fixation explain variable SHARPIN staining between paraffin blocks?
SHARPIN-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (datasheet A06687-2). Record fixative, fixation duration, tissue thickness, and processing for each block before attributing a staining difference to biology (standard IHC practice). For prospectively prepared samples, compare matched tissue fixed for 6 and 24 hours in 10% neutral buffered formalin, using identical retrieval and detection (standard IHC practice). Assess signal within the same cell type and alongside morphology, since poorly preserved tissue complicates scoring (standard IHC practice). Do not infer fixation sensitivity from SHARPIN’s cytosolic location or phosphorylation sites (UniProt Q9H0F6).
Is membrane staining compatible with SHARPIN localisation?
Evaluate the compartment in context: SHARPIN is described in cytosol and at neuronal synapses (UniProt Q9H0F6). Separate imaging evidence places it mainly at the plasma membrane, with additional Golgi and cytosolic signal (HPA subcellular: approved membrane and Golgi; supported cytosol). SHARPIN has no transmembrane segment, so membrane-associated staining does not establish that an epitope is exposed on the cell surface (UniProt Q9H0F6 topology). Score cytoplasmic and membrane patterns separately, using cell boundaries and a counterstain to avoid assigning adjacent cells’ signal incorrectly (standard IHC practice). Treat exclusively nuclear staining as questionable until an independent antibody or specificity control supports it (UniProt Q9H0F6; standard IHC practice).
Can this IHC stain distinguish SHARPIN isoforms or phosphorylation states?
SHARPIN has 2 annotated isoforms, but the supplied antibody evidence gives no epitope map or isoform reactivity (UniProt Q9H0F6; datasheet A06687-2). Its ubiquitin-like domain spans residues 219–288, and annotated phosphoserines occur at 165 and 312 (UniProt Q9H0F6). Those annotations alone cannot show whether fixation or retrieval masks this antibody’s epitope, or whether phosphorylation changes binding (UniProt Q9H0F6; standard IHC practice). Keep retrieval and detection constant when comparing samples, then seek epitope information or an independently validated antibody if isoform assignment matters (standard IHC practice). Report the result as SHARPIN immunoreactivity unless reagent-specific evidence establishes finer discrimination (standard IHC practice).
How should I assess SHARPIN localisation in a separate IF experiment?
For multiplex IF, pair SHARPIN with an independently validated glandular-cell marker when examining colon, where glandular cells show high tissue-IHC staining (HPA tissue IHC: High in colon glandular cells). Choose a far-red channel when tissue autofluorescence obscures shorter wavelengths, and image single-label controls to check bleed-through (standard IF practice). HPA images report membrane, Golgi, and cytosolic locations, while UniProt describes cytosol and synapses (HPA subcellular; UniProt Q9H0F6). Test gentle permeabilisation for an intracellular epitope; the antibody’s epitope and its accessibility on intact cells are unreported (datasheet A06687-2; UniProt Q9H0F6 topology). Assess IF antibody validation separately from the paraffin-section IHC image (datasheet A06687-2; standard IF practice).
What should I check when DAB obscures SHARPIN-positive cells?
First inspect a section without primary antibody to assess secondary-reagent and tissue-associated background (standard IHC practice). Block endogenous peroxidase before HRP detection, then limit DAB development so cellular boundaries remain visible (standard chromogenic IHC practice). The selected image used 10% goat serum blocking, 2 μg/ml primary overnight at 4°C, and an HRP-based DAB readout (datasheet A06687-2). If diffuse staining persists, titrate primary concentration and development time separately while retaining the same EDTA pH 8.0 retrieval (datasheet A06687-2; standard IHC practice). Compare background in weakly stained areas with viable, morphologically intact candidate-positive cells before scoring (standard IHC practice).
How can I score SHARPIN IHC across heterogeneous samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because reported SHARPIN expression varies by cell type and cytoplasmic staining is common (HPA tissue IHC). For interpretable cells, record the percentage at each intensity from 0–3 and calculate an H-score from 0–300 (standard IHC practice). Alternatively, report percentage-positive cells or positive-cell density per mm², with the threshold and sampling method stated (standard IHC practice). Normalise counts to viable cells of the same type, or density to the measured viable tissue area, excluding necrosis and damaged edges (standard IHC practice). Keep imaging, DAB development, and scoring rules consistent across comparison groups (standard IHC practice).
How do I separate true SHARPIN staining from artefact?
Look for reproducible staining in expected cell populations, such as colon glandular cells, which HPA reports as High (HPA tissue IHC). Compare with a low or undetected population, while recognising that HPA reports only medium consistency between antibody staining and RNA data (HPA tissue IHC: Approved). Review compartment: cytoplasmic signal fits tissue-IHC observations, while a purely nuclear pattern needs independent support (HPA tissue IHC; UniProt Q9H0F6). Reject apparent positives confined to cut edges, necrotic regions, or deposits that also appear without primary antibody (standard IHC practice). Use a no-primary control and endogenous peroxidase block to investigate DAB signal unrelated to SHARPIN binding (standard chromogenic IHC practice).
Boster reagents

Best SHARPIN / Sharpin IHC Antibodies

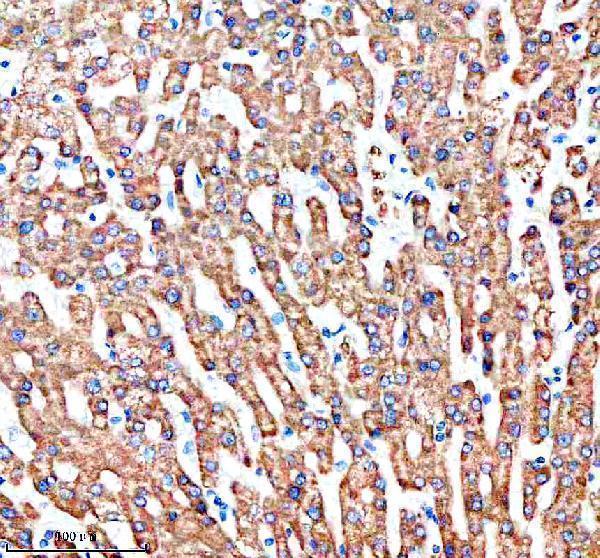
The catalog includes human, mouse and rat reactive anti-SHARPIN antibodies for IHC; the rendered figure shows a human liver paraffin section (catalog reactivity; A06687-2 IHC caption). No IF data are supplied (catalog image records).

Real IHC data IHC analysis of SHARPIN using anti-SHARPIN antibody (A06687-2). SHARPIN was detected in a paraffin-embedded section of human liver tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SHARPIN Antibody (A06687-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SHARPIN Antibody ®
Cat # A06687-2

A06687-2 is the sole rendered card, with IHC listed for human, mouse and rat reactivity (catalog applications and reactivity). Its own figure shows chromogenic IHC on a human liver paraffin section; the fixative is unreported (A06687-2 IHC caption).

Which to pick: Choose A06687-2 for human tissue IHC when a directly illustrated paraffin section is useful; its caption reports EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody, but no fixative (A06687-2 IHC caption). For cross-species work, both SKUs list human, mouse and rat reactivity and IHC, while only A06687-2 supplies an IHC figure, on human tissue (catalog applications and reactivity; A06687-2 IHC caption). Neither SKU lists IF/ICC or supplies an IF image, so neither has payload support for an IF/ICC pick (catalog applications and image records).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9H0F6 (SHRPN_HUMAN, Sharpin).
  2. Human Protein Atlas. SHARPIN tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. SHARPIN subcellular location (ICC-IF): Mainly localized to the plasma membrane. In addition localized to the Golgi apparatus and cytosol..
  4. Human Protein Atlas. SHARPIN antibody validation summary (2 antibodies).
  5. Sharpin promotes hepatocellular carcinoma progression via transactivation of Versican expression. Oncogenesis 2016 — PMC5177774.
  6. Aberrant expression and high-frequency mutations of SHARPIN in nonmelanoma skin cancer. Experimental and therapeutic medicine 2019 — PMC6434243.
  7. Keratinocyte-specific deletion of SHARPIN induces atopic dermatitis-like inflammation in mice. PloS one 2020 — PMC7371178.
  8. Shank-associated RH domain-interacting protein expression is upregulated in entodermal and mesodermal cancer or downregulated in ectodermal malignancy. Oncology letters 2018 — PMC6256368.
  9. PubMed PMID:12753155 — UniProt-cited evidence.
  10. PubMed PMID:20179993 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.