SIGMAR1 / Sigma non-opioid intracellular receptor 1 · IHC design guide

Design Immunohistochemistry for SIGMAR1

Plan SIGMAR1 paraffin section IHC around the cytoplasmic staining reported in most tissues, with high staining in hepatocytes (HPA tissue IHC). This guide covers fixation consistency, antibody concentration, chromogenic detection and interpretation of its ER and nuclear envelope localisation (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SIGMAR1 (IHC for SIGMAR1): expected localisation Cytoplasmic staining (HPA tissue IHC); ER and nuclear envelope localisation (UniProt), antibody A02493-2, validated IHC image, and IHC protocol steps
Printable SIGMAR1 IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC); ER and nuclear envelope localisation (UniProt), antibody A02493-2, controls and protocol steps. Open the full SIGMAR1 IHC guide →

SIGMAR1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC); ER and nuclear envelope localisation (UniProt)
Staining pattern Cytoplasmic in most tissues; high in hepatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02493-2)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Ligand binding can alter localisation (UniProt)
Regulation Expression regulation is not established (UniProt)
Isoform / epitope 5 isoforms; map the epitope to each; residues 31–223 are cytoplasmic (UniProt)
Section 1

Recommended SIGMAR1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol (datasheet A02493-2) with four published SIGMAR1 paraffin-section protocols (PMC11858467; PMC10083329; PMC11089145; PMC11351121).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat colon tissue; fixative not specified (datasheet A02493-2)
FixationImage fixative and duration unreported (datasheet A02493-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02493-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02493-2)
Primary antibodyRabbit anti-SIGMAR1, 2-5 μg/ml (datasheet A02493-2)
Primary incubationOvernight at 4 °C (datasheet A02493-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02493-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSIGMAR1-positive staining in purkinje cells of cerebellum (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA at pH 8.0 for the catalog antibody (datasheet A02493-2); published citrate retrieval offers a tissue-specific alternative (PMC11351121).
Section 2

What Is the Expected SIGMAR1 Staining Pattern?

SIGMAR1 is a membrane protein with 1 transmembrane segment and a cytoplasmic region spanning residues 31–223 (UniProt Q99720 topology). In paraffin IHC, expect predominantly cytoplasmic staining in many tissues (HPA: tissue IHC profile), especially Purkinje cells, hepatocytes, and trophoblastic cells (HPA: High). HPA rates the tissue staining evidence Enhanced, with medium consistency between staining and RNA expression (HPA: reliability description).

What am I looking at on my slide?
Cytoplasmic staining in hepatocytes, trophoblastic cells, or cerebellar Purkinje cells.This fits the observed tissue pattern: each cell population is rated High (HPA: tissue IHC). An ER-associated or nuclear-envelope distribution is biologically plausible (UniProt Q99720 subcellular location), but routine chromogenic IHC may not resolve those membranes individually (general IHC practice). Judge the result against cell identity and background as well as intensity.
Predominantly filled-nuclear staining, with little cytoplasmic signal, in an expected-positive population.This departs from HPA’s predominantly cytoplasmic tissue profile (HPA: tissue IHC). UniProt reports nuclear-envelope membranes, which can appear close to the nucleus; it does not establish diffuse nucleoplasmic staining (UniProt Q99720 subcellular location). Check morphology and a control section before assigning a nuclear pattern (general IHC practice).
Strong signal in adipocytes, marrow hematopoietic cells, or soft-tissue fibroblasts.These populations are listed as Not detected in the sampled HPA tissue IHC images (HPA: tissue IHC). Unexpected staining may reflect nonspecific antibody binding or endogenous detection activity (general IHC practice). The HPA entries are reference observations, so investigate the discrepancy without treating them as proof that every specimen must be negative.
Diffuse color across tissue, stroma, and spaces without recognizable cellular boundaries.An even deposit obscures the cell-associated pattern reported by HPA (HPA: cytoplasmic expression in most tissues). Excess primary antibody, inadequate blocking or washing, and chromogen or endogenous-enzyme background are possible general IHC causes (general IHC practice). Such a slide cannot establish a SIGMAR1-positive compartment.
No detectable stain in a hepatocyte-rich liver section run as a positive control.HPA rates hepatocytes High (HPA: liver tissue IHC), making a blank control a reason to check the assay before interpreting test sections. Confirm that the section contains preserved hepatocytes, the IHC-validated antibody and detection reagents were applied, and the run controls worked (general IHC practice). A blank result alone does not identify the failed step.
💡Expected SIGMAR1 appearanceCall a section positive when identifiable expected cells show cytoplasmic chromogenic staining, strongest among hepatocytes, trophoblastic cells, or Purkinje cells (HPA: High; HPA: cytoplasmic profile); isolated filled-nuclear color or staining that ignores cell boundaries warrants investigation (UniProt Q99720 subcellular location; general IHC practice).
How each factor affects the staining
Membrane topology and apparent compartmentSIGMAR1 has 1 transmembrane segment at residues 10–30, followed by a cytoplasmic region (UniProt Q99720 topology). UniProt places it at the ER and nuclear-envelope membranes during interphase (UniProt Q99720 subcellular location). This supports a cytoplasmic or perinuclear appearance, but the slide cannot by itself distinguish those closely spaced membranes (general IHC practice).
Tissue and cell selectionHPA reports High staining in hepatocytes, trophoblastic cells, and Purkinje cells; Medium staining in several epithelial or neuronal populations; and Low staining in kidney tubules, prostate glands, and cardiomyocytes (HPA: tissue IHC). Choose a documented High population for a positive control. A Low population is a less decisive test of assay sensitivity (general IHC practice).
Strength and limits of the IHC evidenceHPA labels its tissue IHC evidence Enhanced while describing medium consistency with RNA expression (HPA: reliability description). Two listed antibodies have Enhanced IHC status and one has Approved IHC status (HPA: antibody validation). Those ratings support the reference pattern; they do not validate an unlisted catalog antibody or prove that every tissue section will match it.
Isoforms and protein processingUniProt lists 5 SIGMAR1 isoforms, no annotated signal peptide or propeptide, and no annotated glycosylation sites (UniProt Q99720 isoforms and processing). The payload gives no antibody epitope or isoform coverage. Do not infer that an unexpected compartment represents a particular isoform, cleavage product, or glycosylated form from this IHC result.
IF/ICC: what pattern can this section support?The HPA subcellular summary says Membrane, but provides no main location or ICC-IF image-bearing cell lines (HPA: subcellular ICC-IF). UniProt supports ER and nuclear-envelope membrane localization (UniProt Q99720 subcellular location). These facts give a localization expectation, not an IF/ICC validation result; the separate IF/ICC guide should address that application.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The liver positive control is blank.An assay or section problem is possible despite High hepatocyte staining in HPA (HPA: liver tissue IHC). The observation alone does not identify a SIGMAR1-specific cause.Check hepatocyte preservation, reagent application, detection chemistry, and run controls; then optimize retrieval and antibody dilution as general paraffin-IHC variables (general IHC practice). No SIGMAR1-specific retrieval or fixation sensitivity is established here.
The whole section has brown haze or diffuse color.Broad background can result from excess primary antibody, incomplete washing or blocking, or endogenous detection activity (general IHC practice). It obscures HPA’s cell-associated cytoplasmic profile (HPA: tissue IHC).Compare a no-primary control, review blocking and wash steps, and titrate the primary and chromogen development under the assay’s general IHC controls (general IHC practice). Score cells only after background permits compartment assessment.
The strongest signal fills nuclei.HPA describes cytoplasmic tissue staining, while UniProt specifies nuclear-envelope membranes rather than a general nucleoplasmic pool (HPA: tissue IHC; UniProt Q99720 subcellular location).Recheck counterstained cell outlines and compare an expected-positive tissue with a no-primary control (general IHC practice). Record a true nuclear-only pattern as discordant instead of reclassifying it as nuclear-envelope staining.
Adipocytes, marrow cells, or fibroblasts stain strongly.Those sampled populations are Not detected in HPA tissue IHC (HPA: tissue IHC). Nonspecific binding or endogenous detection activity is possible (general IHC practice).Inspect the matching no-primary control and tissue morphology; adjust general blocking or detection steps if background persists (general IHC practice). Confirm the unexpected cell pattern independently before attributing it to SIGMAR1.
A Low reference tissue stains weakly or inconsistently.HPA rates kidney tubules, prostate glandular cells, and cardiomyocytes Low (HPA: tissue IHC). Their faint staining offers limited assurance that a negative run is technically sound (general IHC practice).Include a documented High population, such as hepatocytes, in the same run when feasible (HPA: tissue IHC). Interpret weak target staining only after checking that control and the section’s cellular morphology (general IHC practice).
A perinuclear rim is hard to distinguish from diffuse cytoplasm.UniProt reports ER and nuclear-envelope membrane localization, and HPA reports a broad cytoplasmic tissue pattern (UniProt Q99720 subcellular location; HPA: tissue IHC). Chromogenic light microscopy has limited resolution for these adjacent structures (general IHC practice).Report the observable cytoplasmic or perinuclear pattern and the identified cell type; avoid assigning a precise membrane from this section alone (general IHC practice). Use the separate IF/ICC guide if subcellular resolution is the study goal.

Sample controls for SIGMAR1 IHC & IF

🧪Run liver first and expect hepatocytes to stain (HPA: hepatocytes High). Use adipose tissue as the negative tissue and expect adipocytes to lack specific staining (HPA: adipocytes Not detected); no internal-negative liver cell type is identified, so assess other cells against the background seen in the controls (HPA: liver row identifies hepatocytes only).
Positive control tissue: Cerebellum (Purkinje cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for SIGMAR1; derive a cell-line control from the positive tissue's cell type (Purkinje cells) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only control; a concentration-matched rabbit IgG isotype control; and, if available, SIGMAR1 knockout tissue or a peptide-block control (selected-SKU caption: rabbit primary; standard IHC practice). Quench endogenous peroxidase in liver sections for HRP/DAB detection, and check endogenous biotin if using biotin-based detection (selected-SKU caption: HRP/DAB; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected-SKU rat-colon paraffin IHC caption does not state a fixative (selected-SKU tissue-IHC caption). Heat-mediated EDTA retrieval at pH 8.0 is reported for rat-colon paraffin IHC, but whether liver staining depends on that retrieval is unreported (selected-SKU tissue-IHC caption). The supplied evidence does not establish frozen sections or IF/ICC as easier; endogenous peroxidase can cause liver background with HRP/DAB (HPA subcellular: no ICC-IF image cell lines; standard IHC practice).

HPA tissue IHC evidence for SIGMAR1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells High Protein (IHC) HPA →
Liver Hepatocytes High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced SIGMAR1 IHC Tips

Use the catalog antibody’s paraffin-section evidence as a starting point, then interpret staining against SIGMAR1 topology and tissue patterns.

How should I troubleshoot weak SIGMAR1 staining after antigen retrieval?
Begin with heat-mediated retrieval in EDTA pH 8.0 for paraffin sections (datasheet A02493-2). This condition produced staining in rat colon with 2 μg/ml primary antibody, so hold antibody concentration constant when assessing retrieval (datasheet A02493-2). Compare matched sections processed together, including a no-primary control, and inspect both signal and tissue integrity (standard IHC practice). SIGMAR1 has a single transmembrane segment at residues 10–30 and a cytoplasmic region at 31–223, but the antibody’s epitope is unspecified (UniProt Q99720 topology; supplied product evidence). If signal remains weak, adjust retrieval intensity on matched sections before changing antibody concentration, and document each condition (standard IHC practice).
Could fixation explain inconsistent SIGMAR1 staining between paraffin blocks?
The rat colon caption identifies a paraffin-embedded section but does not state its fixative, so target-specific fixation sensitivity is unknown (caption A02493-2). Record the fixative, delay before fixation, fixation duration, processing history and section thickness for each block (standard IHC practice). Compare blocks using the same EDTA pH 8.0 retrieval and primary antibody conditions before attributing differences to fixation (datasheet A02493-2; standard IHC practice). Include a consistently stained reference section in each run to identify changes in staining performance (standard IHC practice). Neither the HPA tissue pattern nor SIGMAR1 topology establishes how this antibody responds to a particular fixative (HPA tissue IHC; UniProt Q99720 topology; supplied product evidence).
Where should convincing SIGMAR1 chromogenic staining appear?
Expect predominantly cytoplasmic staining across many tissues in IHC, while examining whether the signal follows cellular structures rather than section edges (HPA tissue IHC; standard IHC practice). During interphase, SIGMAR1 is reported at endoplasmic reticulum and inner and outer nuclear membranes; during mitosis, it can appear on cytoplasmic vesicles (UniProt Q99720 subcellular location). A rim around a nucleus is therefore more plausible than uniform staining throughout the nucleoplasm, although chromogenic resolution limits fine compartment assignments (UniProt Q99720 subcellular location; standard IHC practice). Compare the suspected cells with a no-primary control and adjacent morphology before assigning localisation (standard IHC practice). HPA reports high staining in Purkinje cells, hepatocytes and trophoblastic cells as useful tissue-pattern references (HPA tissue IHC).
Can this antibody distinguish SIGMAR1 isoforms or membrane-facing epitopes?
SIGMAR1 has 5 listed isoforms, but the supplied antibody evidence does not identify its epitope or establish which isoforms it detects (UniProt Q99720 isoforms; supplied product evidence). The annotated transmembrane segment spans residues 10–30, with residues 1–9 lumenal and 31–223 cytoplasmic (UniProt Q99720 topology). Consequently, apparent staining differences between blocks cannot identify a particular isoform or epitope without separate validation (UniProt Q99720 isoforms; standard IHC interpretation). Keep retrieval and detection conditions matched when comparing specimens, and report the antibody identity alongside any scored pattern (standard IHC practice). No glycosylation sites or modified residues are annotated here, so neither offers an established explanation for altered staining (UniProt Q99720 processing annotations).
How should I assess SIGMAR1 in a multiplex IF experiment?
Choose a marker for the expected cell type and check colocalisation within individual cells; HPA reports high SIGMAR1 staining in Purkinje cells, hepatocytes and trophoblastic cells (HPA tissue IHC; standard IF practice). Select fluorophores after inspecting unstained tissue autofluorescence, reserving a spectrally separated channel for a weak SIGMAR1 signal (standard IF practice). SIGMAR1 has lumenal residues 1–9 and a cytoplasmic region at 31–223, so test permeabilisation against the antibody’s mapped epitope once that information is available (UniProt Q99720 topology; standard IF practice). Include single-stain and no-primary controls to assess bleed-through and background (standard IF practice). The supplied product image establishes paraffin-section chromogenic staining; it provides no direct IF performance or fixation evidence (caption A02493-2).
What should I check when DAB obscures SIGMAR1 staining?
Start with a no-primary control to separate secondary-reagent or tissue background from staining associated with the primary antibody (standard IHC practice). The rat colon example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and peroxidase-based DAB detection (caption A02493-2). If background persists, compare matched sections after checking wash quality, primary concentration and development time while keeping retrieval fixed at EDTA pH 8.0 (datasheet A02493-2; standard IHC practice). Use a peroxidase block as a general chromogenic workflow step and assess endogenous enzyme staining with appropriate controls (standard IHC practice). Exclude folds, damaged edges and poorly preserved areas when judging the remaining cellular signal (standard IHC practice).
How should I score SIGMAR1 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because HPA describes mainly cytoplasmic tissue staining and UniProt also reports membrane-associated locations (HPA tissue IHC; UniProt Q99720 subcellular location). For comparable sections, use an H-score combining intensity and percentage of positive cells, or report positive-cell percentage with the total eligible cells as denominator (standard IHC practice). If counting discrete positive cells, report density per mm² of viable tissue and state how that area was measured (standard IHC practice). Apply identical retrieval, antibody and DAB development conditions to all comparison groups (standard IHC practice). Record excluded necrotic, folded or edge regions and score reference sections alongside study specimens (standard IHC practice).
How can I distinguish true SIGMAR1 staining from artefact?
Look for cellular staining consistent with the predominantly cytoplasmic HPA pattern and SIGMAR1’s endoplasmic reticulum or nuclear-envelope localisation (HPA tissue IHC; UniProt Q99720 subcellular location). HPA reports high staining in hepatocytes, Purkinje cells and trophoblastic cells, while adipocytes and hematopoietic cells were not detected in its sampled tissues (HPA tissue IHC). Treat these as reference patterns rather than absolute rules, because HPA rates staining versus RNA consistency as medium (HPA tissue IHC). Signal confined to section edges, necrotic areas or a no-primary control warrants investigation of processing, nonspecific deposition or endogenous enzyme activity (standard IHC practice). Confirm a disputed pattern with an independent antibody or orthogonal expression evidence before making a biological claim (standard IHC practice).
Boster reagents

Best SIGMAR1 / Sigma non-opioid intracellular receptor 1 IHC Antibodies

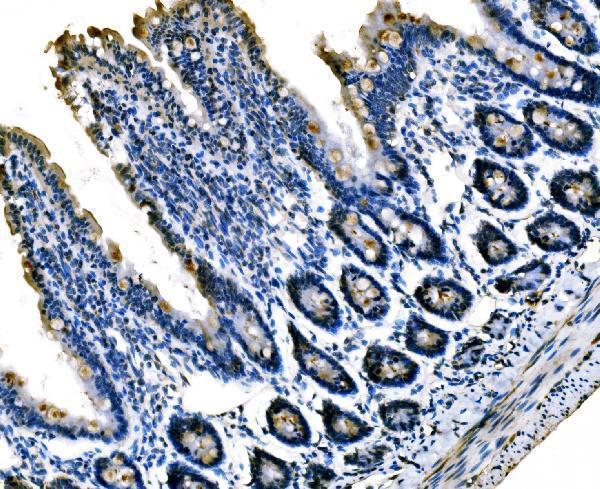
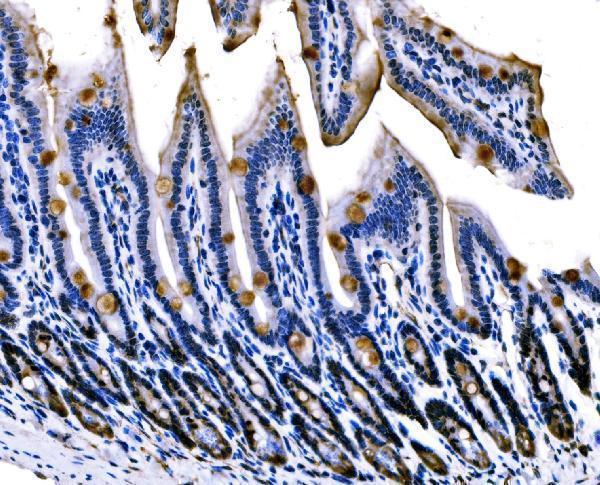
The IHC-validated anti-SIGMAR1 antibody has real paraffin-section data from rat and mouse colon, human colon adenocarcinoma, and human stomach cancer (catalog IHC image captions).

Real IHC data IHC analysis of Sigma1-Receptor/SIGMAR1 using anti-Sigma1-Receptor/SIGMAR1 antibody (A02493-2). Sigma1-Receptor/SIGMAR1 was detected in a paraffin-embedded section of rat colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Sigma1-Receptor/SIGMAR1 Antibody (A02493-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Sigma1-receptor/SIGMAR1 Antibody ®
Cat # A02493-2

A02493-2 has IHC images from rat and mouse colon, human colon adenocarcinoma, and human stomach cancer, all in paraffin sections (A02493-2 IHC image captions). Its listed reactivity includes Human, Monkey, Mouse, and Rat; the IHC images cover Human, Mouse, and Rat (catalog reactivity; A02493-2 IHC image captions).

Which to pick: Choose A02493-2 for paraffin-section tissue IHC; its rat and mouse colon captions report 2 μg/ml primary antibody and EDTA retrieval at pH 8.0, while the fixative is unreported (A02493-2 IHC image captions). For cross-species IHC, A02493-2 lists Human, Monkey, Mouse, and Rat reactivity, with IHC images for Human, Mouse, and Rat (catalog reactivity; A02493-2 IHC image captions). No SKU here is documented for IF/ICC: A02493-2 has no listed IF/ICC application, IF dilution, or IF image (catalog applications; IF dilution and image fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q99720 (SGMR1_HUMAN, Sigma non-opioid intracellular receptor 1).
  2. Human Protein Atlas. SIGMAR1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SIGMAR1 subcellular location (ICC-IF): Membrane.
  4. Human Protein Atlas. SIGMAR1 antibody validation summary (3 antibodies).
  5. SA4503 Mitigates Adriamycin-Induced Nephropathy via Sigma-1 Receptor in Animal and Cell-Based Models. Pharmaceuticals (Basel, Switzerland) 2025 — PMC11858467.
  6. Sigmar1 ablation leads to lung pathological changes associated with pulmonary fibrosis, inflammation, and altered surfactant proteins levels. Frontiers in physiology 2023 — PMC10083329.
  7. Deletion of Sigmar1 leads to increased arterial stiffness and altered mitochondrial respiration resulting in vascular dysfunction. Frontiers in physiology 2024 — PMC11089145.
  8. The Sigma-1 Receptor Exacerbates Cardiac Dysfunction Induced by Obstructive Nephropathy: A Role for Sexual Dimorphism. Biomedicines 2024 — PMC11351121.
  9. PubMed PMID:8954936 — UniProt-cited evidence.
  10. PubMed PMID:9341151 — UniProt-cited evidence.
  11. PubMed PMID:9453537 — UniProt-cited evidence.