This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic SIK1 IHC in paraffin sections using the catalog antibody validated for human IHC-P at 5 μg/mL (datasheet: A04399). Assess nuclear and cytoplasmic staining (HPA tissue IHC), and verify specificity because staining and RNA show low consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear and cytoplasmic staining (HPA tissue IHC) | |
| Staining pattern | Glandular cells show high nuclear and cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation conditions consistent across samples. (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show low consistency; verify specificity (HPA tissue IHC) | |
| Regulation | cAMP may shift SIK1 to the cytoplasm (UniProt) | |
| Isoform / epitope | No annotated isoforms; one 1–783 chain (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by published SIK1 chromogenic IHC protocols for kidney, liver, brain and lymphoma specimens (PMC7885408; PMC6590778; PMC10726907; PMC5746112).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A04399); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-SIK1, 5 μg/mL (datasheet A04399) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SIK1-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control. |
SIK1 can localize to the nucleus and cytoplasm (UniProt P57059). In tissue IHC, expect nuclear and cytoplasmic staining in the cell types reported by HPA, including adrenal glandular cells, bronchial respiratory epithelial cells and cerebral cortex glial cells (HPA: High). SIK1 has no transmembrane segment (UniProt P57059 topology). Treat this pattern as a guide: HPA rates the tissue IHC evidence Approved but reports low consistency with RNA expression and pending external verification (HPA: tissue IHC reliability).
| Clear nuclear staining, with or without cytoplasmic staining, in adrenal glandular cells or bronchial respiratory epithelial cells. | This fits SIK1's nuclear and cytoplasmic localization (UniProt P57059) and the reported High staining in those cell types (HPA: tissue IHC). Compare the signal with neighboring cells and the negative reagent control before scoring it as specific (general IHC practice). |
| Signal is restricted to cell borders or an extracellular deposit, with no convincing intracellular staining. | A border-only or extracellular pattern warrants investigation: SIK1 is reported in the nucleus and cytoplasm and has no transmembrane segment or signal peptide (UniProt P57059). Inspect morphology and control slides for an artefact; the supplied sources do not validate a surface or extracellular IHC pattern. |
| Strong staining appears chiefly in a cell population other than the one expected for the selected tissue. | Recheck cell identity before calling it SIK1. For example, the High bronchus entry refers to respiratory epithelial cells (HPA: tissue IHC). A discordant pattern may reflect antibody cross-reactivity or endogenous detection activity (general IHC practice); HPA lists low tissue specificity, so an unlisted cell type alone cannot establish a false positive (HPA: RNA specificity). |
| Brown chromogen is spread across the section without distinct cellular boundaries or interpretable nuclei. | Diffuse staining is difficult to score as SIK1 even where expression is reported. Check reagent and tissue controls for nonspecific binding or endogenous detection activity, then assess whether localization becomes interpretable (general chromogenic IHC practice). HPA's nuclear and cytoplasmic tissue profile does not validate uniform background (HPA: tissue IHC profile). |
| No signal is visible in an adrenal gland section's glandular cells under the selected staining conditions. | Those cells are a reasonable positive tissue check because HPA reports High staining there (HPA: adrenal gland IHC). Review section integrity, retrieval, antibody working conditions and detection controls (general IHC practice). An absent result does not by itself prove that the specimen lacks SIK1, particularly given HPA's reported RNA–staining inconsistency (HPA: tissue IHC reliability). |
| Compartment and signaling state | UniProt places SIK1 in the nucleus and cytoplasm and notes cytoplasmic localization when inactive after cAMP-induced phosphorylation, probably by PKA (UniProt P57059). Nuclear-only and mixed intracellular patterns therefore need context; a fixed tissue section cannot establish kinase activity from compartment alone. |
| Tissue evidence and antibody agreement | HPA lists High staining in several cell populations, but rates tissue IHC Approved with low consistency between antibody staining and RNA expression and pending external verification (HPA: tissue IHC). HPA lists IHC as Approved for HPA038211 and CAB023801; the supplied record does not give an IHC Enhanced designation (HPA: antibody validation). |
| Intracellular protein architecture | SIK1 has a kinase domain at residues 27–278, a UBA domain at 303–343, no transmembrane segment and no annotated signal peptide or propeptide (UniProt P57059). These facts support checking intracellular localization; they do not identify the catalog antibody's epitope or predict its staining intensity. |
| Phosphorylation | UniProt lists phosphorylation sites including Thr-473 and Ser-575 and describes phosphorylation-dependent interaction with 14-3-3 proteins (UniProt P57059). The supplied evidence does not show whether these modifications alter recognition by the IHC antibody; do not infer a staining change from phosphorylation alone. |
| Antigen retrieval and detection | Optimize retrieval and chromogenic detection against positive tissue and reagent controls (general IHC practice). No target-specific retrieval condition, fixation sensitivity or IHC dilution is supplied, so a particular treatment cannot be presented as established for SIK1. |
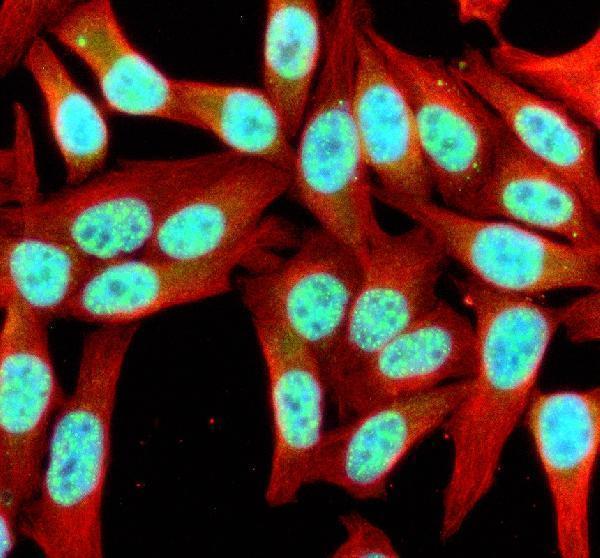
| IF/ICC: where should signal appear? | HPA reports mainly nucleoplasmic signal and additional vesicle localization in ICC-IF, with Approved location annotations (HPA: subcellular). This informs an IF localization check; it is separate from the tissue IHC pattern and supplies no IF protocol. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive tissue is blank. | The run may have lost detectable signal through a section, retrieval, primary antibody or detection problem (general IHC practice); one blank slide cannot establish absent SIK1. | Repeat with a documented positive tissue cell population, such as adrenal glandular cells (HPA: High), and check the section, retrieval and detection controls in sequence (general IHC practice). |
| Every area, including morphologically negative spaces, looks brown. | Broad background can arise from nonspecific binding, excess reagent or endogenous detection activity (general chromogenic IHC practice). | Examine a primary-antibody-omission control; then adjust blocking, reagent concentration or washing as indicated by the control result (general IHC practice). Score SIK1 only where cells and compartments remain discernible. |
| Signal is confined to membranes or extracellular material. | This distribution conflicts with the reported nuclear and cytoplasmic localization and lack of a transmembrane segment or signal peptide (UniProt P57059). | Verify that the signal tracks intact cells, inspect reagent controls and compare a reported positive tissue (general IHC practice; HPA: tissue IHC). Do not score a border-only deposit as a supported SIK1 pattern. |
| Unexpected cells stain more strongly than the HPA-listed cells. | Cell identification, cross-reactivity or endogenous chromogenic activity may explain the contrast (general IHC practice); HPA's low tissue specificity prevents treating every unlisted cell as negative (HPA: RNA specificity). | Reidentify the stained cells on the counterstained section and compare controls and an HPA-listed cell population before interpreting the contrast (general IHC practice; HPA: tissue IHC). |
| A run shows cytoplasmic signal but little nuclear signal. | Cytoplasmic localization is compatible with the UniProt record, including its note about inactive SIK1 after cAMP-induced phosphorylation (UniProt P57059); staining alone cannot identify that signaling state. | Check that cytoplasmic staining is cell-defined and control-dependent, then report the observed compartment without assigning kinase activity (general IHC practice; UniProt P57059 localization). |
| The tissue IHC pattern differs from an ICC-IF image. | HPA reports general nuclear and cytoplasmic tissue staining but mainly nucleoplasmic and additional vesicle localization in ICC-IF (HPA: tissue IHC; HPA: subcellular). The assays provide different observations. | Interpret each preparation against its own controls and reported compartment pattern (general IHC/IF practice). For this paraffin IHC section, prioritize cellular tissue morphology and the HPA tissue IHC evidence. |
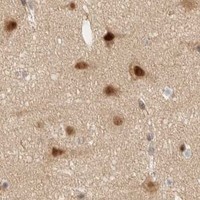


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: SIK1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot SIK1 staining in paraffin sections by checking retrieval, compartment, cell identity, and control tissue before comparing signal intensity (UniProt P57059; HPA tissue IHC).
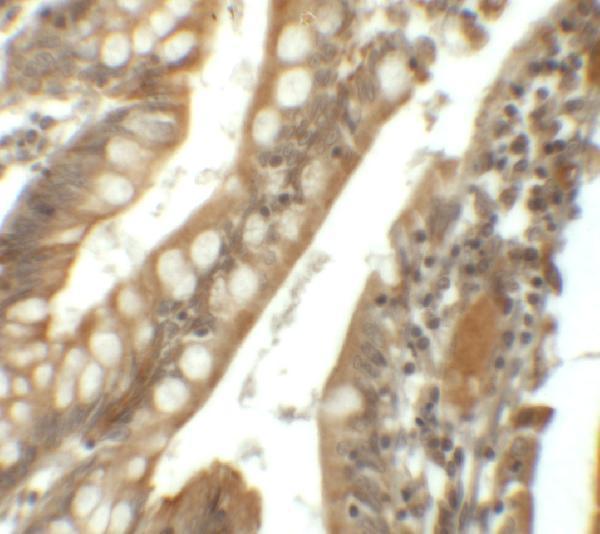
Anti-SIK1 antibodies have human small intestine IHC data (A04399 image caption) and human HeLa IF/ICC data (A04399-2 image caption); listed reactivity also includes mouse and rat (catalog: A04399-2 reactivity).
A04399 is listed for human IHC-P and shown staining human small intestine tissue at 5 μg/mL (catalog: A04399 applications/reactivity; A04399 IHC image caption). A04399-2 is listed for IF/ICC and shown in human HeLa cells at 5 μg/mL (catalog: A04399-2 applications; A04399-2 IF image caption).
Which to pick: Choose A04399 for human paraffin-section IHC (catalog: A04399 IHC-P application and human reactivity); its tissue caption does not report the fixative (A04399 IHC image caption). Choose A04399-2 for human IF/ICC (catalog: A04399-2 applications; A04399-2 IF image caption), or when mouse or rat reactivity is needed (catalog: A04399-2 reactivity); the supplied IF image documents human cells only (A04399-2 IF image caption). Neither catalog entry reports a clone (catalog: A04399 and A04399-2 clone fields).