This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic SIN3B IHC in paraffin sections using the catalog antibody’s 2–5 μg/ml range (datasheet A06424-2). Compare nuclear staining in smooth muscle and stomach glandular cells while accounting for uncertain staining reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in several tissues (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in smooth muscle and stomach glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A06424-2) | |
| Positive control | Smooth muscle+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target binding; reliability uncertain (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | 3 isoforms; no membrane sidedness; epitope coverage unknown (UniProt) |
The catalog antibody has an IHC-P protocol (datasheet A06424-2). The published mouse prostate protocol below provides a paraffin-section example (PMC5626631).
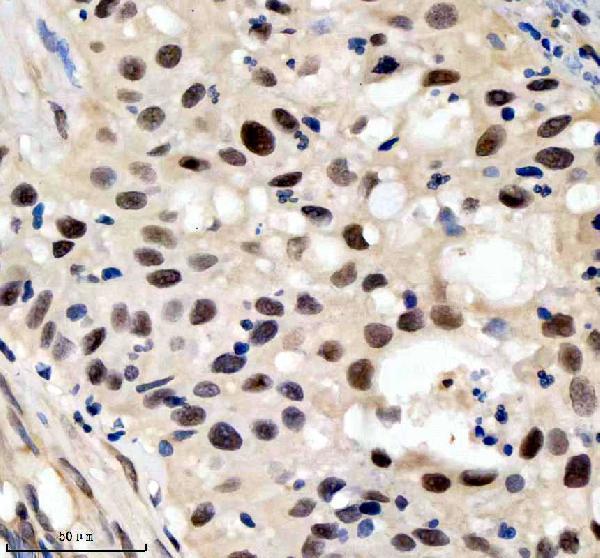
| Sample | Paraffin-embedded human bladder cancer tissue; fixative not specified (datasheet A06424-2) |
| Fixation | Image fixative and duration unreported (datasheet A06424-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A06424-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A06424-2) |
| Primary antibody | Rabbit anti-SIN3B, 2-5 μg/ml (datasheet A06424-2) |
| Primary incubation | Overnight at 4 °C (datasheet A06424-2) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A06424-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SIN3B-positive staining in smooth muscle cells of smooth muscle (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in several tissues. No signal in the no-primary control. |
SIN3B is a nuclear transcriptional corepressor with no transmembrane segment (UniProt O75182: nucleus, function, topology). For IHC, look for nuclear staining in smooth muscle cells and stomach glandular cells, which HPA reports as high; several other cell types show medium staining (HPA: tissue IHC). Treat this as a provisional pattern: HPA rates tissue IHC reliability uncertain, citing low agreement with RNA data and presumed off-target binding (HPA: tissue IHC).
| Nuclear chromogen in smooth muscle cells or stomach glandular cells, with identifiable unstained surrounding structures. | This fits the reported high-staining cell types and expected nuclear location (HPA: high in smooth muscle cells and stomach glandular cells; UniProt O75182: nucleus). Score the named cells and their nuclei, not the whole tissue uniformly. The fit supports interpretation but does not resolve HPA’s uncertain tissue IHC reliability (HPA: tissue IHC). |
| Signal is mainly diffuse cytoplasmic, while nuclei are faint or clear. | That distribution conflicts with UniProt’s nuclear assignment and HPA’s nuclear tissue profile (UniProt O75182: nucleus; HPA: tissue IHC). Inspect the no-primary and detection controls, then reassess background and staining conditions (standard IHC practice). Do not classify cytoplasmic color alone as SIN3B-positive. |
| Strong staining appears in a cell population HPA lists as not detected, such as adipocytes. | HPA reports SIN3B as not detected in adipocytes, so strong staining there is a specificity warning, not proof that SIN3B is absent from every adipose tissue cell (HPA: adipocytes not detected; tissue IHC uncertain). Cross-reactivity or endogenous detection activity are possible explanations; compare controls before assigning either cause (standard IHC practice). |
| Broad, low-contrast color covers nuclei, cytoplasm, and tissue spaces. | This is difficult to score as cell-specific nuclear staining against HPA’s tissue profile (HPA: nuclear expression in several tissues). Check the no-primary control, wash steps, blocking, and chromogen development for general background (standard IHC practice). Background alone cannot establish a SIN3B distribution. |
| No nuclear signal is visible in smooth muscle cells or stomach glandular cells. | Those are HPA’s high-staining examples, so an absent signal calls for a run-level check (HPA: high in smooth muscle cells and stomach glandular cells). Review tissue integrity, retrieval, antibody and detection steps, and counterstain visibility (standard IHC practice). HPA’s uncertain IHC rating limits how strongly one negative section can be interpreted (HPA: tissue IHC). |
| Compartment and assay | UniProt places SIN3B in the nucleus, and HPA describes nuclear tissue IHC (UniProt O75182: nucleus; HPA: tissue IHC). HPA’s ICC-IF record also approves a plasma membrane location; that separate imaging result should not be imposed as the expected chromogenic IHC pattern (HPA: subcellular ICC-IF). |
| Cell type selection | HPA reports high staining in smooth muscle cells and stomach glandular cells, medium staining in several neuronal and epithelial populations, and no detection in specified other cell types (HPA: tissue IHC). Interpret each listed level for its named cell population, with the HPA reliability caveat. |
| Antibody evidence | The HPA050329 antibody is rated uncertain for IHC and approved for ICC-IF; HPA also flags presumed off-target tissue staining (HPA: antibody validation; tissue IHC). An ICC-IF approval does not independently validate every IHC-positive cell population. |
| Isoforms and target-specific conditions | UniProt lists three SIN3B isoforms, but the supplied sources give no antibody epitope or isoform-specific IHC pattern (UniProt O75182: isoforms; HPA: antibody validation). Target-specific fixation sensitivity is unreported here; retrieval conditions must be evaluated as general IHC workflow conditions, not as a proven SIN3B effect. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected high-staining cells show no nuclear chromogen. | A failed staining run is possible, but a single negative result does not identify the failed step (HPA: high in smooth muscle cells and stomach glandular cells; tissue IHC uncertain). | Confirm the named cells are present, then review the IHC-validated antibody, retrieval, detection reagents, and a run control together (standard IHC practice). Record the actual tissue and cell type before interpreting absence. |
| Nuclear staining appears, but no-primary sections also develop color. | Signal can arise from the detection system or endogenous tissue activity rather than primary-antibody binding (standard chromogenic IHC practice). | Use the no-primary result to assess detection background; check appropriate blocking and detection controls, then repeat scoring only where control background is acceptably low (standard IHC practice). |
| Strong signal occurs in an HPA-listed undetected cell type. | The discrepancy raises concern about specificity, especially given HPA’s uncertain tissue IHC rating and presumed off-target binding (HPA: tissue IHC). It does not by itself identify the molecular cause. | Verify cell identity and nuclear localization, compare no-primary staining, and seek an independent specificity check before calling that population SIN3B-positive (standard IHC practice; HPA: tissue IHC uncertain). |
| Most of the section has diffuse color that obscures nuclei. | General background can prevent reliable nuclear scoring; it is not a documented SIN3B-specific fixation effect (standard IHC practice; HPA: nuclear tissue profile). | Check blocking, washes, chromogen development, and control sections; assess whether counterstained nuclei remain distinguishable before scoring (standard IHC practice). |
| Signal is predominantly cytoplasmic or membranous in IHC. | That pattern does not match HPA’s nuclear tissue IHC summary or UniProt’s nuclear assignment (HPA: tissue IHC; UniProt O75182: nucleus). HPA’s approved additional plasma membrane location comes from ICC-IF (HPA: subcellular ICC-IF). | Document the compartment and compare staining controls; avoid treating the ICC-IF membrane observation as validation of a membranous chromogenic IHC result (HPA: subcellular ICC-IF; standard IHC practice). |
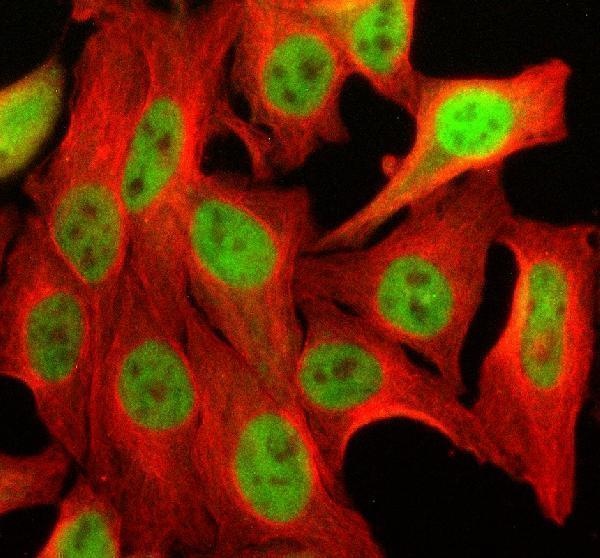
| What should an IF/ICC image show? | IF/ICC has separate localization evidence and is a different assay from paraffin-section IHC (HPA: subcellular ICC-IF; tissue IHC). | Look primarily for nucleoplasmic signal; HPA also approves an additional plasma membrane location in ICC-IF images from HEK293, U-251MG, and U2OS (HPA: subcellular ICC-IF). Interpret that image evidence within an IF/ICC guide. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Smooth muscle | Smooth muscle cells | High | Protein (IHC) | HPA → |
| Stomach | Glandular cells | High | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebellum | Purkinje cells | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Liver | Cholangiocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot SIN3B staining by checking retrieval, nuclear localisation, controls and scoring against the available tissue evidence.
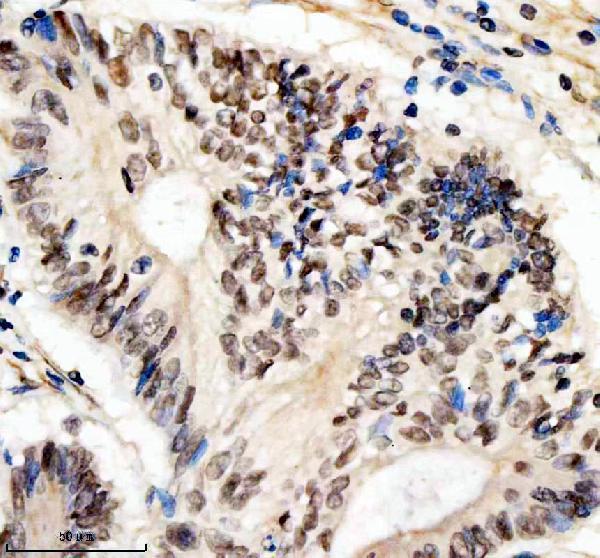
A06424-2 has IHC images from paraffin-embedded human bladder cancer, colon cancer and rat testis, plus IF images from HeLa cells and human and rat tissue sections (catalog image captions).
A06424-2 is listed for IHC, IF and ICC, with human, mouse and rat reactivity (catalog applications and reactivity). Its IHC captions show human bladder cancer, human colon cancer and rat testis paraffin sections; its IF captions show HeLa cells and human bladder cancer and rat testis sections (A06424-2 image captions).
Which to pick: For tissue IHC, choose A06424-2: its paraffin-section captions use EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A06424-2 IHC image captions). For IF/ICC, A06424-2 is listed for both applications and has IF images from cells and paraffin sections (catalog applications; A06424-2 IF image captions). For cross-species work, A06424-2 lists human, mouse and rat reactivity, with IHC images from human and rat samples; mouse IHC imaging and clonality are unreported (catalog reactivity and clone field; A06424-2 IHC image captions).