SLC25A13 / Electrogenic aspartate/glutamate antiporter SLC25A13, mitochondrial · IHC design guide

Design Immunohistochemistry for SLC25A13

Plan paraffin-section SLC25A13 IHC around granular cytoplasmic staining, with hepatocytes as a high-staining reference (HPA tissue IHC). The catalog antibody has a recommended IHC concentration of 2–5 μg/ml (datasheet A03476-2).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SLC25A13 (IHC for SLC25A13): expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A03476-2, validated IHC image, and IHC protocol steps
Printable SLC25A13 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt), antibody A03476-2, controls and protocol steps. Open the full SLC25A13 IHC guide →

SLC25A13 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); inner mitochondrial membrane (UniProt)
Staining pattern Granular cytoplasm; high in hepatocytes (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03476-2)
Positive control ⓘ Caudate+4 more · see all
Negative control ⓘ Soft tissue
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A03476-2)
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Higher expression in liver (UniProt)
Isoform / epitope 2 isoforms; check epitope coverage (UniProt)
Section 1

Recommended SLC25A13 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet: A03476-2) is accompanied by three published SLC25A13 IHC examples (PMC11874833; PMC5141444; PMC13336081).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human appendix adenocarcinoma tissue; fixative not specified (datasheet A03476-2)
FixationImage fixative and duration unreported (datasheet A03476-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03476-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03476-2)
Primary antibodyRabbit anti-SLC25A13, 2-5 μg/ml (datasheet A03476-2)
Primary incubationOvernight at 4 °C (datasheet A03476-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03476-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSLC25A13-positive staining in neuronal cells of caudate (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A03476-2).
Section 2

What Is the Expected SLC25A13 Staining Pattern?

SLC25A13 is an inner mitochondrial membrane protein with six transmembrane segments (UniProt Q9UJS0 topology). On paraffin sections, expect granular cytoplasmic staining, especially in hepatocytes; HPA also reports high staining in several other cell types (HPA: tissue IHC). HPA rates its IHC evidence Enhanced, while describing only medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Granular cytoplasmic staining in hepatocytes.This fits HPA’s reported pattern in liver hepatocytes and the mitochondrial location of SLC25A13 (HPA: tissue IHC; UniProt Q9UJS0 subcellular location). Judge staining within hepatocytes rather than expecting every cell in the section to look alike.
Predominantly nuclear staining, or a crisp cell-surface outline instead of cytoplasmic granules.These compartments do not match the reported mitochondrial location (UniProt Q9UJS0; HPA: subcellular). Treat the pattern as suspect, then inspect controls and staining conditions before assigning it to SLC25A13.
Strong staining in soft-tissue fibroblasts.HPA reports SLC25A13 as not detected in these cells (HPA: soft tissue fibroblasts). Consider antibody cross-reactivity or, with chromogenic detection, residual endogenous enzyme activity; compare a no-primary control (general IHC practice).
Uniform color across cells and tissue spaces, obscuring granules.This prevents a confident call on the reported granular cytoplasmic pattern (HPA: tissue IHC). Check the no-primary control, reagent background and wash steps; broad color alone is insufficient evidence of target staining (general IHC practice).
No staining in hepatocytes of an otherwise interpretable liver section.Liver hepatocytes are a strong expected comparator: HPA reports High IHC staining there, and UniProt reports high liver expression (HPA: liver hepatocytes; UniProt Q9UJS0 tissue specificity). Review run controls before calling the sample negative.
💡Expected SLC25A13 appearanceCall a result positive when hepatocytes show high, granular cytoplasmic staining consistent with mitochondria; dominant nuclear or cell-surface color is suspect (HPA: liver hepatocytes and tissue IHC profile; UniProt Q9UJS0 location).
How each factor affects the staining
Cell type and tissueHPA reports High staining in hepatocytes, kidney tubular cells, selected glandular cells and neuronal cells, but not in soft-tissue fibroblasts (HPA: tissue IHC). Compare like cell types; the liver-enriched RNA designation does not mean liver is the only stained tissue (HPA: RNA specificity and tissue IHC).
Topology and epitopeSLC25A13 spans the inner mitochondrial membrane six times and has regions facing the intermembrane space or matrix (UniProt Q9UJS0 topology). The supplied record does not map the IHC antibody’s epitope, so topology cannot identify a preferred antigen retrieval condition or predict its staining strength.
Isoforms and processingUniProt lists two isoforms and a chain covering residues 2–675, with no signal peptide or propeptide (UniProt Q9UJS0 isoforms and processing). Without a mapped antibody epitope, these entries do not establish which isoform the stain detects; they provide no basis to expect a shed extracellular pattern.
IHC evidenceHPA lists antibody HPA018997 as IHC Enhanced and describes overall tissue evidence as having medium consistency with RNA expression (HPA: antibody validation and reliability). Use the observed cell and compartment pattern as a guide, while keeping that consistency limit in mind.
IF/ICC Q: What pattern should I expect?A: HPA reports supported mitochondrial localization in ICC-IF (HPA: subcellular). That supports a mitochondrial pattern in the separate IF/ICC guide; it does not supply an IF/ICC protocol or turn the paraffin-section IHC observations into an IF/ICC result.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Liver hepatocytes show no visible signal.A known high-staining cell type is negative (HPA: liver hepatocytes); the cause cannot be assigned from this slide alone.Confirm tissue identity and inspect a run control, then review retrieval, primary incubation and detection steps as general IHC checks. The supplied sources give no SLC25A13-specific fixation or retrieval sensitivity.
Nuclear staining dominates the section.Nuclear localization conflicts with the reported mitochondrial location (UniProt Q9UJS0; HPA: subcellular).Compare the no-primary control and check whether hepatocyte cytoplasmic granules remain discernible (general IHC practice; HPA: liver hepatocytes and tissue IHC profile). Avoid scoring the nuclear signal as SLC25A13 without further validation.
Soft-tissue fibroblasts stain strongly.That result conflicts with HPA’s not detected fibroblast observation; cross-reactivity or chromogenic background are possible explanations (HPA: soft tissue fibroblasts; general IHC practice).Check the no-primary control and detection background, and compare the fibroblast signal with the expected granular hepatocyte pattern (general IHC practice; HPA: liver hepatocytes).
Color is diffuse and masks cell boundaries.Diffuse background can prevent assessment of HPA’s granular cytoplasmic pattern (HPA: tissue IHC); its source is undetermined.Inspect the no-primary control, washes and blocking steps using general IHC practice. Reassess only where individual cells and cytoplasmic granules can be distinguished.
Kidney tubules or neuronal cells stain strongly despite liver-enriched RNA.This can agree with the IHC observations: HPA reports High staining in kidney tubular and selected neuronal cells (HPA: tissue IHC and RNA specificity).Score the identified cell type and granular cytoplasmic pattern. Do not treat the liver-enriched RNA label alone as a reason to reject these IHC signals (HPA: tissue IHC and RNA specificity).
Macrophages in lung show weak color.HPA reports Low staining in lung macrophages, so weak color is less decisive than a high-staining hepatocyte comparator (HPA: tissue IHC). Chromogenic background also remains possible (general IHC practice).Compare the no-primary control and a hepatocyte-positive section, then judge whether discrete cytoplasmic granules are visible (general IHC practice; HPA: liver hepatocytes and tissue IHC profile).

Sample controls for SLC25A13 IHC & IF

🧪Run colon first: glandular cells should stain (HPA: High in colon glandular cells). Use soft-tissue fibroblasts as the negative tissue (HPA: Not detected in soft-tissue fibroblasts); compare nonglandular cells on the colon slide for weaker or background staining, without treating them as a confirmed negative population.
Positive control tissue: Caudate (Neuronal cells, HPA High)
Negative control tissue: Soft tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SLC25A13 in A-431, U-251MG, U2OS, NIH 3T3, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a host-species-, isotype-, and clonality-matched rabbit control, and a biological negative such as a validated SLC25A13 knockout or peptide-blocked sample if the immunizing peptide is available (IHC caption: rabbit primary and HRP detection). Block endogenous peroxidase and check for nonspecific DAB signal in colon sections (IHC caption: HRP/DAB detection).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A03476-2 tissue-IHC caption does not state a fixative. The demonstrated paraffin-section procedure used heat-mediated EDTA retrieval at pH 8.0; its result does not establish that retrieval is required under other conditions (IHC caption: EDTA retrieval, pH 8.0). Whether frozen sections or IF are easier is unreported; mitochondrial staining is a useful IF localization check (HPA subcellular: mitochondria supported; UniProt Q9UJS0: mitochondrial inner membrane), while endogenous peroxidase can complicate interpretation of colon HRP/DAB staining (IHC caption: HRP/DAB detection).

HPA tissue IHC evidence for SLC25A13

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Caudate Neuronal cells High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Hippocampus Neuronal cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced SLC25A13 IHC Tips

Troubleshoot chromogenic IHC for SLC25A13 by checking retrieval, tissue handling, mitochondrial staining patterns and cell-specific controls.

What retrieval should I try first for SLC25A13 paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 (datasheet A03476-2). The selected paraffin-section example used this retrieval before overnight primary-antibody incubation at 4°C (datasheet A03476-2). If staining is weak, compare heating duration on adjacent sections while keeping the buffer, antibody concentration and detection method constant (standard IHC practice). Examine tissue integrity alongside signal: excess heating can damage section morphology and make granular staining difficult to score (standard IHC practice). Record the retrieval time and cooling conditions for every comparison, because consistent processing is needed to interpret changes in staining (standard IHC practice).
How should I troubleshoot variable staining between differently fixed specimens?
Target-specific fixation sensitivity for SLC25A13 is unknown from the supplied evidence; the selected paraffin-section caption does not state a fixative (datasheet A03476-2). Record fixative, fixation duration and specimen thickness for each block before comparing staining (standard IHC practice). For new specimens, use a consistent fixation workflow, such as 10% neutral-buffered formalin, and assess any proposed duration against morphology and staining in matched material (standard IHC practice). Compare sections in the same IHC run using the documented EDTA pH 8.0 retrieval (datasheet A03476-2). Avoid attributing a difference to fixation until section quality, retrieval and detection controls have also been reviewed (standard IHC practice).
Which staining pattern fits SLC25A13, and what pattern needs investigation?
Look for granular cytoplasmic staining in appropriately positive cells (HPA: granular cytoplasmic expression in most tissues). SLC25A13 resides in the mitochondrial inner membrane (UniProt Q9UJS0 subcellular location), and HPA independently supports mitochondrial localisation (HPA subcellular: mitochondria). The carrier has 6 transmembrane segments, so diffuse nuclear staining alone is difficult to reconcile with its annotated location (UniProt Q9UJS0 topology; standard IHC interpretation). Check a positive tissue compartment and an antibody-omission control on the same run before judging faint granules (standard IHC practice). Compare the pattern at equivalent section thickness and chromogen development time, since these affect how clearly granules can be resolved (standard IHC practice).
How can epitope location change SLC25A13 staining?
SLC25A13 has 2 annotated isoforms, but the supplied antibody evidence does not identify the epitope or establish isoform-specific staining (UniProt Q9UJS0 isoforms; datasheet A03476-2). Its N-terminal region includes 4 EF-hand domains, while the membrane-spanning region contains 6 transmembrane segments (UniProt Q9UJS0 domains and topology). Ask for the antibody's immunogen or epitope documentation before interpreting a negative compartment as absence of both isoforms (standard IHC interpretation). If results disagree across antibodies, compare their documented epitopes and stain adjacent sections under matched retrieval and detection conditions (standard IHC practice). Treat differences as antibody-dependent until specificity controls support a biological explanation (standard IHC interpretation).
How can IF help assess a questionable IHC staining pattern?
Use IF as a separate follow-up assay and multiplex SLC25A13 with a marker of the cell type being assessed (standard IF practice). For example, hepatocytes show high HPA tissue-IHC staining, while HPA supports mitochondrial localisation for SLC25A13 (HPA tissue: high in hepatocytes; HPA subcellular: mitochondria). Choose fluorophores and acquisition channels after checking tissue autofluorescence with an unstained section, and include single-label controls when using 2 or more channels (standard IF practice). Because the carrier crosses the inner mitochondrial membrane 6 times, select and test permeabilisation against the antibody's documented epitope and its membrane-facing side (UniProt Q9UJS0 topology; standard IF practice). Do not transfer fixation or permeabilisation settings from the paraffin IHC caption, which reports neither an IF workflow nor a fixative (datasheet A03476-2).
What should I check when brown signal obscures mitochondrial granules?
Inspect an antibody-omission control and the unstained tissue appearance before adjusting the primary antibody (standard IHC practice). The selected example used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, a peroxidase-linked secondary and DAB detection (datasheet A03476-2). Use a peroxidase block and appropriate washing as general chromogenic IHC steps; neither step establishes SLC25A13 specificity (standard IHC practice). If background persists, compare a primary-antibody titration and shorter chromogen development on adjacent sections while keeping retrieval constant (standard IHC practice). Check whether staining follows tissue edges, damaged areas or endogenous enzyme activity rather than the expected granular cytoplasmic pattern (HPA: granular cytoplasmic expression; standard IHC interpretation).
How should I score SLC25A13 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell compartment and staining threshold before scoring, using the granular cytoplasmic pattern as the expected signal (HPA: granular cytoplasmic expression in most tissues; standard IHC practice). An H-score combines the percentages of cells at intensity levels 0–3; report the percentage of positive cells separately when it answers the study question (standard IHC scoring practice). For counts, report positive cells per mm² of analysable tissue or within a predefined cell population (standard IHC scoring practice). Normalise comparisons to viable tissue area or the number of relevant cells, and apply identical imaging and threshold settings across sections (standard IHC practice). Keep tissue type and cell type explicit, because HPA reports different staining levels across compartments (HPA tissue IHC).
How do I distinguish true SLC25A13 staining from artefact?
A plausible positive shows granular cytoplasmic signal in an expected cell population and agrees with mitochondrial localisation (HPA tissue IHC; HPA subcellular: mitochondria). HPA reports high staining in liver hepatocytes and no detection in soft-tissue fibroblasts, offering contrasting cell contexts for interpretation (HPA tissue IHC). Investigate predominantly nuclear staining, edge-restricted signal and staining concentrated in necrotic regions with controls before calling a specimen positive (UniProt Q9UJS0 subcellular location; standard IHC interpretation). Check an antibody-omission section for endogenous peroxidase or chromogen-related signal, and compare intact tissue at the same development time (standard IHC practice). Interpret a negative result cautiously when the positive control also fails under EDTA pH 8.0 retrieval (datasheet A03476-2; standard IHC practice).
Boster reagents

Best SLC25A13 / Electrogenic aspartate/glutamate antiporter SLC25A13, mitochondrial IHC Antibodies

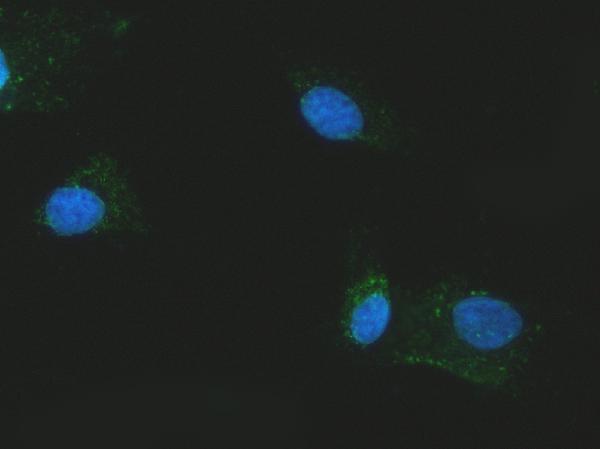
The catalog antibody has IHC data from human paraffin sections and IF data from human paraffin sections and A549 cells (catalog image captions); its listed reactivity is human and rat (catalog reactivity).

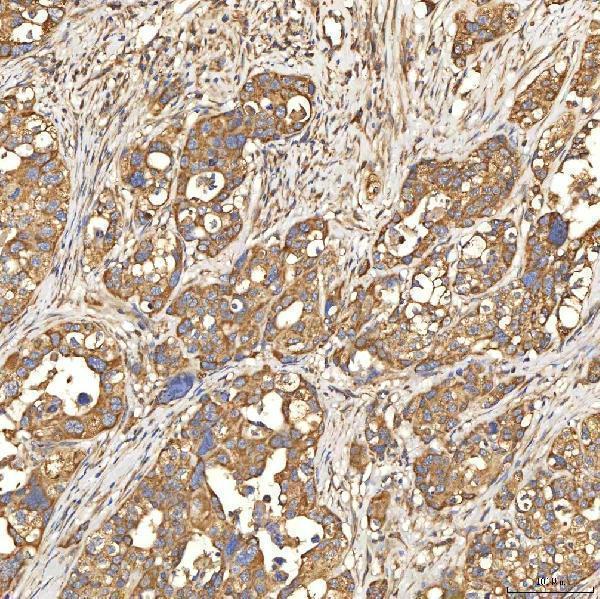
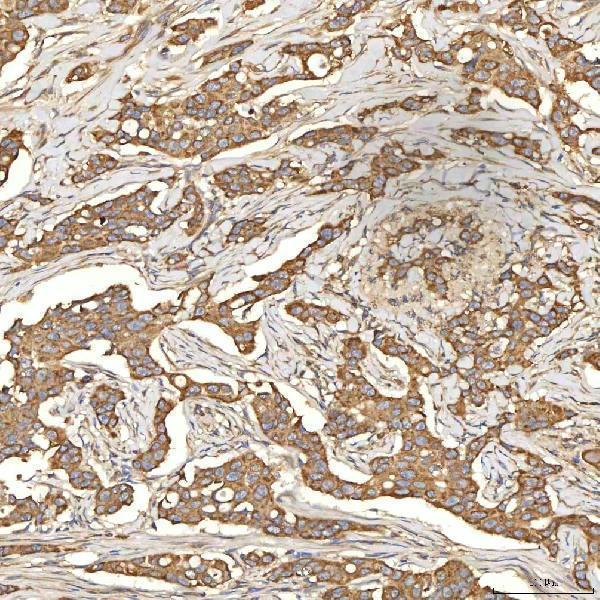
Real IHC data IHC analysis of Citrin/SLC25A13 using anti-Citrin/SLC25A13 antibody (A03476-2). Citrin/SLC25A13 was detected in a paraffin-embedded section of human appendix adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Citrin/SLC25A13 Antibody (A03476-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Citrin/SLC25A13 Antibody ®
Cat # A03476-2

A03476-2 will render with an IHC figure from a human appendix adenocarcinoma paraffin section (A03476-2 IHC image caption). Its catalog also documents IHC in human breast cancer, colon adenocarcinoma, and diffuse large B cell lymphoma paraffin sections, plus IF in A549 cells and human liver and colon cancer paraffin sections (A03476-2 image captions).

Which to pick: Choose A03476-2 for tissue IHC on paraffin sections: its IHC figure used EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody; the fixative is unreported (A03476-2 IHC image caption). The same SKU supports IF/ICC at 5 μg/ml, with IF images from A549 cells and human paraffin sections (A03476-2 applications, IF dilution, IF image captions). For cross-species planning, its listed reactivity includes human and rat, but the supplied IHC and IF images show human samples only; the host is rabbit and clonality is unreported (A03476-2 catalog reactivity, image captions, host and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9UJS0 (S2513_HUMAN, Electrogenic aspartate/glutamate antiporter SLC25A13, mitochondrial).
  2. Human Protein Atlas. SLC25A13 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SLC25A13 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. SLC25A13 antibody validation summary (1 antibodies).
  5. Medium-chain triglyceride supplementation under a low-carbohydrate formula is a promising therapy for adult-onset type II citrullinemia. Molecular genetics and metabolism reports 2014 — PMC5121258.
  6. Unveiling the oncogenic role of SLC25A13: a multi-omics pan-cancer analysis reveals its impact on glioma progression. Cancer cell international 2025 — PMC11874833.
  7. Metabolic Adaptation to Nutritional Stress in Human Colorectal Cancer. Scientific reports 2016 — PMC5141444.
  8. Mitochondrial Carrier SLC25A13 Drives Ferroptosis Resistance and Immune Evasion via a STAT3-IFI6 Circuit in Breast Cancer. Advanced science (Weinheim, Baden-Wurttemberg, Germany) 2026 — PMC13336081.
  9. PubMed PMID:10369257 — UniProt-cited evidence.
  10. PubMed PMID:10642534 — UniProt-cited evidence.
  11. PubMed PMID:11566871 — UniProt-cited evidence.