SLC25A24 / Mitochondrial adenyl nucleotide antiporter SLC25A24 · IHC design guide

Design Immunohistochemistry for SLC25A24

Plan SLC25A24 chromogenic IHC in paraffin sections using the IHC-validated antibody at 2–5 μg/ml (datasheet A08355-1). Assess granular cytoplasmic staining in glandular cells in light of SLC25A24’s inner mitochondrial membrane location (HPA tissue IHC; UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SLC25A24 (IHC for SLC25A24): expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A08355-1, validated IHC image, and IHC protocol steps
Printable SLC25A24 IHC protocol sheet — expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt), antibody A08355-1, controls and protocol steps. Open the full SLC25A24 IHC guide →

SLC25A24 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm (HPA tissue IHC); mitochondrial inner membrane (UniProt)
Staining pattern Granular cytoplasmic staining in glandular cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A08355-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Cardiomyocytes may lack signal despite positive glands (HPA tissue IHC)
Regulation Expression varies by tissue (UniProt)
Isoform / epitope 2 isoforms; map the epitope before interpreting loss (UniProt)
Section 1

Recommended SLC25A24 IHC & IF Protocols

The catalog antibody’s IHC protocol is followed by a published protocol using human colorectal cancer sections (PMC8892738).

Recommended immunohistochemistry (IHC-P) protocol parameters
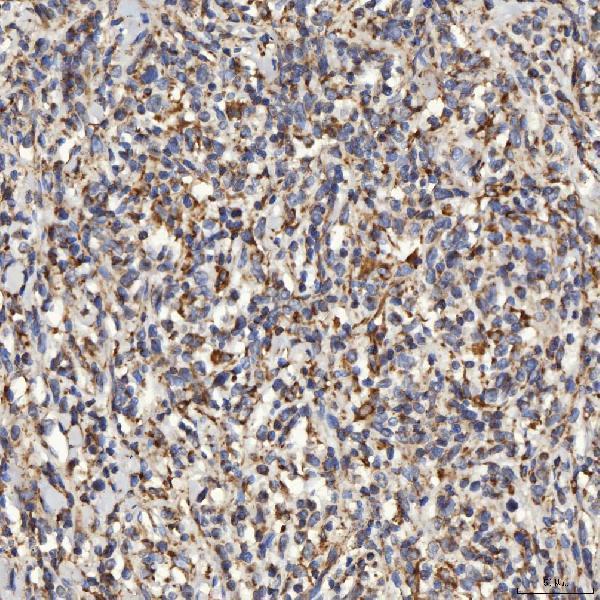
SampleParaffin-embedded human diffuse large B cell lymphoma tissue; fixative not specified (datasheet A08355-1)
FixationImage fixative and duration unreported (datasheet A08355-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A08355-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A08355-1)
Primary antibodyRabbit anti-SLC25A24, 2-5 μg/ml (datasheet A08355-1)
Primary incubationOvernight at 4 °C (datasheet A08355-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A08355-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSLC25A24-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression with a granular mitochondrial pattern. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 (datasheet A08355-1); the published excerpt does not specify retrieval conditions (PMC8892738).
Section 2

What Is the Expected SLC25A24 Staining Pattern?

SLC25A24 resides in the mitochondrial inner membrane and has 6 transmembrane segments (UniProt Q6NUK1 topology). In paraffin sections, expect granular cytoplasmic staining, particularly in glandular and respiratory epithelial cells reported as High by HPA (HPA: tissue IHC). HPA describes the tissue pattern as Enhanced, citing high consistency between antibody staining and RNA expression data (HPA: tissue IHC). Judge the pattern by both cell type and compartment.

What am I looking at on my slide?
Granular cytoplasmic staining in adrenal or colonic glandular cells, with recognizable cell boundaries.This fits the reported mitochondrial pattern and High staining in those cells (HPA: tissue IHC). Score the cells and staining intensity separately; brown granules within cytoplasm support a positive IHC result, while an isolated dark spot without a clear cellular location is harder to interpret.
Predominantly nuclear staining or a continuous outline of the cell surface.Neither distribution matches the mitochondrial inner membrane location (UniProt Q6NUK1 topology) or HPA's granular cytoplasmic pattern (HPA: tissue IHC). Treat it as a possible staining artefact and review the primary antibody control, detection chemistry and counterstain before assigning a positive score.
Strong staining confined to adipocytes or cardiomyocytes, while expected glandular cells are unstained.HPA reports SLC25A24 as Not detected in adipocytes and cardiomyocytes, but High in several glandular cell populations (HPA: tissue IHC). This mismatch raises concern for cross-reactivity or endogenous detection activity. Verify the cell identity and compare a matched section processed without primary antibody.
A uniform haze covers cells, connective tissue and spaces between cells.Broad haze does not resemble the reported granular cytoplasmic pattern (HPA: tissue IHC). It can obscure whether any cell is genuinely positive. Inspect the section processed without primary antibody, then review blocking, washing and chromogen development as general IHC workflow checks.
No staining in glandular cells of an adrenal gland or colon control section.Those cells are reported High by HPA (HPA: tissue IHC), so an absent signal calls for an assay check before interpreting the test section as negative. Confirm the control's cell type, then review the IHC-validated antibody's instructions, retrieval conditions and detection reagents.
💡Expected SLC25A24 appearanceCall a section positive when glandular or respiratory epithelial cells show High, granular cytoplasmic staining consistent with mitochondria (HPA: tissue IHC); dominant nuclear staining, surface outlines or uniform haze are suspect patterns relative to the reported location (UniProt Q6NUK1 topology; HPA: tissue IHC).
How each factor affects the staining
Membrane topology and epitope interpretationSLC25A24 spans the mitochondrial inner membrane 6 times, with regions annotated on the intermembrane and matrix sides (UniProt Q6NUK1 topology). Its location supports a mitochondrial interpretation of cytoplasmic granules. The supplied record does not identify the catalog antibody's epitope, so topology alone cannot specify an antigen retrieval condition.
Choice of tissue controlHPA reports High staining in adrenal, appendix, breast, colon, duodenal, endometrial and epididymal glandular cells, and bronchial respiratory epithelial cells (HPA: tissue IHC). These are candidates for a positive control. HPA reports Not detected in adipocytes and several muscle cell populations (HPA: tissue IHC); evaluate the named cell population, not the tissue label alone.
Antibody evidenceHPA lists IHC as Enhanced for HPA063636, while the supplied IHC field for HPA028519 is empty (HPA: antibodies). HPA's tissue reliability description cites consistency with RNA expression (HPA: tissue IHC). These summaries support pattern interpretation; they do not provide a dilution, retrieval setting or fixation sensitivity.
Isoforms and tissue expressionUniProt lists 2 isoforms and expression in all tissues tested, with relatively weak expression in heart and skeletal muscle (UniProt Q6NUK1). HPA reports Not detected IHC staining in cardiomyocytes and myocytes (HPA: tissue IHC). A weak expression annotation does not require a visible chromogenic signal in those cells; the supplied evidence gives no isoform-specific staining pattern.
IF/ICC question: where should fluorescence appear?Expect mitochondrial fluorescence: HPA assigns an enhanced mitochondrial location and lists ICC/IF images from A-431, U-251MG, U2OS and Rh30 (HPA: subcellular). HPA marks ICC as Supported for both listed antibodies (HPA: antibodies). This provides a compartment cross-check; IF/ICC preparation and settings belong in its separate guide.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The glandular positive control is blank.The result conflicts with High staining reported for several glandular cell types (HPA: tissue IHC); a missed staining step or unsuitable assay condition is possible.Confirm the selected cells on the section. Check the catalog antibody's IHC-P instructions and the run's retrieval, primary incubation and detection steps before scoring other slides.
Brown signal spreads evenly across the section.Diffuse signal obscures the granular cytoplasmic pattern reported by HPA (HPA: tissue IHC); nonspecific binding or detection background is possible.Compare a section processed without primary antibody. Review blocking, wash steps and chromogen development, then reassess whether individual cells contain distinct cytoplasmic granules.
Nuclei are the strongest stained compartment.Predominant nuclear staining conflicts with the mitochondrial inner membrane location (UniProt Q6NUK1 topology).Check whether counterstain or precipitate is being mistaken for target signal. Compare the primary antibody control and a known-positive glandular section before calling nuclei positive.
Adipocytes stain strongly and expected glandular cells do not.HPA reports adipocytes as Not detected and multiple glandular cell types as High (HPA: tissue IHC); the cell pattern suggests cross-reactivity or endogenous detection activity.Verify the cell identities, inspect a section processed without primary antibody, and confirm that the glandular positive control worked in the same run.
Staining varies sharply between adjacent cells or regions.Cell populations can differ in reported staining level: HPA specifies High glandular cells but Not detected adipocytes, cardiomyocytes and myocytes (HPA: tissue IHC).Identify each cell population before treating variation as an assay failure. Score cytoplasmic granules within the relevant cells and compare the distribution with a matched positive control.
A proposed result relies on faint signal in heart or skeletal muscle.UniProt describes weak expression in these tissues, while HPA reports cardiomyocytes and myocytes as Not detected by IHC (UniProt Q6NUK1; HPA: tissue IHC).Do not use faint muscle staining alone to establish specificity. Check a High-staining glandular control and require the expected granular cytoplasmic distribution before interpreting the signal.

Sample controls for SLC25A24 IHC & IF

🧪Run breast first: glandular cells should stain (HPA: High in breast glandular cells). Use adipose tissue as the negative tissue; adipocytes in the breast section, when present, should lack specific staining and provide an internal background comparison (HPA: Not detected in adipose tissue adipocytes).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SLC25A24 in A-431, U-251MG, U2OS, Rh30, with annotated localisation: Mitochondria (enhanced) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and rabbit IgG isotype controls matched to the primary antibody’s format, plus SLC25A24 knockout tissue if available (caption: rabbit primary antibody; standard IHC practice). Quench endogenous peroxidase and check adipocyte-rich areas for nonspecific background before interpreting DAB staining (caption: HRP/DAB detection; standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported, and the selected A08355-1 paraffin-section caption does not state a fixative (caption: fixative not stated). The caption uses heat-mediated retrieval in EDTA at pH 8.0, but does not establish that retrieval is required; the supplied evidence does not establish that frozen sections or IF are easier (caption: EDTA pH 8.0 retrieval; HPA: mitochondrial ICC-IF localization). In breast sections, assess staining in glandular cells separately from any background around adipocytes (HPA: High in breast glandular cells; HPA: Not detected in adipose tissue adipocytes).

HPA tissue IHC evidence for SLC25A24

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Caudate Glial cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Cerebral cortex Glial cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced SLC25A24 IHC Tips

Troubleshoot SLC25A24 staining by checking retrieval, mitochondrial pattern and cell identity before comparing signal intensity across sections.

Which retrieval condition should I start with for SLC25A24 paraffin-section IHC?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 (datasheet A08355-1). The selected paraffin-section image used that condition, followed by 10% goat serum and 2 μg/ml primary antibody overnight at 4°C (datasheet A08355-1). If staining is weak, compare a second retrieval condition on adjacent sections while holding antibody concentration and detection constant (standard IHC practice). Score improvement by the expected granular cytoplasmic pattern, rather than total DAB intensity alone (HPA tissue IHC profile). Reject conditions that produce diffuse nuclear staining or widespread tissue damage (HPA tissue IHC profile; standard IHC practice).
How should I troubleshoot weak staining when tissue fixation may have varied?
The selected product image identifies a paraffin section but does not report its fixative, so target-specific fixation sensitivity remains unknown (datasheet A08355-1 caption). Record the fixative, fixation duration and processing history for each section before comparing staining intensity (standard IHC practice). Compare affected sections with a similarly processed positive control, keeping the EDTA pH 8.0 retrieval and primary incubation constant (datasheet A08355-1; standard IHC practice). If morphology is poor or signal falls across multiple antigens, investigate processing quality before changing the SLC25A24 antibody (standard IHC practice). Do not assign a fixation effect from expression patterns alone (HPA tissue IHC profile; standard IHC practice).
What staining pattern should count as correctly localised SLC25A24?
Expect granular cytoplasmic staining in positive cells, consistent with a mitochondrial pattern (HPA tissue IHC profile). SLC25A24 resides in the mitochondrial inner membrane and has 6 transmembrane segments (UniProt Q6NUK1 subcellular location and topology). At chromogenic IHC resolution, judge the intracellular granularity and cell distribution; do not claim that DAB resolves the inner membrane itself (HPA tissue IHC profile; standard IHC practice). Strong staining confined to nuclei, tissue edges or extracellular material warrants review of controls and section quality (UniProt Q6NUK1 subcellular location; standard IHC practice). Compare suspect fields with well-preserved areas of the same section before assigning a biological difference (standard IHC practice).
Could isoforms or epitope location explain variable staining?
SLC25A24 has 2 listed isoforms, but the supplied product caption does not identify the antibody epitope or isoform coverage (UniProt Q6NUK1 isoforms; datasheet A08355-1 caption). Its N-terminal EF-hand region spans residues 19–157, while six membrane segments begin at residue 198 (UniProt Q6NUK1 domains and topology). If samples differ unexpectedly, obtain an epitope map and check whether the recognized sequence is shared by both isoforms (UniProt Q6NUK1 isoforms; standard IHC practice). The record also lists modified lysines, including positions 320, 336 and 437; their effect on this antibody is unknown (UniProt Q6NUK1 modified residues; datasheet A08355-1 caption). Interpret discordance cautiously until epitope coverage is established (standard IHC practice).
How can IF help investigate an ambiguous SLC25A24 IHC pattern?
Use IF as an orthogonal localisation check: mitochondrial localisation is reported independently of the chromogenic tissue pattern (HPA subcellular; HPA tissue IHC profile). Multiplex SLC25A24 with a mitochondrial marker and a marker identifying the expected cell population, then inspect colocalisation within individual cells (HPA subcellular; standard IF practice). Choose spectrally separated fluorophores after checking the tissue's autofluorescence, and include single-stain controls for channel bleed-through (standard IF practice). Match permeabilisation to the mapped epitope: the N terminus is intermembrane-facing, whereas several loops face the matrix across the inner membrane (UniProt Q6NUK1 topology). Optimise detergent exposure with preserved mitochondrial morphology; the IHC caption supplies no IF fixation or permeabilisation condition (datasheet A08355-1 caption; standard IF practice).
What should I check when DAB staining appears widespread or nonspecific?
Begin with a no-primary control to separate antibody-dependent staining from endogenous peroxidase activity and detection background (standard IHC practice). Block endogenous peroxidase before HRP detection, and assess whether the 10% goat-serum block used in the selected image is adequate for your sections (datasheet A08355-1; standard IHC practice). The selected image used 2 μg/ml primary overnight at 4°C and DAB development, giving a starting condition for antibody and chromogen optimisation (datasheet A08355-1). Shorten development or reduce primary concentration if controls support excess signal, while retaining a positive control on each run (standard IHC practice). Prefer granular cytoplasmic signal over uniform haze when judging specificity (HPA tissue IHC profile).
How should I quantify SLC25A24 staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because SLC25A24 staining varies by cell type in the supplied tissue profile (HPA tissue IHC). Report the percentage of positive cells and an intensity-weighted H-score, or positive-cell density per mm² when cell counts vary across regions (standard IHC practice). Restrict positive calls to the expected granular cytoplasmic pattern and apply one threshold consistently to the comparison set (HPA tissue IHC profile; standard IHC practice). Normalise counts to viable cells or analysed viable-tissue area, and exclude folds, edges and necrotic regions by a prespecified rule (standard IHC practice). Keep retrieval, DAB development and image acquisition consistent across sections (standard IHC practice).
How do I distinguish true SLC25A24 positivity from tissue artefact?
A credible positive follows the granular cytoplasmic mitochondrial pattern and occurs in an identifiable cell population (HPA tissue IHC profile; HPA subcellular). Glandular cells in adrenal gland and colon are reported as high, whereas adipocytes and cardiomyocytes are reported as not detected in the supplied tissue profile (HPA tissue IHC). Treat nuclear-only signal, edge accentuation and staining concentrated in necrotic regions as suspect until controls and morphology support interpretation (UniProt Q6NUK1 subcellular location; standard IHC practice). A no-primary section helps identify endogenous enzyme or detection signal, while a matched positive control checks that the staining run worked (standard IHC practice). Compare cells and compartments before interpreting intensity differences as expression changes (standard IHC practice).
Boster reagents

Best SLC25A24 / Mitochondrial adenyl nucleotide antiporter SLC25A24 IHC Antibodies

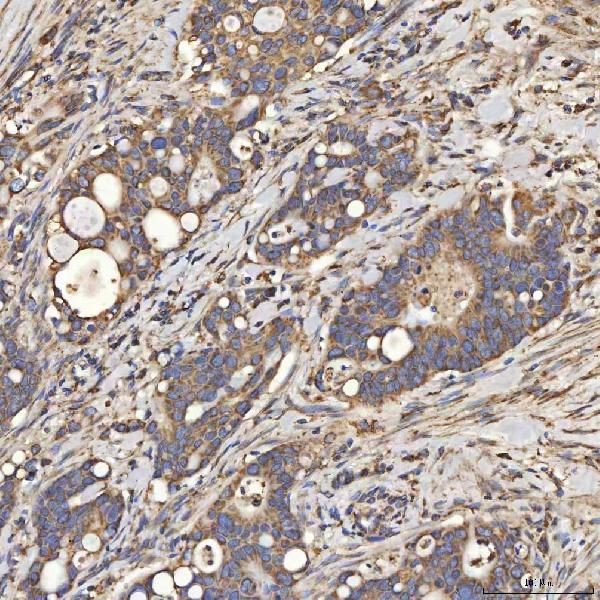
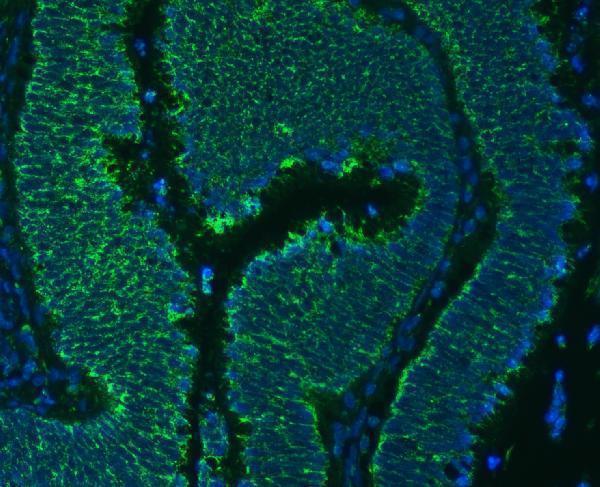
A08355-1 has IHC and IF images from human paraffin sections; the IHC image shows diffuse large B cell lymphoma, and the IF image shows colon cancer (catalog image captions).

Real IHC data IHC analysis of SLC25A24 using anti-SLC25A24 antibody (A08355-1). SLC25A24 was detected in a paraffin-embedded section of human diffuse large B cell lymphoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-SLC25A24 Antibody (A08355-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SLC25A24 Antibody ®
Cat # A08355-1

A08355-1 was tested for IHC in human paraffin sections of diffuse large B cell lymphoma, duodenal papilla adenocarcinoma, endometrioid adenocarcinoma, and glioblastoma (catalog IHC image captions). A08355-1 also has an IF image from a human paraffin section of colon cancer (catalog IF image caption).

Which to pick: Choose A08355-1 for human paraffin-section IHC; its image captions report heat retrieval in EDTA at pH 8.0 and primary antibody at 2 μg/ml, but do not report the fixative (catalog IHC image captions). A08355-1 is also listed for IF at 5 μg/ml and has a paraffin-section IF image; ICC validation is unreported (catalog applications and IF image caption). Cross-species reactivity is unreported: the catalog lists Human only, and no clone is specified (catalog reactivity and clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q6NUK1 (SCMC1_HUMAN, Mitochondrial adenyl nucleotide antiporter SLC25A24).
  2. Human Protein Atlas. SLC25A24 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. SLC25A24 subcellular location (ICC-IF): Localized to the mitochondria..
  4. Human Protein Atlas. SLC25A24 antibody validation summary (2 antibodies).
  5. Comprehensive Analysis and Validation of Solute Carrier Family 25 (SLC25) and Its Correlation with Immune Infiltration in Pan-Cancer. BioMed research international 2022 — PMC9569204.
  6. Tumor bud-derived CCL5 recruits fibroblasts and promotes colorectal cancer progression via CCR5-SLC25A24 signaling. Journal of experimental & clinical cancer research : CR 2022 — PMC8892738.
  7. PubMed PMID:15054102 — UniProt-cited evidence.
  8. PubMed PMID:15123600 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.