SPINT1 / Kunitz-type protease inhibitor 1 · IHC design guide

Design Immunohistochemistry for SPINT1

Plan SPINT1 paraffin IHC around cytoplasmic staining in most tissues (HPA tissue IHC). Appendix glandular cells show high staining, while adrenal gland glandular cells have no detected staining (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
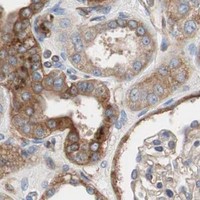
Immunohistochemistry protocol sheet for SPINT1 (IHC for SPINT1): expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A04685, validated IHC image, and IHC protocol steps
Printable SPINT1 IHC protocol sheet — expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC), antibody A04685, controls and protocol steps. Open the full SPINT1 IHC guide →

SPINT1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in most tissues (HPA tissue IHC)
Staining pattern Most tissues show cytoplasmic cell staining (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ Adrenal gland+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Secreted variants may separate RNA and protein patterns (HPA tissue IHC)
Regulation Expression regulation is not annotated (UniProt)
Isoform / epitope 2 isoforms; extracellular versus cytoplasmic epitope is unreported (UniProt)
Section 1

Recommended SPINT1 IHC & IF Protocols

Compare the catalog antibody’s IHC-P protocol with published SPINT1 IHC methods for choroid plexus, pancreas, and tumor tissues (PMC12155093; PMC11615295; PMC7982633).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human prostate tissue; fixative not specified (datasheet A04685)
FixationImage fixative and duration unreported (datasheet A04685); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-SPINT1, 1:50-1:200 (datasheet A04685)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSPINT1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 retrieval at 95–98 °C for 20 min (page retrieval); the pancreas study used protease K specifically for SPINT1 (PMC11615295).
Section 2

What Is the Expected SPINT1 Staining Pattern?

In paraffin-section IHC, expect mainly cytoplasmic staining in many tissues, including glandular cells in appendix and duodenum, adipocytes in adipose tissue, and endothelial cells in colon (HPA tissue IHC). Plasma-membrane staining is also plausible given the reported localisation, although UniProt lists no transmembrane segment (HPA subcellular ICC-IF; UniProt O43278 topology). Interpret the tissue pattern cautiously: HPA rates its IHC evidence Uncertain (HPA tissue IHC).

What am I looking at on my slide?
Clear cytoplasmic chromogen in appendix or duodenal glandular cells, or adipose-tissue adipocytes.These cells have High reported staining and offer useful positive-pattern comparisons (HPA tissue IHC). Assess signal in the named cells, since the HPA tissue profile is Uncertain and does not validate every stained cell (HPA tissue IHC).
A strong, exclusively nuclear IHC pattern with little cytoplasmic signal.Reassess specificity and detection before calling this the expected tissue pattern: HPA describes cytoplasmic IHC in most tissues (HPA tissue IHC). Nucleoplasm is an additional ICC-IF location, so nuclear signal alone cannot prove artefact (HPA subcellular ICC-IF).
Prominent staining in a cell population reported as Not detected, such as lymph-node germinal-center cells.Consider cross-reactivity or endogenous detection activity and compare a negative-reagent control (HPA tissue IHC; general IHC practice). HPA's Uncertain IHC rating makes this a discrepancy to investigate, not proof that the signal is false (HPA tissue IHC).
Diffuse chromogen across tissue and background, obscuring cell boundaries.The distribution cannot establish the reported cell-specific pattern; assess nonspecific binding, blocking, and detection background with controls (general IHC practice). HPA's positive calls identify cell populations, rather than diffuse section-wide staining (HPA tissue IHC).
No signal in appendix or duodenal glandular cells on the test section.Check the stain run and antibody performance against an appropriate control: both cell populations are reported High (HPA tissue IHC; general IHC practice). An absent result is inconclusive on its own because HPA rates the tissue IHC evidence Uncertain (HPA tissue IHC).
💡Expected SPINT1 appearanceCall a positive result when discernible cytoplasmic staining occurs in the reported High cell populations, with possible membrane signal; diffuse background or dominant staining in an unreported cell population warrants control-based review (HPA tissue IHC; HPA subcellular ICC-IF; general IHC practice).
How each factor affects the staining
Tissue pattern and confidenceHPA reports cytoplasmic expression in most tissues but rates tissue IHC Uncertain; use its named High and Not detected cells as comparisons, not absolute pass/fail standards (HPA tissue IHC).
Cellular locationUniProt lists secreted, cytoplasmic, and cell-membrane locations with no transmembrane segment; HPA ICC-IF supports plasma membrane and cytosol (UniProt O43278 topology; HPA subcellular ICC-IF).
Processing and assay epitopeUniProt lists a signal peptide at residues 1–35 and a chain at 36–529. The supplied record gives no IHC antibody epitope, so it cannot predict recognition of processed protein (UniProt O43278 processing).
Isoforms and glycosylationTwo isoforms and three glycosylation sites are recorded, but no supplied IHC evidence assigns a staining difference to either feature (UniProt O43278 isoforms and glycosylation).
Antibody validationHPA006903 is Uncertain for IHC; HPA031178 has no listed IHC status. Their Approved ICC statuses do not establish IHC performance (HPA antibodies).
What should IF/ICC show?HPA supports plasma membrane and cytosol, with nucleoplasm as an additional approved location. This is an ICC-IF localisation reference, not an IHC protocol or a guarantee of matching tissue staining (HPA subcellular ICC-IF).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No chromogen in a reported High cell population.The stain run or antibody may have failed; absence alone cannot resolve the Uncertain HPA IHC evidence (HPA tissue IHC; general IHC practice).Check a same-run positive control, antibody dilution, detection reagents, and counterstain; review retrieval against the antibody's IHC instructions (general IHC practice).
Strong staining in lymph-node germinal-center cells or spleen red-pulp cells.Both populations are reported Not detected; cross-reactivity or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Compare the suspect cells with a negative-reagent control and a reported High cell population in the same run (HPA tissue IHC; general IHC practice).
Section-wide haze obscures glandular cytoplasm.Nonspecific binding or detection background can obscure a cell-resolved IHC pattern (general IHC practice).Inspect negative-reagent controls and blocking, then reassess antibody dilution and detection conditions (general IHC practice).
Only nuclear staining is visible.This differs from the main cytoplasmic tissue profile, although nucleoplasm is an additional ICC-IF location (HPA tissue IHC; HPA subcellular ICC-IF).Check control sections and whether cytoplasmic staining is discernible before assigning the nuclear signal to SPINT1 (general IHC practice; HPA tissue IHC).
Membrane staining appears without a clear cytoplasmic component.Membrane localisation is supported by ICC-IF, but the tissue IHC profile emphasizes cytoplasm (HPA subcellular ICC-IF; HPA tissue IHC).Score the cell type and compartment separately, then compare with reported High cells and controls (HPA tissue IHC; general IHC practice).
An IF/ICC image seems to disagree with the paraffin-section result.HPA's ICC-IF location and tissue IHC pattern come from different applications; its tissue IHC reliability is Uncertain (HPA subcellular ICC-IF; HPA tissue IHC).Interpret each result using its own controls and application-specific antibody status; do not treat Approved ICC as IHC validation (HPA antibodies; general IHC practice).

Sample controls for SPINT1 IHC & IF

🧪Run appendix first: its glandular cells should stain (HPA: appendix glandular cells, High). Use adrenal gland as the negative tissue (HPA: adrenal gland glandular cells, Not detected); on the appendix slide, assess adjacent nonglandular cells as candidate internal negatives only if they are unstained, because HPA does not identify a specific internal-negative cell type there (HPA: appendix glandular cells, High).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: Adrenal gland (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SPINT1 in A-431, RT-4, U2OS, U-251MG, with annotated localisation: Plasma membrane (supported), Cytosol (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and an isotype control matched to the primary antibody’s host species and clonality; use a SPINT1 knockout specimen or peptide blocking, if available, as a biological negative (standard IHC practice). For chromogenic IHC, block endogenous peroxidase when using HRP detection and check for endogenous biotin if using avidin–biotin detection; interpret staining in appendix inflammatory cells cautiously (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the selected A04685 paraffin-section caption does not state a fixative (selected-SKU tissue-IHC caption: fixative not stated). Retrieval dependency is also unreported, so optimize antigen retrieval empirically for paraffin sections (standard IHC practice). Frozen sections or IF cannot be judged easier from these data; HPA reports plasma-membrane and cytosol localization in ICC-IF images, but appendix inflammatory cells may contribute endogenous peroxidase signal in chromogenic IHC (HPA: supported plasma membrane and cytosol localization; standard IHC practice).

HPA tissue IHC evidence for SPINT1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — At least one protein variant secreted, tissue location of RNA and protein might differ and correlation is complex. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →
Cervix Glandular cells High Protein (IHC) HPA →
Colon Endothelial cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Lymph node Germinal center cells Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced SPINT1 IHC Tips

Troubleshoot SPINT1 staining by checking retrieval, cellular location and controls before comparing chromogenic IHC scores across sections.

How should I retrieve SPINT1 in paraffin sections with weak staining?
Use citrate buffer at pH 6.0 for HIER at 95–98 °C for 20 min (page retrieval setting: cytoplasmic/membrane antigen). The selected antibody stains paraffin-embedded human prostate at 1:100, although its caption reports no retrieval conditions or fixative (caption: A04685). Run a positive control alongside test sections, keeping heating, cooling and antibody exposure consistent (standard IHC practice). If signal is weak, check deparaffinisation and delivered temperature before increasing retrieval intensity, which can damage morphology (standard IHC practice). Assess improvement through distinct cellular staining and preserved gland architecture, using appendix glandular cells as a reference pattern (HPA tissue IHC: High in appendix glandular cells).
Could fixation explain variable SPINT1 staining between paraffin blocks?
Target-specific fixation sensitivity is unknown; the selected prostate image identifies paraffin embedding but does not report a fixative (caption: A04685). Record each block’s fixative and fixation duration, and compare sections of similar thickness processed together (standard IHC practice). In a controlled comparison, use the same citrate pH 6.0, 95–98 °C, 20 min retrieval setting and antibody conditions across blocks (page retrieval setting: cytoplasmic/membrane antigen). Check epithelial morphology and internal staining before attributing differences to fixation, since uneven processing can also alter signal (standard IHC practice). Do not infer fixation tolerance from the reported tissue patterns or SPINT1 sequence features (HPA tissue IHC; UniProt O43278).
Should SPINT1 stain membranes, cytoplasm or both in tissue IHC?
Assess membrane-associated and cytoplasmic staining separately: SPINT1 is annotated at the cell membrane and in the cytoplasm, and HPA supports plasma membrane and cytosol localisation (UniProt O43278; HPA subcellular). HPA describes cytoplasmic expression across most tissues, but rates its tissue IHC reliability Uncertain (HPA tissue IHC). Its secreted annotation and lack of an annotated transmembrane segment mean that membrane staining alone cannot establish the molecular form detected (UniProt O43278 topology and localisation). Compare each compartment within the same cell population against a control section processed in parallel (standard IHC practice). Treat isolated nuclear signal cautiously; HPA lists nucleoplasm as an additional location rather than a main location (HPA subcellular).
How can epitope uncertainty affect SPINT1 IHC results?
Confirm the catalog antibody’s epitope before assigning a tissue pattern to either of the 2 annotated SPINT1 isoforms (UniProt O43278 isoforms). The record lists a MANSC region at residues 57–140 and Kunitz regions at 250–300 and 391–441 (UniProt O43278 domains). It also lists glycosylation sites at residues 66, 235 and 523; these positions identify possible epitope considerations, not proven staining effects (UniProt O43278 glycosylation). Compare staining with an independently validated antibody of known epitope, if available, while holding retrieval and detection constant (standard IHC validation practice). Without epitope mapping, report compartment and cell type rather than isoform identity (UniProt O43278 isoforms; standard IHC interpretation).
How should I check SPINT1 localisation by multiplex IF?
Use this IF comparison to examine the membrane and cytosol locations supported by cell imaging (HPA subcellular). Multiplex SPINT1 with a validated marker for the expected glandular cell population, and include single-stain controls to check channel bleed-through (HPA tissue IHC: High in appendix glandular cells; standard IF practice). Choose a far-red fluorophore when tissue autofluorescence compromises shorter-wavelength channels, then inspect an unstained section under identical exposure settings (standard IF practice). Match permeabilisation to the antibody epitope: intracellular access requires it, whereas surface-epitope assessment should first be checked without it (standard IF practice). Because the supplied record does not map this antibody’s epitope, establish epitope accessibility experimentally before interpreting membrane-side signal (UniProt O43278 topology).
What causes diffuse brown background in SPINT1 paraffin IHC?
First compare the test slide with a no-primary control to distinguish detection-system staining from antibody-dependent signal (standard IHC practice). Check deparaffinisation, endogenous peroxidase blocking and wash quality before changing antibody exposure or chromogen development (standard chromogenic IHC practice). The selected antibody has a paraffin-section prostate image at 1:100, but that caption does not establish a working condition for every tissue (caption: A04685). If background persists, shorten primary incubation or titrate around the documented condition while monitoring positive tissue and morphology together (standard IHC practice). Avoid calling diffuse extracellular pigment positive solely because SPINT1 is annotated as secreted; assess its distribution against controls (UniProt O43278 localisation; standard IHC interpretation).
How should I score SPINT1 when membrane and cytoplasmic staining differ? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since SPINT1 has supported membrane and cytosol locations (HPA subcellular). For each compartment, record the percentage of positive cells and an intensity category of 0–3; an H-score can then range from 0–300 (standard IHC scoring practice). Use the same positivity threshold, imaging settings and region-selection rules across sections, with a control slide in each staining run (standard IHC practice). Normalise positive-cell counts to the number of eligible cells, or stained area to the measured tissue area in mm² (standard image-analysis practice). Report glandular and other cell populations separately when comparing tissues with different cellular composition (standard IHC scoring practice).
How do I distinguish credible SPINT1 staining from tissue artefact?
Look for reproducible cellular staining with interpretable membrane or cytoplasmic boundaries, consistent with SPINT1 localisation annotations (UniProt O43278; HPA subcellular). Appendix glandular cells provide a reported high-staining comparison, whereas lymph-node germinal-centre cells are reported as not detected (HPA tissue IHC). Reject isolated section-edge staining, necrotic deposits and signal reproduced on a no-primary slide as evidence of specific cellular SPINT1 staining (standard IHC practice). Check endogenous peroxidase blocking when brown deposits appear in unexpected cells or persist without primary antibody (standard chromogenic IHC practice). Interpret apparent positives conservatively because HPA rates its tissue IHC reliability Uncertain and notes that secreted variants complicate RNA–protein agreement (HPA tissue IHC).
Boster reagents

Best SPINT1 / Kunitz-type protease inhibitor 1 IHC Antibodies

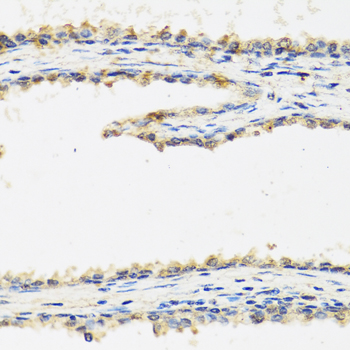
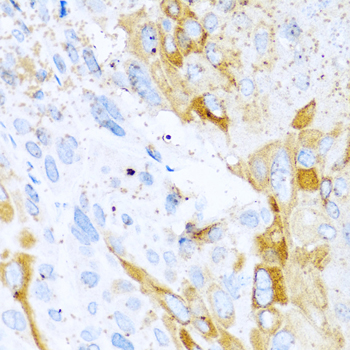
A04685 is listed for IHC and IF in human, mouse, and rat (catalog applications/reactivity). Its images show paraffin-embedded human prostate and mouse esophageal cancer (IHC image captions).

Real IHC data Immunohistochemistry of paraffin-embedded human prostate using SPINT1 antibody at dilution of 1:100 (40x lens).
Anti-SPINT1 Antibody
Cat # A04685

A04685 has an IHC image of paraffin-embedded human prostate at 1:100 (A04685 IHC image caption). It also has an IHC image of paraffin-embedded mouse esophageal cancer at 1:100; IF is listed, but no IF image is supplied (A04685 IHC image caption; catalog applications/IF image alts).

Which to pick: For tissue IHC, choose A04685: its own captions document paraffin-embedded human and mouse specimens, but do not report the fixative (A04685 IHC image captions). For IF/ICC, A04685 is listed for IF at 1:50–1:200, with no IF image or separate ICC validation supplied (A04685 catalog applications/dilution/IF image alts). For cross-species work, A04685 lists human, mouse, and rat reactivity; its host is rabbit and its clonality is unreported (A04685 catalog reactivity/host/clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry O43278 (SPIT1_HUMAN, Kunitz-type protease inhibitor 1).
  2. Human Protein Atlas. SPINT1 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. SPINT1 subcellular location (ICC-IF): Mainly localized to the plasma membrane and cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. SPINT1 antibody validation summary (2 antibodies).
  5. SPINT1 Expressed in Epithelial Cells of Choroid Plexus in Human and Mouse Brains. International journal of molecular sciences 2025 — PMC12155093.
  6. Spint1 disruption in mouse pancreas leads to glucose intolerance and impaired insulin production involving HEPSIN/MAFA. Nature communications 2024 — PMC11615295.
  7. The role of HAI-1 in urothelial bladder cancer: Tissue expression, ectodomain shedding and clinical outcomes. Biochemistry and biophysics reports 2026 — PMC13127185.
  8. MET transcriptional regulator/serine peptidase inhibitor kunitz type 1 panel operating through HGF/c-MET axis as a prognostic signature in pan-cancer. Cancer medicine 2021 — PMC7982633.
  9. PubMed PMID:9045658 — UniProt-cited evidence.
  10. PubMed PMID:12975309 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.