This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC for SRRM2 using its ubiquitous nuclear tissue pattern (HPA tissue IHC). Compare nuclear staining across cells with consistent fixation, and check whether the antibody epitope covers the 3 reported isoforms (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear tissue staining (HPA tissue IHC) | |
| Staining pattern | Ubiquitous nuclear staining (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A07592) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Broad nuclear staining limits tissue specificity (HPA tissue IHC) | |
| Regulation | Low tissue specificity (HPA tissue RNA) | |
| Isoform / epitope | 3 isoforms; check antibody epitope coverage (UniProt) |
The catalog antibody protocol uses Tris-EDTA pH 9.0 retrieval (datasheet A07592). These published IHC protocols provide three tissue-specific comparisons (PMC10827842; PMC13319659; PMC11502262).
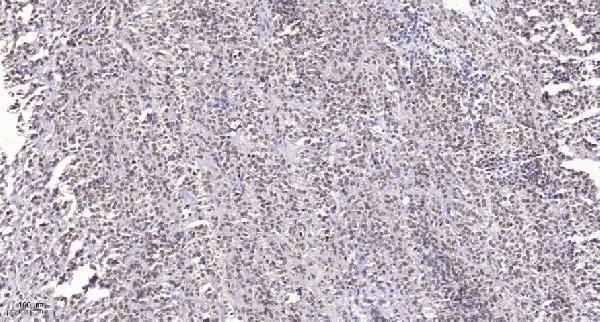
| Sample | Paraffin-embedded human Small intestinal stromal tumor tissue; fixative not specified (datasheet A07592) |
| Fixation | Image fixative and duration unreported (datasheet A07592); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A07592); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-SRRM2, 1:50 (datasheet A07592) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | SRRM2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control. |
SRRM2 should produce nuclear staining in many cell types in paraffin sections (HPA: ubiquitous nuclear expression; UniProt Q9UQ35: nucleus and nuclear speckle). HPA reports high staining in glandular, hematopoietic, respiratory epithelial, neuronal and glial cells across its listed tissues, with supported IHC reliability based on agreement with RNA expression (HPA: tissue IHC, Supported). SRRM2 has no transmembrane segment (UniProt Q9UQ35: topology).
| Nuclear signal in glandular cells of appendix or adrenal gland, or hematopoietic cells of bone marrow. | This fits the reported distribution: each listed population has High HPA tissue staining (HPA: tissue IHC). Score nuclei within the identified cell population; compare intensity and the fraction of positive nuclei within that population. A positive control supports interpretation of the assay, but does not prove that every stained cell in a test section is specific. |
| Strong cytoplasmic, membranous or extracellular deposit dominates while nuclei are weak or blank. | The dominant compartment conflicts with the nuclear assignment (UniProt Q9UQ35: nucleus; HPA: ubiquitous nuclear expression). Treat the deposit as possible nonspecific staining or detection artefact. Recheck morphology, run the appropriate detection controls and assess whether any convincing nuclear signal remains before calling the section SRRM2 positive. |
| Signal is confined to a cell population outside the listed HPA examples while expected nuclei in the same section are blank. | The pattern warrants review for antibody cross-reactivity or endogenous detection activity. HPA reports low tissue specificity and ubiquitous nuclear expression, so an unlisted cell type is not automatically negative (HPA: tissue IHC). The concern is the combined compartment and control pattern, rather than the cell name alone. |
| Widespread diffuse color obscures nuclei, tissue edges or blank spaces. | Background can make a nuclear result uninterpretable. General IHC practice is to inspect the no-primary control, blocking and washes, then shorten chromogen development or reduce detection strength if needed. HPA supports a nuclear target pattern, but does not identify the cause of background in this preparation (HPA: tissue IHC). |
| No nuclear signal appears in a control tissue expected to stain strongly. | A blank appendix glandular compartment or bone marrow hematopoietic compartment conflicts with HPA High staining in those cells (HPA: tissue IHC). First assess tissue preservation, cell identity and the assay controls; then review antibody application, retrieval and detection as general IHC variables. A blank run alone cannot establish absent SRRM2 expression. |
| Tissue and cell selection | HPA reports High staining in adrenal and appendix glandular cells, bone marrow hematopoietic cells, bronchial respiratory epithelium, caudate neuronal cells and cerebral cortex glial cells (HPA: tissue IHC). Use an identified listed population for a positive-control readout. These examples do not define exclusive expression or a validated negative tissue (HPA: low tissue specificity; negative list empty). |
| Antibody evidence | HPA041411 has Supported IHC status; HPA066181 has no IHC status in the supplied record (HPA: antibodies). HPA's tissue profile is also Supported, reflecting agreement with RNA expression (HPA: tissue IHC). Keep these evidence levels separate: an ICC result alone does not establish performance in paraffin sections. |
| Isoforms and epitope | UniProt lists three SRRM2 isoforms and a full-length chain spanning residues 1–2752 (UniProt Q9UQ35: isoforms and processing). The supplied sources do not locate the IHC antibody epitope or show which isoforms it detects. If samples disagree, review the antibody's stated immunogen before attributing the difference to an isoform. |
| Topology and processing | SRRM2 is assigned to the nucleus and nuclear speckle, with no transmembrane segment, signal peptide or propeptide annotated (UniProt Q9UQ35: location, topology and processing). Those annotations support a nuclear readout; they do not establish how fixation or retrieval affects this antibody, or justify interpreting a membrane rim as the expected signal. |
| IF/ICC: what should the pattern look like? | HPA describes enhanced nuclear speckle localization in ICC-IF; both listed antibodies have Enhanced ICC status (HPA: subcellular; HPA: antibodies). Speckles provide a localization cross-check. Assess paraffin chromogenic sections by their nuclear staining pattern and morphology (HPA: tissue IHC); this IF/ICC observation is not an IF protocol recommendation. |
| Situation | Likely cause | Next action |
|---|---|---|
| Known-positive tissue is blank. | Possible assay failure, unsuitable section or missed positive cell population; HPA lists High staining in appendix glandular and bone marrow hematopoietic cells (HPA: tissue IHC). | Confirm the relevant cells are present, examine a run control and check antibody application, retrieval and detection using general IHC practice. Repeat the run before interpreting a test section as truly negative. |
| Color is mainly cytoplasmic or outlines cell membranes. | The compartment disagrees with the reported nuclear location (UniProt Q9UQ35: location; HPA: tissue IHC). Nonspecific primary binding or detection artefact is possible. | Compare with a no-primary control, inspect nuclear counterstain and tissue morphology, and review the antibody's IHC evidence. Count only convincing nuclear staining as the expected readout. |
| Only an unexpected cell population stains. | Cross-reactivity or endogenous detection activity is possible, especially if an HPA-listed high-staining population on the section is blank (HPA: tissue IHC). HPA's low tissue specificity means cell identity alone is insufficient to reject a nuclear signal. | Check the no-primary control and compartment, then compare an HPA-listed positive population. Investigate detection activity and antibody specificity before assigning the signal to SRRM2. |
| Diffuse deposit prevents scoring nuclei. | General IHC background may arise from detection activity, inadequate blocking or excessive development; the supplied HPA and UniProt records do not identify a cause for this specimen. | Inspect no-primary and detection controls, review blocking and washes, and adjust chromogen development or detection strength as appropriate. Re-score only when nuclear boundaries are readable. |
| A strong nuclear signal varies between tissue types. | Cell composition and expression may differ: HPA reports low tissue specificity but identifies particular cell populations with High staining (HPA: tissue IHC). Variation alone does not establish an assay fault. | Compare the same cell types and scoring criteria, verify tissue identity, and include an HPA-listed positive control. Report intensity and proportion of positive nuclei separately. |
| ICC shows speckles, but paraffin-section staining looks less punctate. | HPA's enhanced nuclear speckle result comes from ICC-IF, whereas its tissue result describes ubiquitous nuclear IHC staining (HPA: subcellular; HPA: tissue IHC). The supplied evidence does not require identical visual detail across methods. | For IHC, judge nuclear localization, identifiable positive cells and assay controls. Use the ICC-IF finding as a localization cross-check; consult the separate IF/ICC guide for that application. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — High consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: SRRM2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Use nuclear staining as the reference pattern when troubleshooting SRRM2 in paraffin sections (UniProt Q9UQ35; HPA tissue IHC).
A07592 is listed for human and mouse IHC and IF (catalog: A07592 applications/reactivity); its IHC figure shows a paraffin-embedded human small intestinal stromal tumor (A07592 IHC caption).
A07592 is the only card and has IHC and IF listed for human and mouse samples (catalog: A07592 applications/reactivity). Its available figure documents IHC on a paraffin-embedded human small intestinal stromal tumor; no IF figure is supplied (A07592 image captions).
Which to pick: Choose A07592 for paraffin-section tissue IHC because its own figure documents that preparation, with Tris-EDTA retrieval at pH 9.0 and primary antibody at 1:200 overnight at 4°C (A07592 IHC caption); the fixative is unreported (A07592 IHC caption). For IF, A07592 is listed, but ICC is not listed and no IF figure is supplied (catalog: A07592 applications/image captions). For cross-species work, A07592 lists human and mouse reactivity and a rabbit host; the supplied image documents human tissue only, and clonality is unreported (catalog: A07592 reactivity/host/clone; A07592 IHC caption).