SSBP2 / Single-stranded DNA-binding protein 2 · IHC design guide

Design Immunohistochemistry for SSBP2

SSBP2 shows general nuclear staining in tissue IHC (HPA tissue IHC). This guide helps plan paraffin-section staining with the catalog antibody at 1:50–1:200 (datasheet) and assess the observed pattern.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for SSBP2 (IHC for SSBP2): expected localisation General nuclear staining (HPA tissue IHC), antibody A09631, validated IHC image, and IHC protocol steps
Printable SSBP2 IHC protocol sheet — expected localisation General nuclear staining (HPA tissue IHC), antibody A09631, controls and protocol steps. Open the full SSBP2 IHC guide →

SSBP2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General nuclear staining (HPA tissue IHC)
Staining pattern Nuclear staining across diverse cell types (HPA tissue IHC)
Antigen retrieval Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Catalog IHC images also show cytoplasmic staining (datasheet: IHC)
Regulation Specific expression regulators unreported (UniProt)
Isoform / epitope Five isoforms; antibody epitope coverage unspecified (UniProt; datasheet)
Section 1

Recommended SSBP2 IHC & IF Protocols

The catalog antibody's IHC-P protocol is accompanied by four published SSBP2 tissue microarray IHC protocols (PMC6291933; PMC7766200; PMC7398516; PMC8871390).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon carcinoma tissue; fixative not specified (datasheet A09631)
FixationImage fixative and duration unreported (datasheet A09631); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-SSBP2, 1:50-1:200 (datasheet A09631)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSSBP2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with Tris-EDTA pH 9.0 at 95–98 °C for 20 min (page retrieval setting). Compare citrate pH 6.0 during optimization (all four cited studies).
Section 2

What Is the Expected SSBP2 Staining Pattern?

SSBP2 should appear predominantly in nuclei (UniProt P81877: nucleus; HPA: general nuclear expression), with nucleoplasmic localisation also observed by ICC-IF (HPA: nucleoplasm, enhanced). Expect staining across multiple cell types, including adipocytes and hematopoietic cells (HPA: High in both); tissue expression is broad (UniProt: ubiquitous). Interpret intensity cautiously: HPA rates tissue IHC reliability Approved, with medium consistency against RNA data and external verification pending (HPA: tissue IHC reliability). SSBP2 has no transmembrane segment (UniProt P81877 topology).

What am I looking at on my slide?
Distinct nuclear chromogen in adipocytes or bone marrow hematopoietic cells, with cell borders and cytoplasm easier to distinguish by counterstain.This fits the expected compartment and reported High staining in those cells (UniProt P81877: nucleus; HPA: High in adipocytes and hematopoietic cells). Judge intensity against controls on the same staining run (general IHC practice).
Predominantly cytoplasmic, membranous, or extracellular staining while nuclei remain clear.That distribution conflicts with the reported nuclear pattern (UniProt P81877: nucleus; HPA: general nuclear expression). Check morphology and background before calling it SSBP2; non-nuclear chromogen can reflect nonspecific binding or detection artefact (general IHC practice).
Strong staining confined to an unexpected cell population, especially without convincing nuclear staining in expected cells.Investigate antibody cross-reactivity or endogenous detection activity (general IHC practice). Do not label every unlisted cell type false positive: SSBP2 is described as ubiquitous (UniProt P81877: tissue specificity), and HPA reports low tissue specificity (HPA: RNA specificity).
Diffuse chromogen across tissue, lumina, edges, or the whole section, obscuring nuclear boundaries.This does not establish the reported nuclear pattern (HPA: general nuclear expression). Examine a detection-only control and review blocking, washes, and detection development; these steps can contribute to background (general IHC practice).
No visible nuclear staining in a section expected to be positive, such as adipose tissue or bone marrow.Those cells have reported High staining (HPA: adipocytes; HPA: hematopoietic cells). Check that the expected cells are present, then review the antibody, retrieval, dilution, and detection controls (general IHC practice); one blank section cannot establish biological absence.
💡Expected SSBP2 appearanceCall a result consistent when chromogen is predominantly nuclear in identifiable cells, with strong examples in adipocytes or hematopoietic cells (HPA: High; UniProt P81877: nucleus); isolated diffuse or predominantly non-nuclear colour warrants an artefact check (general IHC practice).
How each factor affects the staining
Compartment and tissue distributionNuclear scoring is appropriate (UniProt P81877: nucleus; HPA: general nuclear expression). Expect more than one positive tissue or cell class (UniProt P81877: ubiquitous; HPA: low tissue specificity); liver cholangiocytes are reported Low, so they are a weaker intensity benchmark (HPA: Low in cholangiocytes).
Strength of tissue evidenceHPA labels the tissue pattern Approved, but reports medium staining–RNA consistency and pending external verification (HPA: tissue IHC reliability). Treat the published pattern as a guide to control selection and localisation, and confirm an unexpected result with appropriate controls (general IHC practice).
Antibody-specific validationOnly CAB020834 has an IHC Approved entry among the listed HPA antibodies; HPA068605 and HPA071780 have no IHC status in this payload (HPA: antibody validation). ICC Approved entries do not establish IHC-P performance (HPA: antibody validation). Check validation for the actual antibody used.
Isoforms and epitope coverageUniProt lists 5 SSBP2 isoforms (UniProt P81877: isoforms). Their presence does not predict a particular IHC pattern because this record supplies no antibody epitope or isoform-specific staining data; consult the selected antibody's documented target region before interpreting discordant staining.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected positive tissue has no nuclear signal.The section may lack the reported positive cells, or an IHC step may have failed (HPA: High in adipocytes and hematopoietic cells; general IHC practice).Confirm tissue identity and cell preservation; compare a same-run positive control, then review retrieval, primary-antibody dilution, and detection settings (general IHC practice). No SSBP2-specific retrieval setting is supplied.
Chromogen fills cytoplasm or outlines membranes.The pattern conflicts with nuclear SSBP2 localisation (UniProt P81877: nucleus; HPA: general nuclear expression); background or off-target binding is possible (general IHC practice).Check nuclear counterstain and tissue morphology, compare a detection-only control, and reassess antibody validation for IHC-P (general IHC practice; HPA: antibody validation).
Unexpected cells stain more strongly than expected cells.Cross-reactivity or endogenous detection activity is possible (general IHC practice), although broad expression prevents declaring an unlisted cell type negative (UniProt P81877: ubiquitous; HPA: low tissue specificity).Check whether the signal is nuclear, compare controls, and assess endogenous enzyme activity if using enzyme-based chromogenic detection (general IHC practice).
Diffuse background hides nuclear boundaries.Incomplete blocking or washing, or excessive chromogen development, can obscure localisation (general IHC practice).Inspect the detection-only control; review blocking, wash conditions, and development time, then score only cells whose nuclei remain distinguishable (general IHC practice).
Liver cholangiocytes stain weakly compared with another tissue.Low cholangiocyte staining is reported (HPA: Low in liver cholangiocytes); stronger staining is reported in several other cell types (HPA: High in adipocytes and hematopoietic cells).Use an appropriate reported High tissue as a same-run positive reference before treating weak cholangiocyte staining as a technical failure (HPA: tissue IHC; general IHC practice).
Can the IHC-P result define an IF/ICC staining protocol?HPA reports enhanced nucleoplasmic ICC-IF localisation and ICC Approved antibody entries (HPA: subcellular localisation; HPA: antibody validation), but the supplied record gives no IF/ICC protocol conditions.Use the separate IF/ICC guide for its protocol; use this section only to compare the expected nuclear compartment (HPA: nucleoplasm, enhanced; UniProt P81877: nucleus).

Sample controls for SSBP2 IHC & IF

🧪Run adipose tissue first: its adipocytes score High for SSBP2 (HPA: High in adipocytes). HPA detects SSBP2 in all 44 scored tissues, so there is no supported negative tissue; no-primary and isotype controls carry the negative, while any unstained nuclei on the positive slide should appear counterstain-only and should not be treated as validated target-negative cells (HPA: no negative tissue rows; detected in all 44 scored tissues).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: SSBP2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show SSBP2 in A-431, U-251MG, U2OS, HeLa, REH, SH-SY5Y, with annotated localisation: Nucleoplasm (enhanced) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, an isotype control matched to the primary antibody’s host species and clonality, and a paired SSBP2 knockout specimen if available; a peptide-block control is another specificity check (standard IHC practice). Check adipose sections for endogenous peroxidase signal before interpreting chromogen staining (standard chromogenic IHC practice).
⚠️Feasibility: A target-specific fixation window and retrieval dependency are unreported in the supplied evidence; the A09631 paraffin-section caption gives 1:50 but does not report a fixative (A09631 tissue-IHC caption). Optimize antigen retrieval empirically for IHC-P; the evidence does not establish whether frozen sections are easier, although ICC-IF images exist in A-431, U-251MG, U2OS, HeLa, REH, and SH-SY5Y cells (HPA: subcellular ICC-IF images). Adipocyte lipid vacuoles displace nuclei, so score intact nuclei carefully; nucleoplasmic staining is the expected localization (standard adipose histology; HPA: nucleoplasm enhanced; UniProt P81877: nucleus).

HPA tissue IHC evidence for SSBP2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: SSBP2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced SSBP2 IHC Tips

Troubleshoot SSBP2 staining by checking nuclear localisation, section processing and control slides before comparing signal across samples.

How should I optimise antigen retrieval when nuclear SSBP2 staining is weak?
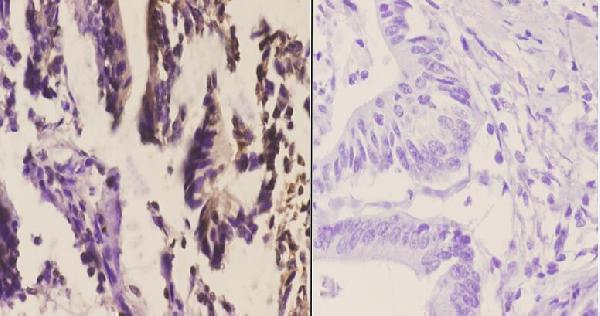
Start with Tris-EDTA pH 9.0 heat-induced antigen retrieval at 95–98 °C for 20 min (page retrieval specification). Assess whether nuclei become distinct without widespread tissue damage, since SSBP2 is nuclear and HPA reports general nuclear staining (UniProt P81877; HPA tissue IHC). If signal remains weak, compare a citrate buffer at pH 6.0 as a fallback on adjacent sections while keeping antibody incubation and detection constant (standard IHC practice). Cool sections consistently after heating and include a no-primary control to identify retrieval-associated background (standard IHC practice). The selected image used the catalog antibody at 1:50 in paraffin-embedded colon carcinoma, but reports no retrieval method (caption A09631).
Could fixation explain inconsistent SSBP2 staining between paraffin sections?
Target-specific fixation sensitivity is unknown; the selected paraffin-section caption does not identify its fixative (caption A09631). Record the fixative, fixation duration and interval before processing for every specimen, then compare sections processed together with the same retrieval and detection conditions (standard IHC practice). If fixation varies, examine matched material under controlled processing conditions before attributing weaker nuclear staining to biological differences (standard IHC practice; UniProt P81877 localisation). Keep section thickness consistent, for example 4 µm, and inspect tissue preservation alongside signal intensity (standard IHC practice). HPA staining patterns establish an observed nuclear profile, but provide no target-specific fixation comparison for this experiment (HPA tissue IHC).
How should I assess cytoplasmic staining when SSBP2 is expected in nuclei?
Score well-defined nuclear staining separately from cytoplasmic staining, because UniProt places SSBP2 in the nucleus and HPA reports enhanced nucleoplasmic localisation (UniProt P81877; HPA subcellular). The selected colon carcinoma image describes both cytoplasmic and nuclear staining, so its cytoplasmic signal warrants independent validation rather than automatic inclusion in the nuclear score (caption A09631). Compare intact cells away from section edges and necrotic regions with a no-primary control processed through the same chromogenic detection steps (standard IHC practice). Review haematoxylin counterstaining at high magnification to confirm that brown signal overlies nuclei rather than adjacent cytoplasm (standard IHC practice). Report the proportion of each staining pattern separately so readers can distinguish observations from the expected localisation (UniProt P81877; caption A09631).
Could an antibody epitope or SSBP2 isoform explain uneven nuclear staining?
SSBP2 has 5 annotated isoforms, while the supplied catalog caption does not define the antibody epitope or isoform coverage (UniProt P81877; caption A09631). Check the immunogen sequence against each isoform before interpreting different staining patterns as isoform-specific (standard antibody validation practice). The annotated LisH region spans residues 18–50, and modified residues include lysine 6, serine 321 and threonine 333; their effects on this antibody's staining are untested here (UniProt P81877). Compare nuclear localisation and staining across adjacent sections under identical retrieval conditions, using an independent epitope if available (standard IHC practice). Document any epitope uncertainty when reporting a negative specimen, since a missing signal alone cannot establish absence of every isoform (UniProt P81877 isoforms; standard antibody validation practice).
How can I check SSBP2 localisation by multiplex immunofluorescence?
Use this as a separate IF optimisation: the selected antibody image documents paraffin-section chromogenic IHC, not an IF validation for that antibody (caption A09631). Pair SSBP2 with a marker for the expected cell type, such as an adipocyte marker in adipose tissue or a glandular-cell marker in adrenal tissue, and add a nuclear counterstain (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores after inspecting tissue autofluorescence, reserving the cleaner channel for the weaker signal (standard IF practice). Because SSBP2 is nucleoplasmic and has no transmembrane segment, optimise permeabilisation for access to the nucleus rather than for an extracellular epitope (HPA subcellular; UniProt P81877). Include single-colour and no-primary controls when evaluating apparent colocalisation (standard IF practice).
What should I check when SSBP2 chromogenic staining appears diffuse?
Run a no-primary slide alongside each staining batch; the selected image used PBS instead of primary antibody as its negative control (caption A09631). For peroxidase detection, check an endogenous-peroxidase block before applying chromogen, and inspect whether deposits persist without primary antibody (standard chromogenic IHC practice). Titrate from the documented 1:50 condition if diffuse colour obscures nuclear boundaries, while holding retrieval and exposure to chromogen constant during the comparison (caption A09631; standard IHC practice). Wash thoroughly between incubations and review tissue edges, folds and necrotic areas for localised artefact (standard IHC practice). Treat cytoplasmic colour cautiously because the image reports it, whereas the broader localisation evidence supports nuclear staining (caption A09631; UniProt P81877; HPA subcellular).
What is a defensible way to quantify SSBP2 in paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the scored compartment as nuclei and record cytoplasmic staining separately, reflecting the nuclear localisation evidence and the mixed staining in the selected image (UniProt P81877; HPA subcellular; caption A09631). For each annotated tissue region, report the percentage of positive nuclei and an H-score calculated from the percentages at intensity levels 0–3 (standard IHC scoring practice). Normalise counts to the number of evaluable nuclei, or report positive-cell density per mm² when cell abundance itself is the outcome (standard image-analysis practice). Exclude folds, necrosis and poorly preserved areas using the same rules for every sample (standard histology practice). Keep retrieval, antibody conditions and image thresholds consistent, and review no-primary slides for background before setting positivity thresholds (standard IHC practice; caption A09631).
How do I distinguish true SSBP2 positivity from staining artefact?
Give greatest weight to reproducible nuclear staining in intact cells, since SSBP2 is nuclear and HPA describes general nuclear expression with enhanced nucleoplasmic localisation (UniProt P81877; HPA tissue IHC; HPA subcellular). Confirm that the signal follows the expected cell population in the chosen tissue, rather than assuming every dark deposit is target-positive (HPA tissue IHC; standard histology practice). Flag isolated cytoplasmic staining for review because the selected image reports it, while the independent localisation records favour nuclei (caption A09631; UniProt P81877; HPA subcellular). Compare section edges and necrotic regions with the slide centre, and investigate colour on no-primary slides as possible detection background, including endogenous enzyme activity (standard IHC practice). Interpret weak or absent staining cautiously because HPA rates tissue staining as Approved with medium RNA agreement and pending external verification (HPA tissue IHC).
Boster reagents

Best SSBP2 / Single-stranded DNA-binding protein 2 IHC Antibodies

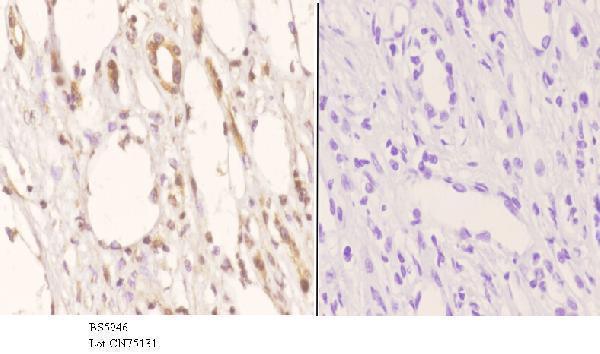
The IHC-validated antibody A09631 has paraffin-section images from human colon and kidney carcinoma (IHC image captions). Human, mouse, and rat reactivity is listed; no IF data are supplied (catalog: reactivity; IF images).

Real IHC data Immunohistochemistry (IHC) analyzes of SSBP2 pAb in paraffin-embedded human colon carcinoma tissue at 1:50.showing cytoplasmic and nucleus staining. Negative control (the right)Using PBS instead of primary antibody, secondary antibody is Goat Anti-Rabbit IgG-biotin followed by avidin-peroxidase.
Anti-SSBP2 Antibody
Cat # A09631

A09631 is listed for IHC and has images of paraffin sections from human colon and kidney carcinoma stained at 1:50 (catalog: applications; IHC image captions). It is listed as reactive with human, mouse, and rat, but the supplied IHC images show human tissue only (catalog: reactivity; IHC image captions).

Which to pick: For tissue IHC, choose A09631: it is rabbit polyclonal, lists an IHC dilution of 1:50–1:200, and has paraffin-section images from human tissue; the fixative is unreported (catalog: host, clonality, dilution; IHC image captions). For IF/ICC, no SKU in this catalog has listed IF testing or an IF image (catalog: applications; IF images). For mouse or rat IHC, A09631 lists reactivity with both species, although its supplied IHC images show human tissue only (catalog: reactivity; IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P81877 (SSBP2_HUMAN, Single-stranded DNA-binding protein 2).
  2. Human Protein Atlas. SSBP2 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. SSBP2 subcellular location (ICC-IF): Localized to the nucleoplasm..
  4. Human Protein Atlas. SSBP2 antibody validation summary (3 antibodies).
  5. Single-stranded DNA binding protein 2 expression is associated with patient survival in hepatocellular carcinoma. BMC cancer 2018 — PMC6291933.
  6. Nuclear Expression Loss of SSBP2 Is Associated with Poor Prognostic Factors in Colorectal Adenocarcinoma. Diagnostics (Basel, Switzerland) 2020 — PMC7766200.
  7. The loss of nuclear expression of single-stranded DNA binding protein 2 of gastric adenocarcinoma and its prognostic role: Analysis of molecular subtype. PloS one 2020 — PMC7398516.
  8. Loss of Single-Stranded DNA Binding Protein 2 Expression Is Associated with Aggressiveness and Poor Overall Survival in Patients with Invasive Breast Carcinoma. Diagnostics (Basel, Switzerland) 2022 — PMC8871390.
  9. PubMed PMID:12079286 — UniProt-cited evidence.
  10. PubMed PMID:10931946 — UniProt-cited evidence.
  11. PubMed PMID:11230166 — UniProt-cited evidence.