STAG2 / Cohesin subunit SA-2 · IHC design guide

Design Immunohistochemistry for STAG2

Plan STAG2 IHC-P around widespread nuclear staining (HPA tissue IHC). Use lymph node germinal center cells as a high-staining reference (HPA tissue IHC), and start the catalog antibody at 2–5 μg/ml (datasheet A03624-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
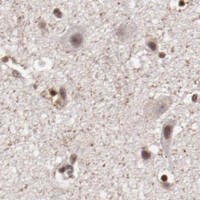
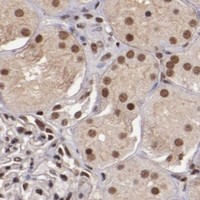
Immunohistochemistry protocol sheet for STAG2 (IHC for STAG2): expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A03624-1, validated IHC image, and IHC protocol steps
Printable STAG2 IHC protocol sheet — expected localisation Nuclear staining in tissue (HPA tissue IHC), antibody A03624-1, controls and protocol steps. Open the full STAG2 IHC guide →

STAG2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in tissue (HPA tissue IHC)
Staining pattern Widespread nuclear staining across tissue cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03624-1)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 44 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Chromatin association changes during mitosis (UniProt)
Regulation Expression regulation is not annotated (UniProt)
Isoform / epitope 2 isoforms; epitope coverage is unknown (UniProt)
Section 1

Recommended STAG2 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet A03624-1). Published protocols below cover bone marrow biopsies (PMC13047209) and bladder tumor arrays (PMC3875130).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon adenocarcinoma tissue; fixative not specified (datasheet A03624-1)
FixationImage fixative and duration unreported (datasheet A03624-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03624-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03624-1)
Primary antibodyRabbit anti-STAG2, 2-5 μg/ml (datasheet A03624-1)
Primary incubationOvernight at 4 °C (datasheet A03624-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03624-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSTAG2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitous nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A03624-1); the bladder study used a high-pH buffer for 30 min (PMC3875130).
Section 2

What Is the Expected STAG2 Staining Pattern?

STAG2 is a nuclear, chromatin-associated cohesin protein with no transmembrane segment (UniProt Q8N3U4). In paraffin-section IHC, expect nuclear staining across many cell types, with intensity varying by tissue and cell population (HPA: ubiquitous nuclear expression; low tissue specificity). HPA rates its tissue IHC evidence Supported, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC reliability).

What am I looking at on my slide?
Nuclear chromogen appears in multiple cell populations, with stronger staining in selected populations.This fits the reported ubiquitous nuclear profile (HPA: tissue IHC). High staining is reported in colon endothelial cells, duodenal glandular cells, and lymph-node germinal-center cells (HPA: High in each population). Compare nuclei within the same section before interpreting intensity differences.
The dominant signal outlines membranes or fills cytoplasm while nuclei remain pale.That compartment conflicts with nuclear and chromatin-associated STAG2 (UniProt Q8N3U4) and the nuclear tissue profile (HPA: tissue IHC). Treat it as suspect staining; inspect the control slide and detection background before assigning it to STAG2.
A population stains much more strongly than expected, or chromogen appears outside cells.Interpret cell identity and compartment together: STAG2 has low tissue specificity, so staining in an additional cell type alone cannot establish cross-reactivity (HPA: low tissue specificity). A nonnuclear or extracellular pattern raises concern for cross-reactivity or endogenous detection activity (general IHC practice).
A broad haze obscures nuclei throughout the section.Diffuse background prevents a reliable nuclear call, even where positive cells are expected (HPA: ubiquitous nuclear expression). Check the negative detection control, blocking, wash conditions, and chromogen development as general IHC troubleshooting steps; do not score the haze as STAG2.
No nuclear signal appears in a selected high-staining control population.A blank control warrants a technical check before calling the specimen negative. Suitable reported high-staining populations include lung alveolar type I cells and placental cytotrophoblasts (HPA: High in each population). Confirm that the selected population is present, then review antibody and detection performance (general IHC practice).
💡Expected STAG2 appearanceCall a result positive when chromogen is predominantly nuclear in identifiable cells, with intensity interpreted against reported High populations (HPA: tissue IHC); dominant membrane, cytoplasmic, or diffuse extracellular color is suspect (UniProt Q8N3U4; general IHC practice).
How each factor affects the staining
Cell population and tissue contextHPA reports High staining in adipocytes, pancreatic endocrine cells, and epididymal glandular cells, but Low staining in liver cholangiocytes and cardiomyocytes (HPA: tissue IHC). Low is a weak-signal expectation, not a negative-control designation.
Compartment and cell-cycle contextSTAG2 associates with chromatin; cohesin distribution changes during mitosis, with centromeric retention in prophase (UniProt Q8N3U4). Assess the overall nuclear pattern across cells rather than demanding identical chromatin detail in every nucleus.
Isoforms and antibody specificityTwo STAG2 isoforms are listed (UniProt Q8N3U4), while the supplied antibody record gives no epitope or isoform coverage (HPA: HPA002857 antibody summary). Do not infer which isoform a stained or unstained nucleus contains.
IF/ICC Q: Does fluorescence show the same compartment?A: HPA reports supported nucleoplasm, nucleoli, and nucleoli fibrillar-center localization in ICC-IF (HPA: subcellular). These finer locations are IF observations; a chromogenic paraffin section need only support a defensible nuclear call.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
The high-staining control is blank.The expected population may be absent from the section, or the IHC workflow may have failed (HPA: reported High populations; general IHC practice).Verify tissue identity and morphology, then check antibody application, detection reagents, and a known-working control run (general IHC practice). Avoid concluding biological STAG2 loss from this slide.
Nuclear signal is weak in liver cholangiocytes or cardiomyocytes.Both populations are reported Low for STAG2 staining (HPA: tissue IHC).Use a reported High population to evaluate assay performance (HPA: tissue IHC). Interpret weak nuclei in these Low populations in context rather than treating them as proof of assay failure.
Cytoplasm or cell borders stain more strongly than nuclei.The distribution disagrees with nuclear STAG2 localization (UniProt Q8N3U4; HPA: ubiquitous nuclear expression).Compare with the negative detection control, review blocking and washing, and assess whether the same nonnuclear pattern occurs across unrelated cells (general IHC practice).
Brown precipitate or diffuse color obscures cellular boundaries.Detection background or excessive chromogen development can obscure localization (general chromogenic IHC practice).Inspect the negative detection control and repeat with controlled development and washes if needed (general IHC practice). Score only signal that can be assigned to intact nuclei.
Only a few cells show intense staining in an otherwise pale section.Cell populations can differ in reported staining level, and the HPA tissue evidence has medium RNA–staining consistency (HPA: tissue IHC reliability and levels).Identify the stained cells morphologically and compare their nuclear pattern with the relevant HPA population; do not generalize a focal result to the entire tissue.
IHC lacks the nucleolar detail shown in an IF image.HPA's nucleoplasm and nucleolar assignments come from ICC-IF, while its tissue IHC profile is described as nuclear (HPA: subcellular; tissue IHC).Judge paraffin-section IHC by identifiable nuclear chromogen and appropriate cell controls (HPA: tissue IHC; general IHC practice). Do not require resolved nucleolar substructures for an IHC-positive call.

Sample controls for STAG2 IHC & IF

🧪Start with colon and score endothelial cells, which HPA rates High for STAG2 (HPA: colon endothelial cells). HPA detects STAG2 in all 44 scored tissues, so there is no validated negative tissue; use no-primary and isotype controls, and expect cells without specific nuclear staining on the positive slide to show counterstain only without treating them as proven biological negatives (HPA: no negative rows; UniProt Q8N3U4: nucleus; standard IHC practice).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: STAG2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show STAG2 in HAP1, SiHa, U2OS, with annotated localisation: Nucleoplasm (supported), Nucleoli (supported), Nucleoli fibrillar center (supported) (HPA subcellular).
Technical controls: Run no-primary (secondary-only) and nonimmune rabbit IgG isotype controls matched to the primary antibody’s format and clonality when known, plus identically processed STAG2-knockout material as a biological negative (selected-SKU caption: rabbit primary antibody; standard IHC practice). For colon HRP/DAB staining, quench endogenous peroxidase and assess background on the no-primary slide (selected-SKU caption: HRP/DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the A03624-1 paraffin-section caption does not state the fixative (selected-SKU tissue-IHC caption). The caption uses heat-mediated retrieval in EDTA at pH 8.0 for colon IHC, but does not establish whether retrieval is required under other conditions (selected-SKU tissue-IHC caption). Frozen-section performance is unreported; HPA has ICC-IF images in HAP1, SiHa and U2OS, but these do not establish that IF is easier, while endogenous peroxidase can create misleading colon DAB background (HPA: subcellular ICC-IF images; standard IHC practice).

HPA tissue IHC evidence for STAG2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Colon Endothelial cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Epididymis Glandular cells High Protein (IHC) HPA →
Lung Alveolar cells type I High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: STAG2 is detected in all 44 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced STAG2 IHC Tips

Use nuclear localisation, the selected antibody’s tissue IHC conditions, and appropriate controls to troubleshoot STAG2 staining in paraffin sections.

What retrieval should I try first when STAG2 nuclear staining is weak?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A03624-1). The selected antibody’s tissue IHC caption used this retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C, so retain those conditions while assessing retrieval (datasheet A03624-1). Include a positive control with expected nuclear staining, such as colon endothelial cells (HPA: High in colon endothelial cells). If signal remains weak, compare a second retrieval buffer on adjacent sections while keeping detection and exposure conditions matched (standard IHC practice). Judge improvement by nuclear signal and tissue preservation together, because damaged morphology makes compartment scoring unreliable (standard IHC practice).
How should I troubleshoot inconsistent STAG2 staining across fixed specimens?
Target specific fixation sensitivity is unknown: the selected paraffin section caption does not state a fixative, and the supplied evidence gives no fixation comparison (datasheet A03624-1). Record each specimen’s fixative and fixation duration, then compare sections processed and stained together to limit handling differences (standard IHC practice). Use the reported EDTA pH 8.0 retrieval and 2 μg/ml primary concentration as reference conditions for the selected antibody (datasheet A03624-1). Check whether intact nuclei in a positive control stain while poorly preserved areas fail, and review morphology before changing antibody concentration (standard IHC practice). Do not treat differences between batches as proof of a STAG2 specific fixation effect without a controlled comparison (standard IHC practice).
Which staining compartment should count as a convincing STAG2 signal?
Prioritise nuclear staining in intact cells: STAG2 is associated with chromatin, chromosomes and centromeres (UniProt Q8N3U4: subcellular location). Tissue IHC shows a ubiquitous nuclear pattern, while cell imaging supports nucleoplasm and nucleolar locations (HPA tissue IHC: ubiquitous nuclear expression; HPA subcellular: supported locations). Compare the chromogenic signal with a nuclear counterstain so cytoplasmic or extracellular colour is not scored as positive nuclei (standard IHC practice). Mitotic cells may differ from interphase cells because cohesin leaves most chromosome arms during prophase while remaining at centromeres (UniProt Q8N3U4: cell cycle localisation). Record those cells separately rather than requiring identical staining patterns across cell cycle stages (standard IHC practice).
Could isoforms or epitope accessibility explain discordant STAG2 IHC results?
STAG2 has 2 annotated isoforms, but the supplied antibody caption does not identify its epitope or establish isoform recognition (UniProt Q8N3U4: isoforms; datasheet A03624-1). Therefore, a negative section cannot distinguish low protein abundance from an inaccessible or unrecognised epitope on its own (standard IHC practice). Compare adjacent sections using the selected antibody’s EDTA pH 8.0 retrieval and matched detection conditions before attributing a discrepancy to isoforms (datasheet A03624-1; standard IHC practice). STAG2 has annotated phosphorylation sites at residues 1058, 1061 and 1064, but their effect on this antibody is unreported (UniProt Q8N3U4: modified residues). Seek independent epitope or isoform information before making an isoform specific claim (standard IHC practice).
How can IF help resolve an ambiguous chromogenic STAG2 pattern?
Use IF/ICC as a separate corroborating assay, then compare its cellular distribution with the nuclear pattern expected in tissue IHC (HPA tissue IHC: ubiquitous nuclear expression). Multiplex STAG2 with a marker identifying the cell population being scored; for example, colon endothelial cells are a reported high staining population, although no marker antibody is specified here (HPA: High in colon endothelial cells). Choose fluorophores and imaging channels after checking specimen autofluorescence and single colour controls (standard IF practice). For cellular IF, use permeabilisation suitable for a nuclear epitope, since STAG2 associates with chromatin and has no annotated transmembrane segment (UniProt Q8N3U4: location and topology; standard IF practice). Interpret nucleoplasmic or nucleolar fluorescence in light of the supported imaging locations, without transferring IF conditions to the paraffin IHC protocol (HPA subcellular: supported locations; standard IHC/IF practice).
What should I change when DAB obscures STAG2 nuclei?
First distinguish diffuse chromogen deposition from discrete nuclear staining using a nuclear counterstain and a section without primary antibody (standard IHC practice). The selected tissue IHC caption used 10% goat serum blocking, a peroxidase conjugated secondary antibody and DAB development (datasheet A03624-1). Check peroxidase blocking, washing and DAB development time as general chromogenic IHC controls, especially when colour appears beyond intact nuclei (standard IHC practice). Titrate detection or primary antibody using adjacent sections if background persists, retaining a positive control to reveal lost sensitivity (standard IHC practice). STAG2 is a nuclear, chromatin associated protein, so widespread extracellular DAB does not support specific target staining (UniProt Q8N3U4: subcellular location).
How should I quantify heterogeneous STAG2 nuclear staining in tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and viable analysis area before scoring, then count only intact nuclei with interpretable chromogen and counterstain (standard IHC practice). Report the percentage of positive nuclei and, if intensity is reproducible, an H score from 0–300 based on the percentages at intensity grades 0–3 (standard IHC practice). Normalise positive counts to all eligible nuclei in the same annotated compartment, or report positive nuclei per mm² with the sampled area stated (standard IHC practice). Keep retrieval, staining and image thresholds matched across comparisons; the selected antibody’s reported retrieval is EDTA pH 8.0 (datasheet A03624-1; standard IHC practice). Stratify cell populations when appropriate because HPA reports high staining in colon endothelial cells and low staining in liver cholangiocytes (HPA tissue IHC: cell specific levels).
When does apparent STAG2 positivity represent artefact rather than true signal?
A convincing result shows signal in intact nuclei within an identified cell population, consistent with STAG2’s nuclear and chromatin association (UniProt Q8N3U4: subcellular location; standard IHC practice). Treat dominant cytoplasmic or extracellular colour, section edge accentuation and necrotic debris as possible artefacts, then compare them with adjacent well preserved tissue (standard IHC practice). A no primary control helps identify detection background, including endogenous enzyme activity in a peroxidase and DAB workflow (standard IHC practice; datasheet A03624-1: detection). Check the cell identity before calling discordance: HPA reports high staining in colon endothelial cells but low staining in liver cholangiocytes (HPA tissue IHC: cell specific levels). Interpret isolated negatives cautiously because the HPA tissue profile has Supported reliability with medium staining to RNA consistency (HPA tissue IHC: reliability).
Boster reagents

Best STAG2 / Cohesin subunit SA-2 IHC Antibodies

The IHC-validated antibody has paraffin-section data from human tumors and IF data from SiHa cells and human colon cancer sections (A03624-1 IHC and IF captions). Human, mouse, and rat reactivity is listed (catalog).

Real IHC data IHC analysis of STAG2 using anti-STAG2 antibody (A03624-1). STAG2 was detected in a paraffin-embedded section of human colon adenocarcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-STAG2 Antibody (A03624-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-SA2/STAG2 Antibody ®
Cat # A03624-1

A03624-1 will render with an IHC figure from a paraffin-embedded human colon adenocarcinoma section (A03624-1 IHC caption). Its IF evidence includes SiHa cells and a paraffin-embedded human colon cancer section (A03624-1 IF captions).

Which to pick: Choose A03624-1 for tissue IHC because its own caption documents chromogenic staining of a paraffin-embedded section; the fixative is unreported (A03624-1 IHC caption). Choose A03624-1 for IF/ICC when an example image matters, or M03624 if a rabbit monoclonal is preferred; M03624 lists IF and ICC applications but has no supplied IF or IHC figure (A03624-1 IF captions; M03624 catalog). Both list human, mouse, and rat reactivity, but the supplied images show human samples only (catalog; A03624-1 IHC and IF captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q8N3U4 (STAG2_HUMAN, Cohesin subunit SA-2).
  2. Human Protein Atlas. STAG2 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. STAG2 subcellular location (ICC-IF): Mainly localized to the nucleoplasm, nucleoli and nucleoli fibrillar center..
  4. Human Protein Atlas. STAG2 antibody validation summary (1 antibodies).
  5. Reduced STAG2 expression in myelodysplastic neoplasms and acute myeloid leukemia myelodysplasia-related: a potential biomarker associated with aneuploidy and disease progression. Frontiers in cell and developmental biology 2026 — PMC13047209.
  6. Frequent truncating mutations of STAG2 in bladder cancer. Nature genetics 2013 — PMC3875130.
  7. Adverse prognostic impact of the loss of STAG2 protein expression in patients with newly diagnosed localised Ewing sarcoma: A report from the Children's Oncology Group. British journal of cancer 2022 — PMC9726932.
  8. Molecular characterization informs prognosis in patients with localized Ewing sarcoma: A report from the Children's Oncology Group. medRxiv : the preprint server for health sciences 2025 — PMC11838998.
  9. PubMed PMID:17974005 — UniProt-cited evidence.
  10. PubMed PMID:15772651 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.