This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic STK3 IHC in paraffin sections around its general cytoplasmic tissue pattern (HPA tissue IHC). Interpret nuclear staining in light of caspase-dependent nuclear entry (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | General cytoplasmic tissue staining (HPA tissue IHC) | |
| Staining pattern | Cytoplasmic staining in adipocytes and glandular cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A02224-2) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep paraffin-section fixation consistent across samples (standard IHC practice; not target-specific) | |
| Caveat | Staining and RNA show medium consistency (HPA tissue IHC) | |
| Regulation | Caspase cleavage may increase nuclear signal (UniProt) | |
| Isoform / epitope | 2 isoforms; cleavage splits chains, so check the epitope (UniProt) |
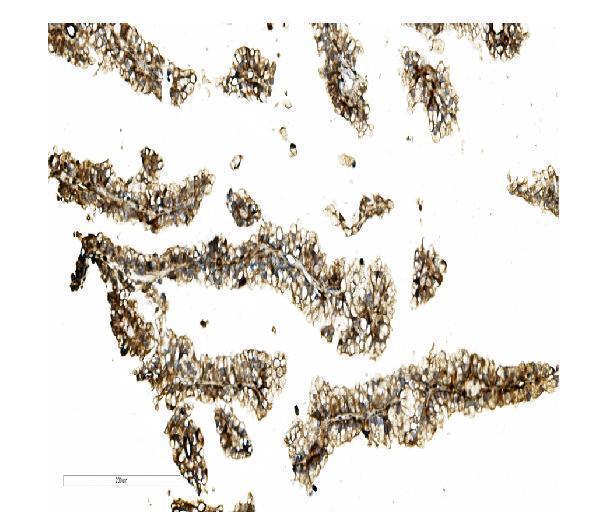
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet: A02224-2). The published IHC protocols below report STK3 staining in canine osteosarcoma and human esophageal carcinoma (PMC12194233; PMC11322239).
| Sample | Paraffin-embedded human renal cancer tissue; fixative not specified (datasheet A02224-2) |
| Fixation | Image fixative and duration unreported (datasheet A02224-2); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A02224-2); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A02224-2) |
| Primary antibody | Rabbit anti-STK3, 2-5μg/ml (datasheet A02224-2) |
| Primary incubation | Overnight at 4 °C (datasheet A02224-2) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet A02224-2) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | STK3-positive staining in adipocytes of adipose tissue (HPA tissue IHC: Medium). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
In paraffin-section IHC, expect a generally cytoplasmic STK3 pattern; HPA rates the tissue staining profile Approved, with medium consistency between antibody staining and RNA data (HPA: tissue IHC). Medium staining is reported in adipocytes, adrenal glandular cells, and bronchial respiratory epithelial cells (HPA: tissue IHC). Nuclear or centrosomal localization is biologically possible (UniProt Q13188: subcellular location). STK3 has no transmembrane segment (UniProt Q13188: topology).
| Cytoplasmic chromogen in adipocytes, adrenal glandular cells, or bronchial respiratory epithelial cells, with recognizable cellular boundaries. | This matches HPA's general cytoplasmic profile and its reported medium staining in those cells (HPA: tissue IHC). Compare cells within the same section as well as across sections; HPA reports low tissue specificity, so a difference between tissues alone does not establish antibody specificity (HPA: tissue IHC). |
| Predominantly membranous or extracellular staining, or nuclear staining without a credible cytoplasmic pattern. | A membrane or extracellular pattern is unexpected for STK3, which lacks a transmembrane segment (UniProt Q13188: topology). Nuclear staining needs context: UniProt reports nuclear localization and cycling of the caspase-cleaved form (UniProt Q13188: subcellular location). Check morphology, controls, and antibody specificity before calling any unusual compartment an artefact. |
| Strong staining in oral or vaginal squamous epithelium while the expected control cells stain weakly or inconsistently. | HPA reports low staining in those squamous epithelial cells (HPA: tissue IHC). A strong reversed pattern raises concern for cross-reactivity or endogenous detection activity, rather than proving either cause (general IHC practice). Inspect the detection-only control and repeat with an independently validated IHC antibody where available (general IHC practice). |
| Uniform haze, edge staining, or chromogen across tissue and empty areas, obscuring cell boundaries. | That distribution does not resemble HPA's cellular cytoplasmic profile (HPA: tissue IHC). Background can arise from nonspecific binding, inadequate washing, or detection chemistry (general IHC practice). Judge the section against a detection-only control before assigning positive cells, and avoid scoring diffuse haze as STK3 expression (general IHC practice). |
| No cellular signal in an adrenal gland or adipose section selected as a positive control. | HPA reports medium staining in adrenal glandular cells and adipocytes, so a blank control warrants a run-level check (HPA: tissue IHC). Confirm that the relevant cells are present and assess control performance, antibody conditions, retrieval, and detection (general IHC practice). A single blank section cannot establish biological absence. |
| Compartment and processing | UniProt places STK3 in cytoplasm, nucleus, and centrosome and reports nuclear–cytoplasmic cycling of its caspase-cleaved form (UniProt Q13188: subcellular location). Its annotated full-length and cleaved chains differ (UniProt Q13188: processing). Thus, nuclear staining can be plausible, but these records do not predict how much of it an individual paraffin section should show. |
| Antibody epitope and isoforms | UniProt lists 2 isoforms and chains spanning residues 1–491, 1–322, and 323–491 (UniProt Q13188: isoforms; processing). An antibody's recognized epitope determines which forms it can detect (general immunoassay principle). The supplied records give no epitope for the IHC antibody, so a particular fragment or isoform cannot be assigned from staining. |
| Tissue and validation context | HPA calls the tissue IHC profile Approved while describing only medium consistency with RNA data; it lists medium staining in several cell types and low staining in others (HPA: tissue IHC). HPA marks HPA073281 and CAB025316 Approved for IHC, whereas HPA007120 is Approved for ICC (HPA: antibody validation). Keep antibody-specific validation tied to the assay used. |
| IF/ICC Q: should its pattern match tissue IHC? | A: HPA reports approved intermediate-filament and rods-and-rings localization in ICC-IF images from HaCaT and U2OS (HPA: subcellular ICC-IF). HPA separately describes general cytoplasmic staining in tissue IHC (HPA: tissue IHC). Treat the ICC-IF structures as an assay-specific observation, not a required chromogenic paraffin-section pattern. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected control cells are blank across the run. | An assay step may have failed; HPA reports medium staining in adrenal glandular cells and adipocytes (HPA: tissue IHC). | Verify control tissue identity and cellular preservation, then check antibody application, the chosen retrieval condition, and chromogenic detection against the assay's IHC instructions (general IHC practice). Reassess study sections only after the control produces interpretable cellular staining. |
| Signal is weak in every section, including the positive control. | Weak assay performance is plausible when the expected HPA medium-staining cells also lose signal (HPA: tissue IHC; general IHC practice). | Review antibody concentration, incubation, retrieval, detection reagents, and counterstain balance using the same positive control (general IHC practice). Adjust one condition at a time; the supplied records do not establish a STK3-specific retrieval or fixation response. |
| Brown signal appears in a detection-only control. | The signal can reflect endogenous detection activity or detection-reagent background rather than primary-antibody binding (general IHC practice). | Use detection-appropriate endogenous-activity controls or blocking and verify the chromogen step according to the detection system (general IHC practice). Reinterpret any matching tissue pattern only after that background is resolved. |
| Strong staining appears mainly at tissue edges or as a section-wide haze. | Edge artefact or nonspecific background can obscure the cellular cytoplasmic pattern HPA describes (HPA: tissue IHC; general IHC practice). | Inspect a detection-only control, washing, blocking, and reagent coverage; then score only well-preserved areas with clear cell boundaries (general IHC practice). Do not turn a diffuse section-wide signal into a positive-cell count. |
| Staining is mostly nuclear or appears as puncta. | UniProt permits nuclear and centrosomal STK3 localization and describes cycling of the caspase-cleaved form (UniProt Q13188: subcellular location). | Check whether puncta lie within identifiable cells and whether the positive control also shows credible cytoplasmic staining (HPA: tissue IHC; general IHC practice). Report the observed compartment; avoid attributing it to cleavage or phosphorylation without separate evidence. |
| Strong staining is concentrated in cells HPA rates low. | An unexpected pattern may reflect specimen biology, cross-reactivity, or detection background; HPA rates oral and vaginal squamous epithelial cells low, not absent (HPA: tissue IHC; general IHC practice). | Compare the cells with an HPA medium-staining control and a detection-only control (HPA: tissue IHC; general IHC practice). If the discrepancy persists, check antibody-specific IHC validation before interpreting it as changed STK3 expression. |



Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Medium | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Medium | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Medium | Protein (IHC) | HPA → |
| Breast | Adipocytes | Medium | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: STK3 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot STK3 staining in paraffin sections by checking retrieval, detection controls, cellular localisation and scoring before interpreting chromogenic signal.
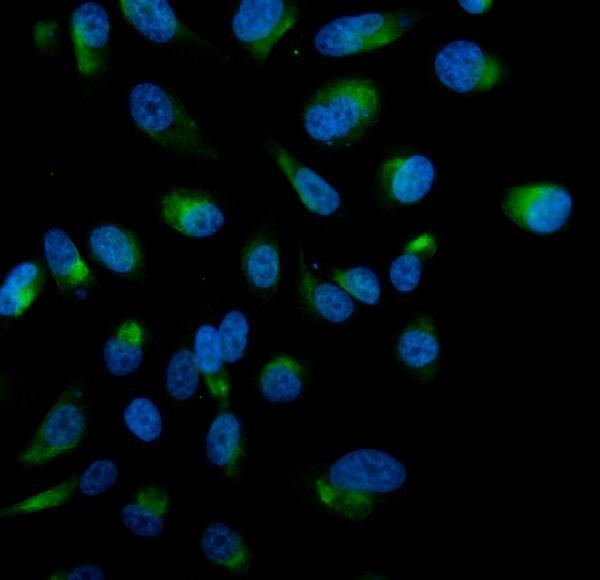
Two anti-STK3 antibodies have human paraffin-section IHC images (A02224-2 and M02224 IHC captions); A02224-2 also has a PC-3 IF/ICC image (A02224-2 IF caption).
A02224-2 will render with IHC in a human renal cancer paraffin section and has a separate IF/ICC image in PC-3 cells (A02224-2 image captions). M02224 will render with IHC in a human kidney paraffin section; IF/ICC is listed as an application, but no IF image is supplied (M02224 IHC caption; catalog applications and IF images).
Which to pick: For tissue IHC, A02224-2 offers a documented human renal cancer paraffin-section example with EDTA pH 8 retrieval and DAB detection; the fixative is unreported (A02224-2 IHC caption). For IF/ICC, choose A02224-2 for its PC-3 fluorescence example (A02224-2 IF caption). For listed mouse or rat reactivity, consider the rabbit monoclonal M02224, whose supplied IHC image shows human kidney paraffin tissue only and does not report the fixative (M02224 catalog reactivity and clone; M02224 IHC caption).