STK33 / Serine/threonine-protein kinase 33 · IHC design guide

Design Immunohistochemistry for STK33

Plan chromogenic STK33 IHC in paraffin sections around the reported cytoplasmic tissue pattern (HPA tissue IHC). Adrenal, breast and parathyroid glandular cells show high staining, but HPA rates the staining reliability uncertain (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for STK33 (IHC for STK33): expected localisation Cytoplasmic in tissue (HPA tissue IHC); perinuclear location is reported (UniProt), antibody A07375-2, validated IHC image, and IHC protocol steps
Printable STK33 IHC protocol sheet — expected localisation Cytoplasmic in tissue (HPA tissue IHC); perinuclear location is reported (UniProt), antibody A07375-2, controls and protocol steps. Open the full STK33 IHC guide →

STK33 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic in tissue (HPA tissue IHC); perinuclear location is reported (UniProt)
Staining pattern Cytoplasmic staining in most tissue cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A07375-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Caudate+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A07375-2)
Caveat Staining has uncertain reliability owing to low RNA agreement (HPA tissue IHC)
Regulation High expression in testis, fetal lung and heart (UniProt)
Isoform / epitope 2 isoforms; confirm antibody epitope coverage (UniProt)
Section 1

Recommended STK33 IHC & IF Protocols

The catalog antibody’s IHC-P protocol is paired with published STK33 staining protocols for aortic and tumor specimens (PMC13480056; PMC6395305).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human colon cancer tissue; fixative not specified (datasheet A07375-2)
FixationImage fixative and duration unreported (datasheet A07375-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A07375-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A07375-2)
Primary antibodyRabbit anti-STK33, 2-5 μg/ml (datasheet A07375-2)
Primary incubationOvernight at 4 °C (datasheet A07375-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A07375-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultSTK33-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues and cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA retrieval at pH 8.0 for the catalog antibody (datasheet: A07375-2); the cited articles do not specify retrieval conditions (PMC13480056; PMC6395305).
Section 2

What Is the Expected STK33 Staining Pattern?

For paraffin-section IHC, expect predominantly cytoplasmic STK33 staining, including in glandular cells of adrenal gland, breast and parathyroid gland (HPA tissue IHC: cytoplasmic profile; High in those cells). UniProt also places STK33 at the cytoskeleton and perinuclear region and reports no transmembrane segment (UniProt Q9BYT3). Treat the pattern as provisional: HPA rates tissue IHC reliability Uncertain because staining and RNA expression have low consistency (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic signal in glandular cells of adrenal gland, breast or parathyroid gland.This fits the reported High staining in these cells (HPA tissue IHC). Compare the stained cell population with tissue structure and a negative control; HPA rates the tissue pattern Uncertain, so intensity alone does not establish specificity (HPA tissue IHC).
Predominantly membrane-bound or extracellular staining, with little cytoplasmic signal.This conflicts with the reported cytoplasmic tissue pattern and the absence of a transmembrane segment (HPA tissue IHC; UniProt Q9BYT3 topology). Check the negative control and section morphology before attributing that pattern to STK33. Nuclear signal alone needs separate interpretation because HPA reports nucleoplasmic ICC-IF staining (HPA ICC-IF).
Strong signal in cells listed as unstained, such as esophageal squamous epithelium.HPA reports STK33 as Not detected in those cells (HPA tissue IHC). Consider cross-reactivity or endogenous chromogenic activity; compare a no-primary control and the expected cytoplasmic distribution. HPA's Uncertain IHC rating makes this a discrepancy to investigate, not proof of either cause (HPA tissue IHC).
Diffuse color across cells, stroma and blank areas.A field-wide deposit obscures the cell-restricted cytoplasmic pattern reported for STK33 (HPA tissue IHC). In general IHC practice, inadequate blocking, concentrated antibody or residual endogenous detection activity can cause background; use a no-primary control to help locate the source.
No signal in adrenal, breast or parathyroid glandular cells.Those cells are reported High by HPA tissue IHC, so an absent signal warrants review (HPA tissue IHC). Check tissue preservation, retrieval, antibody dilution and detection controls using general IHC practice. Do not label the sample STK33-negative from a single failed stain, especially given HPA's Uncertain rating (HPA tissue IHC).
💡Expected STK33 appearanceCall a section provisionally positive when glandular cells show predominantly cytoplasmic staining, potentially strong in adrenal gland, breast or parathyroid gland (HPA tissue IHC: High; Uncertain); widespread acellular color or exclusive membrane staining is suspect (HPA tissue IHC; UniProt Q9BYT3 topology).
How each factor affects the staining
Tissue and cell selectionAdrenal gland, breast and parathyroid glandular cells are reported High, whereas esophageal squamous cells and prostate glandular cells are Not detected (HPA tissue IHC). Use cell-specific comparisons within interpretable sections; these observations remain provisional because HPA rates tissue IHC Uncertain (HPA tissue IHC).
Compartment and topologyUniProt places STK33 in cytoplasm, cytoskeleton and perinuclear region and reports no transmembrane segment or signal peptide (UniProt Q9BYT3). These annotations support intracellular interpretation; they do not identify an antibody epitope or establish how paraffin processing affects staining (UniProt Q9BYT3).
Antibody validationBoth listed antibodies, HPA015742 and HPA056855, have Uncertain IHC status; HPA056855 has Approved ICC status (HPA antibodies). An ICC approval does not resolve the uncertain tissue IHC pattern, so assess specificity with section controls and cell-type context (HPA antibodies; HPA tissue IHC).
IF/ICC Q: should nuclear or flagellar signal appear?Yes, HPA reports Approved nucleoplasm and flagellar-centriole locations, with additional nucleoli, cytosol and mid-piece locations in ICC-IF (HPA ICC-IF). Interpret those images in their own assay context: HPA's tissue IHC summary describes mainly cytoplasmic staining and is rated Uncertain (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected glandular cells have no visible signal.The reported High IHC pattern is absent; HPA rates its tissue IHC reliability Uncertain (HPA tissue IHC).Check section quality, retrieval, dilution and chromogenic detection with appropriate controls using general IHC practice; repeat before interpreting absence as biological.
Signal is weak in an otherwise intact positive tissue.Staining falls below the reported High level in adrenal, breast or parathyroid glandular cells (HPA tissue IHC).Review antibody dilution, incubation and detection performance using general IHC practice; compare cell types, not just overall section color.
Background coats stroma or blank areas.Diffuse deposit obscures the reported cytoplasmic cellular pattern (HPA tissue IHC); the procedural cause is undetermined.Inspect a no-primary control; review blocking, washes and chromogen exposure using general IHC practice.
Membrane or extracellular color dominates.The distribution conflicts with cytoplasmic IHC staining and STK33's lack of a transmembrane segment (HPA tissue IHC; UniProt Q9BYT3).Check morphology and the no-primary control, then reassess whether the cytoplasmic cell signal remains distinguishable.
Cells reported Not detected stain strongly.For example, esophageal squamous cells are listed as Not detected (HPA tissue IHC); off-target binding or endogenous activity is possible.Compare a no-primary control and a reported High cell population; treat the discrepancy cautiously because HPA rates tissue IHC Uncertain (HPA tissue IHC).
Nuclear staining dominates a tissue section.This differs from the mainly cytoplasmic tissue IHC profile, although nucleoplasm is an Approved ICC-IF location (HPA tissue IHC; HPA ICC-IF).Check cell morphology, controls and any accompanying cytoplasmic signal; do not transfer the ICC-IF location directly into an IHC scoring rule.

Sample controls for STK33 IHC & IF

🧪Run adrenal gland first: glandular cells should stain (HPA: High in adrenal gland glandular cells). Use caudate glial cells as the negative tissue (HPA: Not detected in caudate glial cells); on the adrenal slide, adjacent nonglandular tissue should show little background staining, though its STK33 status is not established by the supplied HPA row.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Caudate (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show STK33 in HEK293, U-251MG, U2OS, hTERT-RPE1 (serum starved), Sperm, with annotated localisation: Nucleoplasm (approved), Flagellar centriole (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a rabbit IgG isotype control matched to the primary antibody’s clonality where known, and STK33-knockout tissue or a validated peptide-block control (caption: rabbit anti-STK33 antibody; standard IHC controls). For chromogenic adrenal sections, quench endogenous peroxidase and check that tissue pigment is not mistaken for DAB signal (standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected A07375-2 paraffin-section caption does not state the fixative (caption: fixative not stated). EDTA retrieval at pH 8.0 provides a starting condition, but the caption does not establish that retrieval is required (caption: heat-mediated EDTA retrieval). HPA lists ICC-IF images, but the supplied evidence does not establish whether frozen sections or IF are easier; adrenal pigment may complicate chromogenic scoring (HPA: ICC-IF image cell lines; standard IHC practice).

HPA tissue IHC evidence for STK33

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Parathyroid gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Caudate Glial cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Hippocampus Glial cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced STK33 IHC Tips

Troubleshoot STK33 staining in paraffin sections by checking retrieval, compartment, tissue context and controls before interpreting chromogenic signal.

What retrieval should I try first if STK33 staining is weak?
Start with heat-mediated antigen retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A07375-2). The selected image used that retrieval before incubation with 2 μg/ml primary antibody overnight at 4°C; it does not report a heating time (caption A07375-2). If signal remains weak, compare a second retrieval condition on adjacent sections while holding antibody concentration and DAB development constant (standard IHC practice). Assess tissue integrity and background alongside signal, because excessive heating can damage morphology and make cytoplasmic staining difficult to score (standard IHC practice; HPA: cytoplasmic tissue profile).
Could fixation explain inconsistent STK33 staining between sections?
The selected paraffin-section caption does not state a fixative, so target-specific fixation sensitivity for this antibody is unknown (caption A07375-2). Record fixative, fixation duration and section age for each specimen, then compare matched sections using the same EDTA pH 8.0 retrieval and staining run (standard IHC practice; datasheet A07375-2). If processing varies, test representative specimens side by side before assigning biological meaning to intensity differences (standard IHC practice). Do not use HPA tissue patterns or STK33's lack of a transmembrane segment to infer how a particular fixative affects its epitope (HPA: tissue IHC; UniProt Q9BYT3 topology).
Which staining compartment is plausible for STK33 in tissue sections?
Expect cytoplasmic signal in tissue IHC, while checking whether perinuclear or cytoskeletal accentuation is reproducible (HPA: cytoplasmic tissue profile; UniProt Q9BYT3 subcellular location). STK33 is reported at the caudal end of the manchette in elongating spermatids, so a structured signal there may have biological context (UniProt Q9BYT3 subcellular location). HPA IF/ICC also lists nucleoplasm and flagellar centriole as main locations, but those observations should be checked independently in chromogenic sections (HPA: subcellular location). Compare the same compartment in matched positive and negative controls, and document diffuse, focal and perinuclear patterns separately (standard IHC practice).
How can an unknown epitope affect interpretation of STK33 staining?
STK33 has 2 listed isoforms, a kinase domain at residues 116–381, and a reported phosphoserine at residue 407 (UniProt Q9BYT3 isoforms, domains and modified residues). The supplied caption identifies the antibody concentration and retrieval but gives no epitope sequence or isoform coverage (caption A07375-2). Therefore, staining alone cannot establish which isoform is present or whether phosphorylation at residue 407 changes antibody binding (UniProt Q9BYT3 modified residues; caption A07375-2). If isoform specificity matters, obtain the antibody's immunogen or mapped epitope and validate against an orthogonal isoform-resolving assay before making that claim (standard IHC practice).
How should I adapt STK33 localisation checks to multiplex IF?
Pair STK33 with a marker identifying the expected cell type, and judge overlap within individual cells rather than from adjacent structures (standard IF practice). Because HPA reports cytosol, nucleoplasm and flagellar centriole locations in IF/ICC, select imaging planes and compartment markers that can distinguish these patterns (HPA: subcellular location). Use spectrally separated fluorophores, place the weaker signal in a channel with lower tissue autofluorescence, and include unstained controls (standard IF practice). STK33 has no transmembrane segment; for its intracellular epitopes, optimize permeabilisation after fixation while checking that cell structure and marker staining remain intact (UniProt Q9BYT3 topology and subcellular location; standard IF practice).
How can I reduce diffuse brown background without losing STK33 signal?
Start by comparing a no-primary control with the test section, then check whether brown deposit follows tissue boundaries or appears throughout the slide (standard IHC practice). The selected image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, and a peroxidase-linked secondary for 30 minutes at 37°C (caption A07375-2). If background persists, titrate primary antibody and DAB development on adjacent sections while keeping retrieval at EDTA pH 8.0 (standard IHC practice; datasheet A07375-2). Include an endogenous peroxidase block and adequate washes, and assess any resulting loss of cytoplasmic detail (standard IHC practice; HPA: cytoplasmic tissue profile).
How should I score STK33 staining across heterogeneous specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic compartment before scoring, then apply the same threshold and imaging settings to every section (HPA: cytoplasmic tissue profile; standard IHC practice). An H-score combines the percentage of cells at each intensity with its intensity grade; report the percentage positive separately when intensity estimates are unstable (standard IHC practice). For focal staining, report positive cells per mm² of viable tissue and exclude folds, damaged edges and necrosis (standard IHC practice). Normalize to the number of eligible cells or viable tissue area, and compare matched processing batches because the HPA tissue-IHC reliability is uncertain (standard IHC practice; HPA: uncertain reliability).
What distinguishes credible STK33 staining from artefact in IHC?
Treat reproducible cytoplasmic staining in morphologically intact cells as more credible when it agrees with controls and tissue context (HPA: cytoplasmic tissue profile; standard IHC practice). HPA reports high glandular-cell staining in adrenal gland and breast, medium staining in colon, and undetected staining in prostate glandular cells, but rates its tissue-IHC reliability uncertain (HPA: tissue IHC). Isolated nuclear signal needs separate validation, since HPA IF/ICC lists nucleoplasm while its tissue profile emphasizes cytoplasm (HPA: subcellular location; HPA: tissue IHC). Reject interpretations driven by edge staining, necrosis or signal persisting in a no-primary control, and check for endogenous peroxidase before calling weak DAB deposit positive (standard IHC practice).
Boster reagents

Best STK33 / Serine/threonine-protein kinase 33 IHC Antibodies

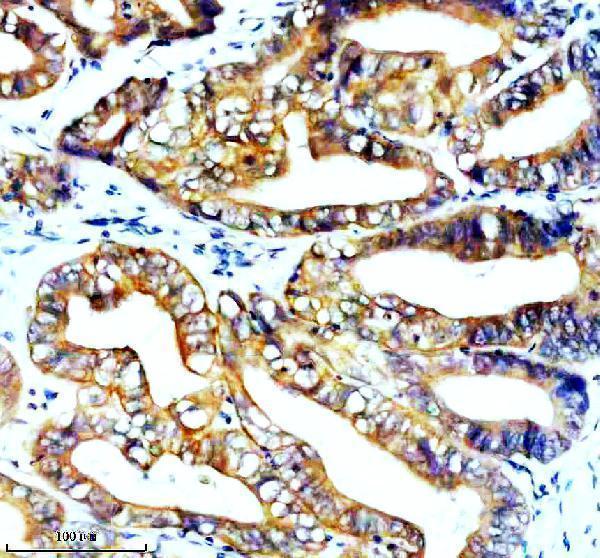
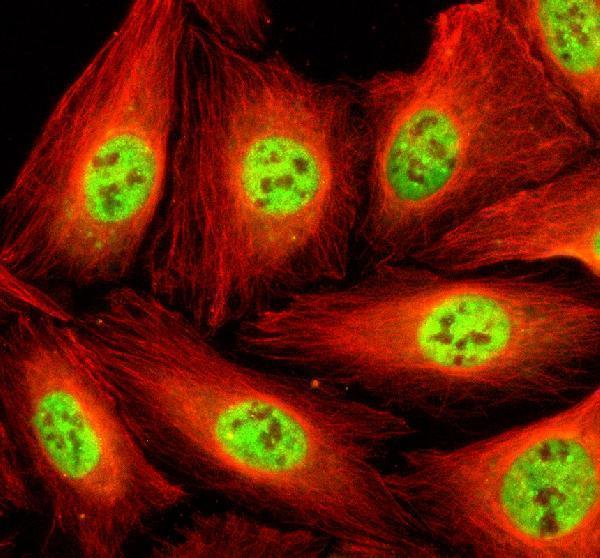
Anti-STK33 IHC/IF options cover human samples (catalog reactivity). A07375-2 also lists mouse and rat reactivity and shows human colon cancer paraffin IHC and U2OS IF/ICC (catalog reactivity; image captions).

Real IHC data IHC analysis of STK33 using anti-STK33 antibody (A07375-2). STK33 was detected in a paraffin-embedded section of human colon cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-STK33 Antibody (A07375-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-STK33 Antibody ®
Cat # A07375-2

A07375-2 has pictured IHC in a human colon cancer paraffin section and IF/ICC in U2OS cells (A07375-2 image captions). M07375 lists human IHC and ICC/IF applications, with no sample image supplied (M07375 catalog).

Which to pick: Choose A07375-2 for chromogenic IHC in human paraffin sections: its own caption documents EDTA retrieval at pH 8.0, 2 μg/ml primary antibody and HRP/DAB detection; the fixative is unreported (A07375-2 IHC image caption). For IF/ICC, A07375-2 has a U2OS image at 5 μg/ml, while M07375 is a rabbit monoclonal that lists human ICC/IF without a supplied IF image (A07375-2 IF image caption; M07375 catalog). For cross-species work, A07375-2 lists human, mouse and rat reactivity, whereas M07375 lists human only; the pictured IHC sample for A07375-2 is human (catalog reactivity; A07375-2 IHC image caption).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9BYT3 (STK33_HUMAN, Serine/threonine-protein kinase 33).
  2. Human Protein Atlas. STK33 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. STK33 subcellular location (ICC-IF): Mainly localized to the nucleoplasm and flagellar centriole. In addition localized to the nucleoli, cytosol and mid piece..
  4. Human Protein Atlas. STK33 antibody validation summary (2 antibodies).
  5. Piceatannol attenuates thoracic aortic aneurysm progression by targeting STK33. Biology direct 2026 — PMC13480056.
  6. STK33/ERK2 signal pathway contribute the tumorigenesis of colorectal cancer HCT15 cells. Bioscience reports 2019 — PMC6395305.
  7. Correlation between STK33 and the pathology and prognosis of lung cancer. Oncology letters 2017 — PMC5649584.
  8. Krüppel-like Factor 4 Suppresses Serine/Threonine Kinase 33 Activation and Metastasis of Gastric Cancer through Reversing Epithelial-Mesenchymal Transition. Clinical cancer research : an official journal of the American Association for Cancer Research 2018 — PMC6765216.
  9. PubMed PMID:11738831 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15489334 — UniProt-cited evidence.