This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan TBCA staining in paraffin sections using its observed cytoplasmic and nuclear tissue pattern (HPA tissue IHC). This guide covers fixation, antibody dilution, detection and interpretation for chromogenic IHC.

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic and nuclear tissue staining (HPA tissue IHC) | |
| Staining pattern | General cytoplasmic and nuclear staining, including glandular cells (HPA tissue IHC) | |
| Antigen retrieval | Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
| Fixation | Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific) | |
| Caveat | Antibody staining has medium consistency with RNA expression (HPA tissue IHC) | |
| Regulation | Low tissue specificity; no regulator reported (HPA tissue IHC; UniProt) | |
| Isoform / epitope | 2 isoforms; epitope differences are unreported (UniProt) |
Compare the catalog antibody’s IHC-P protocol (datasheet) with published chromogenic TBCA IHC methods for zebra finch brain (PMC3754799; PMC4422980).
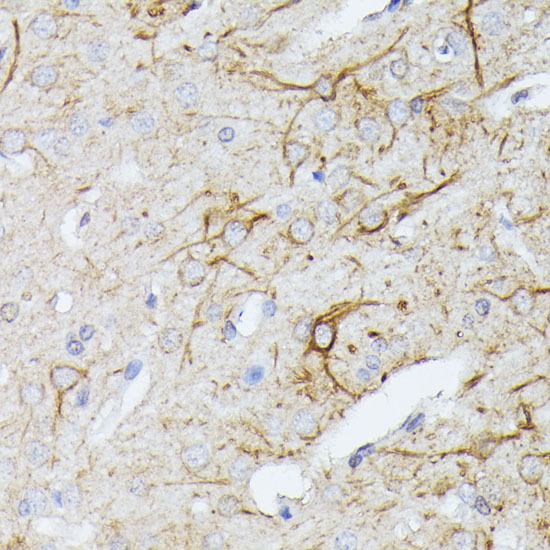
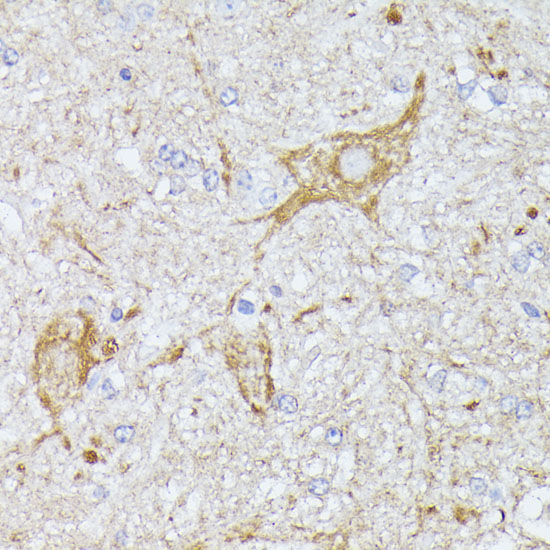
| Sample | Paraffin-embedded rat brain tissue; fixative not specified (datasheet A06926) |
| Fixation | Image fixative and duration unreported (datasheet A06926); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TBCA, 1:50-1:200 (datasheet A06926) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TBCA-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic and nuclear expression. No signal in the no-primary control. |
TBCA is a cytoplasmic, cytoskeleton-associated tubulin-folding protein with no transmembrane segment (UniProt O75347). In paraffin-section IHC, expect staining in glandular, epithelial and muscle cells reported by HPA; HPA also describes general cytoplasmic and nuclear expression (HPA tissue IHC). Treat that pattern as a guide rather than proof of specificity: HPA rates the tissue staining Approved, with medium consistency against RNA data (HPA tissue IHC).
| Cytoplasmic staining in adrenal or parathyroid glandular cells, or pancreatic exocrine cells. | These are reported High-staining populations (HPA tissue IHC). Compare the intended cells with adjacent tissue and controls before scoring: a brown signal in the expected cells supports the pattern, but staining alone does not establish antibody specificity (HPA tissue IHC; standard IHC practice). |
| Cytoplasmic staining with some nuclear staining in an expected cell population. | HPA describes general cytoplasmic and nuclear tissue expression, while UniProt assigns TBCA to the cytoplasm and cytoskeleton (HPA tissue IHC; UniProt O75347). Record the compartments separately; nuclear staining can fit the tissue profile, but it should not replace assessment of the cytoplasmic signal. |
| Predominantly cell-surface, extracellular or tissue-edge staining. | A surface or extracellular pattern is discordant with the annotated cytoplasm and cytoskeleton and the absence of a transmembrane segment (UniProt O75347). Check morphology, section edges and negative controls for nonspecific signal before interpreting it as TBCA (standard IHC practice). |
| Strong staining in cells outside the reported HPA populations, without a convincing pattern in expected cells. | Consider cross-reactivity or endogenous chromogen activity (standard IHC practice). HPA reports low tissue specificity and provides selected examples, not an exhaustive list of positive or negative cell types (HPA tissue IHC); cell identity alone cannot establish that the new signal is false. |
| Diffuse brown haze across cells and extracellular areas, or no staining in a reported high-staining tissue. | Diffuse haze weakens compartment and cell-type scoring; absent signal in a reported positive calls the run into question (standard IHC practice; HPA tissue IHC). Interpret either finding with the negative and positive controls before assigning a biological difference. |
| Cell population and tissue choice | HPA reports High staining in adrenal, appendix, gallbladder and parathyroid glandular cells, pancreatic exocrine cells, nasopharyngeal respiratory epithelium and cardiomyocytes; endometrial stromal cells are Medium (HPA tissue IHC). Use a listed high-staining population as a comparison when judging a weak test section. |
| Compartment interpretation | UniProt places TBCA in the cytoplasm and cytoskeleton; HPA tissue IHC also reports nuclear expression (UniProt O75347; HPA tissue IHC). Document both compartments when present. Their differing emphasis limits how confidently one can reject a nuclear component from tissue IHC alone. |
| Validation and low-signal reference | HPA rates antibody HPA036487 Approved for IHC and calls the tissue profile medium in RNA–staining consistency (HPA antibodies; HPA tissue IHC). Hippocampal glial cells are listed as Low, not negative; weak glial staining is therefore a poor absolute negative control (HPA tissue IHC). |
| Isoforms and processing | UniProt lists 2 isoforms, no signal peptide or propeptide, and a chain spanning residues 2–108 (UniProt O75347). The supplied record gives no IHC epitope position, so it does not show whether the IHC-validated antibody detects both isoforms equally (UniProt O75347; HPA antibodies). |
| IF/ICC Q&A: What localisation should I expect? | Mainly microtubules (supported), with additional nucleolar localisation marked uncertain (HPA ICC-IF). This is an IF/ICC observation, not a requirement that chromogenic tissue IHC resolve microtubules or nucleoli. HPA lists HPA036487 as Supported for ICC and Approved for IHC (HPA antibodies). |
| Situation | Likely cause | Next action |
|---|---|---|
| No signal in a listed high-staining population. | The staining run may have failed, or signal may be below detection; HPA's High designation is a tissue observation, not a guarantee for every section (HPA tissue IHC; standard IHC practice). | Check that the positive control stained and the detection reagents worked; then review the catalog antibody's IHC-P instructions for the chosen retrieval and dilution (standard IHC practice). |
| Weak signal in the test tissue, with a working positive control. | Expression may be lower in the sampled cell population: HPA reports Low in hippocampal glia and Medium in endometrial stromal cells (HPA tissue IHC). | Identify and score the relevant cells before adjusting staining conditions; compare with a listed high-staining population in the same run (HPA tissue IHC; standard IHC practice). |
| Nuclear staining dominates while cytoplasm is faint. | HPA reports nuclear as well as cytoplasmic tissue expression, so nuclear staining alone does not diagnose an artefact (HPA tissue IHC). UniProt's localisation remains cytoplasm and cytoskeleton (UniProt O75347). | Score nuclear and cytoplasmic signal separately, review cell morphology, and compare both compartments with negative controls (standard IHC practice). |
| Brown signal appears in many unrelated cells or outside cells. | Nonspecific binding or endogenous detection activity can obscure the expected cellular pattern (standard IHC practice). Such distribution needs control-based assessment rather than a TBCA call. | Inspect a no-primary control and review blocking, washing and endogenous enzyme suppression appropriate to the chromogenic system (standard IHC practice). |
| Staining is concentrated at tissue edges or on damaged areas. | Uneven reagent exposure or damaged-section background can create a spatial pattern unrelated to the expected cell distribution (standard IHC practice). | Exclude visibly damaged areas from scoring and compare intact regions with the positive and negative controls (standard IHC practice). |
| An IF/ICC image shows nucleolar signal, but tissue IHC does not. | HPA labels nucleoli an uncertain additional IF/ICC location; its supported main IF/ICC location is microtubules (HPA ICC-IF). | Do not require nucleolar staining for a positive IHC call. Judge the tissue section by its cell populations, cytoplasmic pattern and run controls (HPA tissue IHC; standard IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Endometrium | Cells in endometrial stroma | Medium | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: TBCA is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot TBCA staining in paraffin sections by checking retrieval, localisation and controls before comparing signal intensity across samples.
A06926 has IHC images of paraffin-embedded rat brain and mouse spinal cord (A06926 image captions); human, mouse, and rat reactivity is listed (catalog: A06926 reactivity).
A06926 is the sole SKU and is listed for IHC (catalog: A06926 applications). Its images show paraffin-embedded rat brain and mouse spinal cord stained at 1:100 (A06926 image captions).
Which to pick: For paraffin-section tissue IHC, choose A06926; its images use microwave antigen retrieval in 10 mM PBS, pH 7.2, and the fixative is unreported (A06926 image captions). No IF/ICC option is documented: A06926 does not list IF/ICC or show IF images (catalog: A06926 applications and image alts). For work across species, A06926 is a rabbit polyclonal listed as reactive with human, mouse, and rat, with IHC images for rat and mouse (catalog: A06926 host, dilution_raw, reactivity, and image captions).