This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan paraffin-section IHC for TCEA1 using high-staining glandular tissues and a low-staining comparator (HPA tissue IHC). Interpret nuclear staining in light of the observed cytoplasmic signal (UniProt; HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear expected (UniProt); nuclear and cytoplasmic in tissue (HPA tissue IHC) | |
| Staining pattern | High glandular cell staining, nuclear and cytoplasmic (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Appendix+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep formalin fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Cytoplasmic signal may complicate nuclear scoring (HPA tissue IHC) | |
| Regulation | Low tissue specificity at the RNA level (HPA tissue RNA) | |
| Isoform / epitope | 2 isoforms; epitope differences are unreported (UniProt) |
The catalog antibody’s IHC-P protocol is accompanied by a published mouse liver IHC protocol for TCEA1 (PMC9134917).
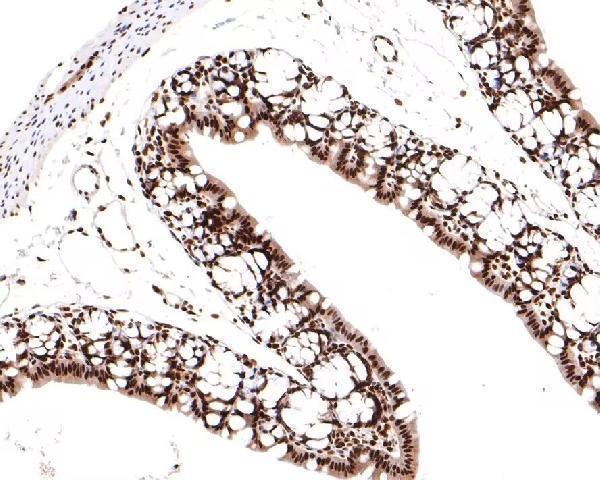
| Sample | Paraffin-embedded mouse large intestine tissue; fixative not specified (datasheet M08133) |
| Fixation | Image fixative and duration unreported (datasheet M08133); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit monoclonal (clone 29T88) anti-TCEA1, 1:50-1:200 (datasheet M08133) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TCEA1-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control. |
TCEA1 is a nuclear transcription factor (UniProt P23193: nucleus; no transmembrane segment). In paraffin sections, expect staining in glandular cells of the appendix, cervix, duodenum, fallopian tube, gallbladder and rectum, among other HPA high-staining cell populations (HPA: tissue IHC). HPA describes general nuclear and cytoplasmic expression; its tissue IHC assessment is Approved, with medium consistency between antibody staining and RNA expression (HPA: tissue IHC).
| Clear nuclear staining in glandular cells, with some cytoplasmic staining. | This fits the expected compartment and cell pattern: UniProt places TCEA1 in the nucleus, while HPA tissue IHC reports general nuclear and cytoplasmic expression and high staining in several glandular cell populations (UniProt P23193: nucleus; HPA: tissue IHC). Compare the signal with adjacent tissue structures before assigning a score. |
| Cytoplasmic staining dominates while nuclei remain unstained. | That pattern deserves review because nuclear localization is supported by UniProt and HPA ICC-IF (UniProt P23193: nucleus; HPA: supported nucleoplasm). Cytoplasmic staining alone is not proof of an artefact: HPA tissue IHC also describes cytoplasmic expression. Check nuclear counterstaining and the positive control before interpreting the compartment. |
| Strong staining appears in adipocytes, cardiomyocytes or skeletal myocytes. | HPA reports TCEA1 as not detected in those cell populations (HPA: tissue IHC). Unexpected signal could reflect cross-reactivity or endogenous detection activity (general IHC practice). Review its location within the cells and compare it with appropriate detection controls; an HPA 'not detected' call is a reference pattern, not an absolute exclusion. |
| Colour is spread evenly across cells, connective tissue and blank slide areas. | A pattern without cell boundaries or the expected nuclear enrichment is difficult to attribute to TCEA1 (UniProt P23193: nucleus; HPA: tissue IHC). Assess blocking, detection reagents and washes using control sections (general IHC practice). HPA's reported cytoplasmic staining should not be confused with uniform slide background. |
| No staining is visible in a high-staining reference cell population. | This conflicts with HPA observations for, for example, appendix glandular cells or lymph-node germinal center cells (HPA: High in those cells). Verify that the expected cells are present and that the staining run worked (general IHC practice). A single negative section cannot establish that TCEA1 is absent. |
| Reference cell population | HPA reports high staining in pancreatic exocrine glandular cells and lymph-node germinal center cells, as well as the listed glandular populations (HPA: tissue IHC). Score the identified cells rather than treating an entire tissue section as uniformly positive. |
| Compartment evidence | UniProt lists the nucleus; HPA tissue IHC describes nuclear and cytoplasmic expression (UniProt P23193: nucleus; HPA: tissue IHC). These sources support a nuclear expectation while allowing cytoplasmic signal in tissue sections. |
| Antibody validation | HPA043786 is Approved for IHC and Supported for ICC (HPA: antibody validation). HPA describes medium consistency between tissue staining and RNA expression (HPA: tissue IHC). Interpret ambiguous or unexpected staining with controls rather than treating the validation label as proof of specificity in every section. |
| Isoforms and processing | UniProt lists 2 isoforms and a single annotated chain spanning residues 1–301, with no signal peptide or propeptide (UniProt P23193). The supplied record gives no antibody epitope, so it cannot establish whether staining distinguishes the isoforms. |
| IF/ICC Q&A | Where should IF/ICC signal appear? Mainly in the nucleoplasm, with additional nucleolar localization (HPA: subcellular ICC-IF). This is an IF/ICC observation; assess the paraffin IHC result against the tissue IHC pattern (HPA: tissue IHC). |
| Situation | Likely cause | Next action |
|---|---|---|
| A reference section has no convincing signal. | The expected cells may be absent from the section, or the staining run may have failed (general IHC practice). | Locate a documented high-staining cell population, such as appendix glandular cells (HPA: High), and check the run controls before changing staining conditions (general IHC practice). |
| Signal is mainly cytoplasmic. | HPA permits cytoplasmic staining in tissue IHC, but a complete lack of nuclear signal needs evaluation (HPA: tissue IHC; UniProt P23193: nucleus). | Check compartment boundaries with the counterstain and compare a high-staining reference section (general IHC practice; HPA: tissue IHC). |
| A normally unstained cell population looks strongly positive. | Possible cross-reactivity or endogenous detection activity (general IHC practice); HPA reports adipocytes and cardiomyocytes as not detected (HPA: tissue IHC). | Compare the signal with a detection control and confirm the cell identity and staining compartment (general IHC practice). |
| The whole section has diffuse colour. | Nonspecific background can arise from blocking, detection or washing conditions (general IHC practice). | Inspect control sections and adjust the relevant general IHC steps; do not score diffuse colour as TCEA1 staining (general IHC practice). |
| Staining varies between fields of one tissue. | HPA levels refer to named cell populations, not every cell in a tissue (HPA: tissue IHC). | Identify and score comparable cells in each field; record compartment and intensity separately (general IHC practice). |
| The IHC pattern differs from an IF/ICC image. | HPA's tissue IHC profile includes nuclear and cytoplasmic staining, whereas its ICC-IF summary emphasizes nucleoplasm and nucleoli (HPA: tissue IHC; HPA: subcellular ICC-IF). | Judge each preparation against its matching HPA observation and review any unexplained compartment difference with controls (general IHC practice). |

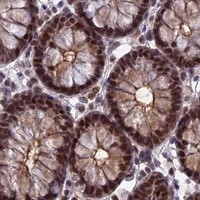
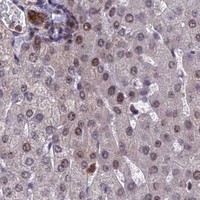


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Cervix | Glandular cells | High | Protein (IHC) | HPA → |
| Duodenum | Glandular cells | High | Protein (IHC) | HPA → |
| Fallopian tube | Glandular cells | High | Protein (IHC) | HPA → |
| Gallbladder | Glandular cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Cerebellum | Cells in granular layer | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
| Hippocampus | Glial cells | Not detected | Protein (IHC) | HPA → |
| Skeletal muscle | Myocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot TCEA1 staining in paraffin sections by checking retrieval, nuclear localisation, controls and scoring before interpreting chromogenic signal.
Anti-TCEA1 catalog antibodies list IHC and IF/ICC use in human, mouse and rat (catalog: M08133, M08133-1 applications and reactivity); only M08133 has a supplied IHC image, from mouse large intestine (M08133 image caption).
M08133 lists IHC and IF/ICC for human, mouse and rat, with an IHC image of a paraffin-embedded mouse large intestine section (M08133 applications, reactivity and image caption). M08133-1 lists IHC and IF/ICC for the same species, but has no supplied IHC or IF image (M08133-1 applications, reactivity and image captions).
Which to pick: Choose M08133 for tissue IHC when an illustrated paraffin-section example matters (M08133 image caption); the caption does not report the fixative (M08133 image caption). Both are rabbit monoclonals listed for IF/ICC and for human, mouse and rat, so either is a catalog-supported starting point for IF/ICC or work across those species (M08133 and M08133-1 host, clone, applications and reactivity). M08133-1 has a different clone and no supplied IHC or IF figure (M08133-1 clone and image captions).