TERF2IP / Telomeric repeat-binding factor 2-interacting protein 1 · IHC design guide

Design Immunohistochemistry for TERF2IP

Plan chromogenic TERF2IP IHC around the observed general nuclear tissue pattern (HPA tissue IHC). The catalog antibody is documented for paraffin sections at 2–5 μg/ml (datasheet A02374-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TERF2IP (IHC for TERF2IP): expected localisation Observed nuclear tissue staining (HPA tissue IHC), antibody A02374-1, validated IHC image, and IHC protocol steps
Printable TERF2IP IHC protocol sheet — expected localisation Observed nuclear tissue staining (HPA tissue IHC), antibody A02374-1, controls and protocol steps. Open the full TERF2IP IHC guide →

TERF2IP Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Observed nuclear tissue staining (HPA tissue IHC)
Staining pattern General nuclear staining across tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02374-1)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+3 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections. (standard IHC practice; not target-specific)
Caveat Staining has medium consistency with RNA expression (HPA tissue IHC)
Regulation Ubiquitous; regulation unspecified (UniProt)
Isoform / epitope No isoforms listed; epitope effects unknown (UniProt)
Section 1

Recommended TERF2IP IHC & IF Protocols

Use the catalog antibody’s IHC-P protocol (datasheet A02374-1) alongside published TERF2IP IHC workflows for colorectal and kidney tissue (PMC10900655; PMC11153720).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human glioma tissue; fixative not specified (datasheet A02374-1)
FixationImage fixative and duration unreported (datasheet A02374-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02374-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02374-1)
Primary antibodyRabbit anti-TERF2IP, 2-5 μg/ml (datasheet A02374-1)
Primary incubationOvernight at 4 °C (datasheet A02374-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02374-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTERF2IP-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A02374-1); compare pH 9.0 high-heat, pressure retrieval for colorectal sections (PMC10900655).
Section 2

What Is the Expected TERF2IP Staining Pattern?

TERF2IP is chiefly nuclear in tissue sections, with HPA describing general nuclear expression and a Supported IHC pattern with medium consistency against RNA data (HPA: tissue IHC). Expect staining in selected cells, including adrenal glandular cells, lymph node germinal center cells, and pancreatic endocrine cells (HPA: High). A cytoplasmic form also exists, but TERF2IP has no transmembrane segment (UniProt Q9NYB0: localization and topology).

What am I looking at on my slide?
Distinct nuclear staining in adrenal glandular cells or lymph node germinal center cells.This fits the reported compartment and high-staining cell populations (HPA: general nuclear expression; High in these cells). Judge the relevant cells individually: the HPA profile does not imply that every cell in either tissue must have equal intensity.
Predominantly membrane staining, with little or no nuclear signal in expected positive cells.A membrane-dominant pattern conflicts with general nuclear tissue staining (HPA: tissue IHC) and the absence of a transmembrane segment (UniProt Q9NYB0: topology). Check morphology and antibody specificity before interpreting it as TERF2IP.
Strong signal in adipocytes, cardiomyocytes, or soft-tissue fibroblasts.These cell types were reported as not detected (HPA: tissue IHC). Unexpected staining warrants a specificity check; cross-reactivity or endogenous detection activity are possible explanations under general IHC practice, not conclusions established by HPA.
Uniform color across nuclei, cytoplasm, and extracellular spaces.Diffuse staining that ignores cell boundaries is difficult to reconcile with general nuclear expression (HPA: tissue IHC). Under general IHC practice, inspect the no-primary control and detection background before assigning this pattern to TERF2IP.
No staining in a well-preserved section containing a reported high-staining cell population.An absent signal in adrenal glandular cells, pancreatic endocrine cells, or cerebellar granular-layer cells conflicts with their reported High staining (HPA: tissue IHC). Verify the relevant cells are present, then review the assay controls and staining workflow; HPA Supported reliability does not guarantee every preparation will stain.
💡Expected TERF2IP appearanceCall the result positive when identifiable cells show clear nuclear chromogen, especially in an HPA High population such as adrenal glandular or lymph node germinal center cells (HPA: tissue IHC); diffuse tissue-wide color or dominant membrane outlining is a suspect pattern (HPA: general nuclear expression; UniProt Q9NYB0: topology).
How each factor affects the staining
Which cells make useful tissue comparisons?Adrenal glandular, cerebellar granular-layer, and lymph node germinal center cells are reported High; adipocytes and cardiomyocytes are Not detected (HPA: tissue IHC). Compare named cell types within intact morphology, rather than calling an entire organ positive or negative.
How much confidence does the tissue pattern carry?HPA labels its tissue IHC pattern Supported and reports medium consistency with RNA data (HPA: tissue IHC). Three listed antibodies have Supported IHC status: HPA006719, CAB018660, and CAB018749 (HPA: antibody validation). This supports a reference pattern, not a guarantee for every reagent or section.
Does cytoplasmic color always mean artefact?UniProt describes a cytoplasmic TERF2IP form associated with the IKK complex (UniProt Q9NYB0: localization). HPA nevertheless describes general nuclear tissue staining (HPA: tissue IHC). Evaluate cytoplasmic signal alongside nuclear staining and controls; its presence alone cannot establish specificity.
IF/ICC Q&A: where should TERF2IP appear?HPA approves nucleoplasm and nuclear bodies as ICC-IF locations (HPA: subcellular). Those observations guide the separate IF/ICC interpretation; they do not specify an IHC retrieval method or prove that nuclear bodies will resolve in chromogenic paraffin sections.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected nuclei are blank in an HPA High cell population (HPA: tissue IHC).The target cells may be absent from the section, or the staining run may have failed (general IHC practice). The supplied sources do not establish TERF2IP-specific fixation sensitivity.Confirm cell identity and section integrity; check the run's positive control and review retrieval and detection against the IHC-validated antibody's own instructions (general IHC practice).
Only a reported Not detected cell population stains strongly (HPA: adipocytes, cardiomyocytes, or fibroblasts).The pattern is discordant with HPA tissue IHC; nonspecific binding or endogenous detection activity is possible (general IHC practice).Check a no-primary control and review blocking and detection controls; compare with a named HPA High cell population in the same staining run (HPA: tissue IHC; general IHC practice).
Chromogen outlines cell membranes more strongly than nuclei.That distribution conflicts with HPA's general nuclear pattern and UniProt's no-transmembrane topology (HPA: tissue IHC; UniProt Q9NYB0: topology).Inspect counterstained morphology and controls, then reassess staining specificity with an IHC-supported antibody where available (HPA: antibody validation; general IHC practice).
A brown haze obscures nuclear detail across the section.Background from detection chemistry, incomplete blocking, or excess staining can obscure localization (general IHC practice).Use a no-primary control to locate background; review blocking, washes, detection, and chromogen development while preserving readable counterstain (general IHC practice).
Cytoplasmic staining accompanies weak nuclear staining.A cytoplasmic form is described (UniProt Q9NYB0: localization), while HPA tissue IHC reports general nuclear expression. The mixed pattern alone cannot identify the source of cytoplasmic color.Score nuclear and cytoplasmic compartments separately; compare HPA High and Not detected cell types and check no-primary background (HPA: tissue IHC; general IHC practice).
Adjacent cells show markedly different staining strengths.HPA reports High, Low, and Not detected staining in specified cell types despite low tissue RNA specificity (HPA: tissue IHC). Uneven technical staining is also possible (general IHC practice).Identify and score each cell population before judging variation; if signal varies independently of cell type, examine section quality and run controls (general IHC practice).

Sample controls for TERF2IP IHC & IF

🧪Run adrenal gland first: its glandular cells should stain (HPA: High in adrenal gland glandular cells). Use parathyroid gland as the negative tissue (HPA: Not detected in parathyroid gland glandular cells); cells without specific staining on the adrenal slide should remain at background, although the supplied HPA rows do not identify a defined internal negative cell type.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
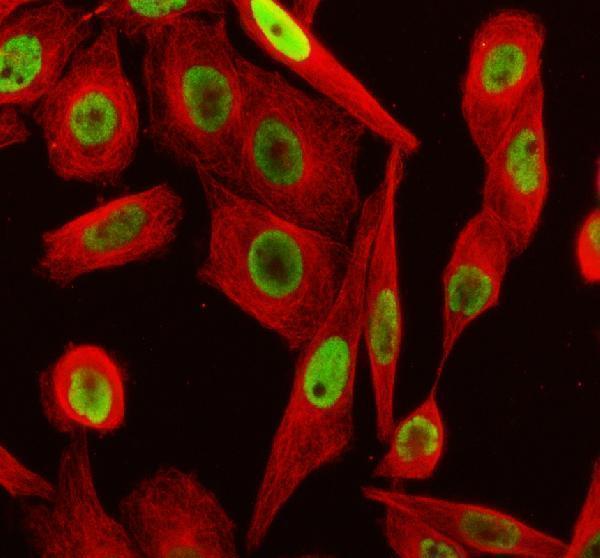
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TERF2IP in A-431, U-251MG, U2OS, SH-SY5Y, SiHa, with annotated localisation: Nucleoplasm (approved), Nuclear bodies (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit IgG isotype control for the rabbit catalog antibody (selected-SKU caption: rabbit anti-TERF2IP). Use TERF2IP knockout material, if available, or a validated peptide block as a biological specificity control; quench endogenous peroxidase and check for intrinsic pigment before interpreting DAB signal (selected-SKU caption: peroxidase secondary and DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU paraffin-section caption does not state the fixative (selected-SKU caption: fixative not stated). The caption uses heat-mediated retrieval in EDTA at pH 8.0, but does not establish that retrieval is required under other conditions (selected-SKU caption: EDTA retrieval). A paraffin IHC procedure is documented, while the supplied evidence does not show that frozen sections or IF are easier; assess adrenal background with the negative controls before scoring (selected-SKU caption: paraffin-section IHC; HPA: High in adrenal gland glandular cells).

HPA tissue IHC evidence for TERF2IP

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Lymphoid tissue High Protein (IHC) HPA →
Cerebellum Cells in granular layer High Protein (IHC) HPA →
Cerebral cortex Neuronal cells High Protein (IHC) HPA →
Hippocampus Neuronal cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced TERF2IP IHC Tips

Use the catalog antibody’s paraffin-section conditions as the starting point, then assess TERF2IP staining by compartment, cell type, and matched controls (caption A02374-1; HPA subcellular).

How should I adjust retrieval if TERF2IP nuclear staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02374-1). The selected tissue image used this condition, 10% goat serum blocking, and 2 μg/ml primary antibody overnight at 4°C (caption A02374-1). If staining is weak, compare shorter and longer heating intervals on adjacent sections while keeping antibody concentration and detection constant (standard IHC practice). Try another retrieval buffer only as a fallback, and check whether stronger signal comes with damaged morphology or edge staining (standard IHC practice). Assess nuclear signal first, since nucleoplasm and nuclear bodies are reported locations (HPA subcellular).
Could fixation explain inconsistent TERF2IP staining between paraffin blocks?
The selected paraffin-section caption does not identify a fixative, so target-specific fixation sensitivity is unknown (caption A02374-1). Record each block’s fixative, fixation duration, and handling history where available, then compare sections stained in the same run (standard IHC practice). Keep retrieval at EDTA pH 8.0 while examining nuclear signal, tissue preservation, and background before changing antibody concentration (datasheet A02374-1; standard IHC practice). Include a consistent reference section to distinguish a block-specific difference from variation between staining runs (standard IHC practice). Neither TERF2IP’s intracellular location nor its annotated phosphorylation sites establish a fixation effect for this antibody (UniProt Q9NYB0).
Is cytoplasmic TERF2IP staining compatible with a convincing IHC result?
Evaluate nuclei first: the tissue profile describes general nuclear expression, and cell imaging places TERF2IP in nucleoplasm and nuclear bodies (HPA tissue IHC; HPA subcellular). Cytoplasmic staining is biologically plausible because a cytoplasmic form associates with the IKK complex (UniProt Q9NYB0). Compare nuclear and cytoplasmic staining separately across cells in the same section, including a secondary-only control for diffuse signal (standard IHC practice). Do not require every positive nucleus to show distinct telomere dots, since TERF2IP also occupies extratelomeric chromosome sites (UniProt Q9NYB0). Treat isolated edge staining or signal restricted to damaged tissue as suspect until it reproduces in intact areas (standard IHC practice).
Can an unreported epitope explain variable TERF2IP IHC staining?
The supplied record lists 0 alternative isoforms but gives no mapped epitope for the catalog antibody (UniProt Q9NYB0; caption A02374-1). TERF2IP has BRCT and Myb-like regions and annotated phosphorylation sites, yet their effect on this antibody’s binding is unknown (UniProt Q9NYB0). Compare adjacent sections with the stated EDTA pH 8.0 retrieval and identical detection before attributing weak staining to epitope accessibility (datasheet A02374-1; standard IHC practice). If retrieval changes signal, also inspect morphology and background so an apparent gain is not overinterpreted (standard IHC practice). An independently validated antibody recognizing a documented different epitope can help test a persistent discrepancy, if available (standard IHC practice).
How can IF help assess an ambiguous chromogenic TERF2IP pattern?
Use a separate IF assay to compare TERF2IP with a marker for the cell type being assessed, such as Hofbauer cells in placenta (HPA: High in Hofbauer cells; standard IF practice). Choose fluorophores whose signals can be separated from tissue autofluorescence, and include single-channel and secondary-only controls (standard IF practice). Permeabilise sufficiently to reach intracellular epitopes because TERF2IP has no transmembrane segment and is reported in nuclear and cytoplasmic compartments (UniProt Q9NYB0; standard IF practice). Compare nuclear localisation with the reported nucleoplasm and nuclear-body pattern rather than expecting exclusively telomeric dots (HPA subcellular; UniProt Q9NYB0). Establish IF fixation conditions within that assay; the paraffin-section caption supplies no fixative (caption A02374-1).
How do I reduce diffuse DAB staining without losing nuclear signal?
First inspect a secondary-only section and an otherwise matched section without primary antibody to locate detection-related background (standard IHC practice). The selected image used 10% goat serum block, 2 μg/ml primary overnight at 4°C, and DAB development (caption A02374-1). If background persists, check peroxidase blocking and shorten DAB development while keeping a reference section in the run (standard IHC practice). Titrate primary concentration around the documented condition only after reviewing controls and confirming that nuclear contrast is preserved (caption A02374-1; standard IHC practice). Score diffuse colour separately from cellular staining, especially where edges or damaged areas stain disproportionately (standard IHC practice).
What is a defensible way to score TERF2IP on DAB sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and nuclear scoring threshold before reviewing groups, then apply the same settings to every section (standard IHC practice). Report the percentage of positive nuclei and an H-score based on staining intensity; use positive-cell density per mm² when cell abundance also matters (standard IHC practice). Normalise nuclear counts to evaluable nuclei in the defined region and density to measured tissue area, excluding folds and necrosis (standard IHC practice). Record cytoplasmic staining separately because TERF2IP also has a reported cytoplasmic form (UniProt Q9NYB0). Include a common reference section across runs, since the reported tissue IHC reliability is Supported with medium staining-to-RNA consistency (HPA tissue IHC; standard IHC practice).
Which TERF2IP staining patterns warrant a specificity check?
A convincing pattern can include nuclear staining, consistent with general nuclear tissue expression and nucleoplasm or nuclear-body localisation (HPA tissue IHC; HPA subcellular). Cytoplasmic signal needs careful comparison with controls, though a cytoplasmic TERF2IP form is reported (UniProt Q9NYB0; standard IHC practice). Check unexpected cell patterns against documented examples: Hofbauer cells are High, whereas adipocytes are Not detected in the reported tissue profile (HPA tissue IHC). Discount staining confined to section edges or necrotic areas, and test DAB colour that persists without primary antibody for endogenous enzyme or detection background (standard IHC practice). Recheck disputed results on intact regions and matched controls before calling a compartment or cell population positive (standard IHC practice).
Boster reagents

Best TERF2IP / Telomeric repeat-binding factor 2-interacting protein 1 IHC Antibodies

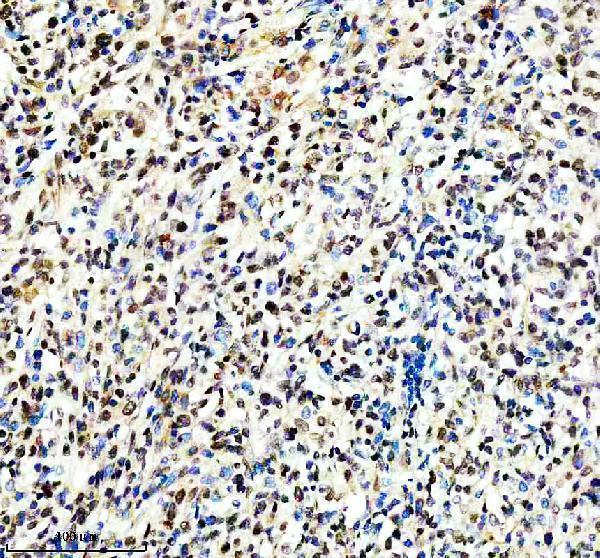
Anti-TERF2IP antibodies have IHC images from human paraffin sections (A02374-1 and M02374 image captions) and an IF image from SIHA cells (A02374-1 IF image caption). A02374-1 also lists mouse and rat reactivity (catalog: A02374-1).

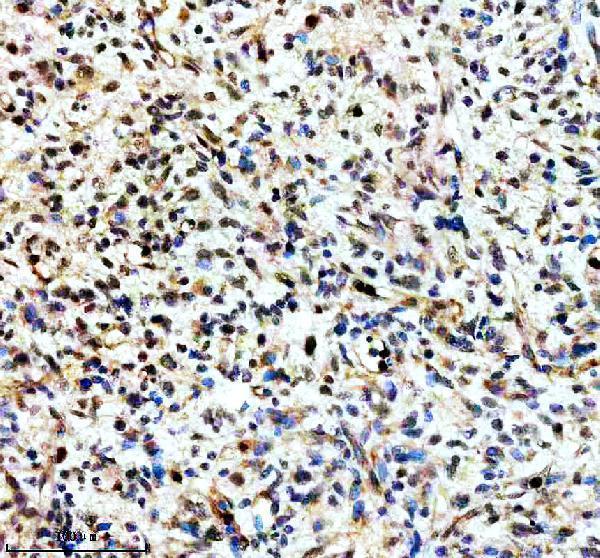
Real IHC data IHC analysis of TERF2IP using anti-TERF2IP antibody (A02374-1). TERF2IP was detected in a paraffin-embedded section of human glioma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-TERF2IP Antibody (A02374-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-TERF2IP Antibody ®
Cat # A02374-1
Real IHC data M02374 staining TE2IP in human testis tissue sections by Immunohistochemistry (IHC-P -paraformaldehyde-fixed, paraffin-embedded sections). Tissue was fixed with formaldehyde and blocked with 3% BSA for 0. 5 hour at room temperature; antigen retrieval was by heat mediation with a citrate buffer (pH6). Samples were incubated with primary antibody (1/25) for 1 hours at 37°C. A undiluted biotinylated goat polyvalent antibody was used as the secondary antibody.
Anti-TERF2IP Antibody
Cat # M02374

A02374-1 will render with a human glioma paraffin-section IHC image; its catalog also includes human lymphoma IHC and SIHA-cell IF images (A02374-1 image captions). M02374 will render with a human testis paraffin-section IHC image (M02374 image caption).

Which to pick: For tissue IHC, choose A02374-1 for human paraffin sections using the pictured EDTA retrieval procedure; its caption does not report the fixative (A02374-1 IHC image caption). M02374 offers a mouse monoclonal alternative for paraffin-section, paraffin-embedded human testis using citrate retrieval (catalog: M02374; M02374 IHC image caption). For IF/ICC or a project involving mouse or rat samples, choose rabbit polyclonal A02374-1 because those applications and species are listed; its pictured IHC evidence is from human tissue (catalog: A02374-1; A02374-1 IHC image captions). The selected A02374-1 tissue-IHC caption documents paraffin sections, but does not specify the fixative (selected-SKU IHC image A02374-1).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9NYB0 (TE2IP_HUMAN, Telomeric repeat-binding factor 2-interacting protein 1).
  2. Human Protein Atlas. TERF2IP tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. TERF2IP subcellular location (ICC-IF): Localized to the nucleoplasm and nuclear bodies..
  4. Human Protein Atlas. TERF2IP antibody validation summary (4 antibodies).
  5. A multi-dimensional approach to unravel the intricacies of lactylation related signature for prognostic and therapeutic insight in colorectal cancer. Journal of translational medicine 2024 — PMC10900655.
  6. Identification and validation of biomarkers in membranous nephropathy and pan-cancer analysis. Frontiers in immunology 2024 — PMC11153720.
  7. PubMed PMID:10850490 — UniProt-cited evidence.
  8. PubMed PMID:15498874 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.