This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan TET2 staining in paraffin sections around its observed nuclear tissue pattern (HPA tissue IHC). This guide covers consistent fixation, IHC antibody selection and interpretation of staining where expression may be reduced in MDS granulocytes (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclei across cell types (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in cells throughout tissues (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adipose tissue+4 more · see all | |
| Negative control | None in HPA (detected in all 45 tissues); use no-primary + isotype controls |
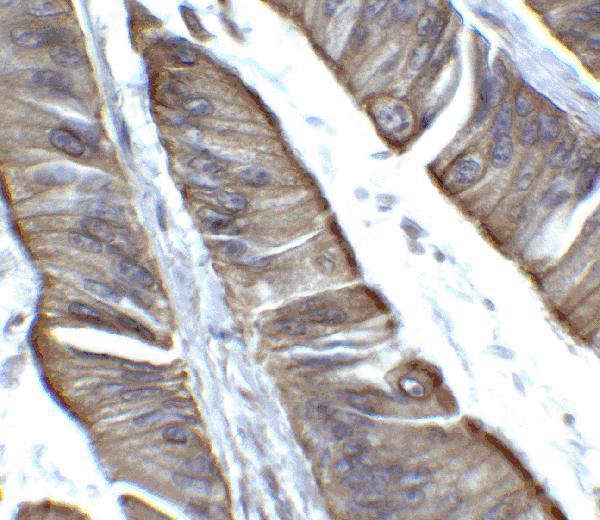
| Fixation | Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A00191) | |
| Caveat | Tissue staining awaits external verification (HPA tissue IHC) | |
| Regulation | Reduced in MDS granulocytes (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope coverage unreported (UniProt; catalog datasheet) |
The catalog antibody’s IHC-P protocol is accompanied by published TET2 staining parameters for head and neck squamous cell carcinoma (PMC7186610) and non-functioning pituitary adenomas (PMC7381329).
| Sample | Tissue sections; selected-image fixative not specified (standard IHC workflow) |
| Fixation | Image fixative and duration unreported (datasheet A00191); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TET2, 2 μg/mL (datasheet A00191) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TET2-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: Ubiquitously expressed in the nuclei of all cells. No signal in the no-primary control. |
TET2 is a nuclear protein with no transmembrane segment (UniProt Q6N021: localization, topology). In paraffin sections, expect staining in nuclei across many cell types, with high staining reported in bone marrow hematopoietic cells and several other cell populations (HPA: tissue IHC). HPA rates the tissue pattern Supported, with medium consistency between staining and RNA expression; external verification is pending (HPA: tissue IHC reliability).
| Nuclear staining appears across multiple cell types in the section. | This fits the reported ubiquitous nuclear pattern (HPA: tissue IHC). Compare intensity within the same run: high staining is reported in bone marrow hematopoietic cells and adrenal glandular cells (HPA: High). Nuclear staining alone does not establish that every stained cell has the same TET2 abundance. |
| Strong signal lies mainly outside nuclei, with little nuclear staining. | A predominantly extranuclear IHC pattern conflicts with TET2's nuclear localization and HPA's tissue pattern (UniProt Q6N021: localization; HPA: tissue IHC). HPA also reports uncertain additional cytosolic localization by ICC-IF, so a small cytoplasmic component is less decisive than loss of the expected nuclear signal (HPA: subcellular ICC-IF). |
| Only one unexpected cell population stains strongly while neighboring nuclei are blank. | TET2 is reported as broadly expressed, and HPA describes nuclear staining in all cells (UniProt Q6N021: tissue specificity; HPA: tissue IHC). An isolated, compartmentally discordant signal warrants checks for cross-reactivity or endogenous chromogenic activity (general IHC practice). Cell-to-cell intensity differences alone do not prove a false positive. |
| A diffuse chromogenic haze obscures nuclei and tissue boundaries. | The slide cannot support a reliable TET2 localization call when background obscures the expected nuclear pattern (HPA: tissue IHC). Review the detection and blocking controls, washing, and primary antibody concentration as general IHC troubleshooting steps (general IHC practice); the supplied sources do not identify a TET2-specific cause. |
| No nuclear signal appears in bone marrow hematopoietic cells. | This differs from a reported high-staining population (HPA: High in bone marrow hematopoietic cells). Check section integrity and run controls before interpreting the absence as biological loss (general IHC practice). HPA reports medium staining/RNA consistency and pending external verification, so one negative section cannot settle TET2 status (HPA: tissue IHC reliability). |
| Expected compartment | UniProt places TET2 in the nucleus and on chromosomes; chromatin localization depends on monoubiquitination at Lys-1299 (UniProt Q6N021: localization). HPA tissue IHC describes ubiquitous nuclear staining (HPA: tissue IHC). Use the nuclear compartment to judge chromogenic signal, without requiring uniform intranuclear texture. |
| Choice of reference tissue | HPA reports high staining in bone marrow hematopoietic cells, adipocytes in adipose tissue, and adrenal glandular cells, among others (HPA: High). Its supplied tissue list contains no negative or low examples (HPA: tissue IHC). Use documented high-staining populations as positive references; do not designate an unsupported tissue as TET2-negative. |
| Antibody and evidence limits | One listed antibody, HPA043135, is rated Supported for IHC (HPA: antibody validation). The tissue profile is Supported with medium staining/RNA consistency and pending external verification (HPA: tissue IHC reliability). These ratings support comparison with the reported pattern, but do not establish that every individual positive or negative cell is correctly classified. |
| Molecular forms | UniProt lists three TET2 isoforms and a single annotated 1–2002 protein chain, with no signal peptide, propeptide, or transmembrane segment (UniProt Q6N021: isoforms, processing, topology). No epitope location is supplied, so the record cannot predict isoform-specific staining or justify interpreting a compartment shift as cleavage or shedding. |
| Situation | Likely cause | Next action |
|---|---|---|
| Nuclei are faint throughout the run, including a documented high-staining control. | Low overall assay sensitivity is plausible; the supplied sources do not identify a TET2-specific retrieval or fixation effect (general IHC practice; HPA: High in bone marrow hematopoietic cells). | Check control performance, antibody dilution and detection reagents, then optimize antigen retrieval within the local IHC workflow (general IHC practice). Do not assign the weak result to TET2 loss until the positive control works. |
| The chromogen is mainly cytoplasmic. | This conflicts with nuclear tissue IHC, although additional cytosolic localization in HPA ICC-IF is marked uncertain (HPA: tissue IHC; HPA: subcellular ICC-IF). | Check the nuclear counterstain and compare compartments in a documented high-staining tissue (general IHC practice; HPA: High in bone marrow hematopoietic cells). Treat persistent cytoplasmic-only IHC as unresolved specificity. |
| Background is widespread even where cellular detail is poor. | Nonspecific antibody binding or detection background can obscure compartment scoring (general IHC practice). The supplied TET2 sources do not specify which mechanism applies. | Inspect a no-primary control, blocking and wash conditions, and the detection system; adjust primary antibody concentration using the local assay's controls (general IHC practice). |
| Signal remains in a no-primary control. | Primary-independent detection or endogenous chromogenic activity is possible (general IHC practice). This control cannot identify TET2 expression. | Troubleshoot the detection chemistry and appropriate endogenous-activity blocking before scoring the TET2 slide (general IHC practice). |
| One cell type appears negative while adjacent cells stain. | True intensity variation or technical variation may contribute; HPA describes ubiquitous nuclear staining but reports only medium staining/RNA consistency (HPA: tissue IHC). | Confirm nuclear morphology, compare same-run positive controls, and repeat or corroborate a consequential cell-type call (general IHC practice). Avoid claiming a validated negative cell population from this payload. |
| The observed pattern differs from HPA images despite an acceptable control. | HPA's tissue interpretation is Supported but pending external verification, and the supplied antibody list gives only one IHC Supported entry (HPA: tissue IHC reliability; HPA: antibody validation). | Record the discrepancy by cell type and compartment, review assay controls, and seek independent corroboration before assigning biological meaning (general IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | High | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Breast | Adipocytes | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| None in HPA: TET2 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead. | ||||
Troubleshoot TET2 staining in paraffin sections by checking retrieval, nuclear localisation, background controls and cell-based scoring before interpreting chromogenic signal.
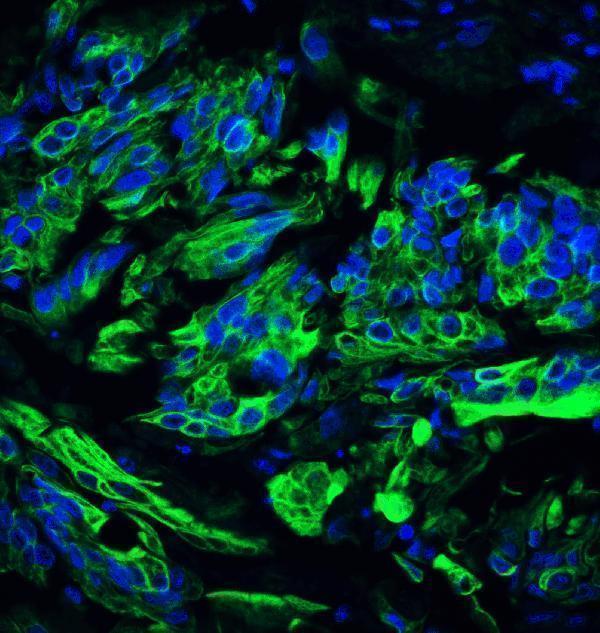
A00191 has IHC and IF images of human colon carcinoma tissue (catalog: A00191 image captions). Its listed reactivity is human (catalog: A00191 reactivity).
A00191 is the SKU with a rendered card and is listed for human IHC-P and IF (catalog: A00191 applications and reactivity). Its own captions show IHC and IF staining in human colon carcinoma tissue (catalog: A00191 image captions).
Which to pick: For tissue IHC, choose A00191: its IHC caption shows human colon carcinoma tissue at 2 μg/mL; the fixative is unreported (catalog: A00191 IHC image caption). For IF, A00191 has an image at 20 μg/mL in human colon carcinoma tissue; for ICC, A00191-2 lists ICC/IF but has no image caption (catalog: A00191 IF image caption; A00191-2 applications and image captions). For mouse or rat samples, A00191-2 lists both species with IHC and ICC/IF, while A00191-3 lists mouse with IHC; clonality is unreported for both (catalog: A00191-2 and A00191-3 reactivity, applications and clone fields).