TFAP2C / Transcription factor AP-2 gamma · IHC design guide

Design Immunohistochemistry for TFAP2C

Plan paraffin IHC around nuclear TFAP2C staining in skin hair follicles, breast glands and placental cytotrophoblasts (HPA tissue IHC). Start with the catalog antibody’s 2–5 μg/ml IHC range (datasheet A01558-2), then compare controls and score nuclear staining.

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TFAP2C (IHC for TFAP2C): expected localisation Nuclear staining in a subset of tissues (HPA tissue IHC), antibody A01558-2, validated IHC image, and IHC protocol steps
Printable TFAP2C IHC protocol sheet — expected localisation Nuclear staining in a subset of tissues (HPA tissue IHC), antibody A01558-2, controls and protocol steps. Open the full TFAP2C IHC guide →

TFAP2C Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear staining in a subset of tissues (HPA tissue IHC)
Staining pattern Nuclei in skin follicles, breast glands and cytotrophoblasts (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01558-2)
Positive control ⓘ Skin+3 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific). Selected-image fixative and duration unreported (datasheet A01558-2); verify before use.
Caveat Staining and RNA show medium consistency (HPA tissue IHC)
Regulation Expression regulation not annotated (UniProt)
Isoform / epitope 2 isoforms; epitope impact unknown (UniProt)
Section 1

Recommended TFAP2C IHC & IF Protocols

The catalog antibody protocol is followed by published TFAP2C IHC methods for EB-clone sections (PMC9395518) and seminoma tissue (PMC11271319).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human testis cancer tissue; fixative not specified (datasheet A01558-2)
FixationImage fixative and duration unreported (datasheet A01558-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01558-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01558-2)
Primary antibodyRabbit anti-TFAP2C, 2-5 μg/ml (datasheet A01558-2)
Primary incubationOvernight at 4 °C (datasheet A01558-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01558-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTFAP2C-positive staining in hair follicles of skin (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in a subset of tissues including skin, placenta and breast. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval (datasheet A01558-2); published alternatives are citrate pH 6 or EDTA pH 9 at 97 °C (PMC11271319).
Section 2

What Is the Expected TFAP2C Staining Pattern?

TFAP2C should appear in nuclei: UniProt places it in the nucleus, and its sequence has no transmembrane segment (UniProt Q92754). On IHC sections, expect staining in skin hair follicles, breast glandular cells, oral squamous epithelium, and placental cytotrophoblasts, with intensity varying by site (HPA tissue IHC). HPA rates the tissue profile Enhanced, while reporting medium consistency between antibody staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Distinct nuclear staining in hair follicles, with weaker staining in selected epithelial cells.This fits the reported pattern: hair follicles are High; breast glandular cells, oral squamous epithelial cells, and placental cytotrophoblasts are Medium (HPA tissue IHC). Judge the relevant cells and their nuclei, rather than expecting every cell in a section to stain (HPA tissue IHC; UniProt Q92754).
Strong cytoplasmic or membrane staining dominates while nuclei remain pale.That compartment does not match the nuclear assignment or the supported nucleoplasmic IF location (UniProt Q92754; HPA subcellular). Treat it as suspect and compare with a known positive section and detection controls before scoring it as TFAP2C (general IHC practice).
Cells outside the expected population stain strongly.Unexpected staining may reflect antibody cross-reactivity or endogenous detection activity (general IHC practice). Check cell identity and compartment, then use appropriate detection controls; HPA describes selected cell populations, not uniform staining throughout each tissue (HPA tissue IHC).
Color is spread diffusely across cells or the section.Diffuse background obscures the nuclear pattern expected for TFAP2C (UniProt Q92754; HPA tissue IHC). Review blocking, washing, antibody concentration, and chromogen development as general IHC variables; background alone is not evidence of TFAP2C expression (general IHC practice).
No nuclear signal appears in a known positive section.A blank result in skin hair follicles is discordant with HPA's High observation (HPA tissue IHC). Check section quality, antibody and detection performance, and the staining workflow before calling a test sample negative; an HPA positive is a reference pattern, not a guarantee for every specimen (HPA tissue IHC; general IHC practice).
💡Expected TFAP2C appearanceCall positive a clear nuclear signal in the relevant cells, strongest in skin hair follicles and medium in the listed breast, oral, and placental populations; dominant cytoplasmic color or widespread staining of unrelated cells is suspect (UniProt Q92754; HPA tissue IHC; general IHC practice).
How each factor affects the staining
Compartment and topologyTFAP2C is assigned to the nucleus and has no transmembrane segment (UniProt Q92754). Assess nuclear contrast against cytoplasm when interpreting chromogenic IHC; a membrane outline is not the expected target pattern (UniProt Q92754; general IHC practice).
Cell and tissue contextHPA reports High staining in hair follicles, Medium in breast glandular cells, oral squamous epithelial cells, and cytotrophoblasts, and Low staining in several other listed populations (HPA tissue IHC). Choose comparison fields by cell type, since a tissue name alone does not define every cell's expected result (HPA tissue IHC).
Reference negative populationsHPA reports Not detected in adipocytes, adrenal and appendix glandular cells, marrow hematopoietic cells, and other listed populations (HPA tissue IHC). These observations help assess unexpected staining; they do not prove absolute absence in every specimen or staining run (HPA tissue IHC).
Strength of tissue evidenceThe overall tissue profile is Enhanced, with medium consistency between staining and RNA expression (HPA tissue IHC). HPA also lists Enhanced IHC validation for HPA055179, CAB016061, and CAB016079; apply those labels only to the listed antibodies (HPA antibodies).
Isoforms and epitope informationUniProt lists 2 isoforms and a single annotated protein chain spanning residues 1–450, with no signal peptide or propeptide reported (UniProt Q92754). No supplied epitope mapping shows whether an IHC antibody detects both isoforms, so do not infer isoform-specific staining or a processing-dependent pattern (UniProt Q92754).
IF/ICC Q&A: where should fluorescence appear?HPA reports a mainly nucleoplasmic location with supported ICC-IF evidence (HPA subcellular). That supports a localisation comparison, but the IHC tissue intensities and IHC antibody ratings do not establish an IF/ICC staining protocol (HPA tissue IHC; HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Hair follicles in a positive section lack nuclear color.The result conflicts with HPA's High hair-follicle observation; tissue or staining-run failure is possible (HPA tissue IHC; general IHC practice).Confirm the follicle-containing field, then review the IHC-validated antibody, detection reagents, and run controls; assess retrieval and antibody dilution within the established IHC workflow (general IHC practice).
The section shows mainly cytoplasmic color.The dominant compartment conflicts with UniProt's nuclear location and HPA's nucleoplasmic IF assignment (UniProt Q92754; HPA subcellular).Compare nuclear counterstain with chromogen placement and review detection controls. Recheck antibody concentration and washing before interpreting cytoplasmic color as specific (general IHC practice).
Color appears in many unexpected cell populations.Cross-reactivity or endogenous detection activity can produce staining outside the selected populations reported by HPA (HPA tissue IHC; general IHC practice).Confirm cell identity on morphology and review reagent-only or other appropriate detection controls; compare the same run with an HPA-reported positive population (general IHC practice; HPA tissue IHC).
Broad haze makes nuclei hard to distinguish.Diffuse staining reduces contrast for the expected nuclear pattern (UniProt Q92754; general IHC practice).Check blocking, wash steps, antibody concentration, and chromogen development within the established workflow; score only distinct cellular signal after background is resolved (general IHC practice).
A low-staining tissue appears blank.HPA lists Low staining in some populations, including esophageal squamous epithelial cells and kidney tubular cells (HPA tissue IHC). Weak signal may fall below visual detection in a particular run (general IHC practice).Use a stronger HPA-reported positive population to check run performance before interpreting the low-staining field; avoid treating its blank appearance as a definitive absence claim (HPA tissue IHC; general IHC practice).
An HPA Not detected population shows nuclear color.The observation differs from the HPA reference, but HPA's tissue profile has only medium staining-to-RNA consistency (HPA tissue IHC).Check cell identity, background, and detection controls, then seek independent support before assigning that signal to TFAP2C; retain the discrepancy in the interpretation (HPA tissue IHC; general IHC practice).

Sample controls for TFAP2C IHC & IF

🧪Run skin first: hair follicle cells should show nuclear TFAP2C staining (HPA: High in hair follicles; UniProt Q92754: nucleus). Use adipose tissue as the negative comparator (HPA: Not detected in adipocytes); cells outside the hair follicles that lack nuclear signal provide an internal background comparison, but should not be assumed TFAP2C-negative without validation (standard IHC practice).
Positive control tissue: Skin (Hair follicles, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
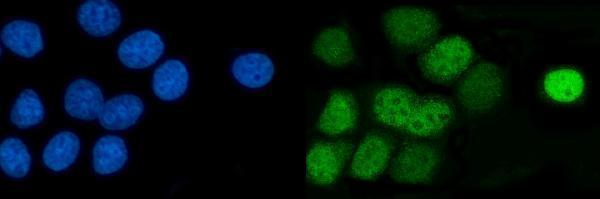
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TFAP2C in MCF-7, PC-3, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide and a species- and clonality-matched isotype control; validate specificity with a TFAP2C-knockout sample or a validated peptide block (standard IHC practice). In skin, check endogenous peroxidase and biotin background when using the caption’s biotin–SABC/DAB detection, and distinguish hair pigment from chromogen (catalog antibody A01558-2 caption; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected paraffin-section caption does not state a fixative (catalog antibody A01558-2 caption). That caption documents heat-mediated EDTA retrieval at pH 8.0, but does not establish that retrieval is required (catalog antibody A01558-2 caption). The supplied evidence does not establish whether frozen sections or IF are easier; skin hair pigment may complicate chromogenic scoring (standard IHC practice).

HPA tissue IHC evidence for TFAP2C

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Skin Hair follicles High Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →
Oral mucosa Squamous epithelial cells Medium Protein (IHC) HPA →
Placenta Cytotrophoblasts Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Appendix Glandular cells Not detected Protein (IHC) HPA →
Bone marrow Hematopoietic cells Not detected Protein (IHC) HPA →
Bronchus Respiratory epithelial cells Not detected Protein (IHC) HPA →
Section 3

Advanced TFAP2C IHC Tips

Use nuclear staining and cell-type controls to troubleshoot TFAP2C in paraffin-section IHC (UniProt Q92754; HPA tissue IHC).

What retrieval should I try first when TFAP2C nuclear staining is weak?
Start with heat-mediated EDTA pH 8.0 retrieval for paraffin sections (datasheet A01558-2). The catalog antibody detected TFAP2C in a paraffin-embedded human testis cancer section after this retrieval, with 2 μg/ml primary antibody overnight at 4°C (datasheet A01558-2). If staining is weak, compare retrieval heating durations on adjacent sections while keeping antibody concentration, detection and imaging conditions fixed (standard IHC practice). Assess nuclear staining in an expected positive cell population, such as placental cytotrophoblasts, alongside morphology and a no-primary control; diffuse tissue darkening alone does not establish successful retrieval (HPA tissue IHC; standard IHC practice).
Could fixation explain weak or patchy TFAP2C staining?
Target-specific fixation sensitivity is unknown: the selected paraffin-section caption does not state a fixative (datasheet A01558-2). Record the fixative, fixation duration and processing history for each specimen, then compare sections processed alike before attributing staining differences to TFAP2C biology (standard IHC practice). Keep EDTA pH 8.0 retrieval and the 2 μg/ml primary condition constant during that comparison (datasheet A01558-2; standard IHC practice). If nuclear staining varies with processing, inspect morphology and an expected positive cell population on each run; neither HPA tissue patterns nor TFAP2C topology or phosphorylation establishes a particular fixation effect (HPA tissue IHC; UniProt Q92754; standard IHC practice).
How should I evaluate cytoplasmic staining when I expect nuclear TFAP2C?
Score clearly resolved nuclei first: TFAP2C is annotated as nuclear, and its supported main location is the nucleoplasm (UniProt Q92754; HPA subcellular). The protein has no annotated transmembrane segment or signal peptide, so broad membranous staining is inconsistent with its recorded topology (UniProt Q92754). Compare cytoplasmic color with the no-primary control and inspect whether dense DAB, section folds or overlapping nuclei obscure compartment boundaries (standard IHC practice). Recheck localisation in an expected positive population, such as hair follicles with high reported staining, using the same EDTA pH 8.0 retrieval before interpreting a changed pattern (HPA tissue IHC; datasheet A01558-2; standard IHC practice).
Can isoforms or phosphorylation explain discordant TFAP2C staining?
TFAP2C has 2 annotated isoforms and reported phosphorylation at residues 252 and 434 (UniProt Q92754). The supplied antibody caption does not identify its epitope, so these annotations cannot establish which isoforms it detects or whether either modification affects staining (datasheet A01558-2; UniProt Q92754). Check the antibody's documented immunogen or epitope before comparing it with another clone, and retain the same EDTA pH 8.0 retrieval for that comparison (standard IHC practice; datasheet A01558-2). If clones disagree, compare staining within matched nuclei and include no-primary controls; a different pattern alone does not identify an isoform or phosphorylation state (standard IHC practice).
How can I check TFAP2C by multiplex IF when chromogenic IHC is ambiguous?
Treat IF as a separate assay: the supplied product evidence describes paraffin-section chromogenic IHC, while HPA lists TFAP2C ICC/IF images without a fixation or permeabilisation protocol here (datasheet A01558-2; HPA subcellular). Pair nuclear TFAP2C with a validated marker for the expected cell population, such as placental cytotrophoblasts, and use a nuclear counterstain to judge overlap (HPA tissue IHC; standard IF practice). Choose fluorophores after checking tissue autofluorescence in unstained sections and use single-color controls to assess bleed-through (standard IF practice). Because TFAP2C is nucleoplasmic and has no transmembrane segment, optimize permeabilisation for intracellular nuclear access rather than assuming a surface-facing epitope; the precise epitope is unreported (HPA subcellular; UniProt Q92754; datasheet A01558-2; standard IF practice).
What should I change when the entire section develops brown background?
Begin with a no-primary section to separate detection-system background from antibody-associated staining (standard IHC practice). The documented workflow used 10% goat serum blocking, a biotinylated secondary, a streptavidin–biotin complex and DAB, so inspect blocking and biotin-related background in that setup (datasheet A01558-2; standard IHC practice). Include a peroxidase block before DAB development and check for staining from endogenous enzyme activity; these are general chromogenic IHC controls, not TFAP2C-specific evidence (standard IHC practice). If background persists, compare shorter development and antibody titration around the documented 2 μg/ml condition while preserving interpretable nuclear staining in a positive control (datasheet A01558-2; standard IHC practice).
How should I score heterogeneous nuclear TFAP2C staining across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and nuclear positivity threshold before scoring, then apply identical segmentation and DAB thresholds across comparable sections (standard IHC practice). Report the percentage of positive nuclei and an H-score based on nuclear intensity, with the number of eligible cells stated for each region (standard IHC practice). If spatial distribution matters, report positive-nucleus density per mm² of viable, annotated tissue rather than total section area (standard IHC practice). Normalize comparisons to the same cell type and viable tissue area, and document retrieval with EDTA pH 8.0 and the run controls; HPA reports nuclear expression in only a subset of tissues (datasheet A01558-2; HPA tissue IHC; standard IHC practice).
How do I distinguish genuine TFAP2C positivity from staining artefacts?
Favor crisp nuclear signal in the expected cells: HPA reports high staining in skin hair follicles and medium staining in placental cytotrophoblasts and breast glandular cells (HPA tissue IHC). Treat broad cytoplasmic or membranous color cautiously because TFAP2C is nuclear and mainly nucleoplasmic, with no annotated transmembrane segment (UniProt Q92754; HPA subcellular). Exclude tissue edges, folds and necrotic regions from scoring, and inspect a no-primary section for DAB signal caused by endogenous enzyme or detection reagents (standard IHC practice). Compare a positive control with an HPA not-detected population, such as adipocytes, under the same EDTA pH 8.0 retrieval; an isolated brown deposit is insufficient to establish TFAP2C expression (HPA tissue IHC; datasheet A01558-2; standard IHC practice).
Boster reagents

Best TFAP2C / Transcription factor AP-2 gamma IHC Antibodies

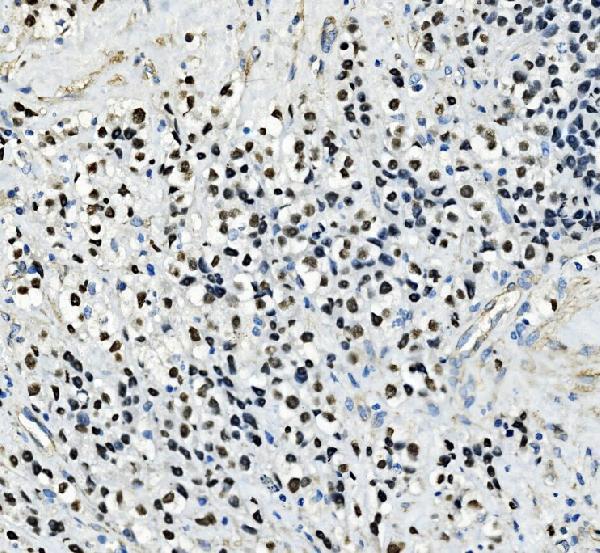
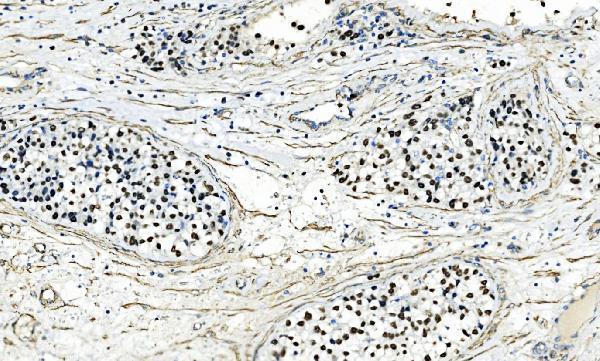
A01558-2 has IHC data from human testis cancer paraffin sections and IF data from MCF-7 cells (catalog image captions); human reactivity is listed (catalog: reactivity).

Real IHC data IHC analysis of AP2 Gamma/TFAP2C using anti-AP2 Gamma/TFAP2C antibody (A01558-2). AP2 Gamma/TFAP2C was detected in a paraffin-embedded section of human testis cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-AP2 Gamma/TFAP2C Antibody (A01558-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-AP2 gamma/TFAP2C Antibody ®
Cat # A01558-2

A01558-2 was demonstrated by IHC on a human testis cancer paraffin section (IHC image caption). The same SKU was demonstrated by IF in MCF-7 cells, with IHC, ICC and IF listed as applications (IF image caption; catalog: applications).

Which to pick: Choose A01558-2 for paraffin-section IHC because its own image caption documents that preparation; the fixative is unreported (IHC image caption). Choose A01558-2 for IF/ICC because IF in MCF-7 cells is pictured and ICC and IF are listed applications (IF image caption; catalog: applications). No cross-species option is documented: A01558-2 lists human reactivity only, and its clone is unspecified (catalog: reactivity and clone).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q92754 (AP2C_HUMAN, Transcription factor AP-2 gamma).
  2. Human Protein Atlas. TFAP2C tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. TFAP2C subcellular location (ICC-IF): Mainly localized to the nucleoplasm..
  4. Human Protein Atlas. TFAP2C antibody validation summary (4 antibodies).
  5. TFAP2C promotes stemness and chemotherapeutic resistance in colorectal cancer via inactivating hippo signaling pathway. Journal of experimental & clinical cancer research : CR 2018 — PMC5812206.
  6. High TFAP2C/low CD44 expression is associated with an increased rate of pathologic complete response following neoadjuvant chemotherapy in breast cancer. The Journal of surgical research 2013 — PMC3820425.
  7. iPSCs derived from infertile men carrying complex genetic abnormalities can generate primordial germ-like cells. Scientific reports 2022 — PMC9395518.
  8. Molecular and histopathological characterization of seminoma patients with highly elevated human chorionic gonadotropin levels in the serum. Virchows Archiv : an international journal of pathology 2024 — PMC11271319.
  9. PubMed PMID:8661133 — UniProt-cited evidence.
  10. PubMed PMID:9113991 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.