TFDP1 / Transcription factor Dp-1 · IHC design guide

Design Immunohistochemistry for TFDP1

Plan chromogenic TFDP1 IHC on paraffin sections using the catalog antibody’s documented workflow (datasheet M04204). Use the tissue staining profile to select positive controls and assess nuclear signal by cell type (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
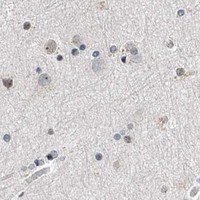
Immunohistochemistry protocol sheet for TFDP1 (IHC for TFDP1): expected localisation Predominantly nuclear staining in tissue (HPA tissue IHC), antibody M04204, validated IHC image, and IHC protocol steps
Printable TFDP1 IHC protocol sheet — expected localisation Predominantly nuclear staining in tissue (HPA tissue IHC), antibody M04204, controls and protocol steps. Open the full TFDP1 IHC guide →

TFDP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Predominantly nuclear staining in tissue (HPA tissue IHC)
Staining pattern Nuclear in hematopoietic and respiratory epithelial cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet M04204)
Positive control ⓘ Bone marrow+4 more · see all
Negative control ⓘ Liver+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat E2F1 binding can shift TFDP1 into nuclei (UniProt)
Regulation Expression varies by cell type (HPA tissue IHC)
Isoform / epitope 2 isoforms; epitope effects are unknown (UniProt)
Section 1

Recommended TFDP1 IHC & IF Protocols

Start with the catalog antibody’s IHC-P protocol (datasheet M04204), then compare published TFDP1 tissue IHC workflows (PMC2815550; PMC4686179).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet M04204)
FixationImage fixative and duration unreported (datasheet M04204); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet M04204); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet M04204)
Primary antibodyRabbit monoclonal (clone 24T75) anti-TFDP1, 1:50 (datasheet M04204)
Primary incubationOvernight at 4 °C (datasheet M04204)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet M04204)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTFDP1-positive staining in hematopoietic cells of bone marrow (HPA tissue IHC: High). HPA tissue profile: General nuclear expression. No signal in the no-primary control.
💡Decision noteTry EDTA pH 8.0 heat retrieval first (datasheet M04204). 10 mM citrate pH 6.5 is a published alternative for breast cancer microarrays (PMC2815550).
Section 2

What Is the Expected TFDP1 Staining Pattern?

TFDP1 should show predominantly nuclear staining in paraffin sections (HPA: general nuclear expression). High staining is reported in bone marrow hematopoietic cells, lymph node germinal center cells, and several epithelial populations (HPA tissue IHC). Its nuclear and cytoplasmic distribution can vary with E2F1 binding (UniProt Q14186: shuttling). TFDP1 has no transmembrane segment (UniProt Q14186: topology). The HPA tissue profile has Enhanced reliability, with medium consistency between staining and RNA expression (HPA tissue IHC).

What am I looking at on my slide?
Clear nuclear chromogen in bone marrow hematopoietic cells or lymph node germinal center cells.This matches reported High staining in those cell populations and the general nuclear pattern (HPA tissue IHC). Judge the named cells rather than the section as a whole; neighboring populations need not share the same intensity. An appropriately stained known-positive section supports interpretation of the run (general IHC practice).
Signal appears predominantly outside nuclei, with little or no nuclear staining in expected-positive cells.Review localisation before calling this positive: nuclear staining is the principal tissue pattern (HPA tissue IHC). Cytoplasmic signal alone is not definitive proof of an artefact because TFDP1 shuttles between compartments (UniProt Q14186: subcellular location), and cytosol is an additional ICC-IF location (HPA subcellular).
Strong signal appears in an unexpected cell population, including liver cholangiocytes.Cholangiocytes are reported as Not detected, while HPA lists high staining in selected other cell types (HPA tissue IHC). Check morphology and controls for cross-reactivity or endogenous detection activity (general IHC practice). A discrepant cell type warrants investigation; one slide cannot establish its cause.
Chromogen covers nuclei and surrounding tissue without clear cell boundaries.Diffuse background makes compartment and cell-type calls unreliable (general IHC practice). Compare the matched negative detection control, inspect wash and blocking steps, and assess whether the primary antibody concentration is excessive (general IHC practice). The HPA nuclear profile cannot validate a pattern obscured by background (HPA tissue IHC).
No discernible nuclear signal in a known-positive bone marrow or placenta section.HPA reports High staining in bone marrow hematopoietic cells and placental cytotrophoblasts (HPA tissue IHC). Confirm those cells are present and compare a concurrent positive control before interpreting the study tissue as negative (general IHC practice). HPA does not establish TFDP1-specific fixation sensitivity.
💡Expected TFDP1 appearanceA convincing positive is distinct nuclear staining in the named High populations, such as bone marrow hematopoietic cells (HPA tissue IHC); diffuse tissue-wide color or strong signal in HPA-undetected cholangiocytes calls for control review (general IHC practice; HPA tissue IHC).
How each factor affects the staining
Cell-type selectionUse the specifically reported populations when choosing interpretive anchors: duodenal glandular cells, esophageal squamous epithelial cells, and placental cytotrophoblasts are High (HPA tissue IHC). Liver cholangiocytes, ovarian follicle cells, and parathyroid glandular cells are Not detected (HPA tissue IHC). These are cell-level observations, not whole-organ rules.
Compartment and cell stateHPA describes general nuclear tissue expression and mainly nucleoplasmic ICC-IF localisation, with additional nuclear membrane and cytosol localisation (HPA tissue IHC; HPA subcellular). TFDP1 moves into the nucleus on heterodimerization with E2F1 (UniProt Q14186: subcellular location). Interpret weak cytoplasmic color alongside nuclear signal and controls.
Antibody evidenceCAB033605 has an Enhanced IHC validation status (HPA antibodies). Three other listed antibodies have ICC support or approval but no supplied IHC status (HPA antibodies). The tissue profile itself is Enhanced with medium staining–RNA consistency (HPA tissue IHC); neither label guarantees every specimen will reproduce a listed intensity.
Isoforms and assay setupUniProt lists 2 TFDP1 isoforms and a single annotated chain spanning residues 1–410 (UniProt Q14186: isoforms; processing). No antibody epitope or isoform coverage is supplied, so an isoform-specific staining prediction is unsupported. Retrieval, primary dilution, and detection conditions must come from the chosen IHC protocol, not this localisation record.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected-positive cells lack staining.A failed staining run or misidentified cells is possible (general IHC practice); those cells are reported High in the cited tissues (HPA tissue IHC).Verify cell identity and the concurrent positive control; review the chosen IHC antibody's stated protocol and detection steps (general IHC practice).
Signal is cytoplasmic with little nuclear definition.Background is possible (general IHC practice), although cytosol is an additional reported location (HPA subcellular).Compare nuclear counterstain and negative control, then score any true nuclear signal separately (general IHC practice; HPA tissue IHC: general nuclear expression).
Cholangiocytes or ovarian follicle cells stain strongly.This conflicts with their Not detected HPA observations; nonspecific staining or endogenous detection activity is possible (HPA tissue IHC; general IHC practice).Confirm the cell type and inspect primary-omission and detection controls before assigning TFDP1 positivity (general IHC practice).
The entire section has diffuse brown haze.Insufficient washing, blocking, or an overconcentrated reagent can raise chromogenic background (general IHC practice).Review washes, blocking, and reagent concentration against the selected IHC protocol; repeat with matched controls (general IHC practice).
Different slides show different nuclear intensity.The sampled cell populations may differ; HPA reports High and Low staining in distinct populations (HPA tissue IHC).Compare the same cell type across slides and check a shared positive control before attributing the difference to TFDP1 abundance (general IHC practice).
IF images suggest a pattern that differs from paraffin IHC.HPA ICC-IF includes nucleoplasm, nuclear membrane, and cytosol, while its tissue IHC profile reports general nuclear expression (HPA subcellular; HPA tissue IHC).Interpret each preparation using its own localisation evidence and controls; use the separate IF/ICC guide for its assay workflow (general IHC/IF practice).

Sample controls for TFDP1 IHC & IF

🧪Run bone marrow first; hematopoietic cells should stain (HPA: bone marrow hematopoietic cells High). Use parathyroid gland as the negative tissue (HPA: parathyroid gland glandular cells Not detected); unstained cells on the bone marrow slide can show background, but HPA does not identify a confirmed negative cell type within that slide.
Positive control tissue: Bone marrow (Hematopoietic cells, HPA High)
Negative control tissue: Liver (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TFDP1 in HEK293, MCF-7, U2OS, A-431, U-251MG, OE19, with annotated localisation: Nucleoplasm (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only section and an isotype control matched to the rabbit primary antibody’s host and clonality where known (caption: rabbit anti-DP1 antibody; clonality unreported). Confirm specificity with TFDP1 knockout material or a validated peptide-block control, and suppress endogenous peroxidase before HRP/DAB detection in bone marrow (HPA: bone marrow hematopoietic cells High; caption: HRP/DAB detection).
⚠️Feasibility: Paraffin-section IHC is demonstrated with heat retrieval in EDTA at pH 8.0, followed by primary antibody at 1:50 overnight at 4°C (M04204 tissue-IHC caption). A target-specific fixation window or fixation effect is unreported, and the exact selected-SKU caption does not report a fixative (M04204 tissue-IHC caption); the retrieval step shows the documented procedure, not a proven retrieval dependency. No supplied comparison establishes whether frozen sections or IF are easier; in bone marrow, endogenous peroxidase can confound chromogenic staining unless blocked (HPA: bone marrow hematopoietic cells High; caption: HRP/DAB detection).

HPA tissue IHC evidence for TFDP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Esophagus Squamous epithelial cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Ovary Follicle cells Not detected Protein (IHC) HPA →
Parathyroid gland Glandular cells Not detected Protein (IHC) HPA →
Section 3

Advanced TFDP1 IHC Tips

Troubleshoot TFDP1 staining in paraffin sections by checking retrieval, nuclear localisation, controls and scoring before interpreting differences between samples.

What should I change when TFDP1 staining is weak in paraffin sections?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections stained with M04204 (datasheet M04204). The documented breast cancer section used that retrieval, 1:50 primary antibody overnight at 4°C, and DAB detection (datasheet M04204). If staining remains weak, compare retrieval duration or heating conditions on adjacent sections while keeping antibody and detection conditions constant (standard IHC practice). Check whether a control section shows nuclear staining before increasing primary antibody concentration; the tissue IHC profile is generally nuclear (HPA tissue IHC). Record the heating conditions used, because the supplied caption does not specify a retrieval time (datasheet M04204).
How can I assess whether fixation is reducing TFDP1 staining?
Target-specific sensitivity of TFDP1 to fixation is unknown from the supplied evidence; the selected paraffin-section caption does not state a fixative (datasheet M04204). Record fixative, fixation duration and processing history for each block before comparing staining intensity (standard IHC practice). Where matched material is available, stain sections processed under different known fixation conditions in the same run, using the documented EDTA pH 8.0 retrieval and 1:50 primary dilution as a starting point (datasheet M04204; standard IHC practice). Include a control section with an interpretable nuclear pattern (HPA tissue IHC). Avoid assigning a weak result to fixation alone when retrieval, antibody exposure and detection also differ (standard IHC practice).
Should TFDP1 staining be nuclear or cytoplasmic in IHC?
Prioritise interpretable nuclear staining: the tissue IHC profile reports general nuclear expression, and the approved subcellular location is nucleoplasm (HPA tissue IHC; HPA subcellular). Cytoplasmic signal is biologically possible because TFDP1 shuttles between cytoplasm and nucleus and enters the nucleus upon E2F1 heterodimerisation (UniProt Q14186 localisation). Additional nuclear membrane and cytosol localisation has also been reported in cell imaging (HPA subcellular). For chromogenic sections, score nuclear and cytoplasmic staining separately rather than combining them into one intensity value (standard IHC practice). Treat diffuse staining that obscures cellular boundaries cautiously and compare it with a negative reagent control (standard IHC practice).
Could isoforms or an inaccessible epitope explain inconsistent staining?
TFDP1 has 2 annotated isoforms, but the supplied antibody caption does not map the recognised epitope or establish isoform coverage (UniProt Q14186 isoforms; datasheet M04204). Its annotated modifications include N6-acetyllysine at residue 3 and phosphoserine at residue 23; their effect on this antibody is unknown (UniProt Q14186 modified residues; datasheet M04204). Compare staining after the documented EDTA pH 8.0 retrieval before attributing section-to-section differences to an isoform (datasheet M04204; standard IHC practice). If epitope identity is needed for interpretation, obtain antibody-specific mapping or validate with an independent reagent against a known region (standard IHC practice). Do not claim isoform-specific staining from this caption alone (datasheet M04204).
How should I investigate TFDP1 localisation with multiplex IF?
Use IF as a complementary localisation check: the IHC tissue profile is generally nuclear, while cell imaging places TFDP1 mainly in the nucleoplasm with additional nuclear membrane and cytosol signal (HPA tissue IHC; HPA subcellular). Pair TFDP1 with a marker identifying the cell population being evaluated and a nuclear counterstain, then inspect each channel separately before assessing overlap (standard IF practice). Choose fluorophores in channels with low tissue autofluorescence and include single-stain controls to assess bleed-through (standard IF practice). TFDP1 has no transmembrane segment, so intracellular and nuclear access matters; select permeabilisation accordingly, while recognising that this antibody’s epitope location is unspecified (UniProt Q14186 topology; datasheet M04204; standard IF practice).
How can I distinguish TFDP1 signal from chromogenic background?
The documented paraffin-section example used 10% goat serum blocking, a 1:50 primary dilution, peroxidase-linked detection and DAB chromogen (datasheet M04204). For excess brown signal, inspect a section without primary antibody and include an appropriate endogenous peroxidase block as part of the general chromogenic workflow (standard IHC practice). Compare background in tissue edges, damaged regions and areas lacking intact nuclei before changing the antibody dilution (standard IHC practice). Increase washing or adjust blocking and detection conditions one variable at a time, then compare sections developed for the same duration (standard IHC practice). Preserve a nuclear positive control so reduced background is not mistaken for lost target staining (HPA tissue IHC; standard IHC practice).
What is a defensible way to score TFDP1 IHC across samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and region before scoring, then measure nuclear TFDP1 because the reported tissue IHC pattern is generally nuclear (HPA tissue IHC; standard IHC practice). Report either the percentage of positive nuclei or a nuclear H-score on a 0–300 scale, with staining thresholds fixed across the comparison (standard IHC practice). Normalise positive counts to the number of evaluable cells in the same compartment; use density per mm² only when tissue area is the intended denominator (standard IHC practice). Record cytoplasmic staining separately because TFDP1 can shuttle between cytoplasm and nucleus (UniProt Q14186 localisation). Exclude folds, necrosis and poorly preserved areas using the same criteria for every section (standard IHC practice).
When is apparent TFDP1 positivity credible rather than artefactual?
Credible TFDP1 staining should follow intact cells and include a coherent nuclear component, consistent with the general nuclear tissue pattern and approved nucleoplasmic location (HPA tissue IHC; HPA subcellular). Evaluate the expected cell population against documented examples, such as high staining in bone marrow hematopoietic cells and bronchial respiratory epithelial cells (HPA tissue IHC). Cytoplasmic signal can occur, but isolated diffuse brown staining without interpretable nuclei deserves further control testing (UniProt Q14186 localisation; standard IHC practice). Discount staining concentrated at section edges or necrotic areas, and check a no-primary control for endogenous enzyme or detection background (standard IHC practice). Interpret differences only after comparing similarly processed sections and consistent scoring compartments (standard IHC practice).
Boster reagents

Best TFDP1 / Transcription factor Dp-1 IHC Antibodies

M04204 has IHC images from human paraffin sections of breast cancer and colorectal adenocarcinoma (catalog IHC captions); mouse and rat reactivity is listed, but no IF image is supplied (catalog reactivity; catalog IF images).

Real IHC data IHC analysis of DP1 using anti-DP1 antibody (M04204). DP1 was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-DP1 Antibody (M04204) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-DP1 Rabbit Monoclonal Antibody
Cat # M04204

M04204 is the only card and shows IHC staining in human paraffin sections of breast cancer and colorectal adenocarcinoma (catalog IHC captions). Its listed applications include IHC, flow cytometry and WB, with human, mouse and rat reactivity (catalog applications; catalog reactivity).

Which to pick: Choose M04204 for tissue IHC: it is a rabbit monoclonal with human paraffin-section images using EDTA retrieval at pH 8.0 and a 1:50 primary dilution (catalog host and clone; M04204 IHC captions). The captions do not report the fixative (M04204 IHC captions). For IF/ICC, no listed SKU has IF/ICC validation or an IF image; for mouse or rat IHC, M04204 lists reactivity with those species, but its supplied IHC images show human tissue only (catalog applications; catalog IF images; catalog reactivity; M04204 IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q14186 (TFDP1_HUMAN, Transcription factor Dp-1).
  2. Human Protein Atlas. TFDP1 tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. TFDP1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm. In addition localized to the nuclear membrane and cytosol..
  4. Human Protein Atlas. TFDP1 antibody validation summary (4 antibodies).
  5. Comprehensive characterization of the DNA amplification at 13q34 in human breast cancer reveals TFDP1 and CUL4A as likely candidate target genes. Breast cancer research : BCR 2009 — PMC2815550.
  6. Single cell deciphering of progression trajectories of the tumor ecosystem in head and neck cancer. Nature communications 2024 — PMC10959966.
  7. CKAP2 Regulated by TFDP1 Promotes Metastasis and Proliferation of Colorectal Cancer through Affecting the Tumor Microenvironment. Journal of microbiology and biotechnology 2024 — PMC11637825.
  8. Recurrent Amplification at 13q34 Targets at CUL4A, IRS2, and TFDP1 As an Independent Adverse Prognosticator in Intrahepatic Cholangiocarcinoma. PloS one 2015 — PMC4686179.
  9. PubMed PMID:8405995 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:15057823 — UniProt-cited evidence.