TFG / Protein TFG · IHC design guide

Design Immunohistochemistry for TFG

Plan chromogenic TFG IHC in paraffin sections around the cytoplasmic staining reported in most tissues (HPA tissue IHC). Colon glandular cells and kidney tubule cells show high staining, while adipocytes were not detected in the HPA survey (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TFG (IHC for TFG): expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A02870-3, validated IHC image, and IHC protocol steps
Printable TFG IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC), antibody A02870-3, controls and protocol steps. Open the full TFG IHC guide →

TFG Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in most tissues (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02870-3)
Positive control ⓘ Appendix+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A02870-3)
Caveat Staining has medium consistency with RNA data (HPA tissue IHC)
Regulation Ubiquitous; no inducer specified (UniProt)
Isoform / epitope 4 isoforms; epitope coverage needs validation (UniProt)
Section 1

Recommended TFG IHC & IF Protocols

The catalog antibody’s paraffin-section protocol uses EDTA retrieval (datasheet: A02870-3). Two published studies provide free-floating rat-section IHC protocols (PMC3317492; PMC3317498).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human breast cancer tissue; fixative not specified (datasheet A02870-3)
FixationImage fixative and duration unreported (datasheet A02870-3); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02870-3); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02870-3)
Primary antibodyRabbit anti-TFG, 2-5 μg/ml (datasheet A02870-3)
Primary incubationOvernight at 4 °C (datasheet A02870-3)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A02870-3)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTFG-positive staining in glandular cells of appendix (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in most tissues. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet: A02870-3). The published protocols used free-floating sections (PMC3317492; PMC3317498).
Section 2

What Is the Expected TFG Staining Pattern?

TFG is expected in the cytoplasm of many tissue cell types, with high IHC staining reported in selected glandular, tubular, glial, exocrine and trophoblastic cells (HPA tissue IHC). Its ER exit site localization and lack of a transmembrane segment support an intracellular pattern (UniProt Q92734). HPA rates tissue IHC reliability Approved, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC).

What am I looking at on my slide?
Cytoplasmic staining in appendix or colon glandular cells, kidney tubule cells, or pancreatic exocrine cells.This fits the reported High staining in those cell types (HPA tissue IHC). Assess staining in the named cells, since intensity elsewhere in the same section is not specified by those entries (HPA tissue IHC).
Predominantly nuclear staining, with little cytoplasmic signal.That compartment conflicts with the reported cytoplasmic tissue pattern (HPA tissue IHC) and ER exit site localization (UniProt Q92734). Treat it as a possible staining artefact; review controls before assigning it to TFG (general IHC practice).
Strong staining in adipocytes, esophageal squamous cells, or skeletal myocytes.Those specified cell types were Not detected in HPA tissue IHC (HPA tissue IHC). Check cell identification and controls; cross-reactivity or endogenous detection activity are possible explanations, not conclusions from the image alone (general IHC practice).
Broad, featureless chromogen over cells and surrounding tissue.A diffuse background makes the expected cytoplasmic distribution hard to judge (HPA tissue IHC). Review the no-primary control and detection background, then reassess whether individual cells show a discernible intracellular pattern (general IHC practice).
No signal in appendix glandular cells or kidney tubule cells.Both are reported High cell populations (HPA tissue IHC). Confirm that the relevant cells are present and that the positive control worked before interpreting a negative result; HPA's tissue rating remains pending external verification (HPA tissue IHC; general IHC practice).
💡Expected TFG appearanceCall a result consistent with TFG when High cytoplasmic staining is seen in an HPA high cell population, such as colon glandular cells or kidney tubule cells; predominantly nuclear signal or strong staining confined to an HPA not-detected cell population warrants control review (HPA tissue IHC; UniProt Q92734; general IHC practice).
How each factor affects the staining
Tissue and cell selection (HPA tissue IHC)HPA reports cytoplasmic expression in most tissues but differing levels by cell type: colon glandular and kidney tubule cells are High, while adipocytes are Not detected (HPA tissue IHC). Compare the identified cells, not whole-section darkness (general IHC practice).
Subcellular resolution (UniProt Q92734; HPA subcellular)UniProt places TFG at ER exit sites; HPA ICC-IF calls vesicles the approved main location and cytosol an uncertain additional location (UniProt Q92734; HPA subcellular). Chromogenic IHC may show cytoplasmic staining without resolving those structures (general IHC practice).
Topology and processing (UniProt Q92734)TFG has no transmembrane segment or signal peptide, and its annotated protein chain spans residues 1–400 (UniProt Q92734). These annotations support an intracellular reading; they do not establish how fixation or antigen retrieval affects staining (UniProt Q92734).
Isoform and epitope coverage (UniProt Q92734)Four isoforms are listed (UniProt Q92734). The supplied sources do not map an IHC antibody epitope or establish isoform-specific staining, so a positive cell should not be assigned to one isoform from its staining pattern alone (UniProt Q92734).
Evidence strength by application (HPA antibodies; HPA tissue IHC)HPA019473 has Approved IHC status; both listed antibodies have Enhanced ICC status, while HPA052206 has no stated IHC status (HPA antibodies). Tissue IHC is Approved with medium RNA concordance and external verification pending (HPA tissue IHC).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in a selected high-positive cell population (HPA tissue IHC).The target cells may be absent from the section, or the staining run may have failed (general IHC practice).Check cell identity and the run's positive control; review retrieval, primary-antibody and detection steps using the assay's instructions (general IHC practice). No TFG-specific retrieval condition is supplied.
Predominantly nuclear signal despite a weak cytoplasmic pattern (HPA tissue IHC).Nuclear dominance is inconsistent with the reported cytoplasmic IHC pattern and ER exit site localization (HPA tissue IHC; UniProt Q92734).Compare with a no-primary control and examine whether detection background obscures cytoplasmic signal (general IHC practice).
Strong color in adipocytes or skeletal myocytes (HPA tissue IHC).These cell types are Not detected in HPA tissue IHC; misidentified cells, cross-reactivity or detection background may explain the result (HPA tissue IHC; general IHC practice).Recheck morphology and compare with no-primary and appropriate positive controls before calling the signal TFG-specific (general IHC practice).
Diffuse color obscures cellular boundaries (general IHC practice).Background from blocking or the detection system can obscure a cellular pattern (general IHC practice).Inspect the no-primary control and review blocking, washes and endogenous enzyme quenching where relevant to the chromogen system (general IHC practice).
Punctate IF appears to disagree with broad cytoplasmic IHC (HPA tissue IHC; HPA subcellular).HPA calls vesicles the approved main ICC-IF location, while tissue IHC is summarized as cytoplasmic (HPA subcellular; HPA tissue IHC).Interpret each image at its own resolution. Use the separate IF/ICC guide for IF assay decisions; this section provides no IF protocol (general microscopy practice).
A low or absent result conflicts with an expected positive tissue (HPA tissue IHC).HPA levels apply to specified cell populations, and its IHC profile has medium consistency with RNA data and awaits external verification (HPA tissue IHC).Score the named cell population, check a run-level positive control, and document the discrepancy without inferring a TFG-specific fixation effect (HPA tissue IHC; general IHC practice).

Sample controls for TFG IHC & IF

🧪Run appendix first and confirm staining in its glandular cells (HPA: High in appendix glandular cells); run adipose tissue as the negative comparator, assessing adipocytes (HPA: Not detected in adipocytes). On the appendix slide, unstained nonglandular areas can serve as background references, but should not be assumed to be TFG-negative cells (UniProt: ubiquitous tissue specificity).
Positive control tissue: Appendix (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
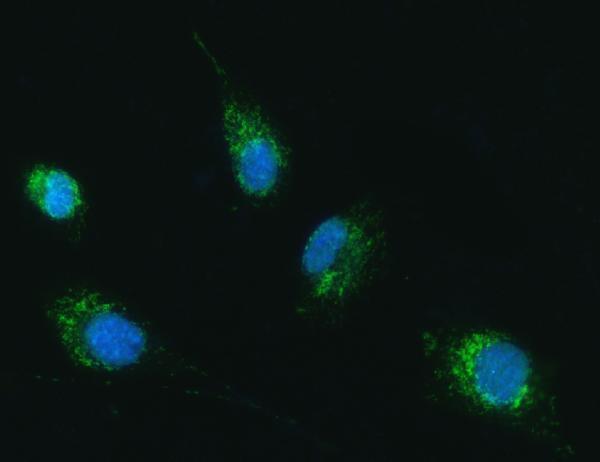
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TFG in A-431, U-251MG, U2OS, NIH 3T3, with annotated localisation: Vesicles (approved) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control and a concentration-matched rabbit immunoglobulin isotype control (selected-SKU tissue-IHC caption: rabbit primary antibody); use TFG knockout tissue or cells, if available, as a biological negative. For chromogenic appendix sections, quench endogenous peroxidase and assess background before interpreting DAB staining (standard IHC practice).
⚠️Feasibility: No target-specific fixation window or fixation effect is reported in the supplied evidence, and the fixative is unreported for the exact A02870-3 tissue-IHC caption. That paraffin-section caption provides a starting protocol with heat retrieval in EDTA at pH 8.0 and primary antibody at 2 μg/ml overnight at 4°C (selected-SKU tissue-IHC caption). The supplied evidence does not establish that frozen sections or IF are easier; assess glandular luminal deposits and endogenous peroxidase background when scoring appendix DAB staining (standard IHC practice).

HPA tissue IHC evidence for TFG

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Appendix Glandular cells High Protein (IHC) HPA →
Cerebral cortex Glial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Cervix Glandular cells Not detected Protein (IHC) HPA →
Esophagus Squamous epithelial cells Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Lung Alveolar cells Not detected Protein (IHC) HPA →
Section 3

Advanced TFG IHC Tips

Use the catalog antibody’s paraffin section result as a starting point, then assess staining against TFG localisation and tissue expression evidence.

How should I optimise antigen retrieval when TFG staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A02870-3). The catalog antibody produced staining in a human breast cancer paraffin section with this retrieval method (caption A02870-3). Keep retrieval conditions identical across test and control sections while checking whether tissue morphology remains intact (standard IHC practice). If staining is weak, vary heating time in a small series before changing buffer, and process every section through the same detection steps (standard IHC practice). The caption reports 2 μg/ml primary antibody overnight at 4°C, which provides a documented starting condition for that comparison (caption A02870-3).
Could fixation explain inconsistent TFG staining between paraffin blocks?
TFG specific sensitivity to fixation is unknown from the supplied evidence; the selected paraffin section caption does not state a fixative (caption A02870-3). Record the fixative and processing history for each block before comparing staining intensities (standard IHC practice). Compare adjacent sections using the same EDTA pH 8.0 retrieval and detection conditions, then assess morphology alongside signal (datasheet A02870-3; standard IHC practice). Include a section from a consistently staining block in each run to detect variation between staining runs (standard IHC practice). Treat a difference between blocks as a processing hypothesis until matched material or another control supports it (standard IHC practice).
Where should convincing TFG staining appear in an IHC section?
Expect predominantly cytoplasmic staining at tissue scale, because that is the reported pattern across most tissues (HPA tissue IHC). TFG localises to endoplasmic reticulum exit sites, also called transitional endoplasmic reticulum, so a perinuclear or punctate cytoplasmic pattern can be biologically plausible (UniProt Q92734 localisation). Cell imaging also reports vesicles as the approved main location and cytosol as an uncertain additional location (HPA subcellular). Examine staining at a consistent magnification and compare the same cell compartment across sections (standard IHC practice). Predominantly nuclear staining deserves independent validation before being scored as TFG, since the supplied localisation records support cytoplasmic compartments (UniProt Q92734 localisation; HPA subcellular).
Could TFG isoforms or epitope accessibility alter the IHC pattern?
TFG has 4 listed isoforms, but the supplied catalog result does not map this antibody’s epitope to an isoform (UniProt Q92734 isoforms; caption A02870-3). Consequently, a difference in staining cannot by itself establish isoform selective recognition (standard IHC interpretation). The protein has a PB1 domain at residues 10–91 and reported modified residues, including phosphoserines at 50 and 197 (UniProt Q92734 domains and modified residues). These features identify questions for epitope mapping; they do not demonstrate that retrieval exposes or masks this antibody’s epitope (standard IHC interpretation). Check documented epitope information and compare staining with an independently validated antibody if isoform specificity matters (standard IHC practice).
How can IF help resolve ambiguous TFG staining in tissue?
Use IF as a separate localisation check: multiplex TFG with a marker for the cell type being assessed, such as a glandular epithelial marker when evaluating colon glands (HPA tissue IHC; standard IF practice). Choose spectrally separated fluorophores and inspect an unstained section for autofluorescence before assigning faint puncta to TFG (standard IF practice). TFG has no transmembrane segment and is reported at ER exit sites, but the antibody epitope’s accessibility is unreported (UniProt Q92734 topology and localisation; caption A02870-3). Compare mild permeabilisation conditions with an appropriate control so cytoplasmic epitopes can be reached without losing cellular structure (standard IF practice). Do not assume the IHC concentration of 2 μg/ml is an IF dilution recommendation (caption A02870-3; standard IF practice).
What should I check when TFG DAB staining is widespread or muddy?
The documented paraffin section procedure used 10% goat serum blocking, peroxidase linked detection and DAB (caption A02870-3). Include a no primary control to assess signal from detection reagents, and apply a peroxidase block when endogenous enzyme activity could contribute to DAB staining (standard IHC practice). Compare background in areas expected to stain and areas reported as undetected, while accounting for cell type differences within each tissue (HPA tissue IHC; standard IHC practice). Check whether dark edges, folds or damaged regions explain the apparent distribution before changing antibody concentration (standard IHC practice). If background persists, titrate the primary around the documented 2 μg/ml condition while keeping retrieval and development consistent (caption A02870-3; standard IHC practice).
How should I score TFG IHC across different tissue regions? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and cytoplasmic compartment before scoring, because reported TFG staining varies by cell type (HPA tissue IHC). For a consistent cell population, record the percentage of positive cells and intensity grades, then calculate an H-score from 0–300 if that scoring system suits the study (standard IHC practice). For spatial comparisons, count positive cells per mm² of viable tissue and report the sampled area (standard IHC practice). Normalise comparisons to the same cell type, viable area, staining run and image acquisition settings (standard IHC practice). Keep thresholds fixed and review borderline calls against controls, especially where HPA reports low staining (HPA tissue IHC; standard IHC practice).
How do I distinguish credible TFG staining from an artefact?
Credible staining should fit a cytoplasmic distribution and the relevant cell type: HPA reports high signal in colon glandular cells and kidney tubule cells (HPA tissue IHC). TFG’s ER exit site localisation makes a cytoplasmic punctate component plausible, while strongly nuclear only staining needs additional evidence (UniProt Q92734 localisation; HPA subcellular). Check edge staining, necrotic regions and no primary controls before attributing DAB deposits to TFG (standard IHC practice). Consider endogenous peroxidase activity when staining appears in unexpected structures despite the antibody control (standard IHC practice). HPA rates its tissue staining “Approved” with medium agreement between staining and RNA data pending external verification, so corroborate unexpected patterns independently (HPA tissue IHC).
Boster reagents

Best TFG / Protein TFG IHC Antibodies

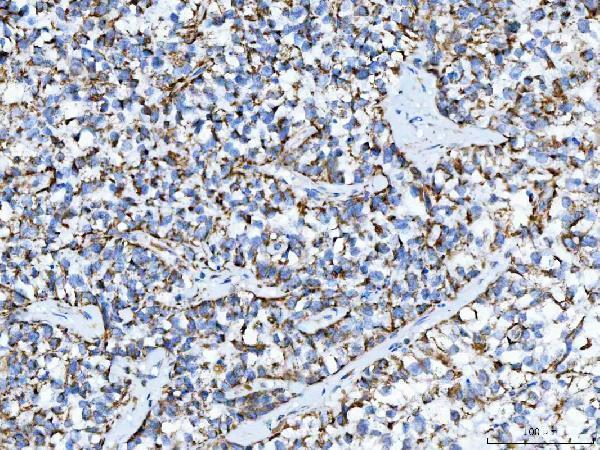
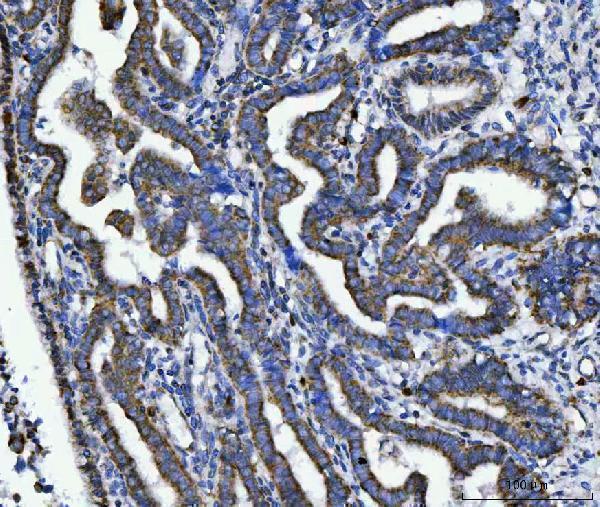
A02870-3 has IHC images from human paraffin sections and IF images from human cells and paraffin sections (catalog image captions). Both antibodies list human, mouse and rat reactivity (catalog reactivity).

Real IHC data IHC analysis of TRK fused gene/TFG using anti-TRK fused gene/TFG antibody (A02870-3). TRK fused gene/TFG was detected in a paraffin-embedded section of human breast cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-TRK fused gene/TFG Antibody (A02870-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-TRK fused gene/TFG Antibody ®
Cat # A02870-3

A02870-3 has IHC images from human breast, cervical and liver cancer and lung paraffin sections, plus IF images from U87 cells and human colon cancer paraffin sections (catalog image captions). M02870 lists IHC and ICC/IF applications and human, mouse and rat reactivity, but has no IHC or IF image captions (catalog applications, reactivity and image captions).

Which to pick: For tissue IHC, choose A02870-3: its human paraffin-section captions document EDTA retrieval at pH 8.0 and primary antibody at 2 μg/ml; the fixative is unreported (A02870-3 IHC image captions). For IF/ICC, A02870-3 has images from U87 cells and a human colon cancer paraffin section, while M02870 is a rabbit monoclonal listed for ICC/IF without an image caption (catalog IF image captions and M02870 host, clone and applications). For work across species, both list human, mouse and rat reactivity, but A02870-3 lists paraffin IHC for human and rat and IF for human; validate staining in each intended sample (catalog reactivity and A02870-3 dilution_raw).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q92734 (TFG_HUMAN, Protein TFG).
  2. Human Protein Atlas. TFG tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. TFG subcellular location (ICC-IF): Mainly localized to vesicles. In addition localized to the cytosol..
  4. Human Protein Atlas. TFG antibody validation summary (2 antibodies).
  5. Immunohistochemical Mapping of TRK-Fused Gene Products in the Rat Brainstem. Acta histochemica et cytochemica 2012 — PMC3317492.
  6. Expression and Localization of TRK-Fused Gene Products in the Rat Brain and Retina. Acta histochemica et cytochemica 2012 — PMC3317498.
  7. TRK-fused Gene Protein Localization Is Prominent in Serotonergic and Noradrenergic Cell Groups, and Some Lower Motor Neurons in the Corticospinal Tract of the Rat Brainstem. Acta histochemica et cytochemica 2018 — PMC6066645.
  8. Cell type-specific gene therapy confers protection against motor neuron disease caused by a TFG variant. Proceedings of the National Academy of Sciences of the United States of America 2024 — PMC11588061.
  9. PubMed PMID:9169129 — UniProt-cited evidence.
  10. PubMed PMID:22883144 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.