This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan TLE2 chromogenic IHC around the nuclear tissue pattern, with cerebellar Purkinje cells as a strong positive reference (HPA tissue IHC). This guide covers fixation, antibody dilution, detection and interpretation, including the reported off-target staining concern (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear staining in tissues (HPA tissue IHC) | |
| Staining pattern | Nuclear staining across tissues, strongest in Purkinje cells (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, heat-mediated (datasheet A10582-1) | |
| Positive control | Cerebellum+4 more · see all | |
| Negative control | Adipose tissue+1 more · see all |
| Fixation | Keep paraffin-section fixation consistent. (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target staining observed (HPA tissue IHC) | |
| Regulation | Tissue-dependent abundance (HPA tissue IHC) | |
| Isoform / epitope | 3 isoforms; verify epitope coverage for each (UniProt) |
The catalog antibody protocol specifies heat retrieval in Tris-EDTA at pH 9.0 (datasheet A10582-1). The published IHC option uses paraffin-embedded xenograft sections (PMC5036407).
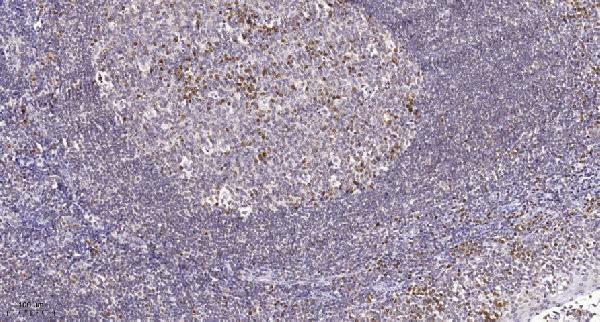
| Sample | Paraffin-embedded human tonsil tissue; fixative not specified (datasheet A10582-1) |
| Fixation | Image fixative and duration unreported (datasheet A10582-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: Tris-EDTA pH 9.0 (datasheet A10582-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TLE2, 1:100-1:300 (datasheet A10582-1) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TLE2-positive staining in purkinje cells of cerebellum (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in all tissues, most abundant in cerebellum. No signal in the no-primary control. |
TLE2 is a nuclear transcriptional corepressor with no transmembrane segment (UniProt Q04725). In paraffin-section IHC, expect nuclear staining across tissues, strongest in cerebellar Purkinje cells (HPA: nuclear expression in all tissues; Purkinje cells High). Treat the pattern as a guide, not absolute specificity: HPA rates its tissue IHC reliability Enhanced but reports medium staining–RNA consistency and presumed off-target binding that was disregarded (HPA: reliability description).
| Strong, defined Purkinje-cell nuclei in cerebellum; some other nuclei stain less strongly. | This fits the most abundant reported tissue pattern (HPA: Purkinje cells High; nuclear expression in all tissues). Compare intensity within the same section before interpreting weaker neighboring cells as negative; HPA reports medium staining in several other specified cell types (HPA: tissue IHC). |
| The apparent signal is mainly cytoplasmic or membranous, with little nuclear staining. | Recheck localization and controls before calling this TLE2. A predominantly nonnuclear IHC pattern conflicts with the expected nucleus (UniProt Q04725: Nucleus; HPA: nuclear tissue expression). It could reflect background or off-target staining; appearance alone cannot identify its cause (general IHC interpretation). |
| Adipocytes or chondrocytes show convincing chromogenic staining. | These specific cell types were reported as Not detected (HPA: adipose-tissue adipocytes; soft-tissue chondrocytes). Review the negative control and whether the deposit lies in cells. Off-target binding or endogenous detection activity is possible (general IHC interpretation); the HPA result does not make every cell in those tissues negative. |
| Color spreads diffusely through tissue, obscuring cell boundaries and nuclei. | This is difficult to score as specific nuclear staining (HPA: nuclear tissue pattern). Diffuse color can arise from nonspecific detection or excess chromogen development (general chromogenic IHC practice). Compare a matched negative control and the nuclear counterstain before assigning TLE2 positivity. |
| Purkinje-cell nuclei show no detectable staining in an otherwise interpretable cerebellar section. | A missed expected positive warrants a run check (HPA: cerebellar Purkinje cells High). Inspect tissue preservation, detection and counterstain, then review the antibody’s documented IHC-P conditions (general IHC practice). Absence in one section cannot by itself establish biological TLE2 loss. |
| Tissue and cell choice | Cerebellar Purkinje cells offer the strongest listed positive comparison (HPA: High). Respiratory epithelial cells in bronchus and neuronal cells in caudate or cortex are Medium (HPA: tissue IHC). A weaker result there should be judged against its own tissue context, not against Purkinje-cell intensity. |
| Compartment and protein architecture | TLE2 is nuclear and has no transmembrane segment or signal peptide (UniProt Q04725). The supplied record gives no basis to expect a membrane-bound or secreted-tissue pattern. Score defined nuclear staining first; a surface-like chromogenic outline requires investigation (general IHC interpretation). |
| Antibody evidence | HPA049103 has Enhanced IHC validation (HPA: antibody validation), while the tissue profile notes medium staining–RNA consistency and presumed off-target binding that was disregarded (HPA: reliability description). These qualifications support using cell type, compartment and controls together; validation does not make every colored structure specific. |
| Isoforms and modifications | UniProt lists three isoforms and four modified residues, including phosphorylated sites (UniProt Q04725). No epitope position or isoform-specific IHC behavior is supplied. Do not infer that one isoform, phosphorylation state or retrieval choice explains a staining difference from these annotations alone. |
| IF/ICC Q&A: should focal-adhesion signal be expected in paraffin IHC? | HPA reports mainly nuclear bodies and an additional focal-adhesion location in ICC-IF (HPA: subcellular ICC-IF). Its tissue IHC profile reports nuclear expression (HPA: tissue IHC). Treat focal-adhesion signal as an ICC-IF observation, not an established positive pattern for chromogenic paraffin IHC. |
| Situation | Likely cause | Next action |
|---|---|---|
| No nuclear signal in cerebellar Purkinje cells. | A positive expected to be High is missing (HPA: Purkinje cells High); the cause is undetermined from the slide alone. | Check a known-positive section and matched detection controls; review the catalog antibody’s IHC-P instructions and run records (general IHC practice). |
| Only cytoplasmic or membrane-like staining is visible. | The dominant compartment disagrees with the reported nuclear pattern (HPA: tissue IHC; UniProt Q04725: Nucleus). | Inspect nuclear counterstain and a negative control; reassess cell boundaries and background before scoring the slide (general IHC practice). |
| Adipocytes or chondrocytes stain strongly. | Those cell types are Not detected in the cited HPA tissues (HPA: tissue IHC); off-target or detection activity is possible (general IHC practice). | Confirm which cell contains the color, then compare a matched negative control; report the discordance rather than counting it as expected TLE2 staining. |
| Diffuse chromogen makes nuclear scoring unreliable. | Background or overdevelopment can hide a cellular pattern (general chromogenic IHC practice). | Compare negative controls and nuclear counterstain; review blocking, wash and chromogen-development steps under the assay’s established conditions (general IHC practice). |
| Color persists in a control lacking primary antibody. | Primary-independent detection activity or background may contribute (general chromogenic IHC practice). | Check the detection reagents and relevant endogenous-activity blocking for the detection system used; resolve control staining before interpreting TLE2. |
| A Medium HPA tissue appears faint beside a cerebellar positive. | Reported levels differ by cell type (HPA: Purkinje cells High; listed bronchial and neuronal cells Medium). | Compare the appropriate cell type and nuclear pattern within each tissue; check controls before calling a faint result technical failure (general IHC interpretation). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Cerebellum | Purkinje cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | Medium | Protein (IHC) | HPA → |
| Caudate | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | Medium | Protein (IHC) | HPA → |
| Colon | Endothelial cells | Medium | Protein (IHC) | HPA → |
Troubleshoot chromogenic TLE2 IHC in paraffin sections using the catalog antibody’s tissue example and independent localisation evidence.
A10582-1 has an IHC image from paraffin-embedded human tonsil (IHC image caption) and lists IF use and Human/Mouse reactivity (catalog: applications; reactivity). No IF image is provided (catalog: IF image alts).
A10582-1 has an IHC image of paraffin-embedded human tonsil (IHC image caption). It lists IF as an application and Human/Mouse reactivity (catalog: applications; reactivity), but provides no IF image (catalog: IF image alts).
Which to pick: Choose A10582-1 for paraffin-section tissue IHC, supported by its human tonsil image; the fixative is unreported (IHC image caption). For IF, A10582-1 lists that application, but ICC validation and an IF image are unreported (catalog: applications; IF image alts). A10582-1 lists Human/Mouse reactivity and has a Rabbit host, but its clone is unreported and the IHC image shows human tissue only (catalog: reactivity; host; clone; IHC image caption).