TMEM184B / Transmembrane protein 184B · IHC design guide

Design Immunohistochemistry for TMEM184B

Plan chromogenic IHC using pancreatic endocrine cells or placental trophoblasts as high-staining references (HPA tissue IHC). This guide covers fixation, retrieval, antibody titration and scoring against the reported cytoplasmic tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TMEM184B (IHC for TMEM184B): expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane protein (UniProt), antibody A12774, validated IHC image, and IHC protocol steps
Printable TMEM184B IHC protocol sheet — expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane protein (UniProt), antibody A12774, controls and protocol steps. Open the full TMEM184B IHC guide →

TMEM184B Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic tissue staining (HPA tissue IHC); membrane protein (UniProt)
Staining pattern Cytoplasmic staining in pancreatic endocrine and trophoblastic cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6.0 HIER, 95–98 °C, 20 min (rule: cytoplasmic / membrane antigen)
Positive control ⓘ Pancreas+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections (standard IHC practice; not target-specific)
Caveat Staining has medium concordance with RNA expression (HPA tissue IHC)
Regulation Expression regulation unannotated (UniProt)
Isoform / epitope 0 isoforms; no cleavage; epitope side matters (UniProt)
Section 1

Recommended TMEM184B IHC & IF Protocols

The catalog antibody protocol is accompanied by one published TMEM184B tissue IHC protocol (PMC9639041 methods).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleTissue sections; selected-image fixative not specified (standard IHC workflow)
FixationImage fixative and duration unreported (datasheet A12774); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat-induced epitope retrieval in citrate buffer, pH 6.0, 20 min at 95–98 °C (standard rule: cytoplasmic / membrane antigen)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% normal serum of the secondary host, 30 min, room temperature (standard)
Primary antibodyRabbit anti-TMEM184B, 5 μg/mL (datasheet A12774)
Primary incubationOvernight at 4 °C (standard)
DetectionHRP-polymer secondary, DAB chromogen 5–10 min (standard)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTMEM184B-positive staining in pancreatic endocrine cells of pancreas (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with citrate pH 6.0 HIER at 95–98 °C for 20 min (page retrieval); consider EDTA pH 8.0 if needed (PMC9639041 methods).
Section 2

What Is the Expected TMEM184B Staining Pattern?

TMEM184B is a membrane protein with 7 transmembrane segments (UniProt Q9Y519 topology). In tissue IHC, expect general cytoplasmic staining, especially in pancreatic endocrine and placental trophoblastic cells, both scored High (HPA tissue IHC). HPA rates its tissue staining Approved, with medium consistency between staining and RNA data and external verification pending (HPA tissue IHC reliability).

What am I looking at on my slide?
Clear cytoplasmic chromogen in pancreatic endocrine cells or placental trophoblastic cells.This matches the strongest listed tissue IHC findings: both cell populations are scored High (HPA tissue IHC). Judge the signal in the named cells, since an adjacent unstained cell does not negate a cell-specific positive result (general IHC practice).
Predominantly nuclear staining in an otherwise positive tissue.A nuclear-only IHC pattern departs from the reported general cytoplasmic tissue profile (HPA tissue IHC). Check controls before treating it as TMEM184B: ICC-IF also reports nucleoplasm as an additional location, so nuclear signal alone does not prove an artefact (HPA subcellular ICC-IF).
Strong staining in adipocytes, salivary glandular cells, or smooth muscle cells.These cell populations are listed as Not detected by tissue IHC (HPA tissue IHC). Unexpected chromogen warrants checks for cross-reactivity or endogenous detection activity, especially if it also appears in a no-primary control (general IHC practice).
Diffuse colour across cells and surrounding tissue, with little cell-specific contrast.This cannot be scored confidently against HPA's named cell populations (HPA tissue IHC). Compare a no-primary control and review blocking, washes, antibody concentration, and detection conditions for nonspecific background (general IHC practice).
No discernible signal in pancreatic endocrine or placental trophoblastic cells.Both are High in HPA tissue IHC, so absence of signal calls for a run-level check (HPA tissue IHC). Confirm the intended cells are present, then review retrieval, primary incubation, detection, and a concurrently processed positive control (general IHC practice).
💡Expected TMEM184B appearanceCall a positive result when chromogen is clearly cytoplasmic in pancreatic endocrine or placental trophoblastic cells at the expected High level (HPA tissue IHC); widespread diffuse colour or strong staining in HPA Not detected cells is suspect (HPA tissue IHC; general IHC practice).
How each factor affects the staining
Cell population selected for scoring (HPA tissue IHC).Pancreatic endocrine and placental trophoblastic cells are High; stomach glandular, bronchial respiratory epithelial, and cerebellar Purkinje cells are Medium (HPA tissue IHC). Score the identified population rather than assigning one intensity to its whole tissue.
Membrane topology versus tissue appearance (UniProt Q9Y519 topology; HPA tissue IHC).UniProt annotates 7 transmembrane segments and a membrane location (UniProt Q9Y519 topology). HPA reports general cytoplasmic tissue staining; topology alone does not specify a resolvable membrane outline in chromogenic sections (HPA tissue IHC; general IHC practice).
Assay-specific localisation evidence (HPA tissue IHC; HPA subcellular ICC-IF).ICC-IF mainly localises TMEM184B to Golgi, with additional nucleoplasm and cytosol (HPA subcellular ICC-IF). Use that as context for a questionable IHC compartment, while judging tissue sections against HPA's cytoplasmic IHC profile (HPA tissue IHC).
Strength of antibody-pattern support (HPA tissue IHC; HPA antibodies).Tissue IHC reliability is Approved, with medium staining–RNA consistency and external verification pending (HPA tissue IHC reliability). HPA024076 is Approved for IHC and ICC; the supplied record gives no Enhanced validation claim (HPA antibodies).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
A known-positive tissue is blank (HPA tissue IHC).The intended High-staining cells may be absent, or a routine staining step may have failed (HPA tissue IHC; general IHC practice).Verify pancreatic endocrine or placental trophoblastic cells on the section, then inspect retrieval, primary incubation, detection reagents, and a processed positive control (HPA tissue IHC; general IHC practice).
Every area develops broad chromogen.Nonspecific antibody binding or endogenous detection activity can obscure cell-specific staining (general IHC practice).Check a no-primary control; review blocking and endogenous enzyme quenching where applicable, then optimize washes and antibody concentration (general IHC practice).
Unexpected cells stain strongly.Cross-reactivity or background is plausible when HPA lists the cells as Not detected (HPA tissue IHC; general IHC practice).Identify and score the stained cell type, compare it with HPA's cell-level observations, and inspect the no-primary control before interpreting the result (HPA tissue IHC; general IHC practice).
Chromogen appears nuclear-only.This conflicts with the general cytoplasmic tissue IHC profile, though nucleoplasm is an additional ICC-IF location (HPA tissue IHC; HPA subcellular ICC-IF).Compare positive and no-primary controls and reassess cell identity and background; do not reject a result solely because some nuclear signal is present (general IHC practice; HPA subcellular ICC-IF).
A weak sample is being called negative.Some listed populations stain Low, including hippocampal glial cells and lung macrophages (HPA tissue IHC).Use a High-staining HPA cell population as a positive reference and score the weak sample's named cells with the same detection and counterstain conditions (HPA tissue IHC; general IHC practice).
IF/ICC: should the signal look like chromogenic tissue IHC?The assays have different reported appearances: general cytoplasmic tissue IHC and mainly Golgi ICC-IF (HPA tissue IHC; HPA subcellular ICC-IF).For IF/ICC interpretation, expect mainly Golgi localisation with additional nucleoplasm and cytosol; use the separate IF/ICC guide for its procedure (HPA subcellular ICC-IF).

Sample controls for TMEM184B IHC & IF

🧪Run pancreas first: pancreatic endocrine cells should stain strongly (HPA: High in pancreatic endocrine cells). Use salivary glandular cells as the negative tissue (HPA: Not detected in salivary glandular cells); on the pancreatic slide, compare staining with adjacent cells that lack signal as an internal background reference, without assuming those cells are TMEM184B-negative.
Positive control tissue: Pancreas (Pancreatic endocrine cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TMEM184B in A-431, U-251MG, U2OS, with annotated localisation: Golgi apparatus (approved) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) slide, a host-species and antibody-format matched isotype or nonimmune IgG control, and a TMEM184B knockout specimen or peptide-block control if a suitable specimen or immunogen is available (standard IHC controls). Quench endogenous peroxidase and check background in the pancreatic section before interpreting chromogenic signal (standard IHC practice).
⚠️Feasibility: A target-specific fixation window and antigen-retrieval dependency are unreported in the supplied evidence; optimize retrieval with the catalog antibody for paraffin sections (application: IHC-P). The selected A12774 lung IHC caption does not report a fixative (selected-SKU caption: fixative not stated), and the evidence does not establish that frozen sections or IF are easier. In pancreas, endogenous peroxidase can produce chromogenic background, so interpret endocrine-cell staining against the control slides (standard IHC practice; HPA: High in pancreatic endocrine cells).

HPA tissue IHC evidence for TMEM184B

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Pancreas Pancreatic endocrine cells High Protein (IHC) HPA →
Placenta Trophoblastic cells High Protein (IHC) HPA →
Stomach Glandular cells Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Breast Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Salivary gland Glandular cells Not detected Protein (IHC) HPA →
Smooth muscle Smooth muscle cells Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Spleen Cells in red pulp Not detected Protein (IHC) HPA →
Section 3

Advanced TMEM184B IHC Tips

Troubleshoot TMEM184B staining by comparing the signal’s compartment, cell type and distribution with appropriate controls (UniProt Q9Y519; HPA tissue IHC; HPA subcellular).

How should I retrieve TMEM184B in paraffin sections when staining is weak?
Start with citrate buffer at pH 6.0, heated to 95–98 °C for 20 min (page retrieval rule). Run a matched section without retrieval to judge whether heating improves signal or raises background (standard IHC practice). TMEM184B has 7 predicted transmembrane segments, so epitope accessibility may depend on the antibody’s binding site; the supplied evidence does not locate that epitope (UniProt Q9Y519 topology; supplied antibody evidence). If staining remains weak, test an alternative retrieval condition on serial sections while holding antibody concentration and detection constant (standard IHC practice). Compare cellular staining and tissue preservation before adopting the alternative (standard IHC practice).
Could fixation explain inconsistent TMEM184B staining between paraffin blocks?
TMEM184B specific sensitivity to fixation is unknown from the supplied evidence; the tissue image caption gives no fixative (selected A12774 caption). Record the fixative, fixation duration, block age and processing history for each specimen, then compare matched sections processed together (standard IHC practice). Begin retrieval with citrate at pH 6.0, 95–98 °C for 20 min, and keep the antibody and detection conditions constant while investigating fixation differences (page retrieval rule; standard IHC practice). Assess morphology alongside signal, since damaged or unevenly processed tissue can confound chromogenic staining (standard IHC practice). Do not infer fixation tolerance from the reported tissue staining pattern or membrane topology (HPA tissue IHC; UniProt Q9Y519 topology).
Where should credible TMEM184B staining appear in an IHC section?
Expect predominantly cytoplasmic staining in tissue IHC, while allowing a Golgi associated pattern where cellular detail permits its assessment (HPA tissue IHC: general cytoplasmic expression; HPA subcellular: approved Golgi). TMEM184B is annotated as a membrane protein with 7 transmembrane segments, but those features alone do not establish a plasma membrane staining requirement (UniProt Q9Y519). HPA also reports nucleoplasm and cytosol as additional locations in its subcellular data; assess those signals against compartment controls rather than assuming every brown nucleus is specific (HPA subcellular; standard IHC practice). Compare matched positive and negative control tissues under the same retrieval and detection conditions (HPA tissue IHC; standard IHC practice). Note whether staining stays within cells and follows their boundaries (standard IHC practice).
How can epitope position affect TMEM184B staining after retrieval?
The supplied record lists a 407 amino acid chain, 7 transmembrane segments and no annotated isoforms (UniProt Q9Y519). It also lists phosphoserines at positions 388, 402 and 403; the supplied antibody evidence does not identify its binding epitope or demonstrate sensitivity to those modifications (UniProt Q9Y519; supplied antibody evidence). Ask for an epitope map before interpreting a loss of staining as an isoform or phosphorylation effect (standard IHC practice). If an epitope map becomes available, assess whether retrieval and detergent exposure suit that region, using serial sections and matched controls (standard IHC practice). Keep the starting retrieval at citrate pH 6.0 for 20 min (page retrieval rule).
How can I check TMEM184B localisation by multiplex IF alongside IHC?
Treat multiplex IF as a separate assay and include a marker for the cell type being assessed, such as pancreatic endocrine cells when using pancreas (HPA tissue IHC: high in pancreatic endocrine cells; standard IF practice). Choose spectrally separated fluorophores and place the weaker expected signal in a channel with low tissue autofluorescence; inspect unstained tissue in every channel (standard IF practice). TMEM184B is a 7 pass membrane protein, while its antibody epitope and membrane facing side are unspecified in the supplied evidence (UniProt Q9Y519; supplied antibody evidence). If the mapped epitope is intracellular, titrate permeabilisation; if it is extracellular, compare staining before permeabilisation (standard IF practice). Evaluate concordance with the approved Golgi location without imposing IF compartment detail on chromogenic IHC (HPA subcellular; standard IHC practice).
What should I change when TMEM184B IHC shows diffuse brown background?
First compare the stained section with a no primary control to separate antibody dependent staining from detection background (standard IHC practice). For peroxidase detection, check the peroxidase block, secondary reagent and DAB development time on matched sections; these are general chromogenic workflow steps (standard IHC practice). The selected A12774 tissue caption reports 5 µg/mL in human lung, but it provides no fixative or background optimisation data (selected A12774 caption). Titrate primary antibody around the working concentration while keeping retrieval at citrate pH 6.0 and wash conditions constant (selected A12774 caption; page retrieval rule; standard IHC practice). Reject signal concentrated at folds, torn edges or drying marks (standard IHC practice).
How should I quantify TMEM184B IHC across tissue samples? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring: HPA reports general cytoplasmic tissue staining and high staining in pancreatic endocrine and trophoblastic cells (HPA tissue IHC). For a cell based readout, record the percentage of positive target cells and an H-score using consistent intensity bins and a fixed threshold (standard IHC practice). For sparse populations, report positive cell density per mm² of viable tissue and normalise counts to the area of the same annotated compartment (standard IHC practice). Keep section thickness, retrieval, antibody concentration, chromogen development and imaging settings consistent across groups (standard IHC practice). Exclude necrosis, folds and edge artefacts before comparing scores (standard IHC practice).
How do I distinguish true TMEM184B signal from IHC artefact?
Judge staining against both cell identity and compartment: HPA reports high signal in pancreatic endocrine and trophoblastic cells, general cytoplasmic tissue staining and an approved Golgi location in subcellular data (HPA tissue IHC; HPA subcellular). A strong signal restricted to an unexpected nucleus or to cells reported as undetected warrants review with matched controls; additional nucleoplasmic localisation has also been reported, so nuclear staining alone is inconclusive (HPA tissue IHC; HPA subcellular; standard IHC practice). Exclude edge effects, necrotic regions and endogenous peroxidase staining using morphology and a no primary control (standard IHC practice). The selected lung caption establishes an image at 5 µg/mL, while HPA lists lung macrophages as low; interpret intensity in its documented context (selected A12774 caption; HPA tissue IHC).
Boster reagents

Best TMEM184B / Transmembrane protein 184B IHC Antibodies

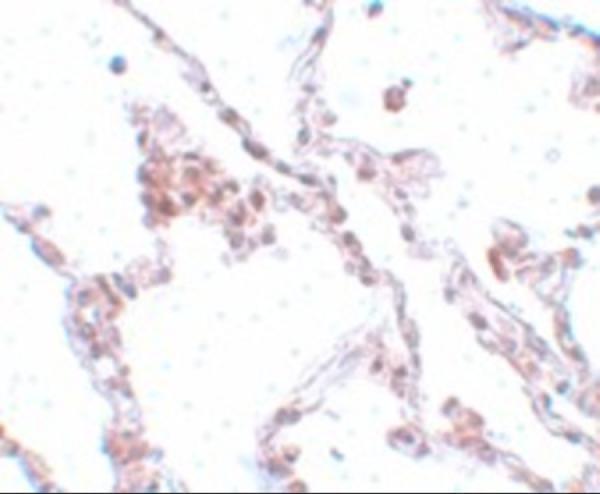
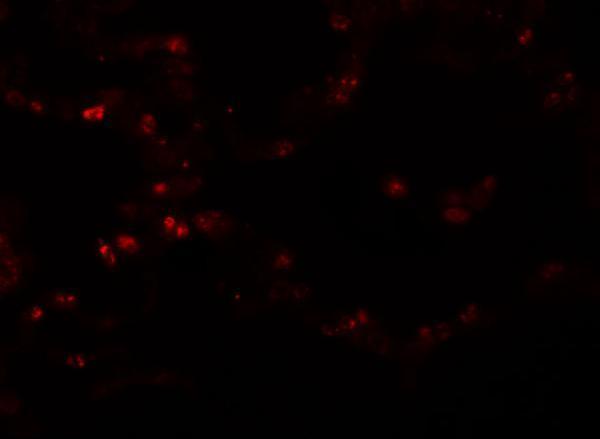
A12774 has IHC-P and IF applications (catalog: applications), with human lung images for both (catalog: image captions) and listed reactivity to human, mouse and rat (catalog: reactivity).

Real IHC data Immunohistochemistry of TMEM184B in human lung tissue with TMEM184B antibody at 5 μg/mL.
Anti-Transmembrane protein 184B TMEM184B Antibody
Cat # A12774

A12774 will render with a human lung IHC image at 5 μg/mL (catalog: IHC image caption). The same SKU has a human lung IF image at 20 μg/mL (catalog: IF image caption).

Which to pick: Choose A12774 for paraffin-section IHC (catalog: IHC-P application); its IHC image shows human lung at 5 μg/mL, but the fixative is unreported (catalog: IHC image caption). For IF, choose A12774 based on its human lung IF image at 20 μg/mL (catalog: IF image caption); ICC-specific validation is unreported (catalog: applications and image captions). For mouse or rat samples, A12774 lists cross-species reactivity (catalog: reactivity), while its IHC and IF images show human tissue only (catalog: image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q9Y519 (T184B_HUMAN, Transmembrane protein 184B).
  2. Human Protein Atlas. TMEM184B tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. TMEM184B subcellular location (ICC-IF): Mainly localized to the Golgi apparatus. In addition localized to the nucleoplasm and cytosol..
  4. Human Protein Atlas. TMEM184B antibody validation summary (1 antibodies).
  5. A TMED3-governed disulfidptosis-related diagnostic signature reveals tumor microenvironment remodeling in intrahepatic cholangiocarcinoma. Frontiers in immunology 2026 — PMC13462420.
  6. TMEM184B promotes proliferation, migration and invasion, and inhibits apoptosis in hypopharyngeal squamous cell carcinoma. Journal of cellular and molecular medicine 2022 — PMC9639041.
  7. PubMed PMID:12761501 — UniProt-cited evidence.
  8. PubMed PMID:15461802 — UniProt-cited evidence.
  9. PubMed PMID:14702039 — UniProt-cited evidence.