TOPBP1 / DNA topoisomerase 2-binding protein 1 · IHC design guide

Design Immunohistochemistry for TOPBP1

Plan TOPBP1 chromogenic IHC on paraffin sections with the IHC-validated antibody at 2–5 μg/ml (datasheet A01867-1). Assess nuclear and cytoplasmic staining against tissue observations (HPA tissue IHC), while accounting for DNA damage-associated foci (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TOPBP1 (IHC for TOPBP1): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A01867-1, validated IHC image, and IHC protocol steps
Printable TOPBP1 IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A01867-1, controls and protocol steps. Open the full TOPBP1 IHC guide →

TOPBP1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Nuclear and cytoplasmic staining; high in adipocytes and glia (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01867-1)
Positive control ⓘ Adipose tissue+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific)
Caveat DNA damage can shift nuclear signal into discrete foci (UniProt)
Regulation DNA damage recruits TOPBP1 to foci (UniProt)
Isoform / epitope No annotated isoforms; one 1–1522 chain (UniProt)
Section 1

Recommended TOPBP1 IHC & IF Protocols

The catalog antibody has an IHC-P protocol (datasheet A01867-1); the published options cover breast, prostate and cervical tissue staining (PMC3358587; PMC7288942; PMC6486426 methods).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded rat brain tissue; fixative not specified (datasheet A01867-1)
FixationImage fixative and duration unreported (datasheet A01867-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01867-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01867-1)
Primary antibodyRabbit anti-TOPBP1, 2-5 μg/ml (datasheet A01867-1)
Primary incubationOvernight at 4 °C (datasheet A01867-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01867-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultTOPBP1-positive staining in adipocytes of adipose tissue (HPA tissue IHC: High). HPA tissue profile: General nuclear and cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA, pH 8.0, for the catalog antibody (datasheet A01867-1). Compare citrate, pH 6.0, when adapting the breast-tissue protocol (PMC3358587 methods).
Section 2

What Is the Expected TOPBP1 Staining Pattern?

TOPBP1 is chiefly nuclear, with chromosome and context-dependent centrosome or spindle-pole localization; it has no transmembrane segment (UniProt Q92547: subcellular location, topology). In tissue IHC, expect nuclear and some cytoplasmic staining across several cell types, including adipocytes, glandular cells, hematopoietic cells and respiratory epithelial cells (HPA: general nuclear and cytoplasmic expression; listed cells High). HPA rates the tissue pattern Approved, with medium consistency against RNA data (HPA: reliability).

What am I looking at on my slide?
Nuclear staining in listed High cells, with some cytoplasmic signal.This fits the reported tissue pattern, especially when nuclei remain distinguishable from the counterstain (HPA: general nuclear and cytoplasmic expression; listed cells High). Compare compartments within the same section; cytoplasmic signal alone gives less support for the expected pattern (HPA: general nuclear and cytoplasmic expression; UniProt Q92547: nucleus).
A distinct nuclear focus or focal signal near a mitotic spindle pole.A focus can be compatible with TOPBP1 recruitment to DNA damage sites; spindle-pole and centrosome localization is reported in mitotic cells (UniProt Q92547: subcellular location). Morphology alone cannot establish DNA damage or cell-cycle phase. Record the context before treating a focal pattern as expected (UniProt Q92547: subcellular location).
Only extracellular, luminal or sharply membrane-rim staining, without discernible nuclear signal.Question the IHC result: the reported tissue profile is nuclear and cytoplasmic (HPA: tissue IHC profile). A membrane location appears as an additional ICC-IF observation, with Approved status, so it does not by itself validate a membrane-only tissue IHC pattern (HPA: subcellular ICC-IF; tissue IHC profile).
Strong color in a cell population outside the listed High cells, or in acellular areas.Investigate cross-reactivity, endogenous detection activity or deposited chromogen (general IHC practice). HPA lists several High cell types but supplies no negative cell population here; staining in another cell type alone cannot prove a false positive (HPA: listed positive cells; negative list empty).
No signal in a section containing listed High cells.Check the assay before interpreting biological absence: adipocytes, glandular cells, hematopoietic cells and respiratory epithelial cells provide reported High examples (HPA: tissue IHC positives). An individual specimen is not guaranteed to stain identically; HPA calls the tissue antibody evidence Approved with medium RNA agreement (HPA: reliability).
💡Expected TOPBP1 appearanceCall a result consistent with TOPBP1 when identifiable cells show nuclear staining, possibly with cytoplasmic signal, in an HPA-listed High population; isolated extracellular or membrane-only color without nuclear staining warrants investigation (HPA: tissue IHC profile and listed positives; UniProt Q92547: nucleus).
How each factor affects the staining
Tissue and cell choiceHPA reports High staining in adipocytes, adrenal and appendix glandular cells, bone-marrow hematopoietic cells, bronchial respiratory epithelial cells, caudate glia and cerebellar granular-layer cells (HPA: tissue IHC positives). These are reference patterns, not guaranteed positive controls for every specimen (HPA: Approved, medium consistency).
Cell state and subcellular distributionUniform nuclear distribution is reported in G phase; DNA damage can produce discrete foci, and mitotic cells can show spindle-pole or centrosome localization (UniProt Q92547: subcellular location). Assess these appearances with cell morphology and experimental context; routine tissue staining alone does not identify the underlying event.
Antibody evidence by applicationThe tissue IHC antibody CAB022451 is Approved, while HPA036738 and HPA036739 are Supported for ICC and have no listed IHC status (HPA: antibody validation). Do not transfer an ICC validation label to paraffin-section IHC; compare the chosen antibody's actual IHC status (HPA: antibody validation).
IF/ICC: what location is expected?Mainly nucleoplasm and nuclear bodies; an additional plasma-membrane location is reported (HPA: subcellular ICC-IF, Supported main locations and Approved additional location). This answers the IF/ICC pattern question only; tissue IHC is separately described as general nuclear and cytoplasmic expression (HPA: tissue IHC profile).
Antigen retrieval and detectionNo TOPBP1-specific retrieval condition or fixation sensitivity is supplied by UniProt or HPA. Select and document retrieval using the IHC-validated antibody's instructions, then evaluate background with an appropriate detection control (general IHC practice). Do not infer retrieval needs from TOPBP1's BRCT domains or phosphorylation sites (UniProt Q92547: domains, modified residues).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No nuclear staining in a listed High cell population.Assay failure or a specimen-dependent difference are possibilities; HPA's Approved rating has medium RNA agreement (HPA: reliability; listed positives).Review section quality, retrieval and antibody instructions; include an appropriate positive control and inspect nuclei against the counterstain (general IHC practice).
Color is diffuse across tissue or visible outside cells.Nonspecific background or detection deposits can obscure the nuclear and cytoplasmic profile (general IHC practice; HPA: tissue IHC profile).Check a no-primary detection control, blocking, washes and chromogen development; then compare cell boundaries and nuclei (general IHC practice).
Cytoplasm is strong but nuclei are consistently blank.The balance conflicts with the reported general nuclear and cytoplasmic IHC profile, though cytoplasmic expression itself is reported (HPA: tissue IHC profile).Review nuclear preservation and counterstain, compare a listed High tissue and confirm the antibody has IHC evidence (general IHC practice; HPA: antibody validation and positives).
An unexpected cell population stains strongly.Cross-reactivity or endogenous detection activity is possible; the supplied HPA data give no negative cell population to establish exclusion (general IHC practice; HPA: negative list empty).Check detection controls and cell identity; describe the observation without declaring that population TOPBP1-negative solely from this payload (general IHC practice; HPA: negative list empty).
Staining forms scattered nuclear dots.TOPBP1 can form discrete foci after DNA damage, but dots in tissue do not establish damage by themselves (UniProt Q92547: subcellular location).Assess nuclear morphology and experimental context, and compare control sections before scoring foci as a biological response (general IHC practice).
Membrane rims dominate the IHC slide.HPA reports an additional plasma-membrane location in ICC-IF, while its tissue IHC summary is nuclear and cytoplasmic (HPA: subcellular ICC-IF; tissue IHC profile).Recheck nuclear signal and detection controls; report membrane-only IHC as unresolved until independently supported (general IHC practice; HPA: tissue IHC profile).

Sample controls for TOPBP1 IHC & IF

🧪Run bone marrow first: hematopoietic cells should stain because HPA scores them High (HPA: bone marrow, hematopoietic cells, High). HPA detects TOPBP1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, while anucleate erythrocytes on the positive slide should lack target-specific nuclear staining (HPA: no negative tissue; UniProt Q92547: nuclear localization).
Positive control tissue: Adipose tissue (Adipocytes, HPA High)
Negative control tissue: None in HPA: TOPBP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TOPBP1 in A-431, HEL, U2OS, HeLa, with annotated localisation: Nucleoplasm (supported), Nuclear bodies (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only slide, a rabbit IgG isotype control matched to the primary antibody’s clonality, and TOPBP1 knockout material processed alongside the test section as a biological negative (caption: rabbit primary; standard IHC controls). Quench endogenous peroxidase in bone marrow before HRP/DAB detection (HPA: bone marrow positive; caption: HRP/DAB detection).
⚠️Feasibility: Paraffin-section IHC is documented with heat-mediated EDTA retrieval at pH 8.0, but the selected A01867-1 caption does not report a fixative; a target-specific fixation window or fixation effect is unreported (A01867-1 tissue-IHC caption). That caption supports a retrieval starting point, not proof that retrieval is required; the supplied evidence does not establish that frozen sections or IF are easier (A01867-1 tissue-IHC caption; HPA: ICC-IF images). In bone marrow, endogenous peroxidase can complicate HRP/DAB interpretation (HPA: bone marrow positive; standard IHC practice).

HPA tissue IHC evidence for TOPBP1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes High Protein (IHC) HPA →
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Glandular cells High Protein (IHC) HPA →
Bone marrow Hematopoietic cells High Protein (IHC) HPA →
Breast Adipocytes High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: TOPBP1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced TOPBP1 IHC Tips

Troubleshoot TOPBP1 staining by checking retrieval, nuclear localisation, controls and scoring against the paraffin-section evidence (datasheet A01867-1; UniProt Q92547; HPA tissue IHC).

What retrieval should I try first if TOPBP1 staining is weak?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A01867-1). The selected rat brain image used this retrieval, followed by 2 μg/ml primary antibody overnight at 4°C; keep those conditions consistent while assessing retrieval (datasheet A01867-1). If signal remains weak, compare a modest change in heating duration on matched sections while monitoring tissue integrity and background, because retrieval can alter both (standard IHC practice). Include a section processed without primary antibody and a reference section in each run so a retrieval change is distinguishable from detection variation (standard IHC practice).
Could fixation explain weak or uneven TOPBP1 staining?
Target-specific sensitivity of TOPBP1 to fixative type or fixation duration is unknown from the supplied evidence; the selected paraffin-section caption does not state its fixative (datasheet A01867-1). Record the actual fixative, duration, tissue thickness and processing history before comparing sections, since these variables can affect epitope access and morphology in IHC (standard IHC practice). Test matched sections with the documented EDTA pH 8.0 retrieval and the same detection settings, then compare intact regions at similar section depth (datasheet A01867-1; standard IHC practice). Avoid assigning a TOPBP1-specific fixation mechanism from its phosphorylation sites or tissue staining pattern alone (UniProt Q92547; HPA tissue IHC).
Should TOPBP1 staining be nuclear, cytoplasmic or punctate?
Expect nuclear staining as the main interpretive pattern: TOPBP1 has uniform nuclear distribution in G phase and can form DNA-damage-associated foci (UniProt Q92547 localisation). HPA describes general nuclear and cytoplasmic tissue expression, while its cell imaging supports nucleoplasm and nuclear bodies, so compartment calls should be made within identifiable cells (HPA tissue IHC; HPA subcellular). Centrosome and spindle-pole localisation is reported in mitotic cells, making a small punctate extranuclear signal plausible in an appropriate mitotic context (UniProt Q92547 localisation). Check nuclear counterstain alignment and compare similarly processed regions before treating diffuse cytoplasmic DAB or isolated dark granules as specific TOPBP1 (standard IHC practice).
Could the antibody epitope or TOPBP1 processing alter my IHC pattern?
The supplied record lists 0 annotated isoforms and one 1–1522 chain; it does not identify this antibody’s epitope (UniProt Q92547; datasheet A01867-1). TOPBP1 contains 8 BRCT domains and annotated phosphorylation sites, so an epitope assignment would require antibody-specific mapping rather than inference from domain positions or staining (UniProt Q92547). Compare retrieval and antibody concentration on adjacent sections while keeping chromogen development constant, because altered accessibility or excess primary antibody can change apparent staining (standard IHC practice). Interpret a compartment shift cautiously until it is reproduced with suitable controls or an independently mapped reagent (standard IHC practice).
How should I investigate TOPBP1 localisation with a complementary IF assay?
Use IF as a separate localisation check alongside chromogenic IHC, selecting an established marker for the expected cell population and a nuclear counterstain to assign TOPBP1 signal to individual cells (standard IF practice). HPA supports nucleoplasmic and nuclear-body localisation in cell imaging, whereas the selected antibody caption documents paraffin-section IHC conditions only (HPA subcellular; datasheet A01867-1). Choose fluorophores after checking the specimen’s autofluorescence and use single-stain controls to assess channel bleed-through during multiplex imaging (standard IF practice). Because TOPBP1 lacks a transmembrane segment and is mainly nuclear, assess permeabilisation for access to intracellular epitopes while preserving nuclear morphology (UniProt Q92547 topology and localisation; standard IF practice).
How can I reduce diffuse brown staining without losing TOPBP1 signal?
First compare a no-primary control with the stained section to identify signal generated by the detection system or tissue rather than the primary antibody (standard IHC practice). The selected protocol blocked with 10% goat serum and used an HRP-based secondary with DAB, so review blocking, washing and chromogen development when brown staining is widespread (datasheet A01867-1; standard IHC practice). A peroxidase block is a general chromogenic IHC step that helps assess endogenous enzyme activity; it is not TOPBP1-specific validation (standard IHC practice). Recheck nuclear counterstain and intact morphology before calling diffuse deposits or staining concentrated at section edges positive (standard IHC practice).
What is a defensible way to score TOPBP1 in paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population, tissue region and nuclear scoring rule before reviewing groups, then report the percentage of positive nuclei and staining intensity separately (standard IHC practice). For an H-score, multiply each intensity category 0–3 by its percentage of cells and sum the products, yielding 0–300 (standard IHC practice). If discrete foci are the endpoint, count positive nuclei or foci per mm² of viable tissue and normalise to nuclei assessed, using the same imaging and threshold settings throughout (standard IHC practice). Keep nuclear and cytoplasmic scores separate because both are described in tissue IHC, and record excluded damaged or edge regions (HPA tissue IHC; standard IHC practice).
How do I distinguish true TOPBP1 staining from section artefact?
A credible result should align with identifiable cells and nuclear counterstain, since nuclear distribution and damage-associated foci are documented for TOPBP1 (UniProt Q92547 localisation; standard IHC practice). HPA reports broad nuclear and cytoplasmic tissue staining with medium agreement to RNA expression, so cytoplasmic colour alone is insufficient to assign a cellular mechanism (HPA tissue IHC). Compare intact interior tissue with edges and necrotic areas, and inspect the no-primary control for endogenous enzyme signal or DAB deposits (standard IHC practice). Reproducible staining in matched sections supports an interpretation, while a compartment or cell-type claim needs appropriate independent validation (standard IHC practice).
Boster reagents

Best TOPBP1 / DNA topoisomerase 2-binding protein 1 IHC Antibodies

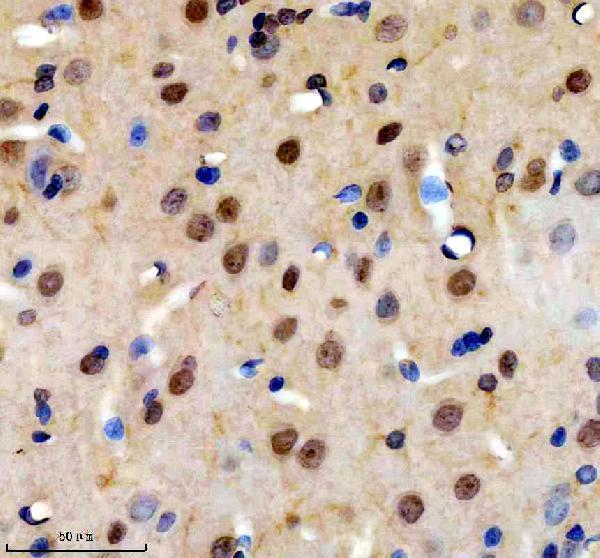
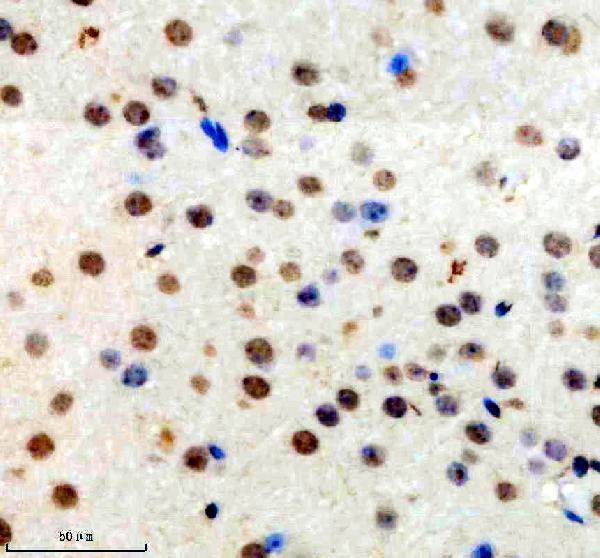
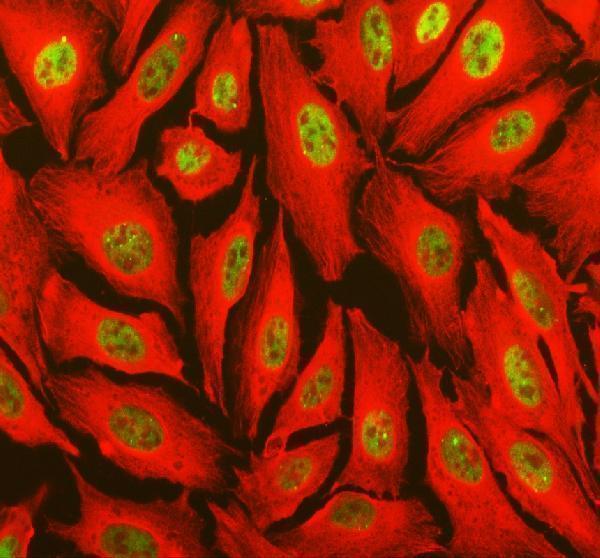
A01867-1 has IHC images from rat and mouse brain paraffin sections and an IF image from U2OS cells (catalog image captions); its listed reactivity is human, mouse and rat (catalog).

Real IHC data IHC analysis of TOPBP1 using anti-TOPBP1 antibody (A01867-1). TOPBP1 was detected in a paraffin-embedded section of rat brain tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-TOPBP1 Antibody (A01867-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-TOPBP1 Antibody ®
Cat # A01867-1

A01867-1 will render with its rat brain paraffin-section IHC figure; a second catalog caption documents mouse brain paraffin-section IHC (catalog image captions). Its IF caption documents staining in U2OS cells (catalog IF image caption).

Which to pick: Choose A01867-1 for paraffin-section IHC using the documented rat or mouse brain examples (catalog IHC image captions); the fixative is unreported (catalog IHC image captions). For IF/ICC, A01867-1 is listed for both applications and has a U2OS cell IF image (catalog applications; catalog IF image caption). It is a polyclonal antibody listed as reactive with human, mouse and rat, although the supplied IHC images document rat and mouse tissue only (catalog dilution data; catalog reactivity; catalog IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry Q92547 (TOPB1_HUMAN, DNA topoisomerase 2-binding protein 1).
  2. Human Protein Atlas. TOPBP1 tissue IHC expression (reliability: Approved).
  3. Human Protein Atlas. TOPBP1 subcellular location (ICC-IF): Mainly localized to the nucleoplasm and nuclear bodies. In addition localized to the plasma membrane..
  4. Human Protein Atlas. TOPBP1 antibody validation summary (3 antibodies).
  5. Expression of TopBP1 in hereditary breast cancer. Molecular biology reports 2012 — PMC3358587.
  6. Topoisomerase II-binding protein 1 promotes the progression of prostate cancer via ATR-CHK1 signaling pathway. Aging 2020 — PMC7288942.
  7. Association between the c.*229C>T polymorphism of the topoisomerase IIβ binding protein 1 (TopBP1) gene and breast cancer. Molecular biology reports 2013 — PMC3611025.
  8. Topoisomerase IIβ-binding protein 1 activates expression of E2F1 and p73 in HPV-positive cells for genome amplification upon epithelial differentiation. Oncogene 2019 — PMC6486426.
  9. PubMed PMID:9461304 — UniProt-cited evidence.
  10. PubMed PMID:9039502 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.