This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic TP73 IHC in paraffin sections using the nuclear staining reported in epithelial subsets as a reference (HPA tissue IHC). Check antibody epitope coverage when interpreting results across TP73’s 11 isoforms (UniProt).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Nuclear in stained epithelial subsets (HPA tissue IHC) | |
| Staining pattern | Nuclear staining in subsets of glandular, squamous and respiratory epithelial cells (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M00688) | |
| Positive control | Bronchus+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Isoform differences may affect antibody epitope coverage (UniProt) | |
| Regulation | Accumulates in nuclei after DNA damage (UniProt) | |
| Isoform / epitope | 11 isoforms; check which forms the antibody epitope covers (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet: M00688) is accompanied by published TP73 protocols for cervical cancer tissue (PMC6682548) and human liver tissue (PMC6920427).
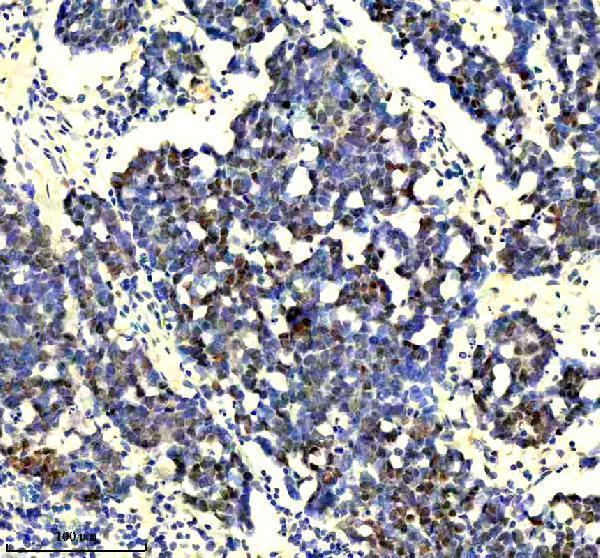
| Sample | Paraffin-embedded human skin cancer tissue; fixative not specified (datasheet M00688) |
| Fixation | Image fixative and duration unreported (datasheet M00688); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M00688); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M00688) |
| Primary antibody | Rabbit monoclonal (clone EHI-20) anti-TP73, 1:50 (datasheet M00688) |
| Primary incubation | Overnight at 4 °C (datasheet M00688) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet M00688) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TP73-positive staining in basal cells of bronchus (HPA tissue IHC: High). HPA tissue profile: Nuclear expression in a subset of glandular cells in fallopian tube, squamous epithelium and respiratory epithelium. No signal in the no-primary control. |
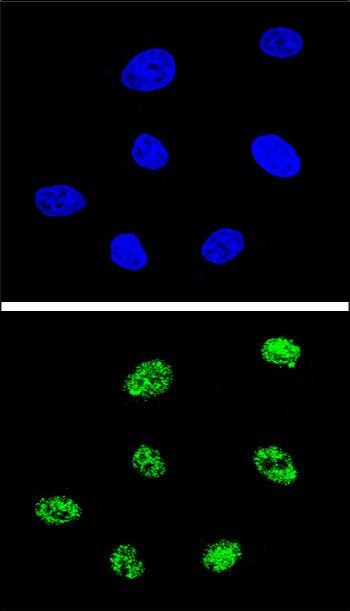
TP73 is primarily nuclear in tissue IHC, with staining reported in subsets of respiratory and squamous epithelial cells (HPA: tissue IHC profile). Nucleoplasmic localization is supported by ICC-IF; UniProt also lists cytoplasm and nuclear accumulation after DNA damage (HPA: subcellular; UniProt O15350: subcellular location). TP73 has no transmembrane segment, so a membrane-only tissue pattern needs scrutiny (UniProt O15350: topology). HPA rates the tissue IHC pattern Enhanced, with medium consistency against RNA data (HPA: tissue IHC reliability).
| Distinct nuclear staining in bronchial or nasopharyngeal basal cells, or skin keratinocytes, with limited surrounding signal (HPA: High in these cells). | This fits the reported positive tissue pattern. Score the named cell population and nuclear compartment separately; a convincing section preserves recognizable morphology and a readable counterstain (HPA: tissue IHC; standard IHC practice). |
| Predominantly membrane, junctional, or diffuse cytoplasmic chromogen, with little nuclear signal. | Do not score this alone as the expected IHC result: the tissue profile is nuclear (HPA: tissue IHC). UniProt permits cytoplasmic localization, and HPA reports additional ICC-IF locations, some uncertain; those observations do not validate a membrane-only tissue IHC pattern (UniProt O15350: subcellular location; HPA: subcellular). |
| Strong staining in adipocytes or in another cell population recorded as undetected in the selected HPA tissue. | Consider cross-reactivity or endogenous detection activity, then inspect the exact tissue and cell annotation before calling it TP73. HPA lists adipocytes in adipose tissue as Not detected; its negatives are cell-specific, not proof that every cell in that tissue lacks TP73 (HPA: tissue IHC; standard IHC practice). |
| Haze across tissue and empty spaces, with nuclei and tissue boundaries hard to distinguish. | Treat widespread diffuse color as background until controls support a cell-specific signal. Review blocking, antibody concentration, washing, and detection chemistry; a clean, localized nuclear pattern is the relevant comparator (HPA: tissue IHC profile; standard IHC practice). |
| No nuclear signal in an otherwise interpretable bronchus, nasopharynx, or skin section. | A technical false negative is possible because HPA reports High staining in the specified basal cells or keratinocytes. Confirm that those cells are present, then check retrieval, antibody concentration, and detection controls before interpreting a negative result (HPA: tissue IHC; standard IHC practice). |
| Tissue and cell selection | HPA reports High staining in bronchial and nasopharyngeal basal cells and skin keratinocytes; cervix, esophagus, and oral mucosa squamous cells are Medium. Choose and score the documented cell type, not the whole section (HPA: tissue IHC). |
| Compartment and assay | Nucleoplasm is the supported main ICC-IF location, whereas tissue IHC describes nuclear expression in selected epithelial cells. Additional ICC-IF locations do not establish a tissue IHC scoring pattern (HPA: subcellular; HPA: tissue IHC). |
| Isoforms and response state | UniProt lists 11 isoforms and nuclear accumulation after DNA damage. An isoform-specific or damage-response claim needs epitope and sample evidence beyond this tissue pattern; avoid inferring either from staining intensity alone (UniProt O15350: isoforms and subcellular location). |
| Antibody validation | The HPA tissue pattern is Enhanced, and two listed antibodies have Enhanced IHC status; HPA also reports medium consistency with RNA. This supports the reported pattern without proving that every reagent or specimen will reproduce it (HPA: tissue IHC reliability; HPA: antibody validation). |
| Antigen retrieval and detection | Use the catalog antibody's IHC-P instructions to set retrieval and dilution, then assess nuclear signal against background (standard IHC practice). No TP73-specific fixation sensitivity or retrieval effect is established by the supplied UniProt and HPA records. |
| IF/ICC Q&A | Q: Should IF puncta or membrane signal be scored as the IHC result? A: No; HPA supports nucleoplasm as the main ICC-IF location and marks plasma membrane and junctions uncertain. Evaluate IF/ICC on its own guide page (HPA: subcellular). |
| Situation | Likely cause | Next action |
|---|---|---|
| Positive-control section has no nuclear staining. | The expected basal cells or keratinocytes may be absent, or retrieval, antibody application, or detection may have failed (HPA: High in named cells; standard IHC practice). | Verify the annotated cell population on the slide; check the IHC-P instructions and detection controls, then repeat with a documented positive section (HPA: tissue IHC; standard IHC practice). |
| Color covers most of the section. | Nonspecific binding, excess antibody, inadequate washing, or detection background can obscure the expected nuclear distribution (HPA: tissue IHC profile; standard IHC practice). | Review blocking and washes, titrate within the catalog IHC-P guidance, and compare a no-primary control with the stained section (standard IHC practice). |
| Color appears mainly at membranes or junctions. | This differs from HPA's nuclear tissue IHC profile; HPA labels membrane and junctional ICC-IF locations uncertain, so staining identity is unresolved (HPA: tissue IHC; HPA: subcellular). | Check cellular morphology and controls, then seek reproducible nuclear staining in a documented positive cell type before scoring the IHC result (HPA: tissue IHC; standard IHC practice). |
| An HPA-listed negative cell type stains strongly. | Cross-reactivity or endogenous detection activity is possible; the HPA negative entry applies to the specified cell type, such as adipocytes in adipose tissue (HPA: tissue IHC; standard IHC practice). | Confirm cell identity and review no-primary and detection controls; avoid extending the HPA cell-specific negative call to the entire tissue (HPA: tissue IHC; standard IHC practice). |
| Fallopian tube staining seems mixed or hard to score. | HPA's profile mentions nuclear staining in a subset of glandular cells, while its cell table records Low staining in ciliated cell bodies; these descriptions warrant cell-level review (HPA: tissue IHC). | Record the cell type and compartment seen, and use a High, clearly annotated tissue as the positive comparator rather than forcing one fallopian tube-wide score (HPA: tissue IHC; standard IHC practice). |
| Nuclear staining varies between specimens. | TP73 can accumulate in nuclei after DNA damage, while HPA reports only medium consistency between antibody staining and RNA; these facts alone do not establish why a given specimen differs (UniProt O15350: subcellular location; HPA: tissue IHC reliability). | Compare like cell populations, morphology, and run controls; report the observed fraction and intensity without assigning a damage state or isoform from IHC alone (HPA: tissue IHC; UniProt O15350: isoforms; standard IHC practice). |





Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Basal cells | High | Protein (IHC) | HPA → |
| Nasopharynx | Basal cells | High | Protein (IHC) | HPA → |
| Skin | Keratinocytes | High | Protein (IHC) | HPA → |
| Cervix | Squamous epithelial cells | Medium | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot TP73 staining in paraffin sections by checking retrieval, cell type, nuclear localisation and antibody epitope before interpreting chromogenic signal.
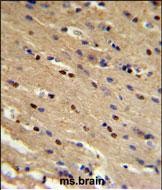
Explore anti-TP73 antibodies with IHC images from human skin and intestinal cancers, mouse brain and intestine, and rat brain, plus a 293-cell IF image (catalog image captions).
M00688 has a paraffin-section IHC image of human skin cancer, while PB9235 has IHC(P) images of human intestinal cancer, mouse intestine, and rat brain (catalog: M00688 and PB9235 IHC captions). A00688-1 has an IHC image of formalin-fixed, paraffin-embedded mouse brain and an IF image of 293 cells (catalog: A00688-1 IHC and IF captions).
Which to pick: For human tissue IHC, M00688 is a rabbit monoclonal shown on a paraffin section of human skin cancer at 1:50; its IHC caption does not report a fixative (catalog: M00688 host, clone, reactivity, and IHC caption). For IF/ICC, M00688 lists both applications for human samples at 1:50; A00688-1 lists IF for human and mouse at 1:10–1:50 and has a 293-cell IF image (catalog: M00688 and A00688-1 applications, reactivity, and IF dilutions; A00688-1 IF caption). For tissue IHC across human, mouse, and rat, PB9235 has IHC(P) images from all three species; its captions do not report a fixative (catalog: PB9235 reactivity and IHC captions).