This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic TRANK1 IHC in paraffin sections using the reported ciliary and cytoplasmic tissue pattern (HPA tissue IHC). The guide covers the 2–5 μg/ml antibody range (datasheet A09518) and interpretation of staining with low antibody–RNA consistency (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cilia and cytoplasm in tissue staining (HPA tissue IHC) | |
| Staining pattern | Strong ciliary staining in ciliated cells; cytoplasm in several tissues (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet A09518) | |
| Positive control | Bronchus+4 more · see all | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A09518) | |
| Caveat | Antibody staining and RNA expression show low consistency (HPA tissue IHC) | |
| Regulation | No expression regulator annotated (UniProt) | |
| Isoform / epitope | 0 isoforms annotated; epitope location unspecified (UniProt) |
The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A09518). The published rat prefrontal cortex protocol uses citrate pH 6.0 (PMC5355521).
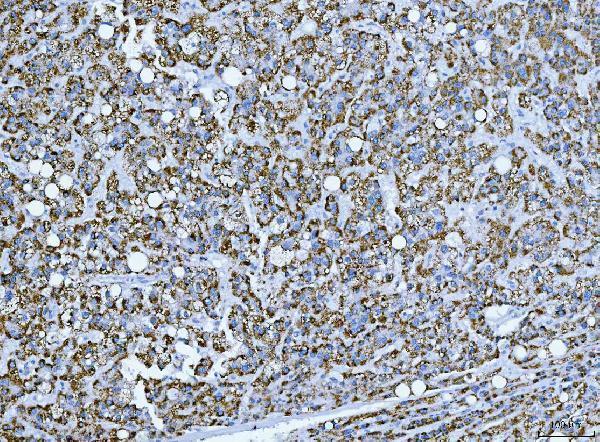
| Sample | Paraffin-embedded human liver cancer tissue; fixative not specified (datasheet A09518) |
| Fixation | Image fixative and duration unreported (datasheet A09518); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet A09518); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet A09518) |
| Primary antibody | Rabbit anti-TRANK1, 2-5 μg/ml (datasheet A09518) |
| Primary incubation | Overnight at 4 °C (datasheet A09518) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet A09518) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TRANK1-positive staining in ciliated cells (cilia axoneme) of bronchus (HPA tissue IHC: High). HPA tissue profile: Distinct expression in cilia in fallopian tube, respiratory epithelia and efferent ducts. Cytoplasmic expression in several tissues. No signal in the no-primary control. |
In paraffin-section IHC, expect strong staining along the cilia axoneme of ciliated cells in bronchus, nasopharynx and fallopian tube, with high staining also reported in efferent-duct ciliated cells (HPA: tissue IHC). Several tissues show cytoplasmic expression (HPA: tissue IHC). TRANK1 has no annotated transmembrane segment (UniProt O15050 topology). HPA rates its tissue staining Approved but reports low agreement with RNA data and pending external verification (HPA: reliability).
| A distinct apical ciliary signal appears in bronchus, nasopharynx or fallopian tube, with little stain outside the ciliated cells. | This matches the strongest, most specific tissue pattern reported for TRANK1: High staining in ciliated-cell cilia axonemes (HPA: tissue IHC). Judge both the cell type and the fine ciliary location; overall brown intensity alone is less informative. The HPA tissue profile remains pending external verification (HPA: reliability). |
| The intended ciliary signal is replaced by nuclear-only or uniformly diffuse staining in ciliated epithelium. | That does not reproduce the cilia-axoneme pattern reported for these tissues (HPA: tissue IHC). Review morphology, counterstain and staining controls before calling it specific (general IHC practice). Nuclear staining alone is not proof of an artefact: HPA separately reports approved nucleoplasmic localisation in ICC-IF (HPA: subcellular ICC-IF). |
| Strong stain appears mainly in an HPA-listed negative cell population while nearby ciliated cells lack the expected pattern. | Treat this as a specificity warning, not an automatic TRANK1-positive call. HPA reports Not detected in alveolar cells and adipocytes, for example (HPA: tissue IHC). Cross-reactivity or endogenous detection activity are possible technical explanations; compare omission and detection controls before assigning a cause (general IHC practice). |
| A broad haze covers tissue, stroma or blank regions and obscures cell boundaries. | A slide-wide haze cannot establish the cell-restricted ciliary pattern (HPA: tissue IHC). Uneven washing, insufficient blocking or detection background can cause diffuse chromogenic signal (general IHC practice). Compare a primary-antibody omission control and inspect whether fine cilia remain distinguishable. |
| No ciliary signal is visible in a well-preserved bronchus, nasopharynx or fallopian-tube section. | This conflicts with HPA's High cilia-axoneme staining in those tissues (HPA: tissue IHC). First confirm that ciliated cells are present in the section; then assess antibody, retrieval and detection performance with appropriate run controls (general IHC practice). An absent signal in one run does not establish biological absence. |
| Tissue and cell selection | Use ciliated epithelium in bronchus, nasopharynx or fallopian tube to assess the defining axonemal pattern (HPA: High in ciliated-cell cilia axoneme). Efferent-duct ciliated cells are another High-staining population, while adrenal, breast and endometrial glandular cells are Medium (HPA: tissue IHC). Compare named cell populations, since an HPA tissue page does not imply every cell in that tissue stains. |
| Validation and strength of inference | HPA lists one antibody, HPA035508, with IHC Approved status (HPA: antibodies). Its tissue assessment reports low consistency with RNA expression and pending external verification (HPA: reliability). Treat the published pattern as a working expectation and weigh morphology and controls before making a biological claim; Approved does not remove the reported caveat. |
| TRANK1 topology and processing | UniProt annotates no transmembrane segment, signal peptide, propeptide, glycosylation site or modified residue, and lists a single chain spanning residues 1–2925 (UniProt O15050 record). These annotations offer no basis to predict a membrane-restricted IHC pattern or a processing-dependent staining difference. No target-specific fixation effect follows from them (UniProt O15050 record). |
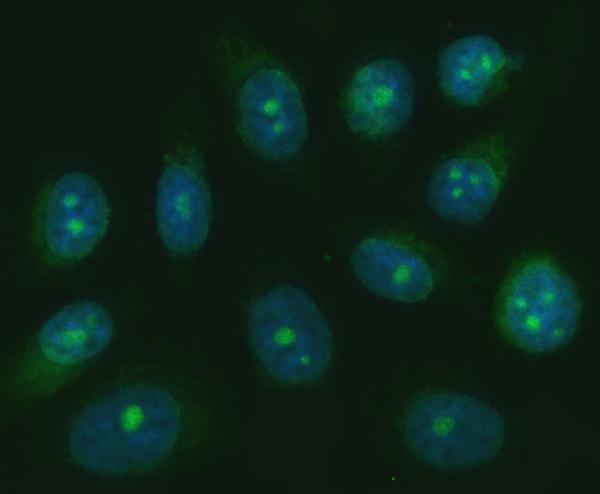
| IF/ICC Q&A: should nuclear fluorescence change the IHC call? | HPA reports nucleoplasm as the main approved ICC-IF location and cytosol as an additional approved location (HPA: subcellular ICC-IF). Interpret that observation in its own assay; the tissue IHC comparison remains the ciliary and cytoplasmic pattern reported by HPA (HPA: tissue IHC). UniProt provides no subcellular annotation to resolve the difference (UniProt O15050 record). |
| Situation | Likely cause | Next action |
|---|---|---|
| No stain appears in the intended positive section. | The section may lack intact ciliated cells, or the IHC detection run may have failed (general IHC practice). HPA reports High axonemal staining in bronchus, nasopharynx and fallopian tube (HPA: tissue IHC). | Locate preserved cilia on the counterstained section, then check run controls, antibody application, retrieval and chromogen steps (general IHC practice). Record the missing control pattern before interpreting the specimen as negative. |
| Brown product fills epithelium but individual cilia cannot be resolved. | Excess background or heavy development can obscure the fine axonemal pattern (general IHC practice). The expected location is the cilia axoneme in several High-staining tissues (HPA: tissue IHC). | Examine a lighter-developed or better-separated area; review primary-antibody concentration, wash steps and development time with run controls (general IHC practice). Score localisation only where morphology remains readable. |
| Negative-control areas or blank regions also develop colour. | Endogenous detection activity or reagent background may contribute signal (general IHC practice). A control-area signal does not support the HPA cell-restricted pattern (HPA: tissue IHC). | Compare primary-antibody omission and detection controls; review blocking and detection chemistry for the system used (general IHC practice). Do not count colour shared with those controls as specific TRANK1 staining. |
| A listed negative population stains strongly. | Cross-reactivity, background or a biological difference may be involved; the slide alone cannot distinguish them. HPA lists alveolar cells, adipocytes and several other named populations as Not detected (HPA: tissue IHC). | Verify the cell identity, compare matched controls and assess whether the stain also occurs in a cilia-positive reference (general IHC practice). Report disagreement with the HPA reference instead of assigning a cause from intensity alone. |
| Staining is predominantly nuclear in tissue IHC. | The observed compartment differs from HPA's defining axonemal tissue pattern (HPA: tissue IHC), although approved nucleoplasmic staining is reported for ICC-IF (HPA: subcellular ICC-IF). | Keep the IHC and ICC-IF observations distinct. Check section morphology, counterstain and assay controls before deciding whether nuclear IHC signal is interpretable (general IHC practice). |
| Two acceptable sections give different staining intensities. | Cell composition and staining-run variation can alter the appearance of a section (general IHC practice). HPA reports High, Medium, Low and Not detected levels in different named cell populations (HPA: tissue IHC). | Compare the same cell type and compartment, then review controls from each run (general IHC practice). Document tissue and cell identity alongside intensity; avoid treating unlike cell populations as equivalent replicates. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Low consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Bronchus | Ciliated cells (cilia axoneme) | High | Protein (IHC) | HPA → |
| Choroid plexus | Ependymal cells | High | Protein (IHC) | HPA → |
| Efferent ducts | Ciliated cells | High | Protein (IHC) | HPA → |
| Fallopian tube | Ciliated cells (cilia axoneme) | High | Protein (IHC) | HPA → |
| Nasopharynx | Ciliated cells (cilia axoneme) | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Cerebral cortex | Endothelial cells | Not detected | Protein (IHC) | HPA → |
| Esophagus | Squamous epithelial cells | Not detected | Protein (IHC) | HPA → |
| Heart muscle | Cardiomyocytes | Not detected | Protein (IHC) | HPA → |
Use matched controls and compartment-aware scoring to troubleshoot TRANK1 staining in paraffin sections; interpret tissue patterns alongside the reported limits of antibody evidence.
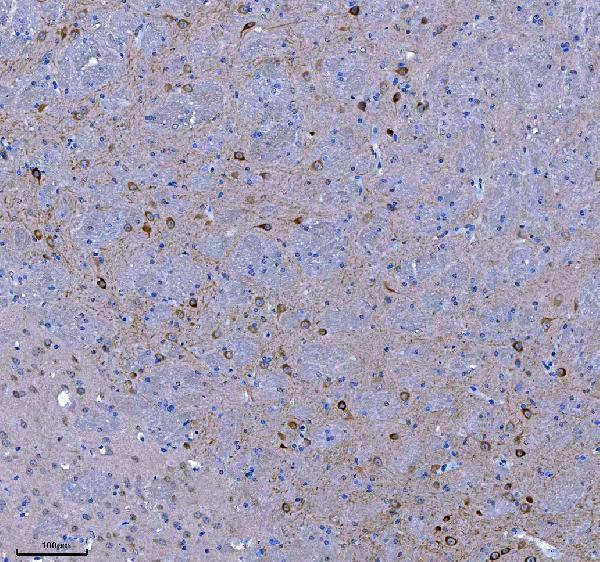
Anti-TRANK1 antibody A09518 has IHC images from paraffin-embedded human liver cancer and mouse and rat brain tissue, plus IF images from those tissues and PC-3 cells (A09518 image captions).
A09518 is listed for IHC and IF/ICC in human, mouse and rat (A09518 catalog applications and reactivity). Its IHC images show paraffin-embedded human liver cancer and mouse and rat brain tissue; its IF images also show PC-3 cells (A09518 image captions).
Which to pick: Choose A09518 for paraffin-section IHC: its captions document EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody (A09518 IHC image captions). The same SKU supports IF/ICC at 5 μg/ml, with IF images from PC-3 cells and paraffin-embedded tissue (A09518 catalog applications and IF image captions). For cross-species IHC, A09518 lists human, mouse and rat reactivity and shows IHC in all three; the IHC captions do not report the fixative (A09518 catalog reactivity and IHC image captions).