This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Start paraffin-section TRIM68 IHC with the catalog antibody at 1:100 (datasheet: IHC image). Compare high staining in adrenal gland glandular cells with undetected staining in spleen red-pulp cells, while accounting for uncertain tissue-IHC reliability (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Tissue: cytoplasmic (HPA tissue IHC); molecular: nuclear/perinuclear (UniProt) | |
| Staining pattern | General cytoplasmic staining across tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | Tris-EDTA pH 9.0 HIER, 95–98 °C, 20 min (rule: nuclear antigen) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Spleen |
| Fixation | Keep fixation conditions consistent across paraffin sections (standard IHC practice; not target-specific) | |
| Caveat | Tissue staining has uncertain RNA consistency (HPA tissue IHC) | |
| Regulation | Androgen-dependent up-regulation possible (UniProt) | |
| Isoform / epitope | 2 isoforms; intracellular epitope coverage needs checking (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet) is accompanied by one published TRIM68 tissue-staining workflow (PMC8101494).
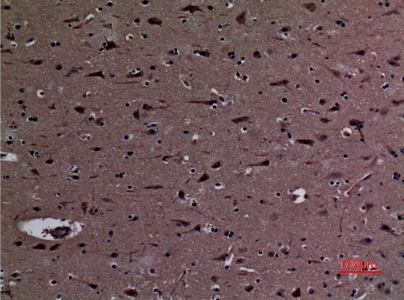
| Sample | Paraffin-embedded human brain tissue; fixative not specified (datasheet A11532) |
| Fixation | Image fixative and duration unreported (datasheet A11532); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat-induced epitope retrieval in Tris-EDTA buffer, pH 9.0, 20 min at 95–98 °C (standard rule: nuclear antigen) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% normal serum of the secondary host, 30 min, room temperature (standard) |
| Primary antibody | Rabbit anti-TRIM68, 1:100 (datasheet A11532) |
| Primary incubation | Overnight at 4 °C (standard) |
| Detection | HRP-polymer secondary, DAB chromogen 5–10 min (standard) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | TRIM68-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control. |
TRIM68 is expected mainly in cytoplasm, sometimes near the nucleus, and may also appear in nuclei (UniProt Q6AZZ1); ICC-IF supports nucleoplasmic and cytosolic localization (HPA: ICC-IF supported). In paraffin-section IHC, look first at glandular and respiratory epithelial cells and selected glial cells reported as high (HPA: tissue IHC). Treat intensity as a guide rather than a guarantee: the tissue IHC profile has uncertain reliability (HPA: tissue IHC, Uncertain).
| Cytoplasmic staining, with possible nuclear staining, in glandular or respiratory epithelial cells. | This fits the reported general cytoplasmic tissue profile (HPA: tissue IHC) and cytoplasmic plus nuclear localization (UniProt Q6AZZ1). Score the two compartments separately; nuclear signal can be plausible and need not match cytoplasmic intensity in every cell (UniProt Q6AZZ1). |
| Strong signal confined to cell borders, lumina, or extracellular material, with little intracellular staining. | That distribution does not fit the reported cytoplasmic, nuclear, or nucleoplasmic locations (UniProt Q6AZZ1; HPA: tissue IHC and ICC-IF). Check morphology, the negative reagent control, and chromogen deposits before assigning it to TRIM68 (standard IHC practice). |
| Prominent staining in spleen red-pulp cells while the expected intracellular pattern is absent. | HPA reports TRIM68 as not detected in spleen red-pulp cells (HPA: tissue IHC). Consider cross-reactivity or endogenous chromogenic activity, especially if the staining also appears in a no-primary control (standard IHC practice). The HPA IHC profile is uncertain, so this is a warning sign, not proof of nonspecificity (HPA: tissue IHC, Uncertain). |
| Uniform haze across cells, stroma, and blank areas, obscuring cell boundaries. | A slide-wide haze is difficult to reconcile with a localized intracellular result (UniProt Q6AZZ1; HPA: tissue IHC). Review blocking, wash steps, antibody concentration, and detection controls as general IHC background checks (standard IHC practice). Do not score the haze as a TRIM68-positive cell population. |
| No intracellular signal in a section containing intact adrenal glandular or bronchial respiratory epithelial cells. | Both cell populations were reported as high in HPA tissue IHC (HPA: adrenal gland and bronchus), so first check section quality and whether the detection run worked (standard IHC practice). A negative result alone does not overturn target expression: HPA rates this IHC profile uncertain, and individual samples may differ (HPA: tissue IHC, Uncertain). |
| Tissue and cell selection | HPA reports high staining in several glandular populations, bronchial respiratory epithelium, and selected brain cells; spleen red-pulp cells were not detected (HPA: tissue IHC). Use cell-level morphology when comparing sections, since HPA also describes low tissue RNA specificity and uncertain IHC reliability (HPA: tissue IHC). |
| Compartment assignment | UniProt lists cytoplasm, including the perinuclear region, and nucleus (UniProt Q6AZZ1). Supported ICC-IF locations are nucleoplasm and cytosol (HPA: ICC-IF). In chromogenic IHC, identify nuclei with a counterstain before deciding whether color is nuclear, perinuclear, or overlapping cytoplasm (standard IHC practice). |
| Isoforms and antibody epitope | Two isoforms are listed (UniProt Q6AZZ1). The supplied record gives no antibody epitope or isoform coverage, so an isoform-specific explanation for tissue differences cannot be assigned. Compare staining with the antibody's stated validation and the observed cell morphology (HPA: HPA023455 IHC Uncertain; standard IHC practice). |
| IHC evidence strength | The HPA tissue profile is rated Uncertain, with medium consistency between antibody staining and RNA expression; HPA023455 is also IHC Uncertain (HPA: tissue IHC and antibodies). Treat the listed high and undetected categories as reference observations, and require appropriate slide controls before interpreting an unexpected result (standard IHC practice). |
| ICC-IF Q: Should its location establish an IHC result? | A: ICC-IF supports nucleoplasm and cytosol, and HPA023455 is ICC Supported (HPA: ICC-IF and antibodies). This helps assess plausible compartments, but tissue IHC remains Uncertain (HPA: tissue IHC and antibodies); evaluate paraffin-section staining on its own controls. |
| Situation | Likely cause | Next action |
|---|---|---|
| Expected positive cells are blank. | The detection run or tissue preservation may have failed; a single negative section is inconclusive (standard IHC practice). | Check a run-level positive control and morphology, then review retrieval and detection conditions as general IHC steps (standard IHC practice). Compare with HPA high cell populations cautiously because tissue IHC reliability is Uncertain (HPA: tissue IHC). |
| Color appears mainly on cell edges or in lumina. | The pattern conflicts with reported intracellular locations (UniProt Q6AZZ1; HPA: ICC-IF). Deposited chromogen or nonspecific binding is possible (standard IHC practice). | Inspect a no-primary control and adjacent morphology; repeat staining only after identifying whether the signal follows cells or extracellular material (standard IHC practice). |
| Spleen red-pulp cells stain strongly. | HPA lists these cells as not detected (HPA: tissue IHC); endogenous detection activity or antibody cross-reactivity could contribute (standard IHC practice). | Compare a no-primary control and assess endogenous enzyme blocking for the chromogenic system (standard IHC practice). Interpret the discrepancy cautiously because the HPA tissue IHC profile is Uncertain (HPA: tissue IHC). |
| The whole section has diffuse brown background. | Excess reagent, incomplete washing, or endogenous detection activity can obscure cellular staining (standard IHC practice). | Check reagent controls, wash steps, blocking, and the working antibody concentration (standard IHC practice). Score TRIM68 only where signal resolves into the intracellular pattern supported by UniProt and HPA (UniProt Q6AZZ1; HPA: tissue IHC). |
| Nuclear signal seems unexpectedly strong. | Nuclear localization is plausible; UniProt also reports colocalization with AR in nuclei (UniProt Q6AZZ1). The IHC tissue profile does not establish a required nuclear intensity (HPA: tissue IHC). | Use the counterstain to confirm that color lies within nuclei, compare the cytoplasmic signal, and review controls before calling it artefact (standard IHC practice). |
| Different tissues give inconsistent intensities. | HPA reports both high and undetected cell populations while rating its tissue IHC profile Uncertain (HPA: tissue IHC). | Record tissue, cell type, compartment, and staining intensity separately; compare matched controls and avoid treating one HPA intensity category as a universal threshold (HPA: tissue IHC; standard IHC practice). |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Breast | Glandular cells | High | Protein (IHC) | HPA → |
| Bronchus | Respiratory epithelial cells | High | Protein (IHC) | HPA → |
| Caudate | Glial cells | High | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Spleen | Cells in red pulp | Not detected | Protein (IHC) | HPA → |
Troubleshoot TRIM68 chromogenic IHC in paraffin sections using the selected image, the page retrieval setting, and compartment and tissue evidence (caption A11532; page setting; UniProt Q6AZZ1; HPA).
A11532 has a real IHC image from a paraffin-embedded human brain section; IF is listed as an application, and human and mouse are listed as reactive species (catalog applications, reactivity and IHC image caption).
A11532 will render with an IHC image of paraffin-embedded human brain at 1:100 (A11532 IHC image caption). Its catalog lists IF and human and mouse reactivity, but provides no IF image (A11532 applications, reactivity and IF image alts).
Which to pick: Choose A11532 for paraffin-section tissue IHC because its own image caption documents human brain staining at 1:100; the fixative is unreported (A11532 IHC image caption). For IF/ICC, A11532 lists IF at 1:50, but ICC is not listed and no IF image is supplied (A11532 applications, IF dilution and IF image alts). A11532 is the cross-species candidate because the polyclonal antibody lists human and mouse reactivity; its IHC image documents human tissue only (A11532 dilution_raw, reactivity and IHC image caption).