TTK / Dual specificity protein kinase TTK · IHC design guide

Design Immunohistochemistry for TTK

Assess TTK staining in paraffin sections using lymph node germinal center cells as a positive reference (HPA tissue IHC). This guide covers the catalog antibody’s 0.5–1 μg/mL IHC range (datasheet A01132-1) and how to interpret its cytoplasmic tissue pattern (HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for TTK (IHC for TTK): expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC), antibody A01132-1, validated IHC image, and IHC protocol steps
Printable TTK IHC protocol sheet — expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC), antibody A01132-1, controls and protocol steps. Open the full TTK IHC guide →

TTK Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining in several cell types (HPA tissue IHC)
Staining pattern Cytoplasmic staining, most abundant in proliferative cells (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01132-1)
Positive control ⓘ Epididymis+4 more · see all
Negative control ⓘ Adipose tissue+4 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent (standard IHC practice; not target-specific)
Caveat Proliferative-cell abundance can shift staining (HPA tissue IHC)
Regulation Enriched in proliferative cells (HPA tissue IHC)
Isoform / epitope Two isoforms; check epitope coverage across both (UniProt)
Section 1

Recommended TTK IHC & IF Protocols

The catalog antibody’s IHC-P protocol uses EDTA pH 8.0 retrieval (datasheet A01132-1). The published TTK IHC protocols below provide tissue-specific preparation, staining, and scoring details (PMC4453723; PMC8721040; PMC13163004).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human rectal cancer tissue; fixative not specified (datasheet A01132-1)
FixationImage fixative and duration unreported (datasheet A01132-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01132-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01132-1)
Primary antibodyRabbit anti-TTK, 0.5-1μg/ml (datasheet A01132-1)
Primary incubationOvernight at 4 °C (datasheet A01132-1)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A01132-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
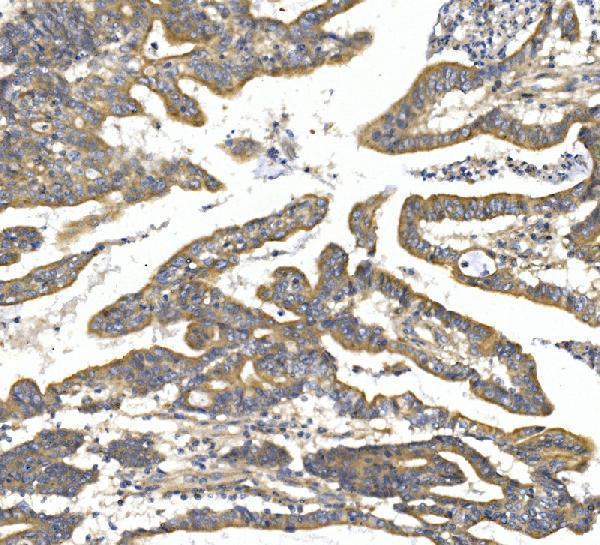
Expected resultTTK-positive staining in glandular cells of epididymis (HPA tissue IHC: High). HPA tissue profile: Cytoplasmic expression in several different cell types, most abundant in highly proliferative cells. No signal in the no-primary control.
💡Decision noteStart with heat-mediated EDTA pH 8.0 retrieval for the catalog antibody (datasheet A01132-1); a published TTK IHC protocol used EDTA pH 9.0 (PMC13163004).
Section 2

What Is the Expected TTK Staining Pattern?

In paraffin-section IHC, expect predominantly cytoplasmic TTK staining, most conspicuous in highly proliferative cells, including germinal center cells and pachytene spermatocytes (HPA: tissue IHC). HPA rates the tissue pattern Enhanced, but reports medium agreement with RNA expression and pending retesting (HPA: tissue IHC). TTK has no annotated transmembrane segment; UniProt does not assign it a subcellular location (UniProt P33981: topology and subcellular annotation).

What am I looking at on my slide?
Cytoplasmic staining in tonsil or lymph-node germinal center cells, with weaker surrounding cells.This fits the reported distribution: germinal center cells stain High, and the overall IHC profile favors highly proliferative cells (HPA: tissue IHC). Compare cells within the same section before judging intensity; HPA levels describe observed staining, not an absolute scoring threshold.
A predominantly nuclear or membranous IHC signal with little cytoplasmic staining.Review compartment assignment and controls before calling this TTK. HPA describes cytoplasmic tissue staining, while UniProt lists no transmembrane segment (HPA: tissue IHC; UniProt P33981: topology). An unexpected compartment can indicate nonspecific detection; it is not, by itself, proof of an artefact.
Strong staining in adipocytes, cardiomyocytes, or smooth muscle cells.These cell types are reported as Not detected (HPA: tissue IHC). Check whether the signal follows tissue pigment, endogenous enzyme activity, or nonspecific antibody binding (general chromogenic IHC practice). An unexpected positive warrants controls before being interpreted as TTK.
A uniform haze across cells and surrounding tissue that obscures cell boundaries.This does not resolve the reported cell-selective cytoplasmic pattern (HPA: tissue IHC). Assess background with an appropriate negative reagent control, then review blocking, wash steps, detection chemistry, and primary-antibody concentration (general IHC practice).
No staining in a well-preserved tonsil germinal center or testis pachytene-spermatocyte control.Both cell populations are reported High and can serve as positive-reference areas (HPA: tissue IHC). First confirm that the expected cells are present; then check the assay controls and the antibody's documented IHC-P conditions (general IHC practice). A failed control leaves the sample result uninterpretable.
💡Expected TTK appearanceCall the result consistent with TTK when distinct cytoplasmic staining is strongest in HPA-reported High cell populations, such as tonsil germinal center cells or testis pachytene spermatocytes; diffuse haze or strong staining in HPA-reported Not detected cells calls for control review (HPA: tissue IHC; general IHC practice).
How each factor affects the staining
Tissue and cell selectionHPA reports High staining in tonsil and lymph-node germinal center cells, testis pachytene spermatocytes, and epididymal and rectal glandular cells; adipocytes, cardiomyocytes, and smooth muscle cells are Not detected (HPA: tissue IHC). Score the named cell population, not the whole tissue.
Strength of tissue evidenceThe tissue IHC assessment is Enhanced, with medium consistency between antibody staining and RNA expression and retesting pending (HPA: tissue IHC). Treat the reported pattern as a useful reference rather than a guarantee for every section or antibody.
IHC versus IF/ICC compartmentQ: Should IF/ICC show only the IHC pattern? A: HPA reports cytosol as the approved main IF/ICC location and nucleoli as an approved additional location; its tissue IHC summary describes cytoplasmic staining (HPA: subcellular ICC-IF; HPA: tissue IHC). Interpret the two applications separately.
Antibody validation and isoformsCAB013229 has Enhanced IHC status, whereas HPA058657 and CAB010166 have Approved ICC status without a listed IHC status (HPA: antibodies). UniProt lists two TTK isoforms; epitope coverage for a chosen antibody is not supplied here (UniProt P33981: isoforms).
Antigen retrieval and epitope accessRetrieval conditions should follow the selected antibody's documented IHC-P method and be checked against controls (general IHC practice). The supplied HPA and UniProt records do not establish a TTK-specific retrieval requirement or fixation sensitivity.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Positive-reference germinal center cells are blank.The expected cell population may be absent from the section, or the IHC assay may have failed (HPA: High in germinal center cells; general IHC practice).Confirm germinal centers on the counterstained section, then review the IHC-validated antibody's documented conditions, retrieval, detection reagents, and a working positive control (general IHC practice).
All tissue compartments show similar chromogen.Diffuse nonspecific binding or detection background may be overwhelming the cell-selective pattern (HPA: tissue IHC; general IHC practice).Run a negative reagent control and inspect blocking, washes, detection chemistry, and primary-antibody concentration under the documented IHC-P method (general IHC practice).
Strong color appears in HPA-reported Not detected cells.Possible cross-reactivity, endogenous detection activity, or misleading pigment should be considered; HPA reports no detectable staining in those named cells (HPA: tissue IHC; general chromogenic IHC practice).Compare with a negative reagent control and with an HPA-reported High cell population on a matched run; inspect whether color follows cells, pigment, or background (general IHC practice).
Signal appears mainly membranous or nuclear in IHC.The compartment conflicts with HPA's cytoplasmic tissue summary; a membrane interpretation also lacks support from UniProt topology (HPA: tissue IHC; UniProt P33981: topology).Recheck morphology and counterstain, examine a positive-reference cell population, and verify the IHC-validated antibody's documented application before assigning localisation (general IHC practice).
IF/ICC shows cytosol plus nucleoli, while IHC appears cytoplasmic.Those findings can coexist: HPA approves cytosol as the main ICC-IF location and nucleoli as an additional location, while summarizing tissue IHC as cytoplasmic (HPA: subcellular ICC-IF; HPA: tissue IHC).Record application and compartment separately. Consult the dedicated IF/ICC guide for that application's controls; do not infer an IHC-P condition from ICC approval (HPA: antibodies; general assay practice).
A sample is weak while its positive-reference tissue stains.TTK staining varies by tissue and cell population; HPA includes Medium, Low, and Not detected categories alongside High populations (HPA: tissue IHC).Identify the sample's cell type and compare with its HPA tissue category before interpreting weak signal. Keep the successful positive control in view and avoid assigning a negative result from intensity alone (HPA: tissue IHC; general IHC practice).

Sample controls for TTK IHC & IF

🧪Run rectum first and score its glandular cells for TTK staining (HPA: High in rectal glandular cells). Use adipose tissue adipocytes as the negative tissue (HPA: Not detected in adipocytes); on the rectal slide, use nonglandular cells as an internal background reference only where they lack staining, since HPA does not assign them a TTK level.
Positive control tissue: Epididymis (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show TTK in A-431, U-251MG, U2OS, RPTEC/TERT1, with annotated localisation: Cytosol (approved) (HPA subcellular).
Technical controls: Include no-primary (secondary-only) and concentration-matched rabbit IgG isotype controls, plus TTK-knockout material as a biological negative where available (selected IHC caption: rabbit primary; standard IHC practice). For the caption’s biotin-based DAB detection, block endogenous peroxidase and assess endogenous biotin background on the rectal section (selected IHC caption: streptavidin–biotin detection with DAB; standard IHC practice).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the exact A01132-1 paraffin-section caption does not state a fixative (selected IHC caption). Heat retrieval in EDTA at pH 8.0 is a documented IHC starting condition, but the evidence does not establish that retrieval is required (selected IHC caption). Frozen sections and IF are not established as easier alternatives; HPA has ICC-IF images, while endogenous peroxidase or biotin background remains a practical concern for the caption’s chromogenic detection (HPA: ICC-IF images; selected IHC caption: streptavidin–biotin with DAB; standard IHC practice).

HPA tissue IHC evidence for TTK

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Pending retesting.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Epididymis Glandular cells High Protein (IHC) HPA →
Lymph node Germinal center cells High Protein (IHC) HPA →
Rectum Glandular cells High Protein (IHC) HPA →
Testis Pachytene spermatocytes High Protein (IHC) HPA →
Tonsil Germinal center cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Adrenal gland Glandular cells Not detected Protein (IHC) HPA →
Cerebellum Cells in granular layer Not detected Protein (IHC) HPA →
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Liver Cholangiocytes Not detected Protein (IHC) HPA →
Section 3

Advanced TTK IHC Tips

Troubleshoot TTK staining in paraffin sections by checking retrieval, cell type, compartment and controls before comparing signal across samples.

What should I change if TTK staining is weak after antigen retrieval?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (A01132-1 tissue-IHC caption). The selected image used 1 μg/ml primary antibody overnight at 4°C, so check those conditions before changing retrieval (A01132-1 tissue-IHC caption). If signal remains weak, compare a cautiously adjusted heating time with the original condition on adjacent sections, keeping detection and exposure comparable (standard IHC practice). Include a responsive control such as rectal glandular cells, reported as High, and inspect tissue preservation alongside staining (HPA tissue IHC: Rectum). An alternate buffer can be tested as a fallback, but it has no support from this selected image (A01132-1 tissue-IHC caption).
Can fixation explain weak or uneven TTK staining in paraffin sections?
Target-specific fixation sensitivity is unknown: the selected paraffin-section image does not state its fixative (A01132-1 tissue-IHC caption). Record the fixative, fixation duration and processing history for each specimen, then compare sections processed together before attributing differences to TTK abundance (standard IHC practice). Assess morphology and staining at the tissue edge and center, since uneven processing can produce misleading gradients (standard IHC practice). Use the documented EDTA pH 8.0 retrieval and 1 μg/ml primary condition as comparison points, while keeping detection constant (A01132-1 tissue-IHC caption). HPA tissue patterns cannot establish how this antibody responds to a particular fixative (HPA tissue IHC).
How should I interpret cytoplasmic and nuclear TTK staining?
Expect predominantly cytoplasmic staining across several cell types, especially highly proliferative cells (HPA tissue IHC: profile). Cell imaging places TTK mainly in the cytosol, with an additional nucleolar location; its reviewed UniProt record supplies no subcellular annotation (HPA subcellular; UniProt P33981). Examine nuclear detail against the counterstain before calling a nucleolar signal, and score cytoplasmic and nucleolar staining separately (standard IHC practice). TTK has no annotated transmembrane segment, so a crisp cell-surface-only pattern needs scrutiny with controls (UniProt P33981 topology). Its spindle-checkpoint role supplies biological context but does not prove the position of every chromogenic deposit (UniProt P33981 function).
Could isoforms or epitope accessibility change TTK staining?
TTK has 2 listed isoforms and a protein kinase domain at residues 525–791 (UniProt P33981). The supplied antibody image identifies neither its binding epitope nor isoform coverage, so staining cannot establish which isoform is present (A01132-1 tissue-IHC caption). TTK also has annotated modified residues, including phosphorylation near its N terminus; whether these affect this antibody is unknown (UniProt P33981). If staining differs across samples, check the antibody's epitope documentation and compare matched sections under the same retrieval and detection conditions (standard IHC practice). Interpret an absent signal as a staining result until epitope accessibility and tissue quality have been assessed (standard IHC practice).
How can I check TTK localisation by IF alongside tissue IHC?
Use IF as a separate localisation check: cell images place TTK mainly in the cytosol and additionally in nucleoli (HPA subcellular). Multiplex TTK with a marker identifying the expected cell population, such as a germinal-center cell marker when examining lymphoid tissue (HPA tissue IHC: Lymph node and Tonsil). Choose spectrally separated fluorophores after checking the specimen's autofluorescence, and include single-channel controls to assess bleed-through (standard IF practice). TTK lacks a transmembrane segment, so permeabilise for access to its intracellular epitopes while confirming that the chosen marker remains detectable (UniProt P33981 topology; standard IF practice). The paraffin-section caption does not establish IF fixation or permeabilisation conditions (A01132-1 tissue-IHC caption).
What controls distinguish TTK signal from chromogenic background?
Inspect a no-primary control for secondary-reagent or endogenous-enzyme staining, especially before interpreting diffuse brown deposits as TTK (standard chromogenic IHC practice). In peroxidase-based detection, include a peroxidase block and assess DAB development time as general workflow controls (standard chromogenic IHC practice). The selected image used 10% goat serum block, a biotinylated goat anti-rabbit secondary, streptavidin-biotin detection and DAB (A01132-1 tissue-IHC caption). Compare cell-rich regions with matched morphology and watch for pigment, necrosis and tissue-edge staining that persists in controls (standard IHC practice). A cytoplasmic pattern is more consistent with the reported tissue profile than isolated extracellular deposit (HPA tissue IHC: profile).
How should I quantify TTK staining across tissue sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since HPA reports cytoplasmic expression most abundant in highly proliferative cells (HPA tissue IHC: profile). For comparable sections, report the percentage of positive cells and an intensity-based H-score from 0–300, using consistent thresholds and blinded review (standard IHC practice). If positive cells are sparse, add their density per mm² of viable tissue and record the analyzed area (standard IHC practice). Normalize cell counts to the number of evaluable cells in the chosen compartment, or density to viable tissue area, excluding necrosis and folds (standard IHC practice). Keep retrieval and detection conditions consistent across the comparison set (standard IHC practice).
When is a TTK-positive stain credible rather than artefactual?
A credible result has interpretable cell morphology, a plausible intracellular pattern and appropriate control behavior (HPA tissue IHC: profile; HPA subcellular; standard IHC practice). High staining in lymph-node germinal-center cells or rectal glandular cells provides a useful tissue comparison, while cardiomyocytes are reported as Not detected (HPA tissue IHC: Lymph node, Rectum and Heart muscle). Scrutinize staining confined to tissue edges, necrosis or extracellular material, and deposits reproduced in the no-primary control (standard IHC practice). A surface-only pattern conflicts with the absence of a transmembrane segment and warrants further checking (UniProt P33981 topology). HPA rates its tissue-IHC evidence Enhanced but reports medium RNA consistency and pending retesting, so corroborate unexpected patterns independently (HPA tissue IHC: reliability).
Boster reagents

Best TTK / Dual specificity protein kinase TTK IHC Antibodies

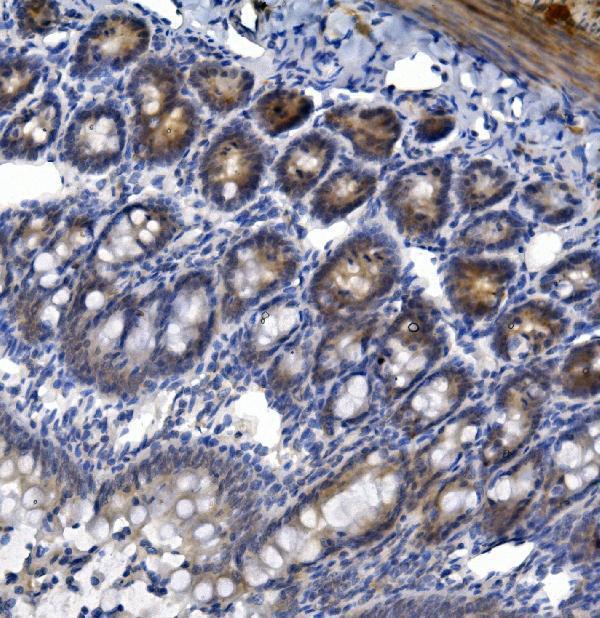
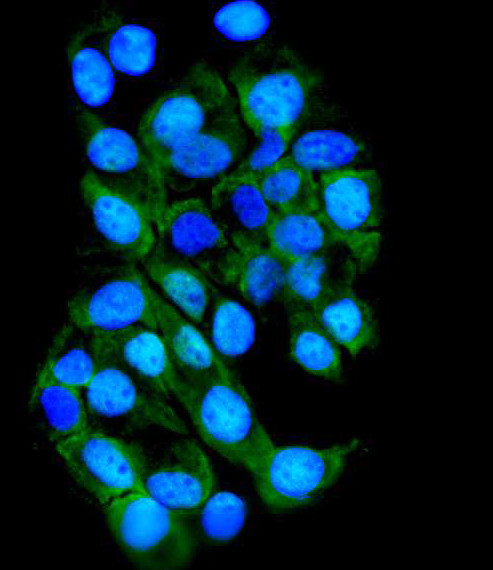
A01132-1 has IHC images from paraffin sections of human rectal cancer and rat intestine (catalog: IHC image captions), plus an IF image from A431 cells (catalog: IF image caption).

Real IHC data IHC analysis of TTK using anti-TTK antibody (A01132-1). TTK was detected in paraffin-embedded section of human rectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-TTK Antibody (A01132-1) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-TTK/Mps1/TTK Antibody ®
Cat # A01132-1

A01132-1 is listed for IHC, IF and ICC; its IHC images show paraffin sections of human rectal cancer and rat intestine (catalog: applications; IHC image captions). Its IF image shows A431 cells, while its listed reactivity covers human, mouse and rat (catalog: IF image caption; reactivity).

Which to pick: Choose A01132-1 for paraffin tissue IHC: its own captions show EDTA retrieval at pH 8.0 and 1 μg/ml primary antibody in human rectal cancer and rat intestine; the fixative is unreported (catalog: IHC image captions). For IF/ICC, the same SKU has an A431 cell IF image and a listed IF/ICC concentration of 2 μg/ml for human samples (catalog: IF image caption; dilution_raw). For cross-species work, A01132-1 lists human, mouse and rat reactivity, but its IHC dilution is specified for human and rat and its IF/ICC dilution for human; clonality is unreported.

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P33981 (TTK_HUMAN, Dual specificity protein kinase TTK).
  2. Human Protein Atlas. TTK tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. TTK subcellular location (ICC-IF): Mainly localized to the cytosol. In addition localized to the nucleoli..
  4. Human Protein Atlas. TTK antibody validation summary (3 antibodies).
  5. TTK is a favorable prognostic biomarker for triple-negative breast cancer survival. Oncotarget 2016 — PMC5348432.
  6. Key role of dual specificity kinase TTK in proliferation and survival of pancreatic cancer cells. British journal of cancer 2014 — PMC4453723.
  7. Identification and Validation of Hub Genes Associated with Bladder Cancer by Integrated Bioinformatics and Experimental Assays. Frontiers in oncology 2021 — PMC8721040.
  8. NFYA-Mediated TTK Up-Regulation Drives Fast Cell Cycle Progression and Its Inhibition Leads to Mitotic Catastrophe in Triple Negative Breast Cancer. Cancers 2026 — PMC13163004.
  9. PubMed PMID:1639825 — UniProt-cited evidence.
  10. PubMed PMID:14702039 — UniProt-cited evidence.
  11. PubMed PMID:14574404 — UniProt-cited evidence.