This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan USP9X paraffin IHC using the catalog antibody at 1:50 as a starting dilution (datasheet M02594-1). Assess granular cytoplasmic staining across tissues and account for cell types reported as undetected (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Granular cytoplasmic staining in tissue (HPA tissue IHC) | |
| Staining pattern | Granular cytoplasm across tissue cell types (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M02594-1) | |
| Positive control | Adrenal gland+4 more · see all | |
| Negative control | Heart muscle+1 more · see all |
| Fixation | Keep fixation conditions consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Cardiomyocytes and smooth muscle cells may lack signal (HPA tissue IHC) | |
| Regulation | Widely expressed in embryonic and adult tissues (UniProt) | |
| Isoform / epitope | 2 isoforms; verify antibody epitope coverage (UniProt) |
The catalog antibody’s IHC-P protocol is paired with four published USP9X IHC protocols for comparing sample preparation, staining, and detection (datasheet M02594-1; PMC13346229; PMC6568031; PMC4016599; PMC5346732).
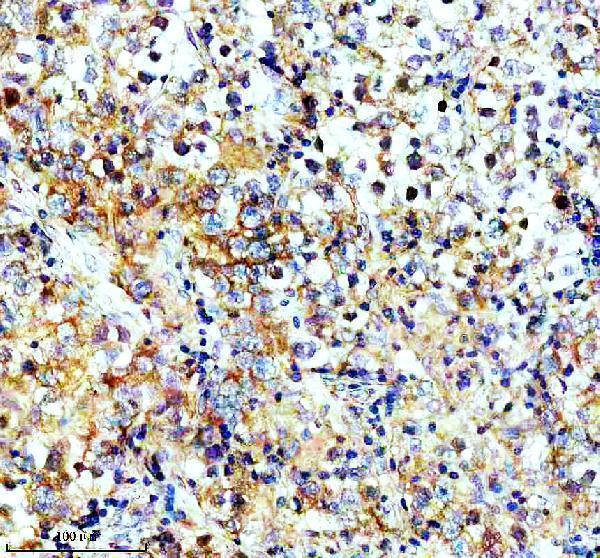
| Sample | Paraffin-embedded human testis cancer tissue; fixative not specified (datasheet M02594-1) |
| Fixation | Image fixative and duration unreported (datasheet M02594-1); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M02594-1); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M02594-1) |
| Primary antibody | Rabbit monoclonal (clone 18U88) anti-USP9X, 1:50 (datasheet M02594-1) |
| Primary incubation | Overnight at 4 °C (datasheet M02594-1) |
| Detection | HRP-conjugated secondary, DAB chromogen (datasheet M02594-1) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | USP9X-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Granular cytoplasmic expression in all tissues. No signal in the no-primary control. |
USP9X should show granular cytoplasmic staining across many tissues, with strong signal in selected glandular, hematopoietic, neuronal and squamous epithelial cells (HPA: tissue IHC). Its reported locations include cytosol, growth cones and cilium axonemes; it has no transmembrane segment (UniProt Q93008: location and topology). HPA rates the tissue IHC profile Approved, with medium agreement between staining and RNA data and external verification pending (HPA: reliability).
| Granular cytoplasmic signal in colon or duodenal glandular cells, marrow hematopoietic cells, or cortical neurons. | This matches reported high staining in these cells (HPA: tissue IHC). Judge the pattern within the identified cell population and alongside tissue controls; signal intensity alone does not establish antibody specificity (general IHC practice). |
| Predominantly nuclear, crisp plasma membrane, or extracellular staining, with little cytoplasmic signal. | This conflicts with the reported granular cytoplasmic IHC pattern and supported cytosolic ICC-IF location (HPA: tissue IHC and subcellular). Check morphology and controls before calling it USP9X; an isolated wrong-compartment pattern may reflect artefact (general IHC practice). |
| Strong signal in cardiomyocytes or smooth muscle cells while expected positive cells are weak. | HPA reports USP9X as not detected in those cell types (HPA: tissue IHC). Consider cross-reactivity or endogenous detection activity, and compare with a reagent-omission control; HPA’s Approved profile still awaits external verification (HPA: reliability; general IHC practice). |
| Uniform colour over cells, stroma and empty areas, obscuring cell boundaries. | That distribution is inconsistent with a cell-associated granular cytoplasmic pattern (HPA: tissue IHC). Diffuse background can arise from nonspecific binding, incomplete washing or detection chemistry; inspect a negative reagent control before scoring cells (general IHC practice). |
| No signal in a well-preserved section of a reported high-staining tissue. | First confirm that the expected cell population is present: HPA reports high staining in adrenal glandular cells, for example (HPA: tissue IHC). Then review section processing, antigen retrieval, reagent performance and detection controls as general IHC checks; this record does not establish USP9X-specific fixation sensitivity. |
| Tissue and cell population | Expression is broad but intensity varies: HPA lists high staining in several glandular populations and neurons, low staining in prostate glandular cells, and no detected staining in cardiomyocytes (HPA: tissue IHC). Choose and score controls by cell type rather than whole-section colour (general IHC practice). |
| Subcellular location and topology | UniProt places USP9X in cytosol, growth cones and cilium axonemes and records no transmembrane segment (UniProt Q93008: location and topology). HPA describes the tissue signal as granular cytoplasmic; neither source supports treating a membrane-only IHC pattern as expected (HPA: tissue IHC). |
| Antibody evidence | CAB011618 and CAB070164 have Approved IHC status (HPA: antibodies). The tissue profile has medium agreement with RNA data and awaits external verification (HPA: reliability), so controls remain necessary when a result departs from the reported pattern (general IHC practice). |
| Isoforms and epitope interpretation | UniProt lists 2 isoforms and a full-length chain spanning residues 1–2554 (UniProt Q93008: isoforms and processing). The supplied sources do not map either antibody’s epitope or show isoform-specific IHC staining; do not assign a tissue pattern to one isoform. |
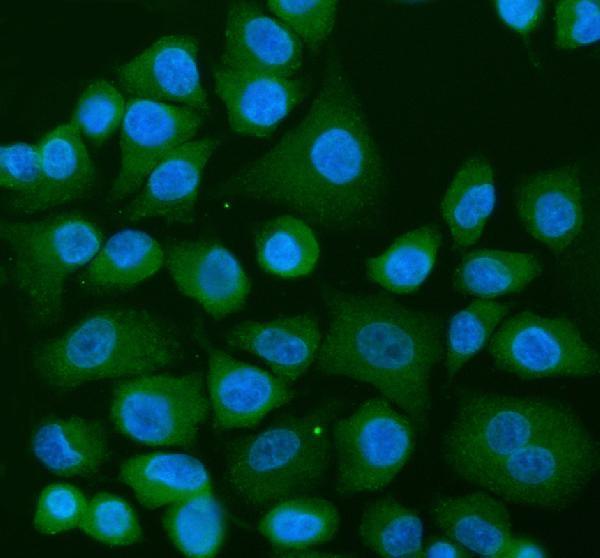
| IF/ICC: should it look similar? | Yes, cytosolic signal is supported in ICC-IF, and CAB011618 has Supported ICC status (HPA: subcellular and antibodies). Compare compartment-level findings cautiously because this section concerns chromogenic IHC in paraffin tissue, while HPA’s ICC-IF evidence comes from cell images. |
| Situation | Likely cause | Next action |
|---|---|---|
| Reported positive glandular cells show no staining. | The expected cells may be absent, or a step in section processing, retrieval or detection may have failed (HPA: high glandular-cell staining; general IHC practice). | Verify cell identity and preservation, then check the catalog antibody’s IHC-P instructions and run appropriate positive and detection controls (general IHC practice). |
| Signal is predominantly nuclear or at the cell surface. | The compartment disagrees with granular cytoplasmic tissue staining and cytosolic ICC-IF localisation (HPA: tissue IHC and subcellular). | Review morphology, staining distribution and reagent-omission controls; interpret the discordant signal cautiously until specificity is supported (general IHC practice). |
| Cardiomyocytes or smooth muscle cells stain strongly. | These cells are reported as not detected by HPA; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; general IHC practice). | Check a reagent-omission control and compare the same run with a cell population reported to stain strongly (HPA: tissue IHC; general IHC practice). |
| Background covers stroma or blank spaces. | The spread of colour differs from cell-associated granular staining; nonspecific binding, washing or detection chemistry may contribute (HPA: tissue IHC; general IHC practice). | Inspect controls, blocking and washes, then adjust general IHC conditions as indicated by the control result (general IHC practice). |
| Signal is weak in prostate glandular cells or ovarian stroma. | Low staining is reported for these populations, so a faint result can agree with the reference pattern (HPA: tissue IHC). | Use a reported high-staining population to assess run performance before changing conditions; score the low-staining cells separately (HPA: tissue IHC; general IHC practice). |
| Two sections differ in staining intensity. | Differences in sampled cell populations can matter because HPA reports both high and low staining across tissues (HPA: tissue IHC). The supplied sources do not establish a USP9X-specific fixation effect. | Compare like cell populations and same-run controls, then review routine processing and detection records if the difference persists (general IHC practice). |

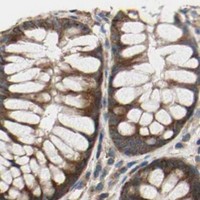


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Approved — Medium consistency between antibody staining and RNA expression data. Pending external verification.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adrenal gland | Glandular cells | High | Protein (IHC) | HPA → |
| Appendix | Glandular cells | High | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | High | Protein (IHC) | HPA → |
| Cerebral cortex | Neuronal cells | High | Protein (IHC) | HPA → |
| Colon | Glandular cells | High | Protein (IHC) | HPA → |
Troubleshoot USP9X staining in paraffin sections using the catalog antibody’s tissue image and reported cytoplasmic localisation (datasheet M02594-1; HPA tissue IHC).
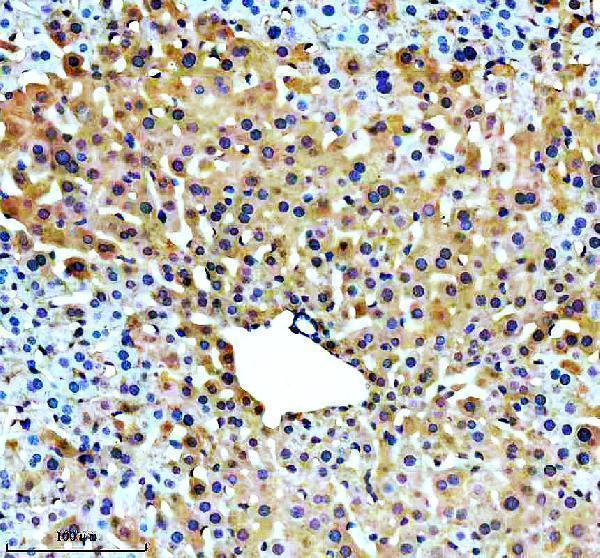
Anti-USP9X antibodies have IHC images from paraffin sections of human testis cancer and mouse liver (M02594-1 IHC captions), and an IF image from A549 cells (A02594-1 IF caption).
M02594-1 lists IHC and has images from paraffin sections of human testis cancer and mouse liver (catalog applications; M02594-1 IHC captions). A02594-1 lists IF/ICC and has an IF image from A549 cells (catalog applications; A02594-1 IF caption).
Which to pick: For tissue IHC, choose M02594-1: it is a rabbit monoclonal with paraffin-section IHC images; the fixative is unreported (catalog host/clone; M02594-1 IHC captions). For IF/ICC, choose A02594-1 for its A549 IF image at 5 μg/mL (A02594-1 IF caption). Both list human, mouse and rat reactivity, while the tissue IHC images show human and mouse samples (catalog reactivity; M02594-1 IHC captions).