VDAC1 / Non-selective voltage-gated ion channel VDAC1 · IHC design guide

Design Immunohistochemistry for VDAC1

Plan chromogenic VDAC1 IHC in paraffin sections using the widespread cytoplasmic staining as a reference pattern (HPA tissue IHC). Lung macrophages and kidney collecting ducts are high-staining positive controls (HPA tissue IHC); the IHC-validated antibody A01168-1 has a stated range of 2–5 μg/mL (datasheet: A01168-1).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for VDAC1 (IHC for VDAC1): expected localisation Cytoplasmic staining (HPA tissue IHC); outer mitochondrial membrane expected (UniProt), antibody A01168-1, validated IHC image, and IHC protocol steps
Printable VDAC1 IHC protocol sheet — expected localisation Cytoplasmic staining (HPA tissue IHC); outer mitochondrial membrane expected (UniProt), antibody A01168-1, controls and protocol steps. Open the full VDAC1 IHC guide →

VDAC1 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Cytoplasmic staining (HPA tissue IHC); outer mitochondrial membrane expected (UniProt)
Staining pattern Widespread cytoplasmic staining; Purkinje cells also show membrane staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A01168-1)
Positive control ⓘ Cerebellum+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific); Matched tissue-IHC evidence does not establish the fixation claim. Validate the specimen-specific method before use. (selected-SKU IHC image A01168-1)
Caveat Ubiquitous staining limits the choice of negative tissue controls (HPA tissue IHC)
Regulation No specific expression regulator reported (UniProt)
Isoform / epitope No annotated isoforms; antibody epitope orientation is unspecified (UniProt)
Section 1

Recommended VDAC1 IHC & IF Protocols

The catalog antibody’s IHC-P protocol (datasheet A01168-1) is followed by three published VDAC1 IHC protocols for breast tissue, oral tissue, and bone marrow smears (PMC7904344; PMC10093190; PMC8808998).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lymphadenoma tissue; fixative not specified (datasheet A01168-1)
FixationImage fixative and duration unreported (datasheet A01168-1); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A01168-1); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A01168-1)
Primary antibodyRabbit anti-VDAC1, 2-5 μg/ml (datasheet A01168-1)
Primary incubationOvernight at 4 °C (datasheet A01168-1)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A01168-1)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultVDAC1-positive staining in purkinje cells - cytoplasm/membrane of cerebellum (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval for the catalog antibody (datasheet A01168-1); the breast tissue study used citrate pH 6.0 (PMC7904344).
Section 2

What Is the Expected VDAC1 Staining Pattern?

VDAC1 should stain predominantly in the cytoplasm, consistent with its mitochondrial outer-membrane location and 19 transmembrane segments (HPA: ubiquitous cytoplasmic expression; UniProt P21796 topology). High staining is reported in lung macrophages, kidney collecting ducts, liver cholangiocytes, and several other cell populations (HPA: tissue IHC). HPA rates the tissue pattern Supported, with medium consistency between antibody staining and RNA expression (HPA: reliability).

What am I looking at on my slide?
Cytoplasmic staining in lung macrophages, kidney collecting ducts, or liver cholangiocytes.These are reported high-staining populations (HPA: tissue IHC). A granular appearance is compatible with mitochondrial localisation, but chromogenic IHC alone cannot identify individual mitochondria (UniProt P21796 subcellular location; general IHC practice).
Strong staining confined to nuclei, with little cytoplasmic signal.A predominantly nuclear pattern conflicts with the reported cytoplasmic tissue staining and membrane localisation (HPA: tissue IHC; UniProt P21796 subcellular location). Assess it as possible artefact; membrane-associated staining alone is not automatically suspect because cell-membrane localisation is also reported (UniProt P21796 subcellular location).
Strong signal mainly in HPA-low cells while nearby HPA-high cells remain unstained.This reversal raises concern for cross-reactivity or endogenous detection activity (HPA: tissue IHC; general IHC practice). VDAC1 expression is widespread, so staining outside the listed high populations is not, by itself, evidence of a false positive (HPA: ubiquitous cytoplasmic expression).
Uniform colour across tissue, including spaces outside cells.This does not match the reported cellular cytoplasmic pattern (HPA: tissue IHC). Diffuse background can arise from nonspecific detection or inadequately controlled chromogen development; interpret localisation only after checking an appropriate detection control (general IHC practice).
No signal in a reported high-staining population.Absence in lung macrophages, kidney collecting ducts, or liver cholangiocytes conflicts with the HPA tissue pattern (HPA: High in these cells). First consider assay performance and whether the relevant cells are present; HPA's Supported rating does not guarantee staining in every specimen (HPA: reliability; general IHC practice).
💡Expected VDAC1 appearanceCall a result positive when cellular cytoplasmic staining is clear in a reported high-staining population, such as lung macrophages or kidney collecting ducts (HPA: High in these cells); predominantly nuclear colour or colour outside cells calls for investigation (HPA: cytoplasmic expression; general IHC practice).
How each factor affects the staining
Subcellular location and topologyMitochondrial outer-membrane localisation supports a cytoplasmic IHC pattern; cell-membrane localisation is also reported (UniProt P21796 subcellular location). The 19 transmembrane segments describe protein topology, not the accessibility of this antibody's epitope (UniProt P21796 topology).
Variation among cell populationsHigh staining is reported in selected cells, including Purkinje cells and lymph-node germinal-center cells; low staining is reported in adipocytes and smooth-muscle cells (HPA: tissue IHC). Compare identified cell populations rather than treating every cell in a section as an equal positive control (general IHC practice).
Strength of tissue evidenceHPA calls the overall tissue pattern Supported and reports medium consistency with RNA expression (HPA: reliability). Its three listed antibodies have IHC status Supported; these records do not establish identical staining with every antibody or specimen (HPA: antibody validation).
Choice of low-staining comparisonThyroid glandular cells and adipocytes are listed as low, not negative (HPA: tissue IHC). Residual staining there need not invalidate a run; an unusually strong signal is more informative when assessed alongside a reported high-staining population and a detection control (HPA: tissue IHC; general IHC practice).
Can the IHC pattern be assumed for IF/ICC?No confirmed HPA subcellular location or ICC-IF images are supplied (HPA: subcellular record). Mitochondrial localisation provides a biological expectation, but an IF/ICC pattern needs its own validation; this tissue-IHC interpretation does not establish one (UniProt P21796 subcellular location; HPA: subcellular record).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-staining reference cells show no colour.The assay may have failed, or the expected cells may be absent from the section (HPA: tissue IHC; general IHC practice).Confirm cell identity and review the IHC run's antibody, detection, and retrieval controls (general IHC practice). No VDAC1-specific retrieval condition is established here.
Nuclear staining dominates.This conflicts with the reported cytoplasmic pattern (HPA: tissue IHC). Nonspecific staining or misread counterstain is possible (general IHC practice).Compare counterstain and detection controls, then reassess cytoplasmic signal in a reported high-staining population (HPA: tissue IHC; general IHC practice).
Colour covers the section rather than identifiable cells.The pattern is inconsistent with cellular cytoplasmic expression (HPA: tissue IHC); nonspecific detection or excessive chromogen development may contribute (general IHC practice).Inspect a detection-only control and review blocking, washes, and development under the established IHC workflow (general IHC practice).
HPA-low cells stain strongly while high cells do not.Cell identification, cross-reactivity, or endogenous detection activity may explain the reversal (HPA: tissue IHC; general IHC practice).Verify the two cell populations and check detection controls before assigning the strong signal to VDAC1 (general IHC practice).
A low-staining tissue still has some signal.HPA labels these cells Low rather than negative; VDAC1 also has ubiquitous cytoplasmic expression (HPA: tissue IHC).Judge the pattern relative to a reported high-staining population and the background control, rather than requiring zero colour (HPA: tissue IHC; general IHC practice).
Staining appears only along cell borders.Cell-membrane localisation is reported, but an exclusively border-only pattern does not reflect HPA's overall cytoplasmic tissue profile (UniProt P21796 subcellular location; HPA: tissue IHC).Check cellular morphology and cytoplasmic staining in reported high-staining cells; use a detection control to assess border artefact (HPA: tissue IHC; general IHC practice).

Sample controls for VDAC1 IHC & IF

🧪Run kidney first: collecting duct cells should stain strongly (HPA: High in kidney collecting ducts). HPA detects VDAC1 in all 45 scored tissues, so there is no supported negative tissue; use no-primary and isotype controls, and treat neighboring cells with lower staining as internal background comparators rather than confirmed VDAC1-negative cells (HPA: no negative tissue rows).
Positive control tissue: Cerebellum (Purkinje cells - cytoplasm/membrane, HPA High)
Negative control tissue: None in HPA: VDAC1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
ICC-IF cell lines (HPA subcellular resource): HPA carries no ICC-IF cell line for VDAC1; derive a cell-line control from the positive tissue's cell type (Purkinje cells - cytoplasm/membrane) and confirm it by RNA or western blot first.
Technical controls: Include a no-primary, secondary-only section and a rabbit IgG isotype control matched to the primary antibody’s clonality where known (selected-SKU caption: rabbit primary and goat anti-rabbit secondary; standard IHC practice). If available, stain a VDAC1 knockout sample as a biological negative; quench endogenous peroxidase and check for endogenous biotin in kidney if using avidin–biotin detection (standard IHC practice).
⚠️Feasibility: Paraffin-section chromogenic IHC is demonstrated with heat retrieval in EDTA at pH 8.0 (selected-SKU tissue-IHC caption). The caption does not report the fixative, and the supplied evidence reports no target-specific fixation window or fixation effect; it also does not establish whether frozen sections or IF are easier (selected-SKU tissue-IHC caption). Kidney can show endogenous biotin signal with avidin–biotin detection, so check the detection-system background (standard IHC practice).

HPA tissue IHC evidence for VDAC1

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Supported — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Cerebellum Purkinje cells - cytoplasm/membrane High Protein (IHC) HPA →
Gallbladder Glandular cells High Protein (IHC) HPA →
Kidney Collecting ducts High Protein (IHC) HPA →
Liver Cholangiocytes High Protein (IHC) HPA →
Lung Macrophages High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: VDAC1 is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced VDAC1 IHC Tips

Troubleshoot VDAC1 staining in paraffin sections by checking retrieval, controls, compartmental pattern, and cell-specific scoring.

What retrieval conditions should I try when VDAC1 staining is weak?
Use heat-mediated antigen retrieval in EDTA buffer at pH 8.0 for paraffin-section VDAC1 IHC (datasheet A01168-1). The selected antibody's tissue image used this condition before incubation with 2 μg/ml primary antibody overnight at 4°C, so reproduce those conditions when assessing weak staining (datasheet A01168-1). Check a positive-control section alongside the test section and compare staining in the same cell populations before increasing antibody concentration (HPA: High in lymph-node germinal center cells; standard IHC practice). If staining remains weak, optimise heating duration on serial sections while monitoring morphology and background; an alternative retrieval buffer requires separate validation (standard IHC practice).
Could fixation explain weak or uneven VDAC1 staining?
The selected tissue-IHC caption identifies a paraffin section but does not report its fixative, so VDAC1-specific fixation sensitivity is unknown (datasheet A01168-1). Record the fixative, fixation duration and section-processing history for each specimen, then compare serial sections under identical EDTA pH 8.0 retrieval and antibody conditions (standard IHC practice; datasheet A01168-1). If staining varies with processing history, assess morphology and a positive-control section before changing retrieval intensity (standard IHC practice). Do not assign a particular fixation effect to VDAC1 from its membrane topology or post-translational modifications; neither establishes fixation sensitivity in these sections (UniProt P21796 topology and modified residues; datasheet A01168-1).
Which staining pattern is plausible for VDAC1 in tissue sections?
Expect predominantly cytoplasmic staining compatible with mitochondria, while allowing a membrane-associated component because VDAC1 is reported at the mitochondrial outer membrane and cell membrane (UniProt P21796 subcellular location; HPA: ubiquitous cytoplasmic expression). A paraffin-section DAB signal will not resolve individual mitochondrial membranes, so judge the pattern at the cellular level rather than claiming organelle-level localisation from brown granules alone (standard IHC interpretation). Compare cells within the same section: HPA reports High staining in lung macrophages and lymph-node germinal center cells, providing context for plausible positive populations (HPA tissue IHC). Reassess diffuse nuclear-only staining against controls and tissue morphology before treating it as VDAC1 localisation (UniProt P21796 subcellular location; standard IHC practice).
How should epitope uncertainty affect VDAC1 IHC optimisation?
The supplied record annotates 0 isoforms and 19 membrane-spanning segments, but it does not map this antibody's epitope (UniProt P21796 isoforms and topology; datasheet A01168-1). Therefore, a change in paraffin-section staining cannot be assigned to isoform recognition or to a particular membrane-facing epitope from these data (UniProt P21796; datasheet A01168-1). VDAC1 also has annotated modified residues, including sites near its N-terminus, but their effect on this antibody's IHC signal is unestablished (UniProt P21796 modified residues). Keep retrieval at EDTA pH 8.0 as the initial condition and compare appropriate controls before pursuing an epitope-based explanation (datasheet A01168-1; standard IHC practice).
How can IF help assess a questionable VDAC1 IHC pattern?
Use IF as a separate localisation check, pairing VDAC1 with a marker for an expected cell population, such as macrophages in lung, and compare the result with the chromogenic section (HPA: High in lung macrophages; standard IF practice). Choose fluorophores and imaging channels after checking tissue autofluorescence with an unstained section, then use single-label controls to assess channel bleed-through (standard IF practice). Because VDAC1 resides mainly at the mitochondrial outer membrane, consider antibody access to the epitope's membrane-facing side when optimising permeabilisation; that side is unspecified for this antibody (UniProt P21796 subcellular location; datasheet A01168-1). The paraffin-section IHC caption provides no IF fixation or permeabilisation validation (datasheet A01168-1).
How do I reduce widespread brown signal without losing VDAC1 staining?
First compare a no-primary control with the stained section to identify signal from detection reagents or endogenous peroxidase, and include a peroxidase-blocking step in the chromogenic workflow (standard IHC practice). The selected image used 10% goat serum blocking, 2 μg/ml primary antibody overnight at 4°C, an anti-rabbit peroxidase secondary for 30 minutes at 37°C, and DAB development (datasheet A01168-1). If controls are clean but staining is diffuse, adjust primary concentration and washing on serial sections while retaining a positive-control tissue (standard IHC practice). Widespread cellular staining alone is not proof of background, because HPA describes VDAC1 expression as ubiquitous and cytoplasmic (HPA tissue IHC).
How should VDAC1 DAB staining be scored across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, since VDAC1 can be cytoplasmic or membrane-associated and HPA reports different levels among cell types (UniProt P21796 subcellular location; HPA tissue IHC). For a comparable cell population, record percent positive cells and an H-score from staining intensity; apply the same thresholds and image settings to every specimen (standard IHC scoring practice). If measuring positive-cell density, report cells per mm² of viable tissue and exclude empty space or necrotic areas by a prespecified rule (standard IHC scoring practice). Normalise comparisons to the relevant cell population or viable tissue area, and review a positive-control section for staining consistency between runs (standard IHC practice).
How can I distinguish genuine VDAC1 signal from staining artefacts?
A plausible positive shows cellular cytoplasmic staining, sometimes with a membrane-associated component, in morphologically intact cells (HPA: ubiquitous cytoplasmic expression; UniProt P21796 subcellular location). High staining in lung macrophages or lymph-node germinal center cells supports a cell-specific interpretation, but it does not establish that every brown deposit is VDAC1 (HPA tissue IHC; standard IHC interpretation). Treat staining restricted to section edges, necrotic areas, or the no-primary control as suspect, and assess endogenous peroxidase before assigning DAB signal to the target (standard IHC practice). Uniform nuclear-only staining is inconsistent with the supplied localisation record and warrants review of controls, morphology and retrieval conditions (UniProt P21796 subcellular location; standard IHC practice).
Boster reagents

Best VDAC1 / Non-selective voltage-gated ion channel VDAC1 IHC Antibodies

The catalog includes VDAC1 antibodies with IHC images from human, mouse and rat tissues, plus IF images from HeLa cells and tissue sections (catalog: IHC/IF image captions).

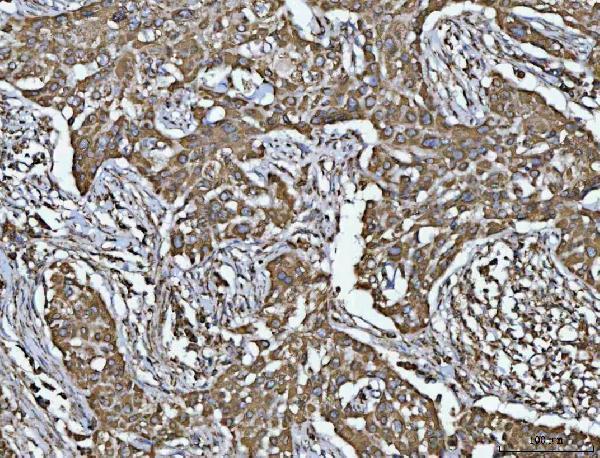
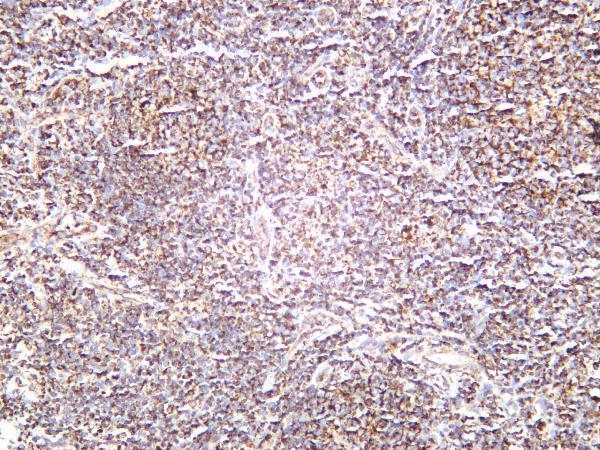
Real IHC data IHC analysis of Porin/VDAC1 using anti-Porin/VDAC1 antibody (A01168-1). Porin/VDAC1 was detected in a paraffin-embedded section of human lymphadenoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-Porin/VDAC1 Antibody (A01168-1) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-Porin/VDAC1 Antibody ®
Cat # A01168-1
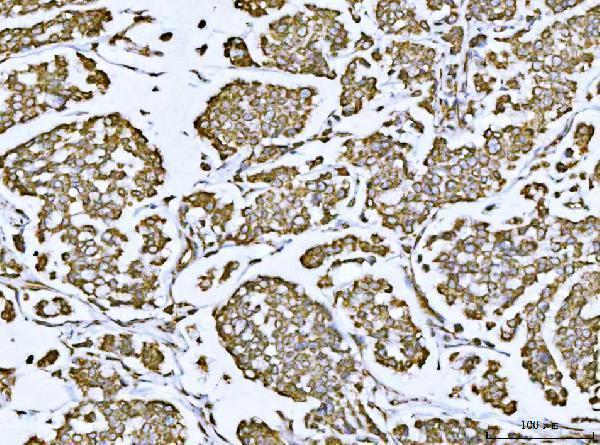
Real IHC data IHC analysis of VDAC1/Porin using anti-VDAC1/Porin antibody (M01168). VDAC1/Porin was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1:50 rabbit anti-VDAC1/Porin Antibody (M01168) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-VDAC1/Porin Rabbit Monoclonal Antibody
Cat # M01168
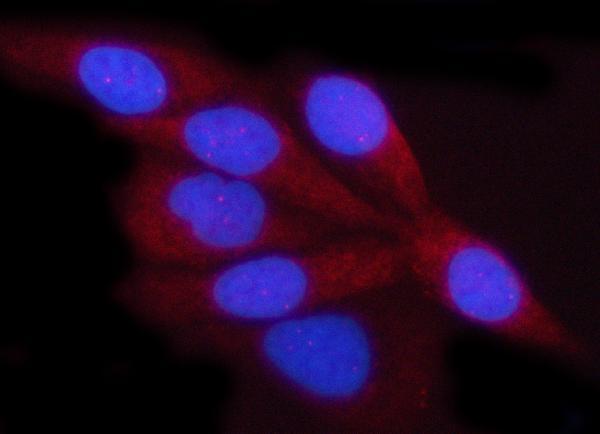
Real IHC data IHC analysis of VDAC/Porin/VDAC1 using anti-VDAC/Porin/VDAC1 antibody (PA1780). VDAC/Porin/VDAC1 was detected in a paraffin-embedded section of human liver cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-VDAC/Porin/VDAC1 Antibody (PA1780) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-VDAC/Porin/VDAC1 Antibody ®
Cat # PA1780
Real IHC data IHC analysis of VDAC using anti-VDAC antibody (PB9455). VDAC was detected in a paraffin-embedded section of human intestinal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1 μg/ml rabbit anti-VDAC Antibody (PB9455) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-VDAC/Porin/VDAC1 Antibody ®
Cat # PB9455
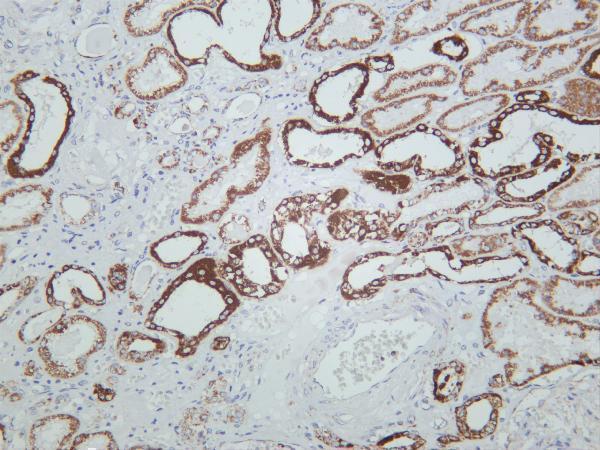
Real IHC data Human kidney was stained with anti-VDAC1 rabbit antibody
Anti-VDAC1 Rabbit Monoclonal Antibody
Cat # M01168-1

A01168-1 shows IHC in human lymphadenoma and IF in HeLa cells (catalog: A01168-1 image captions); M01168 shows IHC in human liver cancer and mouse and rat heart (catalog: M01168 IHC captions); PA1780 shows IHC in human liver cancer and IF in HeLa cells (catalog: PA1780 image captions). PB9455 shows IHC in human intestinal cancer and mouse and rat cardiac muscle (catalog: PB9455 IHC captions); M01168-1 shows IHC in human, mouse and rat kidney (catalog: M01168-1 IHC captions).

Which to pick: For paraffin-section IHC, PB9455 has a human intestinal cancer example using EDTA retrieval at pH 8.0 and 1 μg/ml primary antibody (catalog: PB9455 IHC caption). For IF/ICC, A01168-1 has an IF image in HeLa cells at 5 μg/ml and a separate paraffin IHC example using EDTA retrieval at pH 8.0 (catalog: A01168-1 IF and IHC captions). For cross-species IHC, M01168 is a rabbit monoclonal with human, mouse and rat reactivity and paraffin IHC images using EDTA retrieval at pH 8.0; the fixative is unreported in these IHC captions (catalog: M01168 product record and IHC captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P21796 (VDAC1_HUMAN, Non-selective voltage-gated ion channel VDAC1).
  2. Human Protein Atlas. VDAC1 tissue IHC expression (reliability: Supported).
  3. Human Protein Atlas. VDAC1 subcellular location (ICC-IF): Highest expression in HBEC3-KT: 648.1 nTPM.
  4. Human Protein Atlas. VDAC1 antibody validation summary (3 antibodies).
  5. VDAC1 Conversely Correlates with Cytc Expression and Predicts Poor Prognosis in Human Breast Cancer Patients. Oxidative medicine and cellular longevity 2021 — PMC7904344.
  6. Oxidative phosphorylation patterns in pituitary adenoma/neuroendocrine tumors. Pituitary 2026 — PMC12979347.
  7. Voltage-Dependent Anion Channel 1 Expression in Oral Malignant and Premalignant Lesions. Diagnostics (Basel, Switzerland) 2023 — PMC10093190.
  8. Identification and validation of serum autoantibodies in children with B-cell acute lymphoblastic leukemia by serological proteome analysis. Proteome science 2022 — PMC8808998.
  9. PubMed PMID:8420959 — UniProt-cited evidence.
  10. PubMed PMID:10501981 — UniProt-cited evidence.
  11. PubMed PMID:10772903 — UniProt-cited evidence.