WAPL / Wings apart-like protein homolog · IHC design guide

Design Immunohistochemistry for WAPL

Plan WAPL chromogenic IHC-P around widespread nuclear and cytoplasmic tissue staining (HPA tissue IHC). Compare compartments across sections, since WAPL redistributes to the cytoplasm during mitosis (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for WAPL (IHC for WAPL): expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A03684-2, validated IHC image, and IHC protocol steps
Printable WAPL IHC protocol sheet — expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC), antibody A03684-2, controls and protocol steps. Open the full WAPL IHC guide →

WAPL Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Nuclear and cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Widespread nuclear and cytoplasmic staining (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A03684-2)
Positive control ⓘ Placenta+4 more · see all
Negative control ⓘ None in HPA (detected in all 45 tissues); use no-primary + isotype controls
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep paraffin-section fixation consistent across samples. (standard IHC practice; not target-specific)
Caveat Mitotic cells may show cytoplasmic WAPL (UniProt)
Regulation Isoform 1 is high in uterine cervix tumor (UniProt)
Isoform / epitope 3 isoforms; epitope coverage is unspecified (UniProt)
Section 1

Recommended WAPL IHC & IF Protocols

The catalog antibody uses EDTA pH 8.0 heat retrieval (datasheet A03684-2). The published protocol stains human and mouse paraffin-embedded cervix (PMC8154587).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded mouse colon tissue; fixative not specified (datasheet A03684-2)
FixationImage fixative and duration unreported (datasheet A03684-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A03684-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A03684-2)
Primary antibodyRabbit anti-WAPL, 2-5 μg/ml (datasheet A03684-2)
Primary incubationOvernight at 4 °C (datasheet A03684-2)
DetectionHRP-conjugated secondary, DAB chromogen (datasheet A03684-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultWAPL-positive staining in endothelial cells of placenta (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic and nuclear expression. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 heat retrieval (datasheet A03684-2); the published cervix method does not specify retrieval conditions (PMC8154587).
Section 2

What Is the Expected WAPL Staining Pattern?

WAPL is mainly nuclear and chromatin associated, with cytoplasmic distribution during part of mitosis (UniProt Q7Z5K2). In paraffin sections, expect nuclear and cytoplasmic staining across many cell types, including strong staining in placental endothelial cells and testicular spermatogonia (HPA: ubiquitous expression; High in both cell types). WAPL has no transmembrane segment (UniProt Q7Z5K2 topology). HPA rates tissue staining Enhanced, with medium consistency between staining and RNA data (HPA: tissue IHC).

What am I looking at on my slide?
Placental endothelial cells or testicular spermatogonia show prominent staining.These are useful positive references (HPA: High in both). Assess compartment and cell identity together; intensity alone does not establish specificity (general IHC practice).
Interphase cells show nuclear staining; occasional dividing cells appear more cytoplasmic.Nuclear chromatin association and cytoplasmic redistribution between nuclear envelope breakdown and anaphase fit WAPL biology (UniProt Q7Z5K2). Judge dividing cells separately from interphase cells.
Staining is confined to plasma membranes or extracellular material.That distribution does not fit the reported nuclear and cytoplasmic pattern (HPA: tissue IHC; UniProt Q7Z5K2). Check morphology and controls for nonspecific signal (general IHC practice).
Unexpected cells stain while expected cells in the same section do not.Cross-reactivity or endogenous detection activity is possible (general IHC practice). Compare the cell types with HPA references before interpreting the signal as WAPL (HPA: tissue IHC).
Most of the section has uniform haze, or a known-positive population has no signal.Haze obscures compartment scoring; absence in an HPA High population makes a negative result difficult to interpret (HPA: tissue IHC). Review controls and the IHC workflow (general IHC practice).
💡Expected WAPL appearanceCall a result positive when identifiable placental endothelial cells or testicular spermatogonia show strong nuclear and/or cytoplasmic staining (HPA: High; ubiquitous cytoplasmic and nuclear expression); isolated membrane staining or uniform haze is suspect (UniProt Q7Z5K2 topology; general IHC practice).
How each factor affects the staining
Cell-cycle stageWAPL associates with chromatin in interphase, redistributes to cytoplasm after nuclear envelope breakdown, and returns to nuclei at telophase (UniProt Q7Z5K2). Account for mitotic cells when scoring compartments.
Tissue and cell selectionPlacental endothelial cells and testicular spermatogonia are High; adipocytes and several glandular or epithelial populations are Medium (HPA: tissue IHC). Score named cells, rather than assigning one intensity to a whole tissue.
Low-signal referencesLiver cholangiocytes and ovarian stromal cells are Low (HPA: tissue IHC). Weak staining there is compatible with the reference; it is not a reliable stand-alone test of antibody performance.
Validation strengthHPA037874 and HPA037875 each have Enhanced IHC status (HPA: antibodies). HPA describes medium consistency between staining and RNA data (HPA: tissue IHC); resolve unexpected patterns with controls.
Isoform expressionIsoform 1 is highly expressed in uterine cervix tumor; isoform 2 is widespread, with high levels in skeletal muscle and heart (UniProt Q7Z5K2). No supplied epitope map establishes which isoforms an antibody detects.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
No staining in placental endothelial cells or testicular spermatogonia.A missing positive signal could reflect a failed IHC run; these populations are High references (HPA: tissue IHC).Check section quality, retrieval, antibody dilution and detection against the validated IHC procedure and run controls (general IHC practice). Do not call other tissues negative until the positive control works.
Signal is mainly membranous or extracellular.This conflicts with WAPL's reported intracellular distribution and lack of a transmembrane segment (HPA: tissue IHC; UniProt Q7Z5K2 topology).Inspect the same cells for nuclear or cytoplasmic signal and compare with a negative reagent control (general IHC practice); treat the discordant compartment as suspect.
Uniform chromogen appears across cells and stroma.Diffuse background can arise from nonspecific binding or endogenous detection activity (general IHC practice).Check blocking, washes and detection controls (general IHC practice). Score WAPL only where cell boundaries and intracellular compartments remain distinguishable.
Low-reference cells look as strong as High-reference cells.The result conflicts with the reported Low versus High examples (HPA: liver cholangiocytes and ovarian stroma Low; placenta and testis High).Confirm cell identity and compare controls and exposure to chromogen across sections (general IHC practice). HPA levels are reference patterns, not absolute intensity cutoffs.
Only cytoplasmic staining is seen in apparently dividing cells.WAPL can move into the cytoplasm during mitosis (UniProt Q7Z5K2); cell-cycle stage may explain this distribution.Check mitotic morphology and adjacent interphase cells before rejecting the stain; interphase WAPL is chromatin associated (UniProt Q7Z5K2).
Q: Should an IF/ICC pattern decide this paraffin IHC result?HPA reports supported nucleoplasmic ICC-IF localization and Enhanced tissue IHC staining (HPA: subcellular; antibodies).A: Use nucleoplasmic IF as a localization cross-check (HPA: subcellular). Judge the paraffin result against tissue IHC cell patterns and its own controls (HPA: tissue IHC; general IHC practice).

Sample controls for WAPL IHC & IF

🧪Run placenta first and score endothelial cells for WAPL staining (HPA: High in placental endothelial cells). HPA detects WAPL in all 45 scored tissues, so use no-primary and isotype controls instead of a negative tissue; cells on the placenta slide that show counterstain alone may provide a visual background reference, but no placental cell type is validated here as WAPL-negative (HPA: no negative rows).
Positive control tissue: Placenta (Endothelial cells, HPA High)
Negative control tissue: None in HPA: WAPL is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
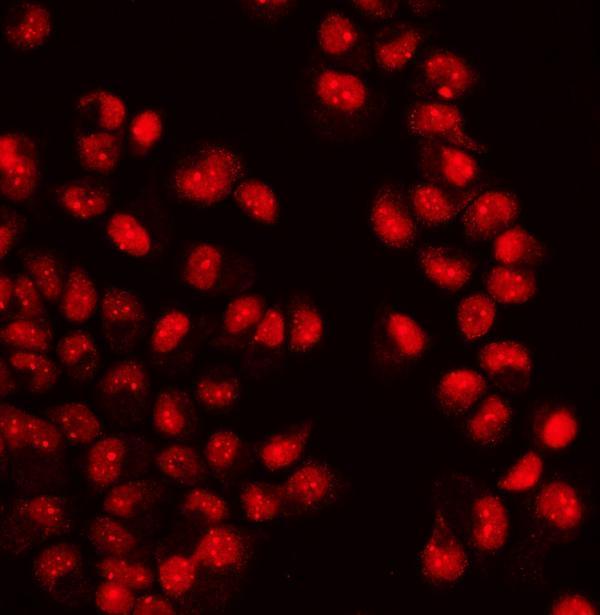
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show WAPL in HeLa, U-251MG, U2OS, with annotated localisation: Nucleoplasm (supported) (HPA subcellular).
Technical controls: Include a secondary-only slide, a matched nonimmune rabbit IgG isotype control, and a WAPL-knockout biological control if available (caption: rabbit primary antibody; standard IHC practice). Quench endogenous peroxidase and check for blood-associated DAB background in placenta (standard IHC practice).
⚠️Feasibility: A target-specific fixation window is unreported, and the selected A03684-2 paraffin-section caption does not state the fixative (caption: fixative unreported). Heat retrieval with EDTA at pH 8.0 is documented for mouse colon IHC, but its effect in placenta is unreported (caption: mouse colon paraffin section). Frozen sections are not established as easier; ICC-IF images are available in HeLa, U-251MG and U2OS, with mainly nucleoplasmic localization, while placental blood-associated background warrants attention in chromogenic IHC (HPA: subcellular images; standard IHC practice).

HPA tissue IHC evidence for WAPL

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Placenta Endothelial cells High Protein (IHC) HPA →
Testis Spermatogonia cells High Protein (IHC) HPA →
Adipose tissue Adipocytes Medium Protein (IHC) HPA →
Adrenal gland Glandular cells Medium Protein (IHC) HPA →
Appendix Glandular cells Medium Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
None in HPA: WAPL is detected in all 45 scored tissues. Use a no-primary (secondary-only) and an isotype control instead.
Section 3

Advanced WAPL IHC Tips

Troubleshoot WAPL staining in paraffin sections by checking retrieval, controls, cellular localisation and scoring before interpreting chromogenic signal.

Which retrieval conditions should I try first for WAPL IHC?
Start with heat-mediated retrieval in EDTA at pH 8.0 for paraffin sections (datasheet A03684-2). The documented mouse colon staining used this retrieval, followed by 10% goat serum block and 2 μg/ml primary antibody overnight at 4°C (datasheet A03684-2). If staining is weak, check that sections reached retrieval temperature uniformly and compare a shorter and longer heating interval on adjacent sections; no target-specific heating duration is supplied (datasheet A03684-2). Keep detection and development conditions matched across that comparison so signal changes can be attributed to retrieval. Include a section processed without primary antibody to assess retrieval-associated background.
How should I troubleshoot fixation-related loss of WAPL staining?
Target-specific fixation sensitivity is unknown: the selected antibody image documents a paraffin section but does not state its fixative (datasheet A03684-2). Record the fixative, fixation interval and processing history for each specimen before comparing WAPL staining between blocks. When signal differs across blocks, stain sections from each in the same run using EDTA retrieval at pH 8.0 (datasheet A03684-2). Compare tissue preservation and an appropriate positive control alongside the WAPL result; poor morphology or a failed control limits interpretation of a negative section. Do not assign a fixation-dependent WAPL effect without a controlled comparison.
Where should WAPL staining appear in paraffin sections?
Assess nuclear and cytoplasmic staining separately: WAPL has reported nuclear, chromosome and cytoplasmic localisation (UniProt Q7Z5K2), while tissue IHC shows a ubiquitous cytoplasmic and nuclear profile (HPA tissue IHC). Nucleoplasmic signal has additional support from cellular imaging (HPA subcellular). Its chromatin association changes across the cell cycle, with cytoplasmic release after nuclear envelope breakdown and nuclear reaccumulation at telophase (UniProt Q7Z5K2). For each compartment, compare the staining pattern with the nuclear counterstain and tissue morphology rather than pooling all brown pixels. A compartment shift in a few dividing cells warrants separate review before interpreting it as a tissue-wide change.
Could isoforms or epitope accessibility explain variable WAPL IHC?
WAPL has 3 reported isoforms, but the supplied antibody caption does not identify its epitope or establish which isoforms it recognises (UniProt Q7Z5K2; datasheet A03684-2). Isoform 1 is reported as highly expressed in uterine cervix tumor, whereas isoform 2 is widely expressed with high levels in skeletal muscle and heart (UniProt Q7Z5K2). These expression statements do not establish isoform-specific IHC staining. Request the immunogen sequence or mapped epitope before assigning a staining difference to alternative splicing. Compare that sequence with each isoform and the WAPL domain at residues 626–1169, then validate any proposed isoform-specific interpretation experimentally (UniProt Q7Z5K2).
How can I assess WAPL by IF alongside cell-type markers?
For the separate IF/ICC workflow, multiplex WAPL with a validated marker of the expected cell type and check whether its signal aligns with nuclear counterstaining; nucleoplasmic localisation is supported (HPA subcellular). Choose fluorophores after inspecting unstained tissue for autofluorescence, and reserve a spectrally distinct channel for the cell-type marker. WAPL has no transmembrane segment and is reported in nuclear and cytoplasmic compartments (UniProt Q7Z5K2), so use permeabilisation sufficient to access intracellular epitopes while preserving morphology. Optimise fixation and permeabilisation with IF controls because the supplied IHC caption provides no IF-specific conditions (datasheet A03684-2). Include single-label controls when assessing channel bleed-through.
How do I reduce diffuse or misleading brown WAPL staining?
First inspect the no-primary control and tissue edges; diffuse brown deposit there suggests detection background rather than interpretable WAPL signal. The documented paraffin-section method used 10% goat serum blocking, a peroxidase-conjugated secondary and DAB development (datasheet A03684-2). Add an endogenous peroxidase block as a general chromogenic IHC step, then compare its effect on the no-primary control and stained section. If background persists, titrate primary concentration around the documented 2 μg/ml condition while holding retrieval and DAB development constant (datasheet A03684-2). Review nuclear and cytoplasmic signal separately because both compartments are reported for WAPL (UniProt Q7Z5K2).
How should I score WAPL staining across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the tissue compartment and eligible cell population before scoring, then record nuclear and cytoplasmic staining separately because both are reported for WAPL (HPA tissue IHC). For cell-level analysis, report the percentage of positive cells and an H-score using intensity categories 0–3, with a theoretical range of 0–300. For spatial analysis, report positive-cell density per mm² of viable tissue and state how the region of interest was selected. Normalise counts to the number of eligible cells or measured viable area, rather than total section area when tissue coverage differs. Apply one threshold and matched imaging or scoring conditions across specimens.
How can I distinguish convincing WAPL signal from artefact?
A convincing result follows cellular boundaries and shows interpretable nuclear or cytoplasmic staining, both reported for WAPL (HPA tissue IHC). Check whether the stained population is plausible in the sampled tissue; reported examples include high signal in placental endothelial cells and testicular spermatogonia (HPA tissue IHC). Treat staining confined to section edges, necrotic regions or the no-primary control as suspect, and investigate residual endogenous peroxidase before calling it positive. Unexpected compartment-only staining merits review against the nuclear counterstain because nucleoplasmic localisation is supported (HPA subcellular). Finally, compare staining with morphology and controls; HPA reports medium consistency between antibody staining and RNA expression, so one discordant section is inconclusive (HPA tissue IHC).
Boster reagents

Best WAPL / Wings apart-like protein homolog IHC Antibodies

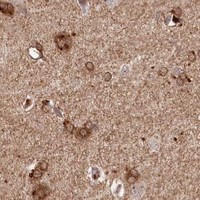
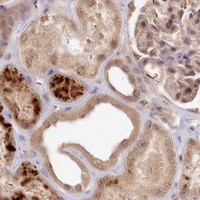
A03684-2 has IHC images from mouse colon and human lymphoma, stomach cancer, and tonsil paraffin sections, plus an IF image from T-47D cells (A03684-2 image captions).

Real IHC data IHC analysis of WAPL/FOE using anti-WAPL/FOE antibody (A03684-2). WAPL/FOE was detected in a paraffin-embedded section of mouse colon tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-WAPL/FOE Antibody (A03684-2) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-WAPL/FOE Antibody ®
Cat # A03684-2

A03684-2 is the sole card that will render; its IHC images show mouse and human paraffin sections (A03684-2 IHC image captions). Its IF image shows T-47D cells (A03684-2 IF image caption).

Which to pick: Choose A03684-2 for tissue IHC: its caption documents EDTA retrieval at pH 8.0 and 2 μg/ml antibody on paraffin sections; the fixative is unreported (A03684-2 IHC image captions). For IF/ICC, A03684-2 has a T-47D IF image at 5 μg/ml, while M03684 is a human-reactive monoclonal listed for ICC/IF at 1:50 but has no IF image in the payload (A03684-2 IF image caption; M03684 catalog). For work across species, A03684-2 lists human, mouse, and rat reactivity, although its IHC images show only human and mouse samples (A03684-2 catalog; A03684-2 IHC image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.