ACADM / Medium-chain specific acyl-CoA dehydrogenase, mitochondrial · IHC design guide

Design Immunohistochemistry for ACADM

Plan paraffin-section ACADM IHC around the granular cytoplasmic staining reported in tissue (HPA tissue IHC). The guide covers fixation consistency, tissue controls, and interpretation alongside ACADM’s mitochondrial matrix location (UniProt).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for ACADM (IHC for ACADM): expected localisation Granular cytoplasm in tissue (HPA tissue IHC), antibody A02383-2, validated IHC image, and IHC protocol steps
Printable ACADM IHC protocol sheet — expected localisation Granular cytoplasm in tissue (HPA tissue IHC), antibody A02383-2, controls and protocol steps. Open the full ACADM IHC guide →

ACADM Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation Granular cytoplasm in tissue (HPA tissue IHC)
Staining pattern Broad granular cytoplasmic staining across cell types (HPA tissue IHC)
Antigen retrieval EDTA pH 8.0 HIER, heat-mediated (datasheet A02383-2)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Adipose tissue+2 more · see all
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across sections (standard IHC practice; not target-specific)
Caveat Adipocytes lack detectable staining (HPA tissue IHC)
Regulation Highest expression in heart and muscle (UniProt)
Isoform / epitope 2 isoforms; mature chain spans residues 26–421 (UniProt)
Section 1

Recommended ACADM IHC & IF Protocols

The catalog antibody protocol uses EDTA pH 8.0 retrieval (datasheet A02383-2); the published ACADM IHC protocol below uses citrate pH 6.0 retrieval (PMC13297011 methods).

Recommended immunohistochemistry (IHC-P) protocol parameters
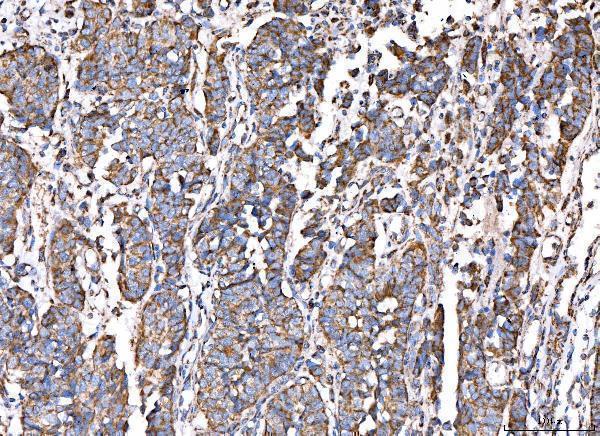
SampleParaffin-embedded human bladder epithelial carcinoma tissue; fixative not specified (datasheet A02383-2)
FixationImage fixative and duration unreported (datasheet A02383-2); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: EDTA pH 8.0 (datasheet A02383-2); 20 min, 95–100 °C (standard)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet A02383-2)
Primary antibodyRabbit anti-ACADM, 2 μg/ml (datasheet A02383-2)
Primary incubationOvernight at 4 °C (datasheet A02383-2)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet A02383-2)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultACADM-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: Ubiquitous cytoplasmic expression with a granular pattern. No signal in the no-primary control.
💡Decision noteStart with EDTA pH 8.0 retrieval for the catalog antibody (datasheet A02383-2). Citrate pH 6.0 is a published alternative for ACADM IHC (PMC13297011 methods).
Section 2

What Is the Expected ACADM Staining Pattern?

ACADM is a mitochondrial matrix protein with no transmembrane segment (UniProt P11310: location and topology). In paraffin-section IHC, expect granular cytoplasmic staining across many tissues (HPA: tissue IHC profile). High staining is reported in heart cardiomyocytes and several glandular and epithelial cell populations (HPA: tissue IHC). HPA rates the tissue pattern Enhanced, while reporting medium consistency between staining and RNA expression (HPA: reliability description).

What am I looking at on my slide?
Granular cytoplasmic staining in cardiomyocytes or colon glandular cells, with little nuclear staining.This fits the reported high staining in those cells (HPA: tissue IHC) and the expected mitochondrial matrix location (UniProt P11310: subcellular location). Judge intensity against cells within the same section; granular signal alone does not establish antibody specificity (standard IHC interpretation).
Predominantly nuclear, membrane-rim, or broad extracellular signal.These compartments conflict with the mitochondrial matrix assignment and lack of a transmembrane segment (UniProt P11310: location and topology). Consider staining artefact or off-target binding; review controls and morphology before assigning the signal to ACADM (standard IHC interpretation).
Prominent staining in adipocytes, basal-layer skin cells, or soft-tissue fibroblasts.HPA reports ACADM as not detected in these particular cells by tissue IHC (HPA: tissue IHC). Check whether the signal is cellular or background, and assess cross-reactivity or endogenous detection activity with controls (standard IHC interpretation). A negative HPA result does not prove universal absence.
Uniform brown haze across tissue, stroma, and empty spaces.A uniform haze obscures the reported granular cytoplasmic pattern (HPA: tissue IHC profile). Consider nonspecific antibody binding, incomplete washing, or detection-system background; compare a no-primary control before scoring cells (standard chromogenic IHC practice).
No convincing signal in heart cardiomyocytes or colon glandular cells.Both are reported High by HPA tissue IHC, so an entirely blank result merits a workflow check (HPA: tissue IHC). Review section integrity, antibody and detection steps, and an appropriate positive control (standard IHC practice). HPA levels do not establish ACADM-specific fixation sensitivity.
💡Expected ACADM appearanceCall a result positive when the relevant cells show discernible granular cytoplasmic staining, potentially High in heart cardiomyocytes or colon glandular cells (HPA: tissue IHC), consistent with a mitochondrial matrix protein (UniProt P11310: location); isolated nuclear, extracellular, or uniform background staining is suspect (standard IHC interpretation).
How each factor affects the staining
Subcellular locationMatrix localization and absence of a transmembrane segment favor intracellular, granular cytoplasmic interpretation over a surface-membrane pattern (UniProt P11310: location and topology; HPA: tissue IHC profile).
Choice of reference cellsHPA reports High staining in heart cardiomyocytes and bronchial respiratory epithelial cells, but Not detected in adipocytes (HPA: tissue IHC). These are observed cell-level comparisons, not guarantees for every specimen.
IHC evidence strengthHPA rates tissue IHC Enhanced and reports medium staining–RNA consistency (HPA: reliability description). HPA006198 and HPA026542 each have Enhanced IHC status (HPA: antibody validation); assess the actual run with controls.
Protein processing and isoformsUniProt annotates a mature chain at residues 26–421 and two isoforms (UniProt P11310: processing and isoforms). Their presence alone does not predict how a given IHC antibody binds; no epitope location is supplied.
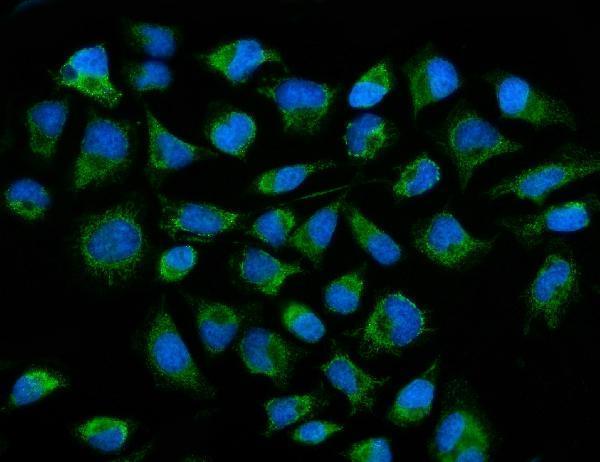
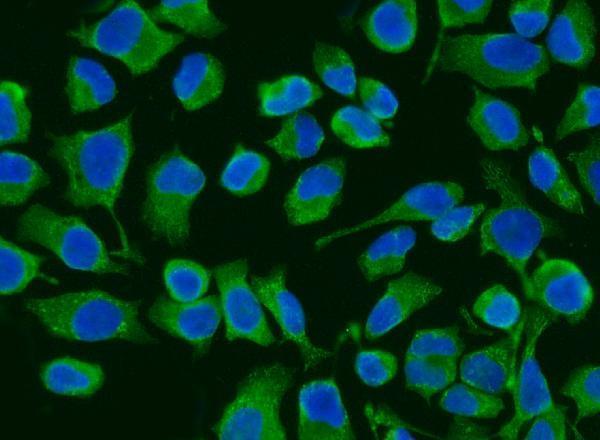
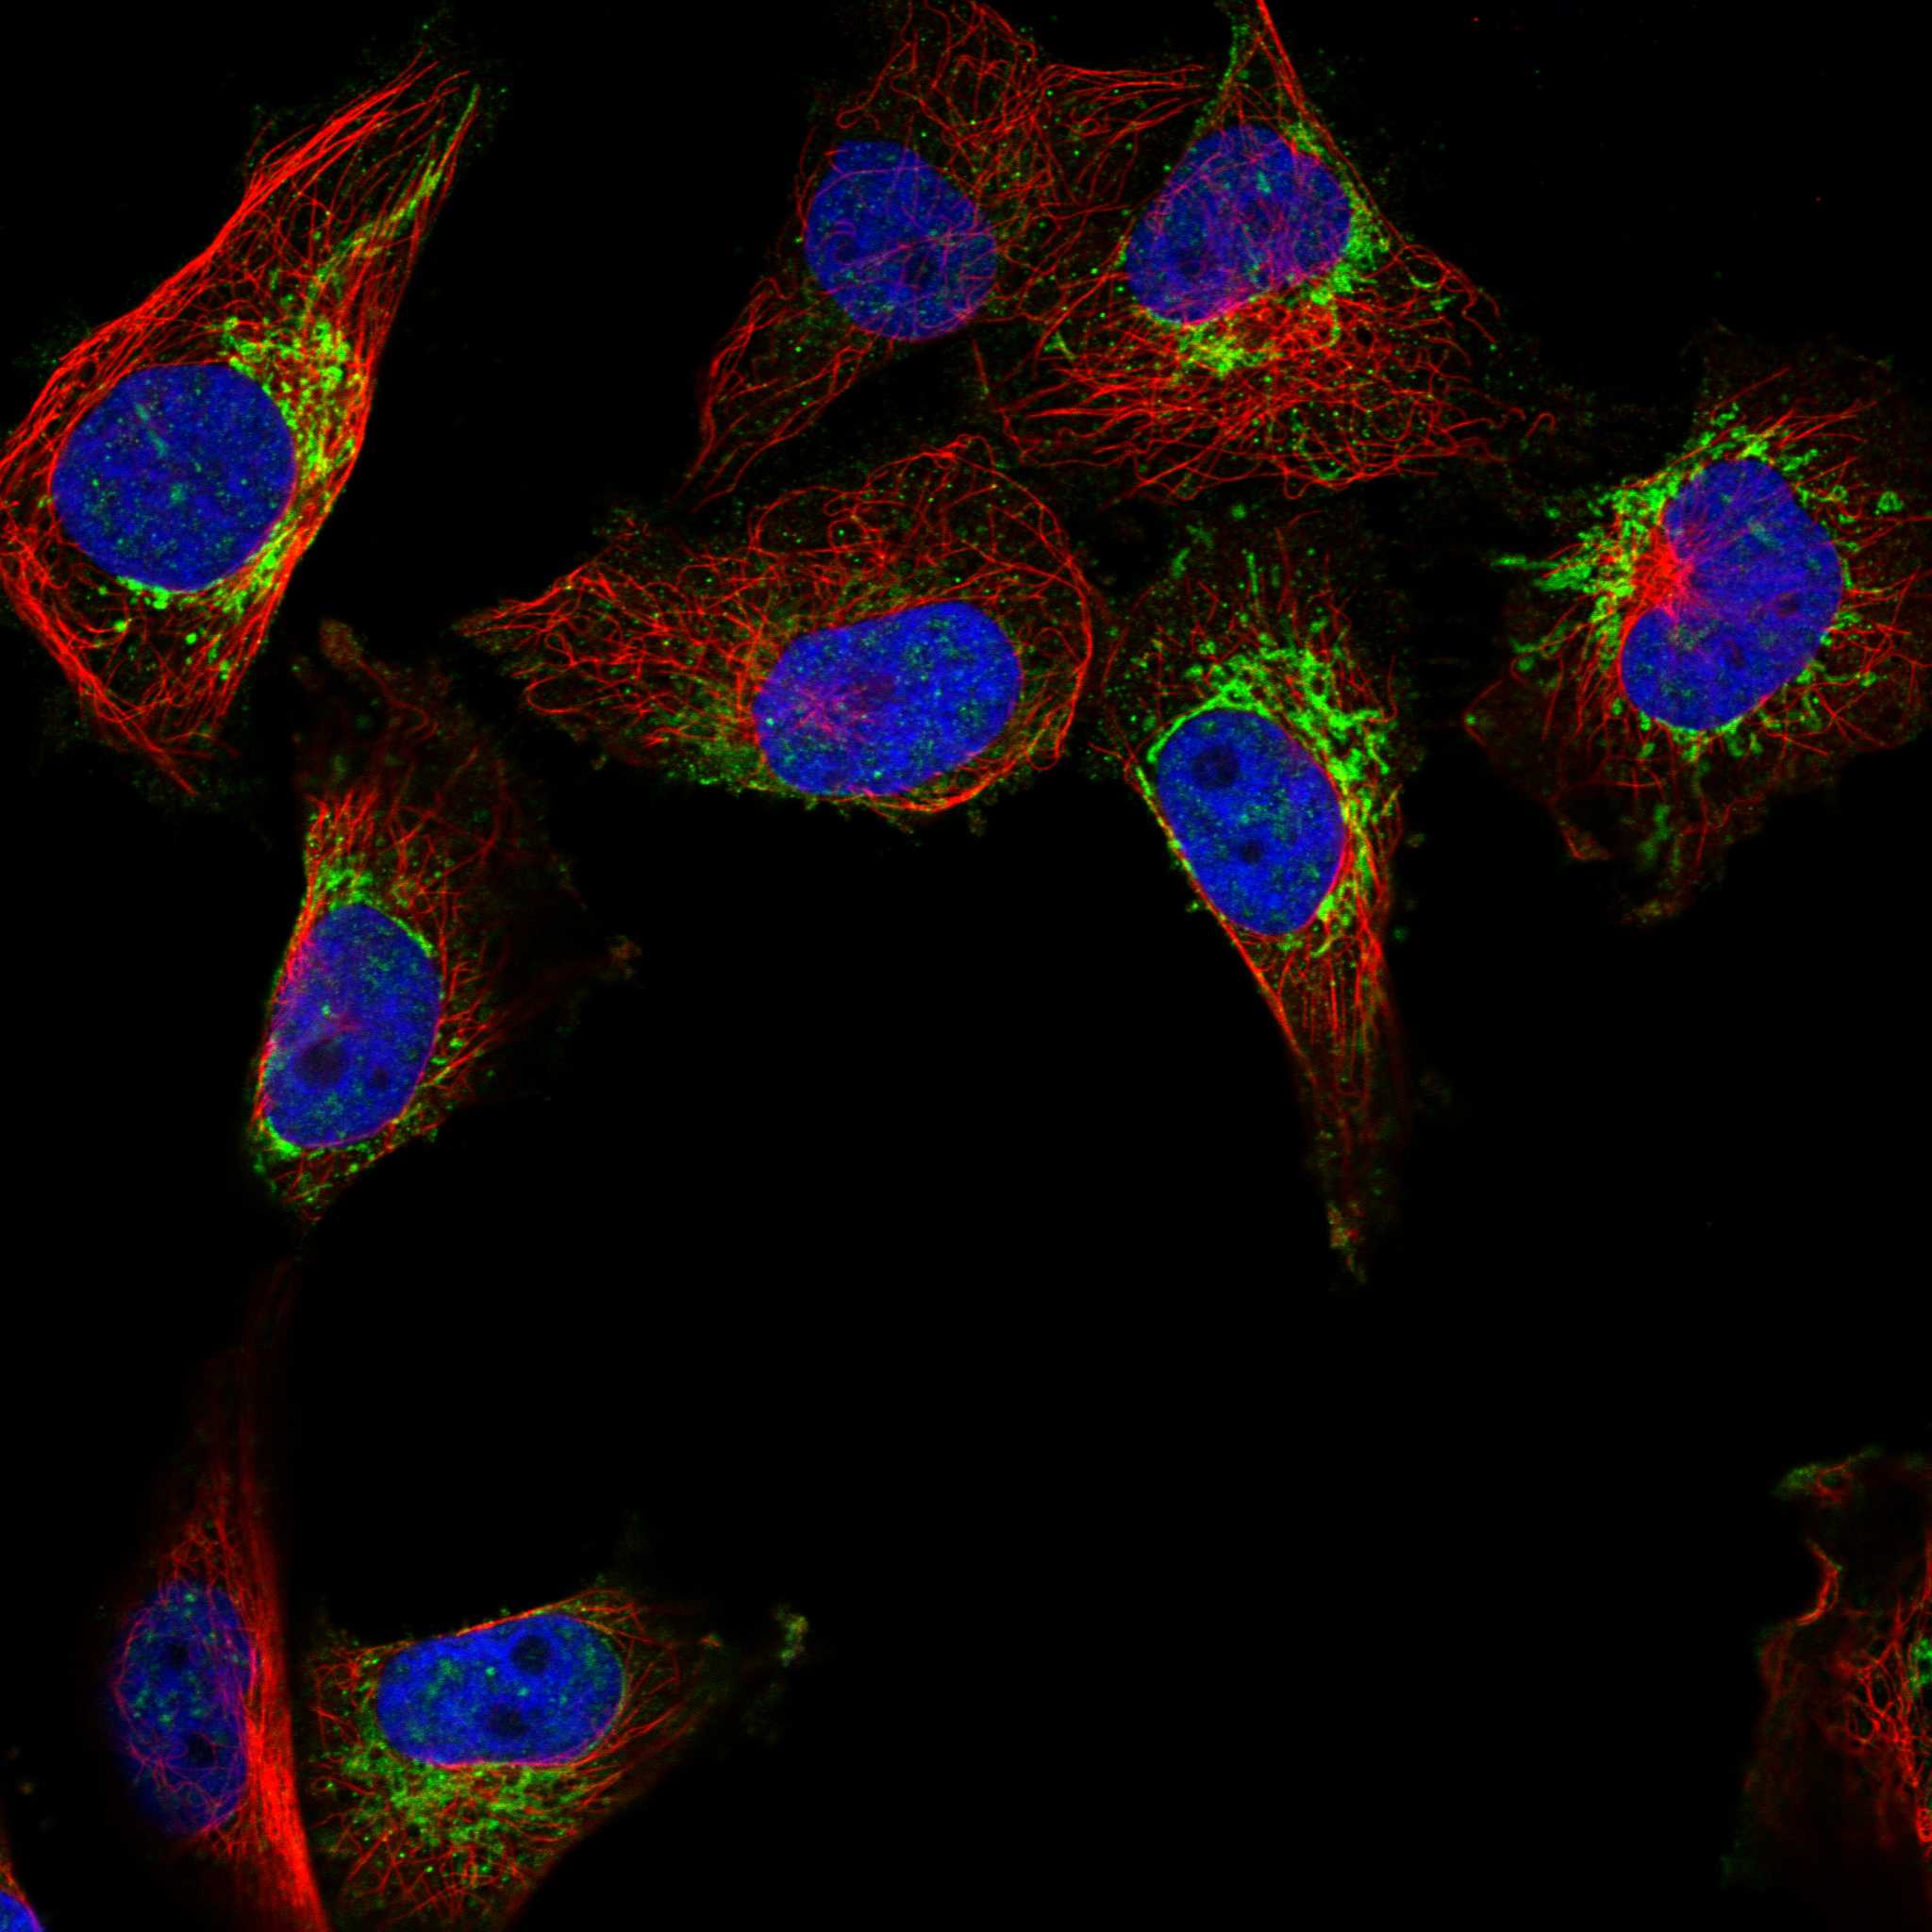
IF/ICC Q&A: what location should fluorescence show?Mainly mitochondria (HPA: supported ICC-IF location). HPA also reports perinuclear theca, calyx, and principal piece in sperm (HPA: approved additional ICC-IF locations); this is localization context, not an IHC protocol.
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
High-reference tissue is blank.The expected cell population may be absent, or an antibody or detection step may have failed (HPA: High cardiomyocytes and colon glandular cells; standard IHC practice).Confirm cell identity and section integrity, then run a documented positive control and check the antibody, detection reagents, and counterstain sequence (standard IHC practice).
Signal is weak but granular in a reference tissue.HPA's High category is an observed pattern, not a required intensity for every section (HPA: tissue IHC). General IHC variables can affect the visible result (standard IHC practice).Compare with the same-run positive control; review the documented IHC-P dilution and retrieval conditions for the antibody used (standard IHC practice). No ACADM-specific retrieval effect is supplied.
Nuclei or cell borders dominate the stain.That distribution disagrees with mitochondrial matrix localization and no transmembrane segment (UniProt P11310: location and topology).Recheck morphology and no-primary controls, then assess nonspecific binding and detection background before scoring ACADM (standard IHC practice).
Adipocytes or fibroblasts appear strongly positive.Those cell classes are reported Not detected in the specified HPA tissues; cross-reactivity or endogenous detection activity is possible (HPA: tissue IHC; standard IHC interpretation).Verify the cell type, compare a no-primary control, and interpret against a same-run HPA-positive cell population (standard IHC practice; HPA: tissue IHC).
Diffuse brown background hides cell boundaries.Nonspecific binding, incomplete washing, or detection-system background can obscure granular cytoplasmic staining (standard chromogenic IHC practice; HPA: tissue IHC profile).Inspect no-primary controls; review blocking, wash steps, and chromogen development using the detection system's instructions (standard chromogenic IHC practice).
Granular signal varies among tissue regions.HPA describes ubiquitous granular expression but reports different staining levels among cell populations (HPA: tissue IHC profile and cell-level results).Score identified cell types separately, compare regions with the same-run controls, and avoid treating low or absent staining in one cell population as whole-section failure (standard IHC interpretation; HPA: tissue IHC).

Sample controls for ACADM IHC & IF

🧪Run adrenal gland first and score glandular cells for ACADM staining (HPA: High in adrenal gland glandular cells). Run skin as the negative comparator and score its basal-layer cells (HPA: Not detected in skin basal-layer cells); on the adrenal slide, use non-glandular cells with background-only staining as internal comparators, without assuming all such cells are ACADM-negative (HPA: High is reported for glandular cells).
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Adipose tissue (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show ACADM in U-251MG, U2OS, A-431, Sperm, KOLF2.1J, with annotated localisation: Mitochondria (supported) (HPA subcellular).
Technical controls: Include a no-primary, secondary-only control, a host- and isotype-matched rabbit antibody control, and ACADM knockout tissue or a validated peptide-block control (caption: rabbit primary antibody; standard IHC practice). Check endogenous peroxidase and biotin before interpreting DAB signal because the reported detection uses a biotinylated secondary and streptavidin–biotin complex (caption: SABC-DAB detection).
⚠️Feasibility: The supplied evidence reports no ACADM-specific fixation window or fixation effect, and the exact A02383-2 tissue-IHC caption leaves the fixative unreported (caption: fixative not stated). Heat retrieval in EDTA at pH 8.0 was used for the reported paraffin-section staining, but its necessity in adrenal gland is unreported (caption: EDTA retrieval in bladder carcinoma tissue). Whether frozen sections or IF are easier is unreported; inspect adrenal sections for pigment that could complicate chromogenic scoring (standard IHC practice).

HPA tissue IHC evidence for ACADM

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Appendix Lymphoid tissue High Protein (IHC) HPA →
Bronchus Respiratory epithelial cells High Protein (IHC) HPA →
Colon Glandular cells High Protein (IHC) HPA →
Duodenum Glandular cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Adipose tissue Adipocytes Not detected Protein (IHC) HPA →
Skin Cells in basal layer Not detected Protein (IHC) HPA →
Soft tissue Fibroblasts Not detected Protein (IHC) HPA →
Section 3

Advanced ACADM IHC Tips

Use the catalog antibody’s paraffin section evidence and ACADM’s mitochondrial localisation to troubleshoot chromogenic IHC; assess IF separately.

Which retrieval conditions should I use if ACADM staining is weak in paraffin sections?
Start with heat mediated antigen retrieval in EDTA at pH 8.0 (datasheet A02383-2). The selected paraffin section image used that retrieval, followed by 10% goat serum and 2 μg/ml primary antibody overnight at 4°C (caption A02383-2). If staining is weak, first check heating consistency, section adhesion and whether the primary incubation matched the documented conditions (caption A02383-2; standard IHC practice). Compare any longer retrieval or alternative buffer on adjacent sections, because excessive heating can damage morphology and complicate granular cytoplasmic scoring (standard IHC practice; HPA: granular cytoplasmic expression). Include a documented positive tissue control in each comparison (HPA: high in heart muscle cardiomyocytes; standard IHC practice).
How should I troubleshoot fixation when ACADM staining varies between paraffin blocks?
The selected image documents a paraffin section but does not state its fixative, so ACADM specific fixation sensitivity is unknown (caption A02383-2). Record fixative, fixation duration and processing history for each block before attributing differences to the antibody (standard IHC practice). Run blocks side by side with the documented EDTA pH 8.0 retrieval and 2 μg/ml primary incubation overnight at 4°C (caption A02383-2; standard IHC practice). Check tissue preservation and granular cytoplasmic staining together; damaged morphology makes cellular scoring unreliable (HPA: granular cytoplasmic expression; standard IHC practice). Do not infer a fixation effect from tissue expression patterns or ACADM sequence annotations (HPA: tissue IHC profile; UniProt P11310: protein annotations).
What staining pattern supports ACADM localisation in a tissue section?
Expect cytoplasmic staining with a granular pattern in positive cells (HPA: tissue IHC profile). That pattern is consistent with ACADM in the mitochondrial matrix, although chromogenic IHC alone cannot resolve matrix localisation (UniProt P11310: mitochondrial matrix; standard IHC practice). Compare candidate staining with a positive cellular reference, such as cardiomyocytes in heart muscle, where HPA reports high expression (HPA: high in heart muscle cardiomyocytes). Assess cytoplasm and nuclei separately at the same magnification, then inspect whether granules lie within intact cells (HPA: cytoplasmic granular pattern; standard IHC practice). Predominantly nuclear or diffuse extracellular DAB warrants a background and morphology check before an ACADM interpretation (UniProt P11310: mitochondrial matrix; standard IHC practice).
Can isoforms or protein processing explain an unexpected ACADM staining pattern?
ACADM has 2 annotated isoforms, and the annotated mature chain spans residues 26–421 (UniProt P11310: isoforms and chain). The supplied antibody evidence does not identify its epitope, so neither isoform recognition nor sensitivity to processing can be assigned to this reagent (caption A02383-2; UniProt P11310: isoforms and chain). ACADM also has annotated modified residues, including acetylation and succinylation, but their effects on this antibody’s IHC staining are unreported (UniProt P11310: modified residues; caption A02383-2). If staining differs between specimens, compare morphology, retrieval and controls before invoking an epitope explanation (standard IHC practice). Document any epitope mapping or isoform validation obtained later alongside the scored sections (standard IHC practice).
How can I assess ACADM by multiplex IF alongside cell identity markers?
For a separate IF experiment, pair ACADM with a marker identifying the expected cell population, such as cardiomyocytes in heart muscle, and compare intracellular patterns within those cells (HPA: high in heart muscle cardiomyocytes; standard IF practice). Assign the weaker signal to a spectrally separated far red channel when tissue autofluorescence compromises shorter wavelengths (standard IF practice). ACADM resides in the mitochondrial matrix and has no annotated transmembrane segment, so optimise detergent permeabilisation for access inside mitochondria rather than treating it as a surface epitope (UniProt P11310: matrix localisation and topology; standard IF practice). Titrate permeabilisation while checking cell structure and mitochondrial pattern (standard IF practice; HPA: mitochondrial localisation). The paraffin IHC caption does not establish IF fixation or antibody performance (caption A02383-2).
How do I distinguish granular ACADM staining from chromogenic background?
Inspect whether DAB granules remain within intact cytoplasm; ACADM has a granular cytoplasmic tissue pattern and mitochondrial localisation (HPA: tissue IHC profile; UniProt P11310: mitochondrial matrix). The selected workflow used 10% goat serum, a biotinylated secondary antibody and a streptavidin biotin complex with DAB (caption A02383-2). Include a primary omission control, inspect endogenous biotin or peroxidase signal, and apply an appropriate peroxidase block as part of the chromogenic workflow (caption A02383-2; standard IHC practice). Compare controlled sections at matched exposure to DAB and assess diffuse staining, tissue edges and damaged regions separately (standard IHC practice). Reduce nonspecific signal by optimising blocking and washing while preserving positive cell staining (standard IHC practice; HPA: high in heart muscle cardiomyocytes).
How should I quantify ACADM staining across specimens? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and tissue region before scoring, because ACADM expression varies by cell type and the expected signal is granular cytoplasmic (HPA: tissue IHC profile). An H-score can combine the percentage of positive cells at each intensity; alternatively, report percent positive cells or positive cell density per mm² (standard IHC scoring practice). Apply the same positivity threshold, counterstain assessment and image acquisition settings to every section (standard IHC practice). Normalise counts to viable cells or analysed viable tissue area, and report compartment specific staining separately from background (standard IHC scoring practice; UniProt P11310: mitochondrial matrix). Record retrieval batch and control tissue performance alongside scores to identify staining drift (caption A02383-2: EDTA pH 8.0 retrieval; standard IHC practice).
What would make an apparent ACADM positive result unconvincing?
A convincing result places granular cytoplasmic signal in intact cells, consistent with the tissue IHC profile and mitochondrial matrix localisation (HPA: granular cytoplasmic expression; UniProt P11310: mitochondrial matrix). Compare cell identity with a supported positive population, such as heart muscle cardiomyocytes, while recognising that ACADM is expressed across many tissues (HPA: high in heart muscle cardiomyocytes; HPA: ubiquitous expression). Strong nuclear, extracellular or tissue edge staining should prompt review of morphology and controls before calling it ACADM (UniProt P11310: mitochondrial matrix; standard IHC practice). Exclude necrotic areas from scoring and check primary omission controls for endogenous enzyme or detection system signal (standard IHC practice). Interpret intensity against the same batch’s positive control and documented retrieval conditions (caption A02383-2; standard IHC practice).
Boster reagents

Best ACADM / Medium-chain specific acyl-CoA dehydrogenase, mitochondrial IHC Antibodies

A02383-2 and A02383-3 have human paraffin-section IHC and HeLa-cell IF images (catalog image captions); both list human, mouse and rat reactivity (catalog applications/reactivity).

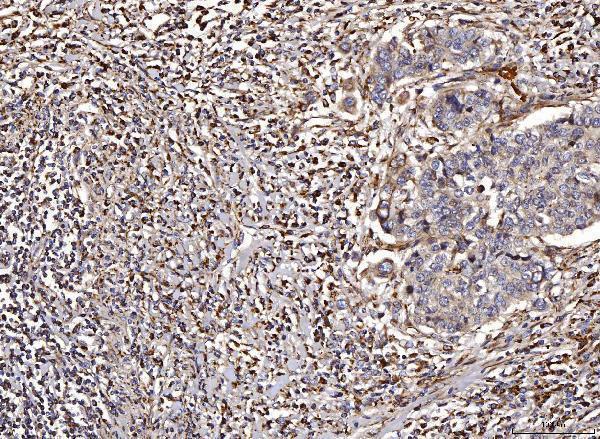
Real IHC data IHC analysis of ACADM/MCAD using anti-ACADM/MCAD antibody (A02383-2). ACADM/MCAD was detected in a paraffin-embedded section of human bladder epithelial carcinoma tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ACADM/MCAD Antibody (A02383-2) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC) (Catalog # SA1022) with DAB as the chromogen.
Anti-ACADM/MCAD Antibody ®
Cat # A02383-2
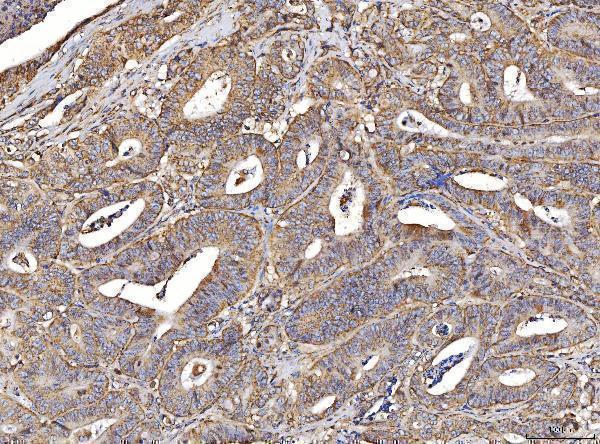
Real IHC data IHC analysis of ACADM/MCAD using anti-ACADM/MCAD antibody (A02383-3). ACADM/MCAD was detected in a paraffin-embedded section of human colorectal cancer tissue. Heat mediated antigen retrieval was performed in EDTA buffer (pH 8.0, epitope retrieval solution). The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 2 μg/ml rabbit anti-ACADM/MCAD Antibody (A02383-3) overnight at 4°C. Peroxidase Conjugated Goat Anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using HRP Conjugated Rabbit IgG Super Vision Assay Kit (Catalog # SV0002) with DAB as the chromogen.
Anti-ACADM/MCAD Antibody ®
Cat # A02383-3

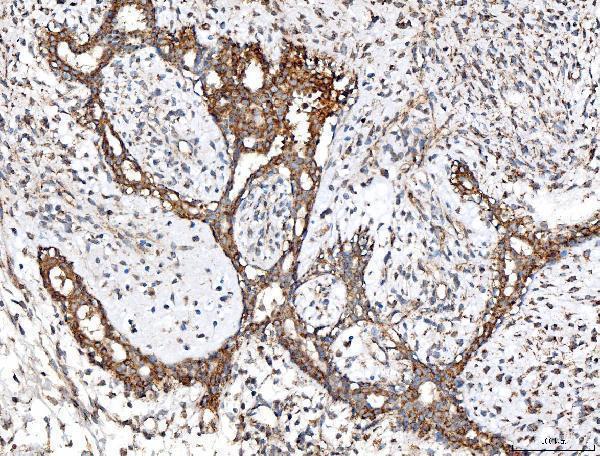
A02383-2 will render with IHC detection in human bladder epithelial carcinoma; its additional captions show breast carcinoma, Classic Hodgkin's lymphoma and hepatocellular carcinoma, plus IF in HeLa cells (A02383-2 image captions). A02383-3 will render with IHC detection in human colorectal cancer; another caption shows lung cancer, and an IF caption shows HeLa cells (A02383-3 image captions).

Which to pick: For tissue IHC, choose A02383-2 if its broader set of human paraffin-section examples matches your study; its caption uses EDTA retrieval at pH 8.0 and 2 μg/ml primary antibody, with the fixative unreported (A02383-2 IHC image captions). For IF/ICC, A02383-3 has a HeLa-cell IF example at 5 μg/ml (A02383-3 IF image caption). For mouse or rat work, either SKU lists reactivity, but the supplied IHC and IF images show human samples only; clonality is unreported for both (catalog reactivity; image captions; clone fields).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P11310 (ACADM_HUMAN, Medium-chain specific acyl-CoA dehydrogenase, mitochondrial).
  2. Human Protein Atlas. ACADM tissue IHC expression (reliability: Enhanced).
  3. Human Protein Atlas. ACADM subcellular location (ICC-IF): Mainly localized to the mitochondria. In addition localized to the perinuclear theca, calyx and principal piece..
  4. Human Protein Atlas. ACADM antibody validation summary (2 antibodies).
  5. Low ACADM expression predicts poor prognosis and suppressive tumor microenvironment in clear cell renal cell carcinoma. Scientific reports 2024 — PMC11045743.
  6. Low expression of fatty acid oxidation related gene ACADM indicates poor prognosis of renal clear cell carcinoma and is related to tumor immune infiltration. Oncology research 2024 — PMC10865730.
  7. Schisandrin B Attenuates Renal Fibrotic Remodeling in Association with Restoration of a PPARα-Related Tubular Fatty-Acid Oxidation Program. Biomedicines 2026 — PMC13297011.
  8. Three novel hub genes and their clinical significance in clear cell renal cell carcinoma. Journal of Cancer 2019 — PMC6909945.
  9. PubMed PMID:3035565 — UniProt-cited evidence.
  10. PubMed PMID:1731887 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.