This website uses cookies to ensure you get the best experience on our website.


- Table of Contents
Plan chromogenic IHC on paraffin sections with the catalog antibody at 0.5–1 μg/ml (datasheet M05278). Use liver hepatocytes as a positive reference and assess cytoplasmic staining with the reported off-target caveat in mind (HPA tissue IHC).

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.
| Expected localisation | Cytoplasmic in liver tissue (HPA tissue IHC) | |
| Staining pattern | Hepatocytes: medium cytoplasmic staining (HPA tissue IHC) | |
| Antigen retrieval | EDTA pH 8.0 HIER, heat-mediated (datasheet M05278) | |
| Positive control | Liver | |
| Negative control | Adipose tissue+4 more · see all |
| Fixation | Keep fixation consistent across sections. (standard IHC practice; not target-specific) | |
| Caveat | Presumed off-target staining has been observed (HPA tissue IHC) | |
| Regulation | Liver-enriched expression (UniProt) | |
| Isoform / epitope | 3 isoforms; epitope coverage is unknown (UniProt) |
The catalog antibody’s IHC-P protocol (datasheet M05278) is accompanied by 2 published AKR1D1 paraffin IHC protocols (PMC8417905; PMC7906155).
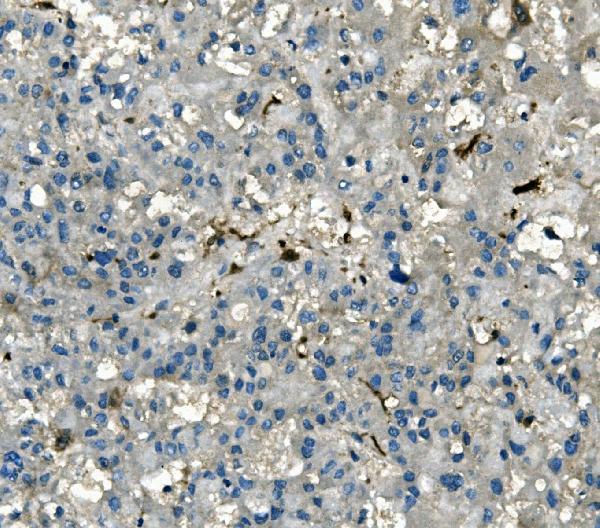
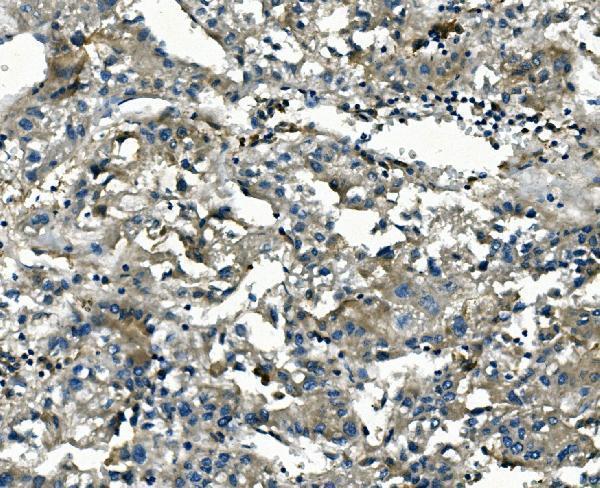
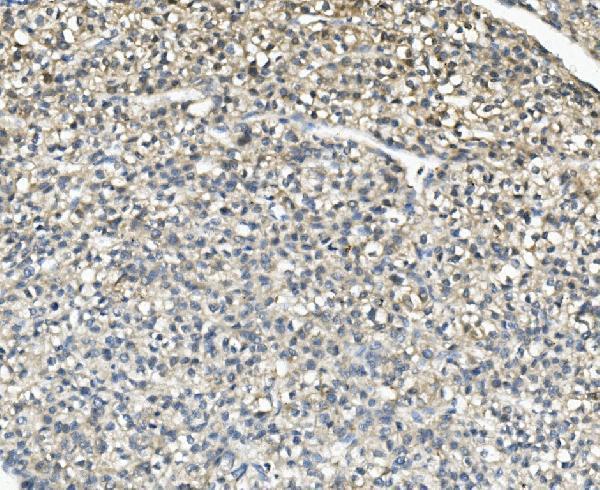
| Sample | Paraffin-embedded human liver cancer tissue; fixative not specified (datasheet M05278) |
| Fixation | Image fixative and duration unreported (datasheet M05278); verify before use. |
| Sectioning | 4–5 µm sections on charged slides (standard) |
| Deparaffinisation | Xylene, graded ethanol series to water (standard) |
| Antigen retrieval | Heat retrieval: EDTA pH 8.0 (datasheet M05278); 20 min, 95–100 °C (standard) |
| Peroxidase block | 3% H2O2, 10 min, room temperature (standard) |
| Blocking | 10% goat serum (datasheet M05278) |
| Primary antibody | Mouse monoclonal (clone 6I4) anti-AKR1D1, 0.5-1μg/ml (datasheet M05278) |
| Primary incubation | Overnight at 4 °C (datasheet M05278) |
| Detection | Streptavidin-biotin complex (SABC), DAB chromogen (datasheet M05278) |
| Counterstain | Hematoxylin, blue, dehydrate and mount (standard) |
| Expected result | AKR1D1-positive staining in hepatocytes of liver (HPA tissue IHC: Medium). HPA tissue profile: Selective cytoplasmic expression in liver. No signal in the no-primary control. |
AKR1D1 is a cytoplasmic protein with no transmembrane segment (UniProt P51857). In paraffin-section IHC, expect selective cytoplasmic staining of liver hepatocytes at medium intensity (HPA tissue IHC). HPA rates the tissue pattern Enhanced, while noting medium consistency with RNA expression and presumed off-target staining that was disregarded (HPA tissue IHC). Interpret other staining against that qualified reference pattern.
| Hepatocytes show clear cytoplasmic chromogen, with nuclei less stained than cytoplasm (HPA tissue IHC). | This matches the reported medium-level hepatocyte signal and selective liver pattern (HPA tissue IHC). Assess cells and compartments, not just whether the section looks brown. A liver positive control should show recognizable hepatocyte cytoplasm without widespread staining of unrelated structures (HPA tissue IHC; general IHC practice). |
| Nuclei dominate the signal in liver IHC, with little hepatocyte cytoplasmic staining. | That differs from the reported liver IHC pattern (HPA tissue IHC). Check the counterstain, chromogen distribution and antibody controls before calling nuclear IHC positive. HPA separately reports nucleoplasm as the main ICC-IF location, so a nuclear IF image alone does not resolve an unexpected paraffin IHC result (HPA subcellular ICC-IF). |
| Cells outside the expected hepatocyte population stain strongly, including a tissue reported as negative (HPA tissue IHC). | Treat this as a specificity or detection concern, especially because HPA disregarded presumed off-target binding in its tissue assessment (HPA tissue IHC). Cross-reactivity or endogenous detection activity can mimic a positive IHC result (general IHC practice); compare a tissue-matched negative control and a no-primary control before assigning AKR1D1 expression. |
| Hepatocytes and surrounding tissue have an even haze or poorly defined brown signal. | Diffuse staining lacks the selective cytoplasmic distribution reported for hepatocytes (HPA tissue IHC). Review no-primary controls, blocking, washes and detection chemistry for nonspecific background (general IHC practice). Do not score uniform slide-wide color as cellular AKR1D1 staining solely because liver is the expected positive tissue (HPA tissue IHC). |
| No convincing hepatocyte cytoplasmic signal appears in the liver control. | That conflicts with the reported medium-level hepatocyte staining (HPA tissue IHC), but a single negative section cannot establish absent AKR1D1. Check section integrity, the catalog antibody’s IHC-P conditions and detection controls (general IHC practice). Confirm that the tissue contains assessable hepatocytes before interpreting an experimental negative. |
| Positive tissue and cell type | Liver hepatocytes are the supplied medium-level IHC positive reference (HPA tissue IHC). UniProt describes liver as highly expressing AKR1D1 (UniProt P51857). Use hepatocyte localization when judging a run; tissue-wide color by itself is less informative than a cell-resolved pattern (general IHC practice). |
| Negative tissue comparison | HPA reports adipocytes in adipose tissue and glandular cells in adrenal gland as not detected, among other listed examples (HPA tissue IHC). These are comparison patterns, not proof that every specimen from those tissues must be entirely colorless (HPA tissue IHC; general IHC practice). |
| IHC antibody evidence | HPA057002 has Enhanced IHC validation, and HPA’s tissue summary also flags medium RNA agreement and disregarded presumed off-target binding (HPA antibodies; HPA tissue IHC). Give greatest weight to the reported hepatocyte cytoplasmic pattern while checking unexpected staining with controls; Enhanced does not make every positive cell specific. |
| Cellular topology | AKR1D1 is annotated as cytoplasmic, without a transmembrane segment, signal peptide, propeptide or annotated modified residues (UniProt P51857). These annotations support a cytoplasmic interpretation; they do not identify the antibody epitope or establish any AKR1D1-specific fixation or antigen-retrieval effect. |
| Alternative isoforms | UniProt lists 3 isoforms (UniProt P51857). The supplied record gives no isoform-specific IHC pattern or antibody epitope, so a difference between samples cannot be assigned to an isoform from staining alone. Keep the interpretation at the protein-pattern level unless separate isoform evidence becomes available. |
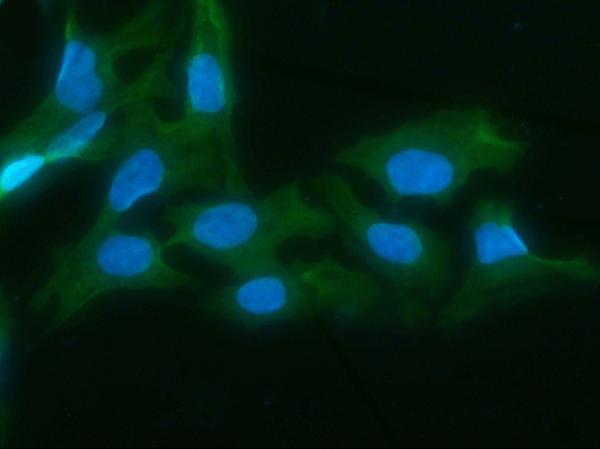
| IF/ICC Q: Should nucleoplasmic staining be expected? | A: HPA reports nucleoplasm as the main ICC-IF location and cytosol as an additional location (HPA subcellular ICC-IF). HPA057002 is rated Uncertain for ICC (HPA antibodies). This is separate from the selective cytoplasmic liver IHC result; evaluate IF/ICC on its own guide page, without treating its pattern as an IHC-P protocol option. |
| Situation | Likely cause | Next action |
|---|---|---|
| Liver control is blank or much weaker than the reported medium hepatocyte pattern (HPA tissue IHC). | A failed staining or detection step, unsuitable section, or an unoptimized IHC-P condition is possible (general IHC practice). The supplied sources do not establish an AKR1D1-specific fixation sensitivity. | Check tissue morphology and hepatocyte content, then verify the catalog antibody’s actual IHC-P instructions and reagent controls. Review retrieval and detection as general IHC variables; do not infer a target-specific retrieval requirement from HPA staining (general IHC practice). |
| Nuclear chromogen predominates in paraffin liver IHC. | The distribution does not match HPA’s selective cytoplasmic liver IHC report (HPA tissue IHC). Nucleoplasmic ICC-IF localization is a separate observation (HPA subcellular ICC-IF). | Compare nuclear counterstain with chromogen in a no-primary section and inspect hepatocyte cytoplasm. Reassess antibody specificity if nuclear color persists, documenting the IHC/ICC difference rather than merging the two readouts (general IHC practice; HPA tissue IHC). |
| A reported negative cell population shows strong staining (HPA tissue IHC). | Nonspecific antibody binding or endogenous enzyme activity may account for unexpected chromogen (general IHC practice). HPA’s reliability note also records presumed off-target staining that was disregarded (HPA tissue IHC). | Compare a no-primary control and an appropriate tissue comparison; check endogenous enzyme blocking for the chosen chromogenic system (general IHC practice). Report the unexpected cell type explicitly and avoid calling it AKR1D1 positive without corroboration. |
| Brown haze obscures hepatocyte borders or fills the whole section. | Excess background from antibody, blocking, washing or detection can obscure cell localization (general IHC practice). A uniform haze differs from HPA’s selective cytoplasmic hepatocyte pattern (HPA tissue IHC). | Inspect the no-primary control, wash performance and detection background, then adjust only the variables identified by those controls (general IHC practice). Score AKR1D1 only where hepatocyte cytoplasm remains clearly distinguishable (HPA tissue IHC). |
| Only scattered cells stain in a liver section despite intact hepatocytes. | The distribution is less convincing than the reported hepatocyte pattern (HPA tissue IHC). Patchy technical staining or an atypical specimen could contribute; these sources do not establish which explanation applies. | Examine morphology and control sections, document which cell types stain, and repeat using the catalog antibody’s IHC-P guidance if the controls are unsatisfactory (general IHC practice). Keep the result indeterminate until the cellular pattern can be assessed. |
| An IF/ICC image appears nuclear while the liver IHC slide appears cytoplasmic. | HPA reports mainly nucleoplasmic ICC-IF localization with additional cytosol, but selective cytoplasmic liver tissue IHC (HPA subcellular ICC-IF; HPA tissue IHC). The listed antibody’s ICC status is Uncertain (HPA antibodies). | Record assay, specimen and antibody validation separately. Judge this paraffin IHC result against hepatocyte cytoplasmic staining (HPA tissue IHC); use the separate IF/ICC guide for fluorescence controls and localization assessment. |


Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Enhanced — Medium consistency between antibody staining and RNA expression data. Presumed off target binding observed and disregarded.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Liver | Hepatocytes | Medium | Protein (IHC) | HPA → |
| Tissue | Cell type | Level | Evidence | Source |
|---|---|---|---|---|
| Adipose tissue | Adipocytes | Not detected | Protein (IHC) | HPA → |
| Adrenal gland | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Appendix | Glandular cells | Not detected | Protein (IHC) | HPA → |
| Bone marrow | Hematopoietic cells | Not detected | Protein (IHC) | HPA → |
| Breast | Adipocytes | Not detected | Protein (IHC) | HPA → |
Troubleshoot AKR1D1 staining in paraffin sections using the catalog antibody’s tissue image, tissue expression evidence and appropriate IHC controls.
Both antibodies have IHC images from paraffin-embedded human liver cancer tissue (catalog IHC captions); A05278-2 also has IF data from U2OS cells (catalog IF caption). Both list human, mouse, and rat reactivity (catalog).
M05278, a mouse monoclonal antibody, has an IHC image from paraffin-embedded human liver cancer tissue (catalog: M05278 IHC caption). A05278-2, a rabbit antibody, has an IHC image from paraffin-embedded human liver cancer tissue and an IF image from U2OS cells (catalog: A05278-2 IHC and IF captions).
Which to pick: For paraffin-section IHC, either SKU has its own human tissue image using EDTA retrieval at pH 8.0 and 1 μg/ml primary antibody (catalog: each SKU’s IHC caption); the fixative is unreported in both captions. Choose A05278-2 for IF/ICC because those applications are listed and its IF image uses U2OS cells at 4 μg/ml (catalog: A05278-2 applications and IF caption). Both SKUs list human, mouse, and rat reactivity for cross-species planning, while their IHC images show human tissue only (catalog: reactivity and IHC captions).