AKT2 / RAC-beta serine/threonine-protein kinase · IHC design guide

Design Immunohistochemistry for AKT2

Plan AKT2 staining in paraffin sections using breast glandular cells as a high-staining reference and heart cardiomyocytes as a not-detected reference (HPA tissue IHC). Use the IHC-validated antibody to assess cytoplasmic staining, and interpret the reference patterns with the atlas’s uncertain reliability in mind (datasheet PB9043; HPA tissue IHC).

Evidence assembled Oct 2026 · For research use; verify linked source records and product datasheet before use
Immunohistochemistry protocol sheet for AKT2 (IHC for AKT2): expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody PB9043, validated IHC image, and IHC protocol steps
Printable AKT2 IHC protocol sheet — expected localisation General cytoplasmic tissue staining (HPA tissue IHC), antibody PB9043, controls and protocol steps. Open the full AKT2 IHC guide →

AKT2 Immunohistochemistry Experimental Design Guide

Expected localisation, validated protocols, controls and antibodies — the at-a-glance facts below, then the full design guide.

Must know before staining
Expected localisation General cytoplasmic tissue staining (HPA tissue IHC)
Staining pattern Cytoplasmic staining in glandular and other cells (HPA tissue IHC)
Antigen retrieval Citrate pH 6 HIER, heat-mediated (datasheet PB9043)
Positive control ⓘ Adrenal gland+4 more · see all
Negative control ⓘ Heart muscle
Important caveats
Reasons your staining may differ from the expected pattern.
Fixation Keep fixation consistent across paraffin sections. (standard IHC practice; not target-specific)
Caveat Check antibody specificity against related AKT1/3 (UniProt)
Regulation No specific expression regulator reported (UniProt)
Isoform / epitope 2 isoforms; verify epitope coverage (UniProt)
Section 1

Recommended AKT2 IHC & IF Protocols

The catalog antibody protocol uses citrate pH 6 retrieval (datasheet: PB9043). The published IHC protocols below cover breast carcinoma, xenografts and lung sections, and basal cell carcinoma (PMC8353139; PMC9224635; PMC3271997).

Recommended immunohistochemistry (IHC-P) protocol parameters
SampleParaffin-embedded human lung cancer tissues; fixative not specified (datasheet PB9043)
FixationImage fixative and duration unreported (datasheet PB9043); verify before use.
Sectioning4–5 µm sections on charged slides (standard)
DeparaffinisationXylene, graded ethanol series to water (standard)
Antigen retrievalHeat retrieval: Citrate pH 6, 20 min (datasheet PB9043)
Peroxidase block3% H2O2, 10 min, room temperature (standard)
Blocking10% goat serum (datasheet PB9043)
Primary antibodyRabbit anti-AKT2, 0.5-1μg/ml (datasheet PB9043)
Primary incubationOvernight at 4 °C (datasheet PB9043)
DetectionStreptavidin-biotin complex (SABC), DAB chromogen (datasheet PB9043)
CounterstainHematoxylin, blue, dehydrate and mount (standard)
Expected resultAKT2-positive staining in glandular cells of adrenal gland (HPA tissue IHC: High). HPA tissue profile: General cytoplasmic expression. No signal in the no-primary control.
💡Decision noteFor the catalog antibody, start with heat-mediated citrate pH 6 retrieval (datasheet: PB9043); a published basal cell carcinoma protocol also used citrate pH 6 (PMC3271997).
Section 2

What Is the Expected AKT2 Staining Pattern?

AKT2 is widely expressed and can localize to cytoplasm, nucleus, cell membrane, and early endosomes; it has no transmembrane segment (UniProt P31751). In paraffin-section IHC, expect mainly cytoplasmic staining in the cell types identified by HPA, including glandular cells in breast and adrenal gland (HPA: High). Treat tissue-level predictions cautiously: HPA describes general cytoplasmic expression but rates its tissue IHC profile Uncertain because antibody staining and RNA data have medium consistency (HPA: Uncertain).

What am I looking at on my slide?
Cytoplasmic staining in breast or adrenal gland glandular cells (HPA: High).This fits HPA's general cytoplasmic IHC profile (HPA: General cytoplasmic expression). Compare the stained cells with adjacent unstained structures, a negative control, and the same run's positive control before scoring intensity (general IHC practice). HPA's Uncertain reliability limits how strongly one section can confirm specificity (HPA: Uncertain).
Predominantly extracellular, stromal, or luminal deposit with little intracellular signal.This is outside the recorded AKT2 compartments: cytoplasm, nucleus, membrane, and early endosome (UniProt P31751). Check whether the deposit follows tissue edges, folds, or reagent pooling, which can create artifactual chromogen patterns (general IHC practice). Nuclear or membrane signal alone needs context: both are documented AKT2 locations (UniProt P31751).
Strong cardiomyocyte staining in heart muscle (HPA: Not detected).Question antibody specificity or endogenous detection activity before calling this AKT2 positive (HPA: Not detected; general IHC practice). HPA's tissue IHC assessment is Uncertain, so this discrepancy warrants controls and replication rather than an automatic biological conclusion (HPA: Uncertain). Compare cell identity and staining distribution with the positive-control section (general IHC practice).
Diffuse brown haze across several cell types and extracellular spaces.A widespread haze does not reproduce HPA's cell-associated, generally cytoplasmic profile (HPA: General cytoplasmic expression). In chromogenic IHC, incomplete blocking, excess antibody or detection reagent, and residual endogenous enzyme activity can raise background (general IHC practice). Judge cell-specific signal only after assessing a no-primary control (general IHC practice).
No signal in breast or adrenal gland glandular cells (HPA: High).This conflicts with HPA's observed high staining in those cells, but the profile is rated Uncertain (HPA: High; HPA: Uncertain). First check tissue preservation, section processing, control staining, and the antibody's validated IHC-P conditions (general IHC practice). A blank positive-control section cannot distinguish absent AKT2 from an unsuccessful staining run (general IHC practice).
💡Expected AKT2 appearanceCall a result consistent with AKT2 when cell-associated, mainly cytoplasmic staining is conspicuous in HPA-high glandular cells (HPA: General cytoplasmic expression; HPA: High); diffuse extracellular chromogen is suspect (UniProt P31751 topology; general IHC practice).
How each factor affects the staining
Compartment and topologyAKT2 has no signal peptide or transmembrane segment, while cytoplasm, nucleus, membrane recruitment, and early endosomes are documented (UniProt P31751). A membrane rim can therefore be plausible in context; an extracellular-only pattern lacks support (UniProt P31751).
Tissue selection and evidence strengthBreast and adrenal gland glandular cells are HPA-high; heart cardiomyocytes are not detected (HPA: High; HPA: Not detected). Use these as comparison tissues while retaining HPA's Uncertain tissue-IHC rating (HPA: Uncertain).
Antibody validationBoth listed HPA IHC antibodies have an Uncertain IHC assessment (HPA: CAB004204; HPA: CAB080295). Interpret an isolated unusual pattern alongside cellular morphology and run controls; HPA does not establish target-specific fixation sensitivity (HPA: Uncertain).
Isoforms and epitope coverageUniProt lists two AKT2 isoforms (UniProt P31751). Without the antibody's epitope or isoform-reactivity information, their separate contributions to IHC staining cannot be assigned (UniProt P31751; general IHC practice).
Post-translational modificationUniProt annotates phosphorylation and glycosylation sites on AKT2 (UniProt P31751). These annotations alone cannot predict whether this antibody's staining changes with modification; that requires epitope-specific evidence (general IHC practice).
IF/ICC Q&A: where should signal appear?HPA reports enhanced cytosol and vesicle localization, with supported nucleoplasm staining in ICC-IF (HPA: subcellular). These IF observations inform localization, while paraffin-section IHC interpretation follows the tissue IHC profile (HPA: General cytoplasmic expression).
Why is my staining missing, weak or wrong?
SituationLikely causeNext action
Expected glandular cells are blank in a paraffin section (HPA: High).The staining run may have failed, or the section may be unsuitable (general IHC practice); HPA's Uncertain profile also limits prediction for an individual specimen (HPA: Uncertain).Check a same-run positive control, section integrity, and the IHC-validated antibody's stated retrieval and detection conditions (general IHC practice). Do not infer an AKT2-specific fixation effect without evidence.
Many compartments show uniform brown haze.Nonspecific binding, excess detection reagent, or residual endogenous enzyme activity can obscure cell-associated staining (general IHC practice).Review a no-primary control, verify blocking and wash steps, and adjust antibody or detection conditions within the validated IHC workflow (general IHC practice). Reassess the cytoplasmic pattern after background is controlled (HPA: General cytoplasmic expression).
Heart cardiomyocytes stain strongly (HPA: Not detected).Cross-reactivity or endogenous chromogenic activity is possible (general IHC practice); HPA's Uncertain IHC assessment prevents treating the mismatch as definitive (HPA: Uncertain).Confirm cell identity, compare no-primary and positive controls, and repeat with an independently validated AKT2 reagent if available (general IHC practice). Record the disagreement with HPA's cardiomyocyte observation (HPA: Not detected).
Signal is confined to extracellular material.That distribution does not match UniProt's intracellular and membrane-associated AKT2 locations (UniProt P31751). Tissue folds or reagent deposits can mimic localized staining (general IHC practice).Inspect the section at lower magnification for edge and fold effects; compare adjacent cells and a no-primary control (general IHC practice). Score intracellular signal separately (UniProt P31751).
Nuclear or membrane staining seems to replace cytoplasmic staining.Nuclear localization and lipid-dependent membrane recruitment are documented for AKT2 (UniProt P31751), although HPA's tissue IHC profile is generally cytoplasmic (HPA: General cytoplasmic expression).Record the cell type and compartment, compare controls, and avoid calling a documented compartment artifactual solely because it differs from the dominant HPA tissue pattern (UniProt P31751; HPA: General cytoplasmic expression).
Chromogen obscures cell boundaries or nuclear counterstain.Overdeveloped detection or an overly strong counterstain can prevent compartment scoring (general IHC practice).Repeat with controlled development and readable counterstaining, then score cell type, subcellular distribution, and intensity separately (general IHC practice). Compare with the same-run positive and no-primary controls (general IHC practice).

Sample controls for AKT2 IHC & IF

🧪Run breast first: glandular cells should stain (HPA: Breast glandular cells High). Run heart muscle as the negative tissue (HPA: Heart muscle cardiomyocytes Not detected); on the breast slide, nonglandular stromal cells should show only control-level background, but their AKT2-negative status requires validation.
Positive control tissue: Adrenal gland (Glandular cells, HPA High)
Negative control tissue: Heart muscle (HPA Not detected)
ICC-IF cell lines (HPA subcellular resource): HPA ICC-IF images show AKT2 in A-549, RT-4, U2OS, ASC52telo, RPTEC/TERT1, hTERT-RPE1 (serum starved), with annotated localisation: Vesicles (enhanced), Cytosol (enhanced) (HPA subcellular).
Technical controls: Include a no-primary (secondary-only) control, a matched rabbit IgG isotype control (selected PB9043 caption: rabbit primary), and AKT2-knockout tissue or cells as a biological negative. For the biotin-based DAB method, block endogenous peroxidase and assess endogenous biotin background on the breast section (selected PB9043 caption: SABC/DAB).
⚠️Feasibility: A target-specific fixation window or fixation effect is unreported, and the selected PB9043 paraffin-section caption does not state a fixative (selected PB9043 caption). That example uses heat retrieval in citrate buffer at pH 6 for 20 minutes; validate retrieval on the chosen tissues (selected PB9043 caption). The supplied evidence does not establish whether frozen sections or IF/ICC would be easier; on breast sections, distinguish glandular staining from biotin-related background using the controls (selected PB9043 caption: SABC/DAB).

HPA tissue IHC evidence for AKT2

Comprehensive Human Protein Atlas IHC scoring per tissue (reliability: Uncertain — Medium consistency between antibody staining and RNA expression data.). Rows are taken directly from the HPA tissue chart — click any row's HPA link to view the source.

Positive expression · recommended positive controls

TissueCell typeLevelEvidenceSource
Adrenal gland Glandular cells High Protein (IHC) HPA →
Breast Glandular cells High Protein (IHC) HPA →
Bronchus Ciliated cells (cell body) High Protein (IHC) HPA →
Caudate Glial cells High Protein (IHC) HPA →
Cerebellum Purkinje cells High Protein (IHC) HPA →

Undetected expression · recommended negative controls

TissueCell typeLevelEvidenceSource
Heart muscle Cardiomyocytes Not detected Protein (IHC) HPA →
Section 3

Advanced AKT2 IHC Tips

Use the catalog antibody’s paraffin-section IHC conditions as a starting point, and interpret staining alongside the reported AKT2 localisation and tissue patterns (datasheet PB9043; UniProt P31751; HPA tissue IHC).

What should I change if AKT2 staining is weak after antigen retrieval?
Start with heat-mediated retrieval in citrate buffer at pH 6 for 20 minutes (datasheet PB9043). The selected paraffin-section example then used 1 µg/ml primary antibody overnight at 4°C, so check those conditions before changing retrieval (datasheet PB9043). Compare a known positive tissue and a no-primary control in the same run, while keeping section thickness, heating, cooling, and detection consistent (standard IHC practice; HPA tissue IHC: high staining in adrenal glandular cells). If staining remains weak, test an alternative retrieval buffer on adjacent sections as a controlled fallback, because retrieval changes can alter background and tissue morphology (standard IHC practice).
Can the paraffin-section example tell me which fixation preserves AKT2 staining?
No fixative is stated for the selected paraffin-section image, so target-specific fixation sensitivity is unknown (datasheet PB9043 caption). Record the fixative, fixation duration, processing schedule, and section age for each case before comparing stain intensity (standard IHC practice). If establishing a workflow, use consistently processed sections and compare candidate fixation conditions with the same citrate pH 6, 20-minute retrieval and detection run (standard IHC practice; datasheet PB9043). Include a positive tissue control and a no-primary control; differences between conditions need replication before they can be assigned to fixation rather than processing or staining variation (standard IHC practice).
Is nuclear or membrane-associated AKT2 staining plausible in IHC?
Cytoplasmic staining is a reasonable starting expectation, while nuclear and cell-membrane localisation are also reported for AKT2 (HPA tissue IHC: general cytoplasmic expression; UniProt P31751 subcellular location). AKT2 has no transmembrane segment, and its PH domain can recruit it to the plasma membrane through phosphoinositide binding (UniProt P31751 topology and subcellular location). Nuclear localisation can vary with cellular state, as reported for primary myoblasts, so a nuclear signal alone does not establish an artefact (UniProt P31751 subcellular location). Score cytoplasmic, nuclear, and membrane-associated DAB separately, then check the cell type, tissue morphology, and controls before assigning biological meaning (standard IHC practice).
How can I tell whether this antibody distinguishes AKT2 isoforms or other AKT proteins?
AKT2 has 2 annotated isoforms and is closely related to AKT1 and AKT3, making epitope placement important for specificity claims (UniProt P31751 isoforms and function). Its PH domain spans residues 5–108, kinase domain 152–409, and AGC kinase C-terminal region 410–481 (UniProt P31751 domains). The supplied caption gives the staining conditions but no epitope sequence or isoform-specific validation, so IHC staining cannot establish which AKT2 isoform was detected (datasheet PB9043 caption). Obtain epitope and cross-reactivity documentation, then assess tissue staining against appropriate biological controls before reporting isoform or AKT2-specific conclusions (standard IHC validation practice).
How should I adapt this IHC result when planning AKT2 immunofluorescence?
Treat IF as a separate validation: the selected evidence describes chromogenic staining of paraffin sections, with citrate pH 6 retrieval and DAB detection (datasheet PB9043). For multiplex IF, pair AKT2 with a marker identifying the expected cell type, such as a validated ciliated-cell marker when examining bronchus, and assess channel overlap at cellular resolution (HPA tissue IHC: high in bronchial ciliated cells; standard IF practice). Choose spectrally separated fluorophores after checking tissue autofluorescence, often reserving a longer-wavelength channel for the weaker signal (standard IF practice). Because AKT2 is intracellular and has no transmembrane segment, optimise permeabilisation for access to cytosolic and nuclear epitopes and verify compartment patterns with controls (UniProt P31751 topology and subcellular location; standard IF practice).
What should I check when AKT2 DAB staining looks diffusely brown?
Run a no-primary control through the same secondary, avidin-biotin complex, and DAB steps to locate detection-system background (standard IHC practice; datasheet PB9043 detection method). The selected example used 10% goat serum block, biotinylated goat anti-rabbit secondary, and streptavidin-biotin complex, so check blocking and nonspecific secondary binding when background rises (datasheet PB9043). Include an endogenous-peroxidase block and evaluate whether endogenous biotin contributes to staining in the avidin-biotin workflow (standard chromogenic IHC practice). Compare intact cells with damaged tissue and section edges, and adjust washes or antibody concentration using a positive control before calling diffuse brown signal AKT2 (standard IHC practice).
How should I quantify AKT2 staining across paraffin sections? ⚠ ANSWER MARKED FOR VERIFICATION
Define the cell population and compartment before scoring, because AKT2 can be cytoplasmic, nuclear, or membrane-associated (UniProt P31751 subcellular location). An H-score combines the percentage of cells at intensity levels 0–3 into a 0–300 score; alternatively report percentage positive cells or positive-cell density per mm² of viable tissue (standard IHC scoring practice). Normalise counts to the number of eligible cells or viable tissue area, and keep retrieval, detection, imaging, and thresholds fixed across cases (standard IHC practice). Report compartments separately and use the same positive control across runs, since the available HPA tissue-IHC reliability is uncertain (standard IHC practice; HPA tissue IHC: Uncertain).
How do I distinguish credible AKT2 staining from tissue or detection artefacts?
Credible staining should localise to intact cells in a plausible cytoplasmic, nuclear, or membrane-associated pattern and reproduce in a suitable positive control (UniProt P31751 subcellular location; standard IHC practice). Compare the stained cell type with tissue architecture: high AKT2 staining is reported in adrenal glandular cells, whereas cardiomyocytes were reported as not detected (HPA tissue IHC). Treat staining confined to cut edges, necrotic areas, or extracellular deposits cautiously, and inspect the no-primary control for endogenous-enzyme or detection background (standard IHC practice). HPA rates tissue-IHC reliability as uncertain, so compartment and intensity differences alone should not be taken as proof of AKT2 activity or isoform identity (HPA tissue IHC: Uncertain; UniProt P31751 isoforms).
Boster reagents

Best AKT2 / RAC-beta serine/threonine-protein kinase IHC Antibodies

Anti-AKT2 antibodies have IHC images from paraffin-embedded human tissue and a frozen rat section (PB9043 image captions), plus IF images from human MCF7 and HeLa cells (M00725-1 and M00725-3 image captions).

Real IHC data IHC analysis of AKT2 using anti-AKT2 antibody (PB9043). AKT2 was detected in paraffin-embedded section of human lung cancer tissues. Heat mediated antigen retrieval was performed in citrate buffer (pH6, epitope retrieval solution) for 20 mins. The tissue section was blocked with 10% goat serum. The tissue section was then incubated with 1μg/ml rabbit anti-AKT2 Antibody (PB9043) overnight at 4°C. Biotinylated goat anti-rabbit IgG was used as secondary antibody and incubated for 30 minutes at 37°C. The tissue section was developed using Strepavidin-Biotin-Complex (SABC)(Catalog # SA1022) with DAB as the chromogen.
Anti-AKT2 Antibody ®
Cat # PB9043
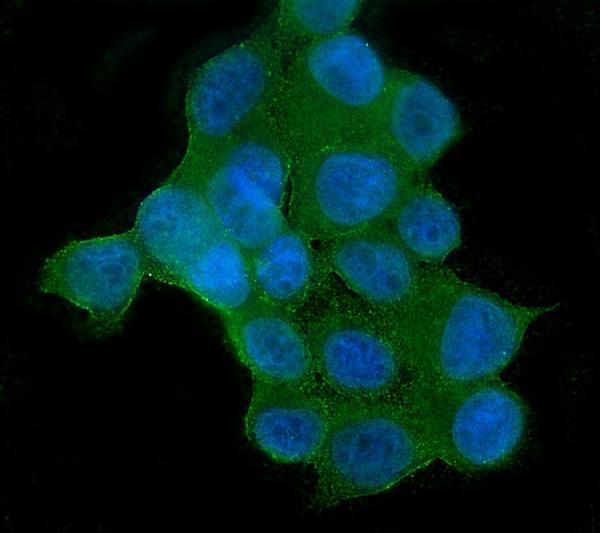
Real IF data IF analysis of AKT2 using anti-AKT2 antibody (M00725-1). AKT2 was detected in immunocytochemical section of MCF7 cells. Enzyme antigen retrieval was performed using IHC enzyme antigen retrieval reagent (AR0022) for 15 mins. The cells were blocked with 10% goat serum. And then incubated with 2μg/mL mouse anti-AKT2 Antibody (M00725-1) overnight at 4°C. DyLight®488 Conjugated Goat Anti-Mouse IgG (BA1126) was used as secondary antibody at 1:100 dilution and incubated for 30 minutes at 37°C. The section was counterstained with DAPI. Visualize using a fluorescence microscope and filter sets appropriate for the label used.
Anti-AKT2 Antibody ® (monoclonal, 10C6)
Cat # M00725-1
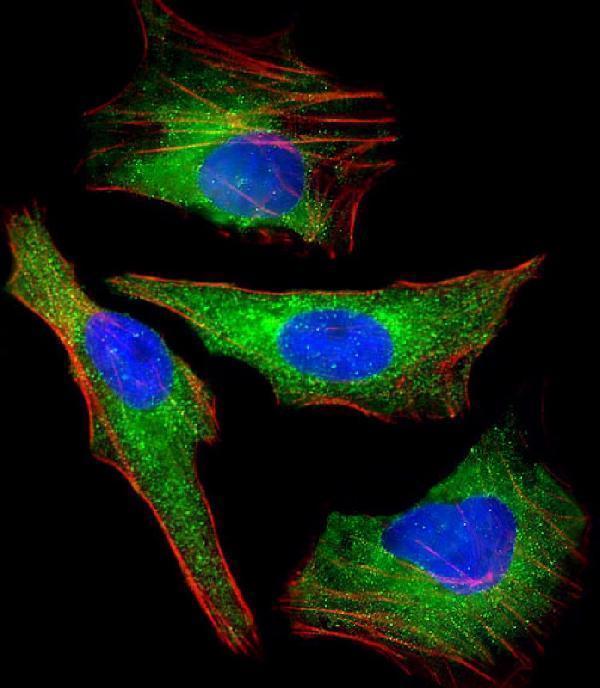
Real IF data Immunofluorescent analysis of 4% paraformaldehyde-fixed, 0.1% Triton X-100 permeabilized HeLa (human cervical epithelial adenocarcinoma cell line) cells labeling AKT2 with M00725-3 at 1/25 dilution, followed by Dylight® 488-conjugated goat anti-mouse IgG secondary antibody at 1/200 dilution (green). Immunofluorescence image showing cytoplasm staining on HeLa cell line. Cytoplasmic actin is detected with Dylight® 554 Phalloidin at 1/100 dilution (red).The nuclear counter stain is DAPI (blue).
Anti-AKT2 Antibody
Cat # M00725-3

PB9043 is listed for IHC and has images from paraffin-embedded human lung and intestinal cancer tissue and frozen rat brain tissue (catalog applications; PB9043 image captions); M00725-1 is listed for IF/ICC and has an MCF7 cell IF image (catalog applications; M00725-1 image caption). M00725-3 is listed for IF, with human and rat reactivity and an IF image from human HeLa cells (catalog applications/reactivity; M00725-3 image caption).

Which to pick: Choose PB9043 for paraffin-section human tissue IHC: its caption documents citrate retrieval at pH 6 for 20 minutes and primary antibody at 1 μg/ml overnight at 4 °C; the fixative is unreported (PB9043 image caption). For human cell IF/ICC, choose mouse monoclonal M00725-1 for its IF/ICC listing and MCF7 image, or mouse monoclonal M00725-3 for its IF listing and HeLa image (catalog host/applications; M00725-1 and M00725-3 image captions). For cross-species tissue IHC, PB9043 lists human, mouse and rat reactivity, with paraffin-section images for human tissue and a frozen-section image for rat tissue (catalog reactivity; PB9043 image captions).

Each figure is that product's own IHC / IF validation image from its datasheet.

References

  1. UniProt Consortium. UniProt entry P31751 (AKT2_HUMAN, RAC-beta serine/threonine-protein kinase).
  2. Human Protein Atlas. AKT2 tissue IHC expression (reliability: Uncertain).
  3. Human Protein Atlas. AKT2 subcellular location (ICC-IF): Mainly localized to vesicles and cytosol. In addition localized to the nucleoplasm..
  4. Human Protein Atlas. AKT2 antibody validation summary (4 antibodies).
  5. Potential of AKT2 expression as a predictor of lymph-node metastasis in invasive breast carcinoma of no special type. Journal of pathology and translational medicine 2021 — PMC8353139.
  6. Vav1 Selectively Down-Regulates Akt2 through miR-29b in Certain Breast Tumors with Triple Negative Phenotype. Journal of personalized medicine 2022 — PMC9224635.
  7. Akt2 regulates metastatic potential in neuroblastoma. PloS one 2013 — PMC3582607.
  8. Human Papillomaviruses, p16INK4a and Akt expression in basal cell carcinoma. Journal of experimental & clinical cancer research : CR 2011 — PMC3271997.
  9. PubMed PMID:1801921 — UniProt-cited evidence.
  10. PubMed PMID:1409633 — UniProt-cited evidence.
  11. PubMed PMID:14702039 — UniProt-cited evidence.